
Funny ICD-10 codes exist because ICD-10-CM is built to be extremely specific, and that same specificity is what every biller has to get right on real claims. Odd external-cause entries, such as a spacecraft collision code, are a handy way to learn how 7th characters, placeholder X characters and full-length codes decide whether a code is valid.
Lists of funny ICD-10 codes circulate every year, usually with a joke attached and no code year or official source. This guide skips the jokes and keeps the useful part: what the unusual entries reveal about how the code set works, and which rules a coder or practice manager can apply to everyday claims.
Only codes and rules that could be checked against CMS or CDC material are used below. For the wider picture of how diagnosis, procedure and supply codes fit together, start with our overview of CPT, ICD-10 and HCPCS codes explained.
Key takeaways
- Odd-sounding ICD-10-CM entries exist because the classification describes how, where and when an injury happened, not only what the injury is.
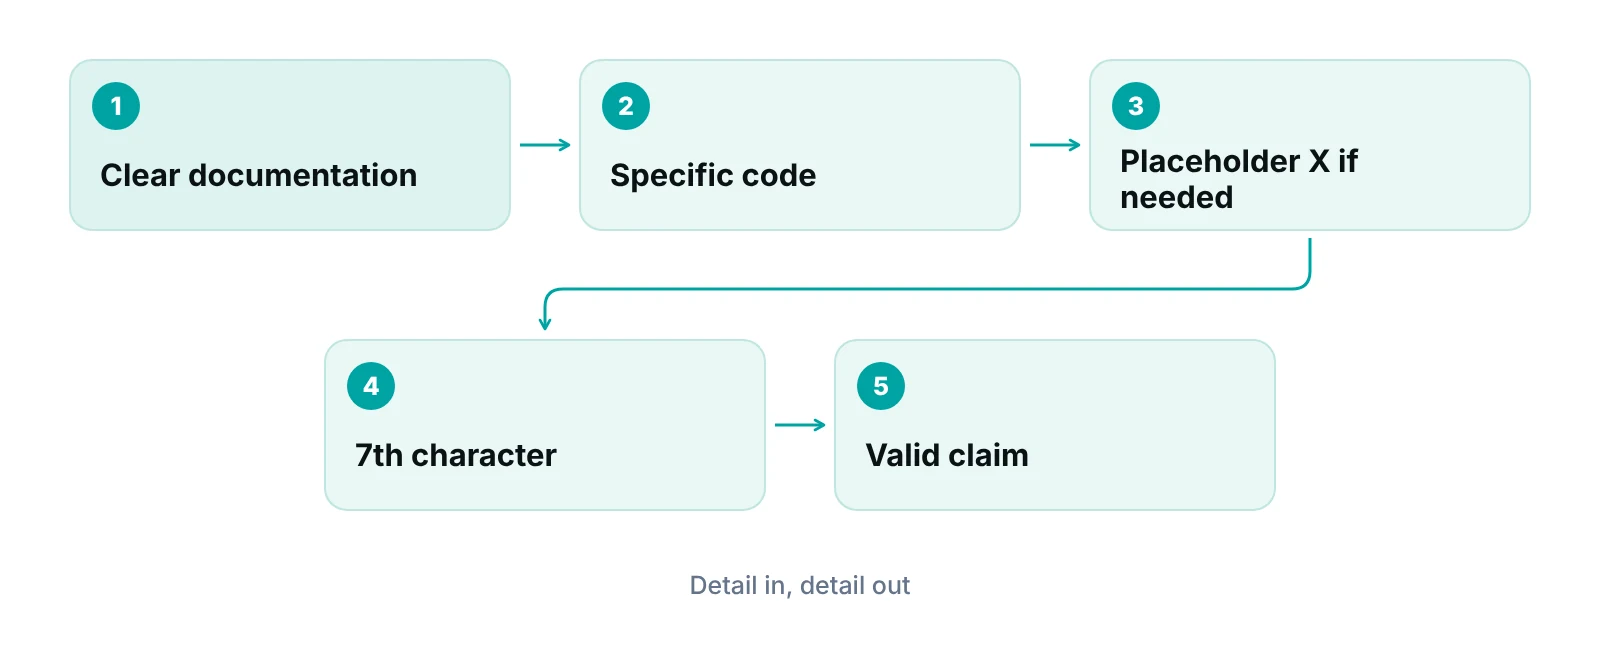
- A code that requires a 7th character is invalid without it, and a placeholder X must fill any empty positions first.
- The 7th character A, D or S tells the payer whether care is active treatment, healing-phase follow-up or a late effect, so the note has to support it.
- CMS says there is no national requirement to report external-cause codes, but a state or payer may require them, so check each payer’s policy.
- Any list of unusual codes is only as reliable as its code year: confirm each entry in the current CDC or CMS files before using it.
Why do funny ICD-10 codes exist at all?
ICD-10-CM is a diagnosis classification with a large chapter for external causes of morbidity (Chapter 20). Instead of recording only that a patient was injured, the code set can record what caused the injury, where it happened and what the patient was doing. That level of detail is why the code set contains entries that sound surprising when read out of context.
A good example is the transport section of the external-cause index. The CMS External Cause of Injuries Index lists a collision under spacecraft as V95.43, next to a separate entry for spacecraft at V95.40. Nobody expects a clinic to see that code often. It exists because the classification was designed to describe every category of event consistently, including very rare ones, so researchers and public health agencies can count them.
For a practice, the entertaining part is irrelevant and the structure is what matters. The same design that produces a rare code also produces the everyday codes for falls, animal bites and sports injuries that a family medicine, urgent care or orthopedic office submits weekly. If you understand why the rare codes are built the way they are, the common ones become easier to code correctly.
What do verified unusual codes show about coding?
The table below uses only entries that appear in CMS material fetched for this review. They are not the funniest codes online. They were chosen because each one demonstrates a rule that affects ordinary claims. The spacecraft collision entry comes from the CMS index, and the other three come from CMS coding training material that uses them as worked examples.
| Code | What it is | Rule it illustrates |
|---|---|---|
| V95.43 | Spacecraft collision entry in the External Cause of Injuries Index | External-cause chapter covers rare events as well as common ones |
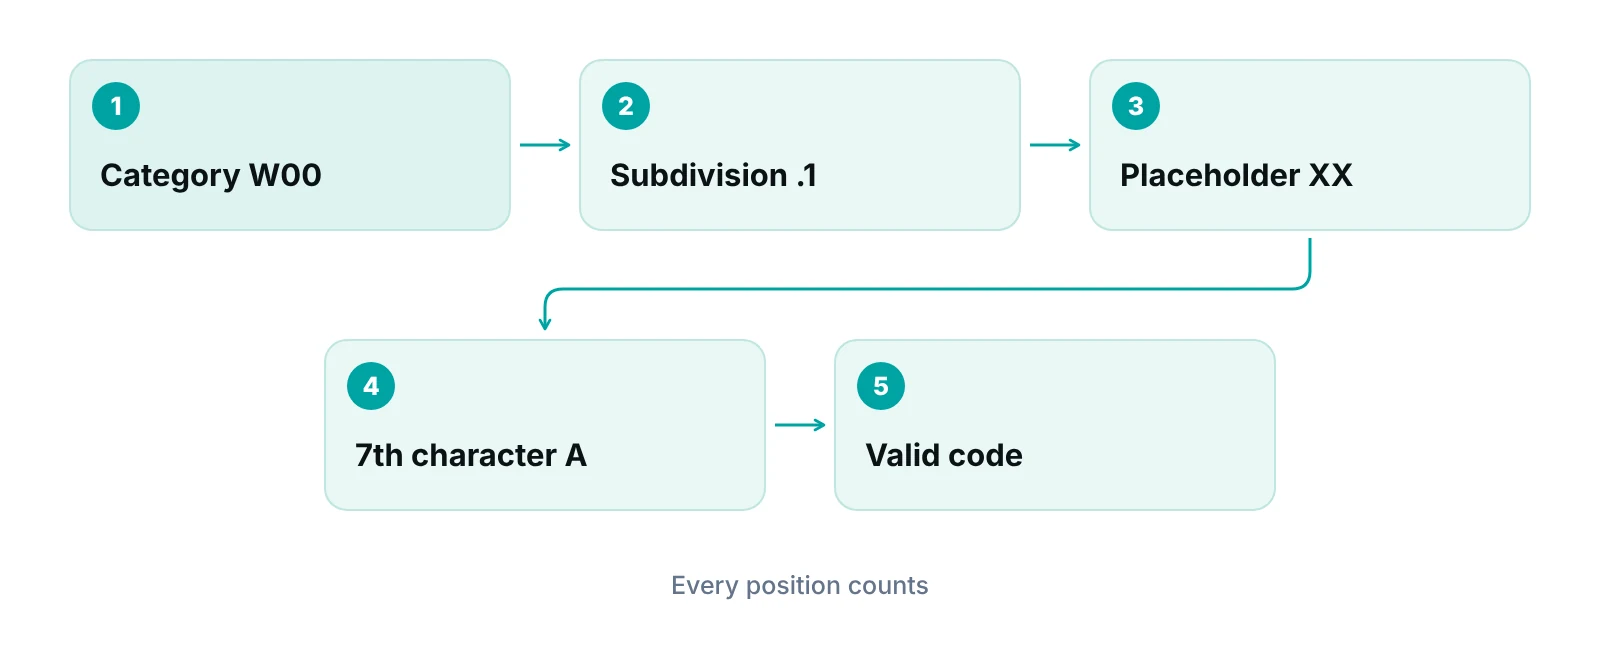
| W00.1XXA | Fall from stairs and steps due to ice and snow, initial encounter | Placeholder X characters fill empty positions so the 7th character can be added |
| T15.02XD | Foreign body in cornea, left eye, subsequent encounter | D marks a subsequent encounter, and laterality is part of the code |
| T46.1X5A | Adverse effect of calcium-channel blockers, initial encounter | A code with a placeholder X is only valid when the X is present |
Source: CMS ICD-10-CM web-based training text and CMS ICD-10 basics slides (undated training material); CMS External Cause of Injuries Index (2020 edition). Code titles and validity can change by fiscal year.
Why some popular funny codes are missing here
Many roundups repeat the same dozen codes, and some of them are copied from older lists. Several widely shared entries could not be confirmed in an official CDC or CMS file during this review, so they are left out rather than repeated. If you want to use any unusual code in training material, look it up in the CDC ICD-10-CM files for the current fiscal year first.
A second lesson sits in the year labels. FY2027 ICD-10-CM codes took effect on October 1, 2026, and CMS lists a separate set of files for the April 1, 2026 update within FY2026. A code that was valid on one list can be split, revised or deleted on the next, which is why a code table without a year is a risk even when it was accurate once.
What do the A, D and S at the end of a code mean?
In the injury and external-cause chapters, the 7th character tells the payer where the patient is in the course of care. CMS training material describes it as classifying an initial encounter, a subsequent encounter or a sequela, which is a late effect. It is a coding character, but the information behind it has to come from the clinician’s note.
| 7th character | Meaning | What the note should make clear |
|---|---|---|
| A | Initial encounter: the patient is receiving active treatment for the condition | That this visit is part of active treatment |
| D | Subsequent encounter: care after active treatment, such as aftercare during healing | That this is follow-up care and the condition is being monitored or healing |
| S | Sequela: a late effect of the original injury | The current problem and its link to the earlier injury |
Source: CMS ICD-10 basics slides and CMS ICD-10-CM web-based training text (undated training material).
Two practical points follow from the CMS material. First, for injury aftercare, the instruction is to assign the acute injury code with the 7th character for a subsequent encounter, not a separate aftercare code. Second, CMS states there is no time limit on when a sequela code can be used. A common mistake is to treat the 7th character as a visit counter. It describes the type of care, not how many visits have occurred.
The same logic explains why follow-up visits for an injury deserve their own check. Our guide to follow-up ICD-10 codes walks through how diagnosis choices change after the first visit, and the ICD-10 codes for dog bites and ICD-10 codes for ground-level falls show the external-cause pairings that urgent care and primary care teams meet most often.
Why does a placeholder X make or break a code?
Some codes have fewer than six characters before the 7th character is added. In those cases the empty positions are filled with an X. The FY2027 Official Guidelines state it directly: if a code that requires a 7th character is not 6 characters, a placeholder X must be used to fill in the empty characters. They also say a code with an applicable 7th character is considered invalid without it.
That is why the worked example W00.1XXA looks odd to a newcomer. The two X characters are not decoration. They hold the fifth and sixth positions open so the A can sit in the seventh position. Leave them out, or type a code by hand and drop the 7th character, and the code is not valid for the date of service regardless of how accurate the diagnosis is.
“A code is only as good as the weakest character in it. The category can be right and the claim can still fail on the 7th position.”
The guidelines also set the standard for how far to take a code: diagnosis codes are to be reported at their highest number of characters available and to the highest level of specificity documented in the medical record, and a three-character code is used only if it is not further subdivided. In practice, that means a parent category should never be the code a team settles for when a more specific one exists.
Are external-cause codes required on every claim?
Not nationally. CMS training material states there is no national requirement for mandatory ICD-10-CM external-cause code reporting, and encourages providers to report them voluntarily because they support injury research. The same material notes that a state or payer may have its own requirements, which is why a payer-by-payer check matters.
There is one firm sequencing rule to know. The FY2027 Official Guidelines state that external-cause of morbidity codes are never to be recorded as a principal diagnosis. They describe how or why something happened, so they accompany a diagnosis that describes the condition being treated. A template that treats the external-cause code as enough on its own is set up to create a problem.
For specialties that see many injuries, such as the practices on our urgent care billing and revenue cycle page, the question is less about whether to report these codes and more about reporting them consistently, so the data a payer sees for one patient looks the same as for the next. Consistency is easier to maintain with a written rule, a short template prompt and a regular audit than by relying on memory.
Where does specificity break down on real claims?
Specificity problems rarely look dramatic. They show up as a missing character, a template that offers a parent code, or a note that does not say which kind of visit occurred. The table below connects each pattern to a rule from the guidelines and a prevention step a practice can adopt.
| Specificity error | Rule behind it | Prevention step |
|---|---|---|
| 7th character left off a code that requires one | A code with an applicable 7th character is invalid without it | Use validated code pick-lists instead of free-text entry |
| Placeholder X dropped or misplaced | Placeholder X must fill empty positions before the 7th character | Run a claim edit that flags any injury code shorter than seven characters |
| Parent category used when a more specific code exists | Codes are reported at the highest number of characters available | Remove parent categories from superbills and favorites lists |
| External-cause code sent without a condition code | External-cause codes are never a principal diagnosis | Require a condition diagnosis whenever an external-cause code is present |
| A, D or S chosen without support in the note | The 7th character classifies the type of care | Add a visit-type prompt to injury templates |
| Old code used after the annual update | Code sets change each fiscal year | Review templates and favorites lists each October |
Source: ICD-10-CM Official Guidelines for Coding and Reporting, FY2027 (CDC/NCHS); CMS ICD-10 training material. Prevention steps are general practice suggestions.
When a payer cannot match a claim to its edits, the common outcome is a rejection or a request for more information. Our guide to CO-16 missing-information denials explains what that denial type looks like and how teams respond to it. The point to take from the table is that most of these failures are preventable before the claim leaves the building, because they come from templates and data entry rather than clinical judgment.
A fast self-check
Pull ten recent injury claims and, for each, confirm three things: the code has seven characters if it requires them, the 7th character matches the type of visit in the note, and a condition code accompanies any external-cause code. Ten claims is enough to show whether a template problem exists.
Curious how specificity affects your own denials?
A free practice audit looks at how your claims move from the visit note to payment and where coding and data gaps begin. Pricing, if you decide to go further, is quoted after the audit.
How should a practice handle annual code changes?
The ICD-10-CM code set is revised on a fixed schedule. CMS shows the FY2027 files, effective for discharges and encounters from October 1, 2026 through September 30, 2027, along with a guidelines document for the same year. It also lists a separate April 1, 2026 file set inside FY2026. The CMS page does not publish a count of new, revised or deleted codes, so this post does not quote one.
The workable approach is a standing annual task rather than a memory exercise. Each October, someone confirms the favorites list, superbill, problem-list mappings and any hard-coded claim edits against the new files. Any template that surfaces a code retired or split in the update becomes a source of rejections until it is fixed.
A short internal audit helps too. Sample recent injury claims, score the code length, the 7th character and the supporting note, and track the result by month. That makes the quality of external-cause and injury coding measurable instead of anecdotal. If your team lacks capacity for this, medical billing services can support coding review and claim checks as part of the billing workflow.
Our recommendations
- Remove parent categories from templates. We recommend reviewing superbills, favorites lists and problem-list mappings so that codes with a more specific subdivision no longer appear as choices.
- Add a visit-type prompt to injury notes. A one-line field that asks whether the visit is active treatment, follow-up during healing or a late effect gives the coder what is needed to choose A, D or S.
- Validate length before submission. Set a claim edit that flags any injury or external-cause code shorter than seven characters when a 7th character applies, so placeholder X errors are caught before the payer sees them.
- Check each payer's external-cause policy. Because there is no national mandate, record which payers and states ask for these codes and make the template behave the same way each time.
- Re-check templates every October. Treat the annual update as a scheduled task with an owner, and confirm each code on a favorites list against the current CDC or CMS files.
Bottom line
Funny ICD-10 codes are a reminder that the code set rewards detail: the same 7th character and placeholder X rules that shape a spacecraft collision entry shape every injury claim a practice submits. Teams that treat specificity as a system to audit, not a trivia list, send cleaner claims. If you would like help turning that into a workflow, see our medical billing services and denial management services, or start with CPT, ICD-10 and HCPCS codes explained. To size what rework costs your practice, try the revenue calculator or talk to our team.
Frequently asked questions
Are funny ICD-10 codes real?
Many unusual codes are real entries, such as the spacecraft collision entry V95.43 in the CMS External Cause of Injuries Index. Others on viral lists are copied from older code years or cannot be confirmed in official files, so check any code in the current CDC or CMS release before using it.
Why does ICD-10 have such specific codes?
The external-cause chapter is designed to describe how, where and under what circumstances an injury happened. That detail supports research and tracking, and it is why rare events have their own entries. For a practice, the practical effect is that the code set keeps adding precision, so documentation and templates need periodic review to keep up.
What does the 7th character in an ICD-10 code mean?
In injury and external-cause codes, the 7th character classifies the encounter as initial (A), subsequent (D) or sequela (S). The clinician’s note has to support the type of care that the character represents, so a coder does not have to guess between a first visit, a follow-up and a late effect. When the note is unclear, the usual remedy is a query to the clinician before the claim is sent.
What is a placeholder X in ICD-10-CM?
It is an X used to fill empty positions in a code shorter than six characters so a required 7th character can sit in the seventh position. The FY2027 Official Guidelines say it must be used, and a code that needs a 7th character is invalid without one.
Do I have to report external-cause codes?
CMS training material says there is no national requirement for mandatory external-cause code reporting, and it encourages voluntary reporting. A state or payer can still require them, so check each payer’s policy. Whatever the policy, the code should only be reported when it is supported by the documentation, and it should accompany a code for the condition being treated.
Can an external-cause code be the primary diagnosis?
No. The FY2027 Official Guidelines state external-cause of morbidity codes are never to be recorded as a principal diagnosis. They accompany a code that describes the condition being treated.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- ICD-10-CM Official Guidelines for Coding and Reporting, FY2027 (October 1, 2026) — CDC / NCHS (2026)
- ICD-10 Codes (CMS coding and billing page) — CMS (2026)
- Comprehensive Listing of ICD-10-CM Files — CDC / NCHS (2026)
- Diagnosis Coding: Using the ICD-10-CM (web-based training text) — CMS (n.d.)
- ICD-10 Basics slides — CMS National Provider Call (2014)
- ICD-10-CM External Cause of Injuries Index (2020) — CMS (2020)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. Code titles, validity and payer rules change by fiscal year and vary by payer and state. Verify each code in the current CDC or CMS ICD-10-CM files and confirm requirements with your payers and qualified advisers before you act.
