

Medical billing service pricing usually follows one of four models: a percentage of collections, a flat monthly fee, a per-claim fee, or hourly staff. The model matters less than what the fee covers, what is billed on top, and how results are measured. We quote only after a free audit.
Most pricing pages give you a range and stop. That is the easy part. The costly surprises are the fees that sit outside the base rate, a contract that is vague about scope, and quotes that cannot be compared because each uses different terms. This guide explains how each fee model is built, which fees to ask about, and how to put two quotes side by side using your own claim data. If you are choosing between vendors, our ten questions to ask before hiring a medical billing company is the companion checklist.
Key takeaways
- Four fee models cover most contracts: percentage of collections, flat fee, per-claim fee and hourly or dedicated staff. Each rewards different behavior.
- HHS OIG has said percentage billing may increase the risk of upcoding, so ask what review sits around that model.
- The base rate is only part of the bill. Ask about clearinghouse, statement, resubmission, onboarding, minimum and exit charges before you sign.
- Compare quotes on total cost against cash collected, using written metric definitions such as HFMA’s Cost to Collect.
- We do not publish price ranges because we found no independent survey behind the figures online. Real quotes depend on your specialty, volume and scope.
How is medical billing service pricing structured?
Most contracts use one of four models, or a mix: a percentage of collections, a flat monthly fee, a fee per claim, or hourly or dedicated staff. Each one rewards a different behavior, so the model changes what your billing company is paid to care about.
| Fee model | How the fee is set | What it rewards | Check before you sign |
|---|---|---|---|
| Percentage of collections | A share of the money collected for your claims. | Collecting more. | Which payments count, how reversed payments are treated, and what review guards against upcoding. |
| Flat monthly fee | A fixed fee for a defined scope. | Staying inside the scope. | What claim volume it covers and what counts as out-of-scope work. |
| Per-claim fee | A charge for each claim handled. | Handling more claims. | Whether resubmissions and appeals count as new claims. |
| Hourly or dedicated staff | You pay for time, or for a named person. | Time spent. | How hours are reported and who is accountable for quality. |
| Hybrid | A base fee plus a smaller variable fee. | A mix, depending on the split. | How the variable part is capped and measured. |
Source: HHS OIG, Compliance Program Guidance for Third-Party Medical Billing Companies (63 Fed. Reg., Dec. 18, 1998), on percentage billing. The other columns are RCM Finder’s practical checks.
Percentage pay gets the most scrutiny. In its 1998 guidance for billing companies, HHS OIG said percentage billing arrangements may increase the risk of upcoding, and that coders should not be paid in a way that creates an incentive to upcode. A law-firm summary adds that OIG has also flagged percentage-based pay under the federal anti-kickback statute and that state rules differ (Wilson Sonsini, a secondary source). None of this bans the model. It means you should ask what coding review sits around it and have counsel read the fee clause.
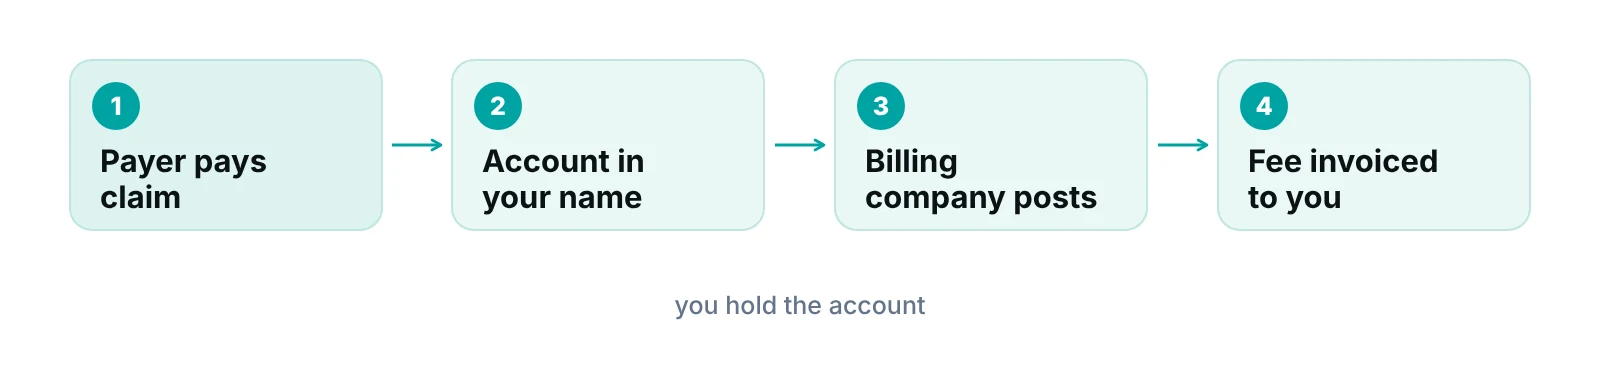
There is also a Medicare payment rule. Under 42 CFR 424.73, payment to a billing agent is always made in the provider’s name, and Medicare may pay an agent only under conditions that include pay that is not related in any way to the dollar amounts billed or collected. That condition applies to an agent that receives payment for you. If payers deposit into an account in your practice’s name, it is not in play, which is one reason to ask where the money lands. Your counsel can confirm how it applies to your contract.
What decides the price you are quoted?
Five things move a quote: how many claims you send, your specialty and payer mix, how much of the revenue cycle you hand over, how hard your claims are to get paid, and the systems involved. We did not find an independent, dated survey for billing prices, so we do not print a price or percentage range here. Any range without a method and year is a guess, and your own numbers matter more.
- Claim volume: more claims mean more work, but a larger practice may negotiate a different rate or model.
- Specialty and payer mix: procedure-heavy or authorization-heavy specialties need more checking per claim. See the specialties we support for how billing patterns differ.
- Scope: claim submission and payment posting alone is a smaller job than eligibility checks, coding support, denial appeals and A/R follow-up.
- Claim difficulty: a high denial rate or old A/R means extra work, and some vendors price it separately.
- Systems: whether the vendor works inside your EHR or practice management system, or asks you to change software.
Scope is where quotes drift apart most. Some vendors bundle only claim submission, while others cover the full cycle. Our medical billing services cover billing, claims, charge entry and coding support, and we price them by scope after reviewing your claims. Ask every vendor to list what is in and what is out, in writing.
Which fees sit outside the base price?
Ask for a full fee schedule, not just the headline rate. The charges below are the ones that most often appear outside the base fee. Whether any apply to you depends on the contract, so ask about each by name.
| Item | Why it can add cost | Question to ask |
|---|---|---|
| Clearinghouse or transaction charges | Claims, eligibility checks and remittances often pass through a clearinghouse. | Who pays these, and are they passed through at cost? |
| Patient statements | Printing, mailing or portal delivery of balances. | Is statement handling included, and who sets the cadence? |
| Resubmissions and appeals | A denied claim must be corrected and sent again. | Does a resubmission or appeal count as a new claim or a new fee? |
| Onboarding or setup | Data transfer, payer setup and system access at the start. | Is there a one-time fee, and what does it include? |
| Monthly minimum | A floor on the fee when volume is low. | What is the minimum, and does it apply in slow months? |
| Software or EHR access | Seats, interfaces or reports that carry their own price. | Which tools are included and which are billed separately? |
| Credentialing and enrollment | Payer enrollment is often a separate service. | Is it in scope, or priced as its own project? |
| Exit and data export | Moving data out in a usable format at the end. | What does leaving cost, and in what format do I get my data? |
Source: RCM Finder practical checklist. No prices are stated because fees are set by each vendor’s contract.
Clearinghouse charges deserve their own read, because they sit between your claims and the payer. Our guide to clearinghouses in medical claims management explains what they do.
Ask who pays when a filing deadline is missed
Medicare generally denies a claim as untimely if it is received more than 12 months or one calendar year after the date of service, with four listed exceptions (CMS manual, Ch. 1, Sec. 70.4 and 70.7). Other payers set their own windows. Your contract should say who bears the loss when a vendor misses a deadline, and how it tracks each payer’s window.
How do you compare two billing quotes fairly?
Compare total cost against cash collected, using the same scope and the same definitions. A low rate on a narrow scope can cost more than a higher rate on a full one. HFMA’s MAP Keys give you a ready frame for this.
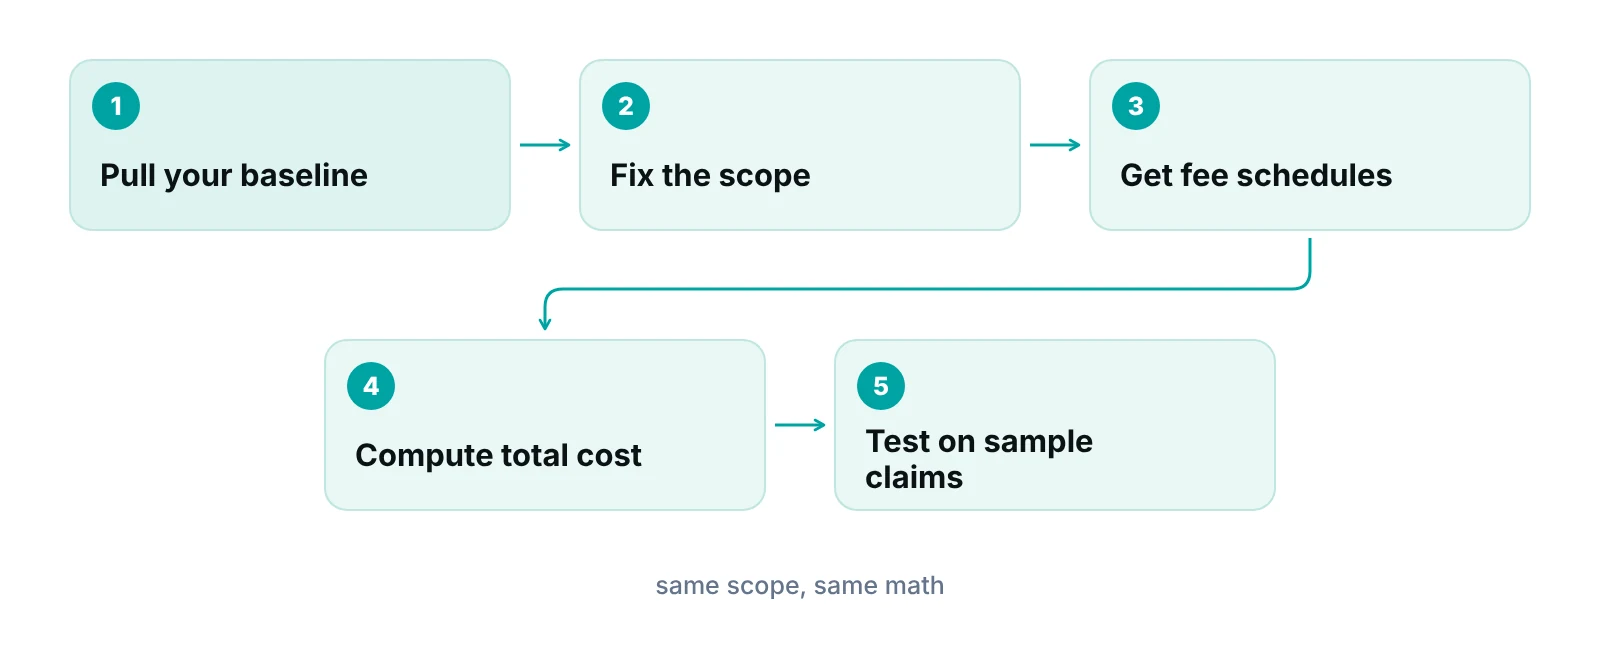
Start with Cost to Collect. HFMA defines it as total revenue cycle cost divided by total patient service cash collected, and its cost side counts items such as salaries and benefits, subscription fees, outsourced arrangements, software maintenance and transaction fees. Use the same idea for your quotes: add the base fee, every add-on and any software you still pay for, then divide by the cash you expect to collect.
| Measure | How HFMA defines it | Question for the vendor |
|---|---|---|
| Cost to Collect (FM-6) | Total revenue cycle cost divided by total patient service cash collected, net of refunds. | Which costs do you count: fees, software, our staff time? |
| Net Days in A/R (FM-1) | Net A/R divided by average daily net patient service revenue, using the most recent three-month average. | Do you report it this way every month? |
| Remittance Denial Rate (AR-5) | Claims denied divided by claims remitted, counting actionable denials that can be corrected and resubmitted. | Do you count appeal denials, and what do you exclude? |
Source: HFMA, MAP Keys: Indicators of Revenue Cycle Excellence, 2023 Edition.
Hospital-focused definitions need adapting for a small practice, but the structure holds: a named numerator, a named denominator and a time window. Our revenue cycle KPIs guide explains the wider set, and the revenue calculator can put a rough number on stalled A/R.
Curious what stalled A/R could be costing you?
Use our revenue calculator to put a rough number on open claims before you compare billing companies.
What should you count when weighing in-house against outsourced billing?
Count the full in-house cost, not just payroll. The same HFMA frame that you use for a vendor quote works for your own team, so the two sides are measured the same way.
- People: salaries, benefits, training, and cover for leave and turnover.
- Software: practice management or EHR billing modules, clearinghouse and reporting tools.
- Rework: time spent on denials, resubmissions and aging claims.
- Oversight: who reviews coding and who watches payer rules and deadlines.
- Outsourced side: the fee schedule from the table above, plus your own time managing the vendor.
If your volume is small, our guide to medical billing services for small practices covers fit by practice size. A hybrid is common: keep patient calls and charge capture in-house and hand claims follow-up to a vendor.
“A cheap quote on a narrow scope is not cheap. Price the whole cycle, then decide what to hand over.”
— Awais Afzal, Healthcare Operations & Data Analyst
What should the contract say besides the price?
It should say who does what, where the money goes, how patient data is protected and how you can leave. These terms decide whether a fair price stays fair.
- Written responsibilities: OIG recommends that compliance responsibilities be formalized in the written contract, including which functions the billing company owns and which stay with the provider. OIG also states that documentation is the provider’s responsibility.
- Business associate agreement: HHS lists billing and claims processing among business associate activities, and a written agreement is required before PHI is shared.
- Breach notice: a business associate must notify the covered entity no later than 60 calendar days after discovery of a breach. A contract can set a shorter time, and many practices ask for one.
- Claim review: OIG recommends at least an annual statistical sample of claims reviewed before and after submission by a qualified expert.
- Exit terms: HHS says the BAA must require the business associate to return or destroy PHI at termination where feasible. Add notice period, export format and transition help.
Our HIPAA compliance in medical billing guide goes deeper on the privacy side.
How do we handle pricing at RCM Finder?
We do not publish rates. We quote after a free practice audit, which reviews a sample of your claims, denials and A/R aging, so the quote reflects your scope and your volume. Our team works inside your existing EHR (for example PrognoCIS, eClinicalWorks or athenahealth), and we put a Business Associate Agreement in place before accessing patient data.
The audit also gives you a baseline to hold any vendor to, including us. Read the full fee schedule first, and ask us the same questions you would ask anyone else.
Want a baseline before you compare quotes?
Our free practice audit reviews a sample of your claims, denials and A/R aging, so you have numbers to hold any billing company to, including us. We quote after the audit.
Our recommendations
- Pull your numbers before you ask for a quote. We would gather 12 months of claims, remittances, denial reasons and A/R aging first. A quote is only comparable if every vendor prices the same volume and the same scope.
- Ask every vendor for a one-page fee schedule. Base fee, add-ons, pass-through charges, minimums and exit charges, all on one page. If it cannot fit on a page, the contract is hiding something.
- Name the metrics in the contract. Write down how net days in A/R, denial rate and cost to collect are defined and how often you receive them. Without definitions, a report is just a number.
- Keep payer deposits in your own account. Money flow decides who controls cash and who can see it. We would not sign anything that sends payer payments to an account you cannot see.
- Match the model to your risk. If you worry about upcoding, ask what review the vendor runs. If you worry about cost surprises, favor a fixed scope with a clear out-of-scope list. If you want shared upside, ask how a hybrid is capped.
- Test with a sample of your own claims. Ask the vendor to work a sample, including denials, before you commit. Judge the review you get back, not the demo.
Bottom line
The best-priced billing contract is the one you can read, compare and exit. Start with a clear scope and a one-page fee schedule, then measure total cost against cash collected. If you want that baseline, our free practice audit comes first, and the quote follows. You can also see how our end-to-end revenue cycle management service works, or reach us through the contact page.
Frequently asked questions
How much do medical billing services cost?
It depends on your specialty, claim volume, payer mix, scope of work and the fee model. We do not publish a range because we found no independent survey with a method and year behind the figures online. Ask each vendor for a written fee schedule, and we quote after a free practice audit.
Is a percentage of collections or a flat fee better?
Neither is better for every practice. A percentage ties the vendor’s pay to what is collected but needs review against upcoding risk. A flat fee is predictable but depends on a clear scope. Test each against your own claim volume and your risk tolerance before you choose.
What fees are not in the base price?
Common items are clearinghouse or transaction charges, patient statements, resubmissions and appeals, onboarding, software or EHR access, credentialing work, monthly minimums and exit charges. Ask for each by name and get the answer in the contract, not in a sales call.
Can a billing company be paid a percentage of Medicare collections?
It depends on the arrangement. 42 CFR 424.73 limits how Medicare can pay an agent that receives payment for you, and OIG has flagged percentage pay under the anti-kickback statute. State law varies as well. Have healthcare counsel review the fee clause before you sign.
Is outsourcing billing cheaper than doing it in-house?
Not automatically. Count the full in-house cost: salaries, benefits, software, training and rework, then compare it with the outsourced fee on the same basis. HFMA’s Cost to Collect is a good frame because it includes staff, software and outsourced fees against cash collected.
What should I check before I sign a billing contract?
Check scope, fee schedule, where payer deposits land, the business associate agreement, breach notice terms, reporting, and what happens when you leave, including data export and return or destruction of PHI. Our checklist of ten questions covers each one.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Compliance Program Guidance for Third-Party Medical Billing Companies, 63 Fed. Reg. (Dec. 18, 1998) — HHS Office of Inspector General / Federal Register (1998)
- 42 CFR 424.73 Prohibition of assignment of claims by suppliers — eCFR / Cornell LII (current)
- MAP Keys: Indicators of Revenue Cycle Excellence, 2023 Edition — HFMA (2023)
- Business Associates (HIPAA guidance) — HHS Office for Civil Rights (current)
- 45 CFR 164.410 Notification by a business associate — eCFR (current)
- FAQ 2082: ePHI retention after services end — HHS Office for Civil Rights (current)
- Medicare Claims Processing Manual transmittal 12909 (Pub. 100-04, Ch. 1, Sec. 70.4 and 70.7) — CMS (2024)
- Key Considerations for Contracting with Healthcare Revenue Cycle Management Companies — Wilson Sonsini (law firm; secondary source) (current)
Disclaimer: This article is general educational information for medical practices. It is not legal, tax, coding or compliance advice. Fee arrangements, payer rules and state law vary, and the rules cited here can change. Confirm requirements with qualified counsel and your payers before signing a contract.
