
Communication barriers in healthcare stall payment at four points: hand-offs between clinical staff and billing, provider queries, patient money conversations and language access. Each leaves a claim unbillable, a denial unexplained or a balance unpaid. Fix them by giving every hand-off a named owner and a written step.
Most writing on this topic is about the exam room. This post is about the other half: the conversations that happen after the visit, between your own staff and with the patient about money. Those are where a good clinical visit turns into a slow or unpaid claim. For the front-desk side, see our front desk and revenue cycle guide; for statement layout and timing, see the patient billing statements guide. Here we cover what sits between them.
Key takeaways
- Four gaps matter most for payment: clinical-to-billing hand-offs, provider queries, patient money conversations and language access.
- A hand-off with no named owner and no written definition of done is where claims wait.
- Language access is a legal duty for practices that receive HHS federal financial assistance, and it reaches billing and collections materials.
- Do not use a child or an untrained adult to interpret a billing conversation. The rule allows only narrow exceptions.
- You can fix most of this with a short written process. No new software is required, though tracking claims by stage helps.
Where do communication barriers show up in the revenue cycle?
They show up wherever information has to move from one person to another: clinical team to billing, billing to provider, and practice to patient. Each move can drop something, and a payer or a patient usually discovers the gap weeks later.
The table lists the five we see most. It is a working list from our operations experience, not a ranking, and we do not attach percentages to it because we have not found a primary source that measures these gaps across practices.
| Gap | What gets lost | What it does to payment | First fix |
|---|---|---|---|
| Clinical team to billing | Whether the visit is finished, signed and complete | Claims wait, or go out with missing services | Write a one-line definition of ‘encounter complete’ and a daily list of open encounters |
| Billing to provider (queries) | The exact question, the part of the note it refers to, the answer | Codes are guessed or the claim is held with no one watching | Use one query template with one question per query and a due date |
| Payer to clinical team (denials) | The denial reason, in plain words, and what to change | The same denial repeats every month | Send a short monthly list of top denial reasons to providers and the front desk |
| Practice to patient (money) | What the patient owes, why and by when | Balances age, patients call with questions, some pay late | Use plain-language estimates, statements and call scripts |
| Practice to patient with limited English | The same facts, in a language the patient can read or hear | Statements go unread, balances age, and the practice may miss a legal duty | Record language at registration and carry it to statements and calls |
Source: RCM Finder operations experience (a working list, not measured data).
What goes wrong between the clinical team and billing?
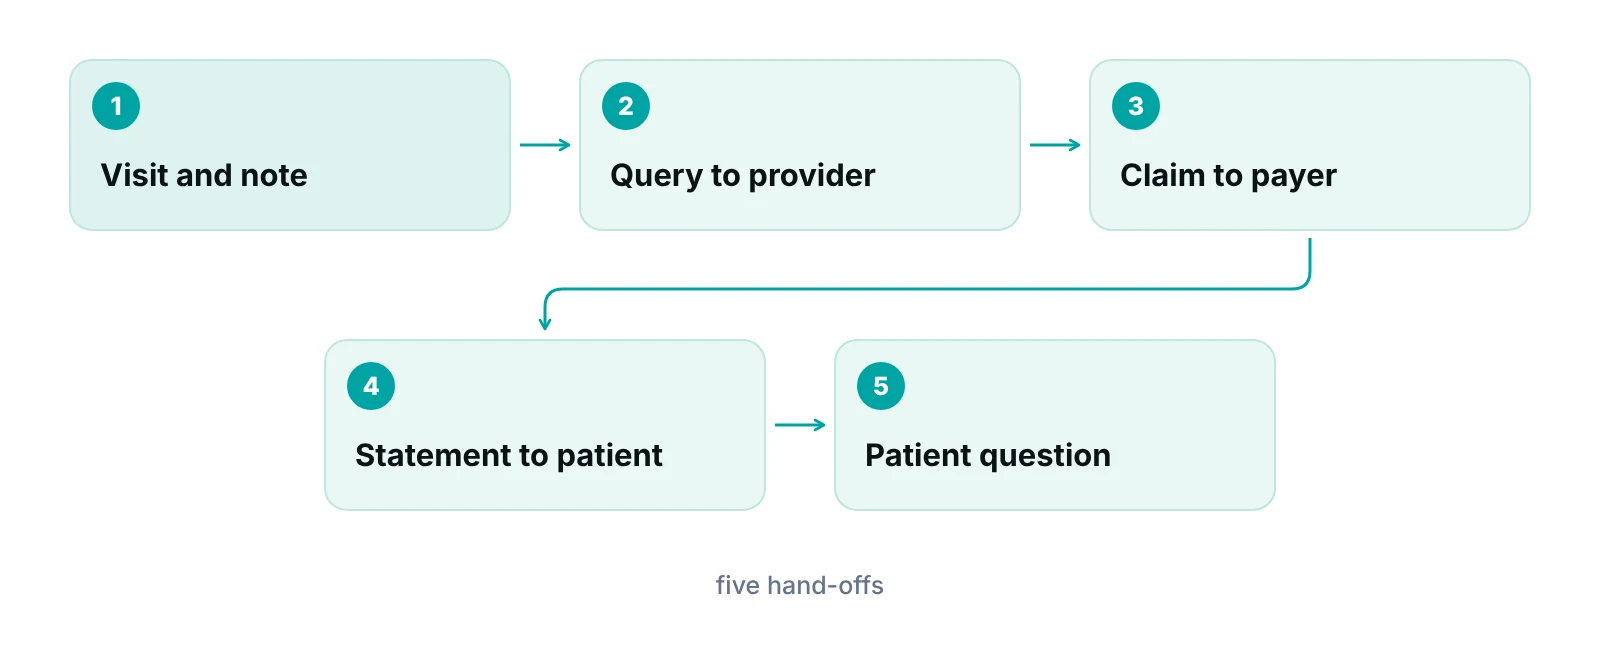
The usual failure is a hand-off with no owner. The clinical team believes the visit is done; billing does not know it exists, or knows it exists but cannot bill it. Nobody is wrong, and nobody is watching.
Three hand-offs that stall claims
- Encounter to charge. Unsigned notes, services done but not entered, or an authorization number that never reached billing.
- Billing back to the clinic. A claim is held for a missing detail and the request sits in someone’s inbox.
- Payer back to the clinic. A denial is fixed once by billing, but the cause (a documentation habit, a visit type) never reaches the person who can change it.
Three plain habits help. Define ‘done’ in writing (signed note, services entered, authorization on file). Give every held claim an owner and a reason. Send the clinic a short list of denial reasons each month. Our documentation and medical billing guide covers what the note needs to support a claim.
If you track claims in a spreadsheet, you can do this today. If you want it built in, a practice management system that tracks claims by stage can show each claim’s stage and owner, check data completeness before submission and hold or flag a claim by rule. It is a claims system, not an EHR.
How should billing and coding staff ask providers questions?
Ask one clear question about the documentation, point to the part of the note it concerns and say when you need the answer. A vague or stacked question is the most common reason a query comes back late or unanswered.
There is a recognised standard for this. The Association of Clinical Documentation Integrity Specialists (ACDIS) and AHIMA published Guidelines for Achieving a Compliant Query Practice (2022 Update) on December 14, 2022. ACDIS describes it as the recommended industry standard for provider queries and says it supersedes the 2019 version. AHIMA’s announcement lists the updates as query guidelines, the use of ‘unable to determine’ in multiple-choice queries, compliant use of query templates, information on problem lists and the role of information from previous encounters.
We have not reproduced the brief’s rules here. Read the brief itself and have your compliance adviser check your templates against it. What we can add from operations is practical:
- Keep one query to one question. A provider can answer a single question between patients.
- Say what in the record prompted the question, so the provider does not have to search.
- Set a response window and decide who follows up when it is missed.
- Keep the answer with the claim, so the next person does not ask again.
Keep queries about the record
A query should clarify documentation. It should not push a provider toward a code or a payment outcome. Ask your compliance adviser to review your query templates before you roll them out.
Why do patients not understand what they owe?
Often the information was given but not in a form the patient could use. The US government’s Healthy People 2030 program defines organizational health literacy as ‘the degree to which organizations enable individuals to find, understand, and use information and services.’ That puts the job on the practice, not the patient.
Applied to billing, the test is simple. Can a patient find the amount, understand why it is that amount, and act on it? The table maps the four moments where we see this fail. It is our framework; the definition above is the only sourced item.
| Moment | What the patient needs to leave knowing | What staff should record | Access check |
|---|---|---|---|
| Scheduling or estimate | What the visit is likely to cost and what is not yet known | That an estimate was given, when and how | Offered in the patient’s language and format? |
| Check-in | What is due today and why | Amount collected, or the plan agreed for it | Interpreter offered for this conversation? |
| After the statement | What insurance paid, what remains and by when | Questions asked and answers given | Statement readable by this patient? |
| Follow-up call | How to pay, or who to call to set up a plan | Outcome of the call and the next date | Call made in the patient’s language? |
Framing: Office of Disease Prevention and Health Promotion, Healthy People 2030 (definition of organizational health literacy). Table rows: RCM Finder.
For statement content and timing, see our patient billing statements guide. For scripts and tone on the phone, see our billing communication guide. One habit works anywhere: ask the patient to say back what they will pay and when. If they cannot, the message did not land.
Staff also need a clear line on who answers what. The front desk and revenue cycle guide explains what the front desk owns. Billing owns balances after insurance. Say so in the script, so patients are not passed between desks.
What does language access require for billing and collections?
If your practice receives federal financial assistance from HHS, you must take reasonable steps to give people with limited English proficiency meaningful access, and that includes billing communications. The duty comes from Title VI of the Civil Rights Act and from Section 1557 of the Affordable Care Act.
Who is covered
HHS’s Title VI guidance applies to recipients of HHS federal financial assistance. In the 2024 Section 1557 final rule, HHS gave notice that it interprets Medicare Part B as federal financial assistance (see the Federal Register notice). Some practices that were outside Section 1557 before may now be inside it. Ask counsel whether you are covered.
What the rules say
| Rule | What it says | What it means for billing |
|---|---|---|
| HHS Title VI guidance (LEP) | Recipients must take reasonable steps to give meaningful access. The extent depends on four factors: how many people, how often, how important the service is, and the resources available. | There is no one-size answer. Document how you decided what to translate and what to offer. |
| 45 CFR 92.201(a)-(b) | Covered entities must take reasonable steps to give meaningful access. Language assistance must be free, accurate and timely, and protect privacy and independent decision-making. | Patients do not pay for an interpreter and should not wait weeks for a translated statement. |
| 45 CFR 92.201(c) | Offer a qualified interpreter when interpretation is required and use a qualified translator when translation is required. Machine translation of critical, high-stakes or technical content needs review by a qualified human translator. | Do not send raw machine translation on documents the patient must act on without human review. Ask counsel which of your documents count as critical. |
| 45 CFR 92.201(e) | Do not require patients to bring or pay for their own interpreter. Do not rely on untrained adults, minor children or non-qualified staff, except in an emergency until a qualified interpreter is found, or when the patient privately asks for an accompanying adult and a qualified interpreter is present and the request is documented. | A coworker who ‘speaks a bit of Spanish’ or a patient’s child is not an interpreter for a money conversation. |
| 45 CFR 92.201(f)-(g) | Video and audio remote interpreting must allow meaningful access: real-time, high-quality audio, and for video a clear image. | A phone line with poor audio does not meet the standard. |
| 45 CFR 92.11 | Covered entities must tell people that language assistance and auxiliary aids are free, in English and at least the 15 languages most commonly spoken by people with limited English proficiency in the state. The notice goes in listed communications, including cost and payment communications such as medical billing and collections materials and good faith estimates. | Billing letters, statements and estimates are on the list. Check what notice each carries. |
Sources: HHS Office for Civil Rights, Title VI guidance on LEP (HHS.gov); 45 CFR 92.201 (eCFR, current Oct 8, 2026); 45 CFR 92.11 (Cornell LII); HHS OCR Dear Colleague letter, Dec 5, 2024.
Two points about timing. HHS published the Section 1557 final rule on May 6, 2024; it took effect July 5, 2024. HHS’s OCR told covered entities in a December 5, 2024 letter that the language access requirements must be fully implemented by July 5, 2025, and noted that courts have stayed or enjoined some provisions of the rule. Read the status on HHS.gov before you act, and do not treat this post as legal advice.
Conversation-heavy specialties feel this most. In behavioral health billing operations, a patient may share sensitive information in a session and then get a bill they cannot read. Use the same qualified-interpreter standard for the financial conversation as for the visit.
Disability access is separate
The same notice rule covers auxiliary aids and services for people with disabilities. Those duties are outside this post. Ask counsel about hearing, vision and other access needs alongside language.
How do you close these gaps without a big project?
Start with one written page per gap: who owns it, what ‘done’ means, and where the evidence is kept. Then review it monthly. Small changes beat a large rollout nobody maintains.
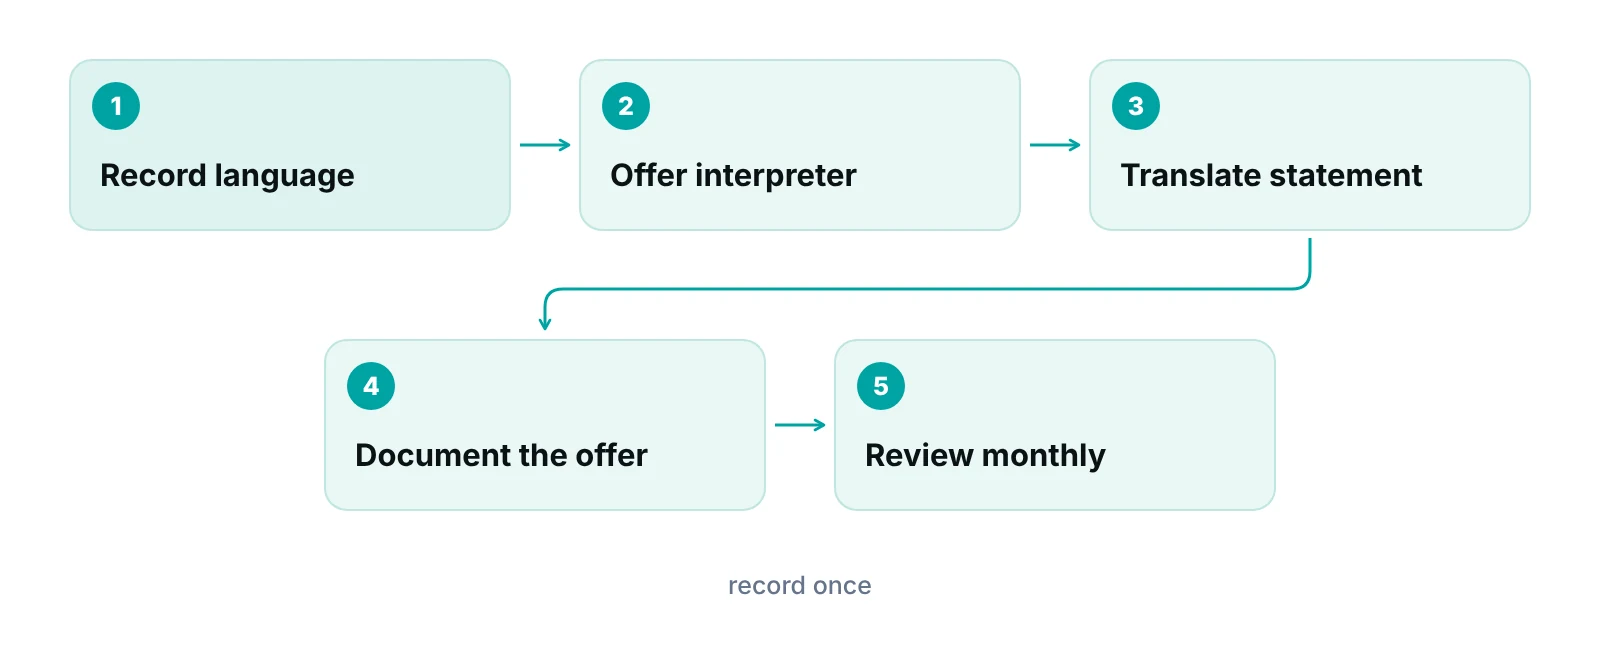
- Add a language field at registration. Record the patient’s preferred language and format once, and show it on the statement and the call list.
- Pick qualified language help in advance. Decide who your qualified interpreters and translators are before you need them, and write down how staff reach them.
- Write the hand-off definitions. ‘Encounter complete’, ‘claim held’ and ‘query answered’ each get one sentence and an owner.
- Review a sample of denials monthly. Sort by reason and send the top reasons to the people who can change them.
- Test your own statement. Ask someone outside billing to explain it back to you.
Use the guide to revenue cycle KPIs to pick the measures. If you want to see what delays cost in cash, use our revenue calculator.
Where do your hand-offs break?
Our free practice audit follows a sample of your claims from the visit to the final balance and shows where information is dropped. Pricing for any service is quoted after the audit.
“Most of the delays I see are not complicated. Two people each assumed the other had it. A named owner and a written definition of done fix more than another reminder email.”
— Awais Afzal, Healthcare Operations & Data Analyst
Our recommendations
- Define 'encounter complete' in one sentence. Write what must be true before billing takes over: signed note, services entered, authorization on file. Post it where both teams can see it.
- Give every held claim an owner and a reason. A held claim with no name on it is where cash waits. Keep the owner, the reason and the date in one list that billing and the clinic both read.
- Standardise provider queries. Use one template: one question, the part of the note it refers to, a response date. Have your compliance adviser check it against the AHIMA and ACDIS brief.
- Record language once and carry it forward. Capture preferred language and format at registration. Show it on estimates, statements and call lists so staff do not ask again.
- Never use a child as the interpreter. Set a rule that money conversations use a qualified interpreter, not a family member or a coworker who speaks some of the language. Make the rule easy to follow by listing how to reach one.
- Send denial reasons back to the people who can change them. A short monthly note to providers and the front desk turns repeated denials into a process change.
A practice management system built around claims, not charts.
RCM Finder's portal shows each claim's stage and owner, checks claim data for completeness before submission and applies workflow rules to flag or hold a claim. It is a claims system, not an EHR.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Communication barriers in healthcare cost the revenue cycle when a hand-off has no owner, a query is vague, a patient cannot read the bill or the language help is missing. Fix them with written definitions, named owners and a language workflow, then measure. If you want a second pair of eyes on your claim path, our medical billing services team can review it, or talk to us.
Frequently asked questions
What are the most common communication barriers in healthcare billing?
The common ones are clinical-to-billing hand-offs with no owner, vague provider queries, denial reasons that never reach the clinic, statements patients cannot understand and missing language help. Each one delays a claim or a balance. A written owner and a written definition of done at each hand-off is the usual first fix.
Does Section 1557 apply to billing statements and collection letters?
For covered entities, yes. 45 CFR 92.11 requires a notice of free language assistance and auxiliary aids in listed communications, and the list includes communications about the cost and payment of care, such as medical billing and collections materials and good faith estimates. Whether your practice is a covered entity is a question for counsel.
Can a bilingual coworker or a family member interpret a billing conversation?
Generally not. 45 CFR 92.201(e) says covered entities must not rely on untrained adults, minor children or non-qualified staff to interpret. The exceptions are a temporary emergency, or a patient’s private request for an accompanying adult with a qualified interpreter present and the request documented.
Do we have to translate every statement into the patient's language?
HHS’s Title VI guidance says the extent of language assistance depends on four factors: how many LEP people you serve, how often they contact you, how important the service is and what resources you have. It also treats some documents as vital. Section 1557 adds a notice duty. Ask counsel which documents you must translate.
What is a provider query and why does it affect payment?
A provider query is a request from coding or documentation staff asking a provider to clarify the record. If it is vague or goes unanswered, the claim waits or is coded on a guess. ACDIS and AHIMA’s 2022 guidelines are the recognised standard for how to write them.
How do I know whether poor communication is costing my practice money?
Look at claims held for documentation, repeated denial reasons, the age of balances and the volume of patient billing calls. Compare them month to month and trace a sample to the hand-off where information was lost. Our KPI guide lists the standard measures.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Guidance to Federal Financial Assistance Recipients Regarding Title VI and the Prohibition Against National Origin Discrimination Affecting LEP Persons — HHS Office for Civil Rights (2025 (page reviewed Mar 6, 2025))
- Fact Sheet: Guidance for Federal Financial Assistance Recipients Regarding Title VI and LEP Persons — HHS Office for Civil Rights (2025)
- 45 CFR 92.201 Meaningful access for individuals with limited English proficiency — eCFR (HHS) (2026 (current as of Oct 8, 2026))
- 45 CFR 92.11 Notice of availability of language assistance services and auxiliary aids and services — Cornell Legal Information Institute (CFR text) (2024 rule)
- Dear Colleagues letter: language access provisions of the Section 1557 final rule — HHS Office for Civil Rights (2024)
- Nondiscrimination in Health Programs and Activities (final rule) — Federal Register, vol. 89, no. 88 (2024)
- Health Literacy in Healthy People 2030 — Office of Disease Prevention and Health Promotion, HHS (2025)
- Guidelines for Achieving a Compliant Query Practice (2022 Update) — ACDIS and AHIMA (2022)
- Practice brief provides updates for achieving a compliant query practice — AHIMA (2022)
Disclaimer: This article is general educational information for medical practice owners and managers. It is not legal, compliance, coding or billing advice. Whether Title VI or Section 1557 applies to your practice, and what it requires, depends on your funding and facts, and the Section 1557 rule has been subject to court action. Confirm with qualified counsel and check HHS.gov for current status before acting.
