

Medical practice cash flow improves when you shorten the time between a visit and money in the bank. Collect the patient's share at check-in, send clean claims quickly, work denials by cause, follow up aged A/R oldest first, cut no-shows and track how long each payer takes to pay.
Most cash-flow problems are timing problems. The care was delivered and the claim exists, but the payment is stuck in registration errors, denials, aged A/R or empty slots. The fix is to find where it is stuck and remove that delay.
This guide covers how payment timing works, the six measures worth tracking, seven practical fixes and a table to match your symptom to a first step. It replaces an earlier version of this post, and we removed statistics we could not trace to a primary source.
Key takeaways
- Cash flow is the timing of payer and patient payments; delays come from rework, not just slow payers.
- Medicare will not pay a clean electronic claim before day 14 or a paper claim before day 29, per First Coast Service Options.
- Define net days in A/R and denial rate the HFMA way and set your own baseline before chasing a benchmark.
- Text reminders probably raise attendance versus no reminder (Cochrane 2013, risk ratio 1.14).
- Fix the earliest step that explains your delay: registration, claim speed, denials or aged A/R.
What drives cash flow in a medical practice?
Two streams of money drive it: payments from payers and payments from patients. Cash flow is the timing of those payments against your payroll, rent and supplier bills. A practice can be busy and profitable on paper and still be short of cash if payment arrives late.
The delay is built from steps. A visit is registered, documented, coded, billed, adjudicated by the payer, posted and, if unpaid, followed up. Each step adds days, and each error sends the claim back to an earlier step. Faster cash usually comes from removing rework, not from working harder at the end.
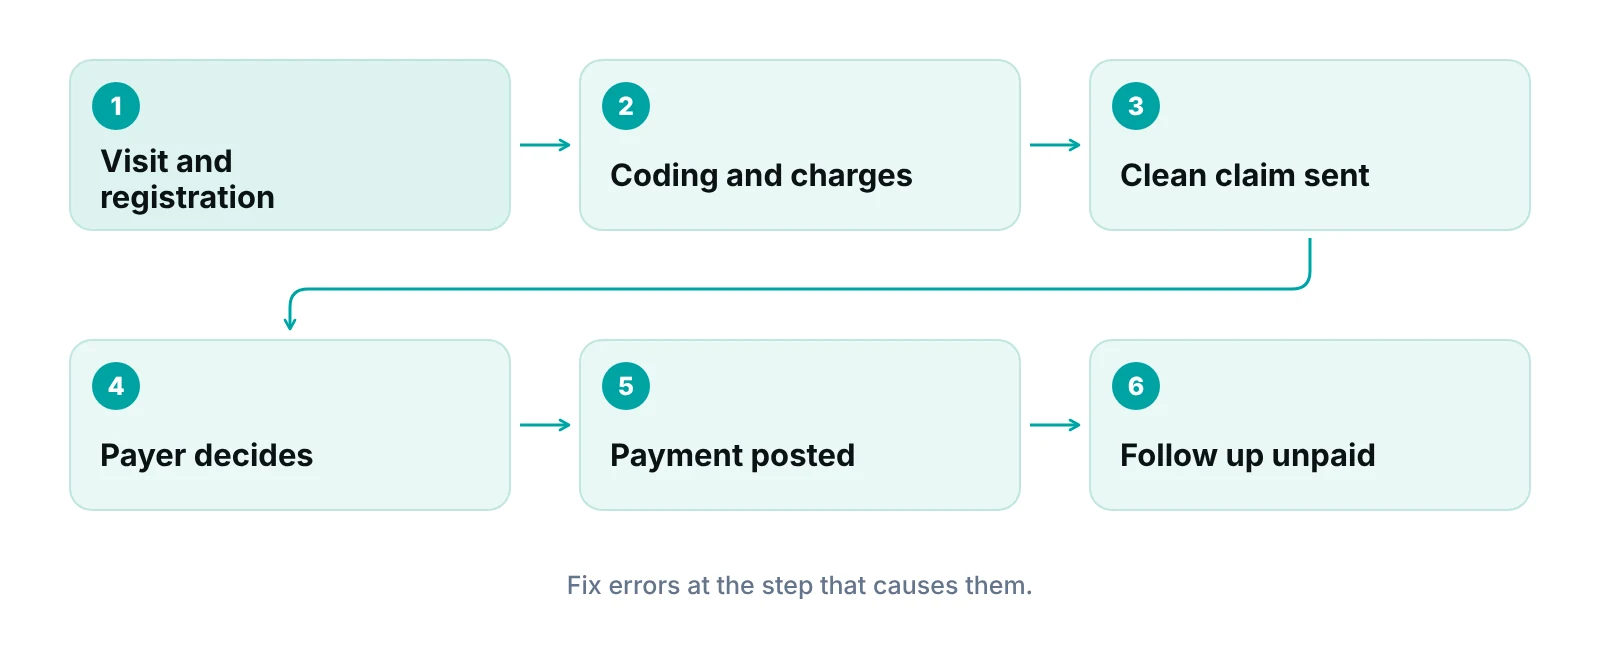
This is why we treat cash flow as a revenue cycle question rather than a banking one. If you want the full end-to-end picture, see our overview of revenue cycle management. The rest of this guide is a practical list of where payment gets stuck and what to do about each place.
Which rules set the pace of payment?
For Medicare, a few published rules set the earliest and latest points at which a clean claim should be paid and the last day you can file. Commercial payers set their own terms in each contract and state law, so you need to read yours. The table lists what we could verify.
| Rule or finding | What it says | Why it matters for cash |
|---|---|---|
| Medicare payment floor | A Medicare contractor may not pay a clean claim before 14 days from receipt for electronic claims and 29 days for paper claims (First Coast Service Options). | A clean electronic claim cannot be paid sooner than two weeks. Counting paper claims in your cash forecast adds about two more weeks. |
| Medicare processing window | A Medicare Administrative Contractor has up to 30 days to process a clean claim without paying interest (CGS, citing CMS Pub. 100-04, chapter 1, section 80.2.1.1). | A clean claim that is still unpaid well past 30 days is worth a status check. A claim that is not clean does not carry this protection. |
| Medicare timely filing | A claim must be filed within one calendar year after the date of service, with limited exceptions (42 CFR 424.44). | Unbilled or stuck claims lose their value when the window closes. |
| Reminders and attendance | A Cochrane review of eight randomised trials (6,615 participants, searches to August 2012) found text reminders probably increase attendance versus no reminder (risk ratio 1.14, 95% CI 1.03 to 1.26, moderate certainty). | An empty slot is a visit that cannot be billed. Reminders are cheap relative to the revenue lost. |
Sources: First Coast Service Options; CGS Medicare; eCFR, 42 CFR 424.44; Cochrane Database of Systematic Reviews (2013), CD007458.
What a payment floor is not
The floor is the earliest a contractor can pay, not a promise of when it will. Payment times vary by payer, claim type and whether anything needs review. Use the floor to set realistic expectations, then measure your own payers.
Which numbers show whether cash is moving?
Six measures cover most of it: net days in A/R, the age of that A/R, the denial rate, cash collected against revenue, point-of-service collections and cost to collect. Define each one the same way every month so you can compare. HFMA MAP Keys (2023 edition) gives formal definitions for each.
| Measure | HFMA MAP Keys definition (2023 edition) | Rule of thumb (AAFP, undated) |
|---|---|---|
| Net days in A/R | Net A/R divided by average daily net patient service revenue, using the most recent three months. | Below 50 days at minimum; 30 to 40 days preferable. |
| Aged A/R | Share of billed A/R in each bucket: 0-30, 31-60, 61-90, 91-120 and over 120 days. Buckets must sum to 100%. | AAFP names A/R over 120 days as a benchmark but gives no figure. |
| Remittance denial rate | Actionable claims denied divided by claims remitted. Excludes patient-responsibility denials and duplicates. | 5% to 10% described as the industry average; below 5% more desirable. |
| Cash collection as % of net revenue | Patient service cash collected, net of refunds, divided by average monthly net patient service revenue. | AAFP’s adjusted collection rate: 95% at minimum; 95% to 99% average. A different formula, so do not mix them. |
| Point-of-service cash | Point-of-service payments divided by total self-pay cash. Counts cash collected before, at or up to seven days after the service. | No published target. |
| Cost to collect | Total revenue cycle cost divided by total patient service cash collected. | No published target. |
Sources: HFMA MAP Keys, 2023 edition (definitions); AAFP, Managing practice finances (rules of thumb, undated and without a named underlying source).
Treat benchmarks as a starting point
The AAFP figures are rules of thumb on an undated page, and the HFMA edition we reviewed lists no target values. Specialty, payer mix and billing model change what good looks like. Set your own baseline first, then improve against it. Our guide to revenue cycle KPIs and essential A/R report metrics go deeper on reading them.
Seven ways to get paid faster
Start with the steps nearest the visit, because errors there are cheapest to fix and cause the most rework later. The first four apply to nearly every practice. The last three depend on your payer mix and your schedule.
1. Collect the patient's share at the visit
Money asked for at check-in is usually easier to collect than money asked for in a statement weeks later. Check the plan, copay and deductible status before the visit, tell the patient what to expect, and collect at check-in. HFMA’s point-of-service cash measure counts payments made before, at, or within seven days after the service, so it gives you a way to track this. See our guide to improving patient collections for scripts and workflows.
2. Send clean claims quickly
A clean claim is paid sooner and needs no rework. Capture charges the same day, check for missing or mismatched data before submission and send electronically. A paper claim cannot be paid by Medicare until day 29, against day 14 for electronic. If your EHR and billing system are separate, check that charges, demographics and diagnoses move across without re-typing. Our clean claims guide covers the checks in detail.
3. Work denials by cause, not by claim
Appeal individual denials, but also tag each one with its root cause every month: registration, eligibility, authorization, coding, documentation or payer error. A short list of repeat causes tells you what to fix upstream. The old advice to review denials monthly is sound; the percentages by cause are not universal, so use your own data. For the process, see medical billing denial management.
4. Work A/R by age, oldest first
Sort unpaid claims into the aging buckets (0-30, 31-60, 61-90, 91-120 and over 120 days) and review the oldest first. Each bucket should have an owner and a next action: check status, correct and resubmit, appeal or write off with approval. Keep the filing window in mind: Medicare allows one calendar year from the date of service, and other payers set their own limits. Our accounts receivable guide and A/R recovery tips for small practices explain the routine.
“The biggest cash-flow gains I see come from a weekly habit, not a new tool: look at the oldest unpaid claims, assign each one an owner and a next step, and do it again next week.”
— Awais Afzal, Healthcare Operations & Data Analyst
5. Track how long each payer takes to pay
Compare each payer’s actual days-to-pay with the Medicare floor and processing window above, and with the terms in your contract. A payer that consistently pays slower than its contract allows is a conversation for your contracting or credentialing contact, or for the state insurance regulator where prompt-pay rules apply. Those rules vary by state, so check yours before you cite them.
6. Reduce no-shows with reminders
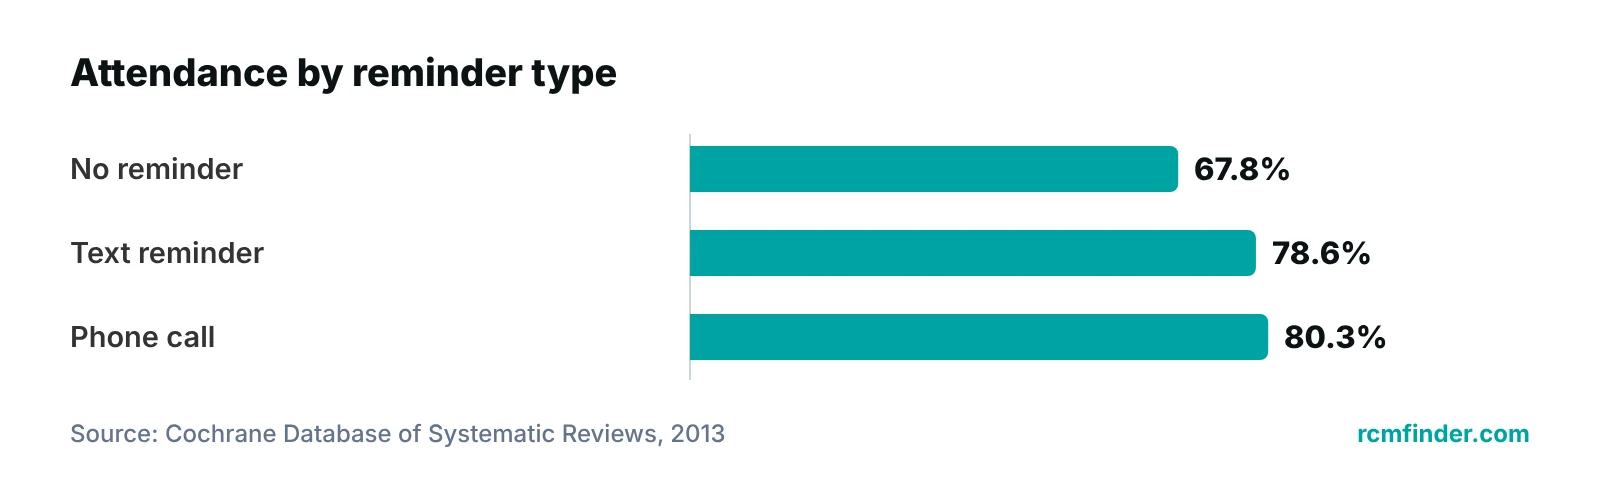
Reminders are among the best-studied fixes. In the pooled Cochrane trials, average attendance was 67.8% with no reminders, 78.6% with text reminders and 80.3% with phone call reminders, and the review found text reminders and phone calls performed about the same (risk ratio 0.99). Two studies in the review reported a lower cost per attendance for text reminders than for phone calls. The trials were run in many settings and are over a decade old, so treat the size of the gain as a rough guide.
Offering telehealth where it is clinically appropriate can also help with access. We do not recommend overbooking as a cash-flow fix, because it affects patient access and safety and the right approach is a clinical and operational decision for you.
7. Make paying easy
Offer card payments, a secure online payment option and, for larger balances, a written payment plan. Each option lowers the effort for the patient and gives your staff a clear next step. Keep plan terms consistent and documented. Our guide to patient payment plans covers the structure. Any online portal that handles patient information should be set up with the vendor’s Business Associate Agreement in place.
Do the math on your own practice
Before you pick a fix, estimate what a few days of A/R is worth to you. Our revenue calculator is a quick way to frame it.
Where is your cash stuck, and what should you fix first?
Match the symptom to the likely cause, then fix the earliest step that explains it. Most practices find that one or two causes account for most of the delay. The table is a starting point for a conversation with your billing lead.
| What you see | Likely cause | First fix | Usual owner |
|---|---|---|---|
| Net days in A/R rising | Slow claim submission, repeat denials or no follow-up on aged claims | Pull an aging report; assign the oldest buckets | Billing lead |
| Many denials on new patients | Registration or eligibility errors at the desk | Checklist at registration; verify before the visit | Front desk manager |
| Claims rejected before payer review | Data or format errors that a pre-submission check should catch | Add a scrub step; review rejection reasons weekly | Billing team |
| Large patient balances, little collected | Collections start after the visit, with few payment options | Collect at check-in; offer plans | Front desk and billing |
| Empty slots, steady fixed costs | No-shows and late cancellations | Text or call reminders; a cancellation list | Front desk manager |
| One payer always slow | Contract terms, claim edits or payer processing | Track days-to-pay; escalate with data | Practice administrator |
Whether to fix these in-house or hand part of the work to a partner depends on volume and staffing. A small team often has the knowledge but not the weekly hours for A/R follow-up. Our accounts receivable management services work claims by age and payer inside your existing EHR (for example PrognoCIS, eClinicalWorks or athenahealth). Practices that want the whole cycle managed can look at our end-to-end revenue cycle management. We quote pricing after a free audit, not before.
See where your cash is stuck
Our free practice audit reviews your aging, denial reasons and front-end workflow and shows which of these fixes to start with. Pricing for any service is quoted after the audit.
If your specialty has its own billing quirks, such as authorization-heavy services or bundled codes, the order of fixes can change. Browse the specialties we support to see how we handle your area.
Our recommendations
- Pick one number and a baseline. We start every review with net days in A/R and the aging report, defined the HFMA way. Write down this month’s figure before you change anything.
- Give every aged claim an owner. A claim with no owner does not get worked. Assign each bucket to a person and a weekly time slot.
- Tag denials by cause. Add a cause field and review it monthly. Fix the top repeat cause upstream before you hire for appeals.
- Collect before the patient leaves. Verify coverage before the visit, state the expected amount and ask for it at check-in. Offer a written plan for larger balances.
- Send reminders and measure the result. Use text or phone reminders, then track your own no-show rate before and after. Do not rely on someone else’s percentage.
- Review payer speed quarterly. Compare actual days-to-pay with contract terms and the Medicare timing rules. Bring data when you call the payer.
Cash flow slows when nobody owns a stuck claim.
The RCM Finder portal tracks each claim by stage with a named owner, and flags payments that arrive below the expected amount, so a late or short-paid claim is visible before the month closes.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Faster cash comes from fewer errors and a weekly routine. Measure net days in A/R, tag your denials and give every aged claim an owner. If follow-up is where your team runs short of time, our accounts receivable management services can take it on, and our revenue cycle management service covers the whole cycle from registration to payment.
Frequently asked questions
What is a good number of days in A/R for a medical practice?
It depends on specialty and payer mix. The AAFP’s practice-finance guidance says below 50 days at minimum and 30 to 40 days preferable, but that page is undated and does not name its source. HFMA defines how to calculate net days in A/R but, in the edition we reviewed, sets no target. Start with your own trend.
How long does Medicare take to pay a claim?
Not before the payment floor: First Coast Service Options states 14 days from receipt for electronic claims and 29 days for paper. CGS says contractors have up to 30 days to process a clean claim without paying interest. Claims that need review or are not clean can take longer, so measure your own contractor.
Do text reminders really reduce no-shows?
A 2013 Cochrane review of eight randomised trials found text reminders probably improve attendance compared with no reminder (risk ratio 1.14, moderate certainty) and perform about the same as phone calls. The trials are over a decade old and varied in setting, so test reminders in your own practice and track the result.
How long do I have to file a Medicare claim?
Under 42 CFR 424.44, a claim must generally be filed within one calendar year after the date of service, with limited exceptions. Other payers set their own deadlines in their contracts, and some are much shorter. Check each contract and track the oldest unbilled encounters.
Should a small practice outsource accounts receivable follow-up?
It can make sense when your team knows the work but cannot give it steady weekly hours, or when aged claims keep growing. Weigh volume, staffing and how well your current system reports on aging. Ask any vendor how they report, who works each claim and how they handle patient data under a Business Associate Agreement.
What should I fix first to improve cash flow?
Fix the earliest step that explains your delay. For many practices that means registration and eligibility errors, claims sent late or aged A/R with no owner. Pull an aging report and a month of denial reasons, and the answer is usually visible in a few hours.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- MAP Keys, 2023 Edition — HFMA (2023)
- Managing practice finances — American Academy of Family Physicians (undated (site copyright 2026))
- New provider roadmap: Claims submission — First Coast Service Options (Medicare Administrative Contractor) (2025)
- Payment timeframes for clean claims — CGS Medicare (Medicare Administrative Contractor) (n/a)
- 42 CFR 424.44 Time limits for filing claims — eCFR / U.S. Government (current)
- Mobile phone messaging reminders for attendance at healthcare appointments (CD007458) — Cochrane Database of Systematic Reviews (2013)
Disclaimer: This article is general educational information for medical practice owners and managers. It is not legal, financial, compliance, coding or billing advice. Payer rules, filing limits, prompt-pay laws and contract terms vary by payer, plan and state and change often. Confirm requirements with each payer and qualified advisers before acting.
