

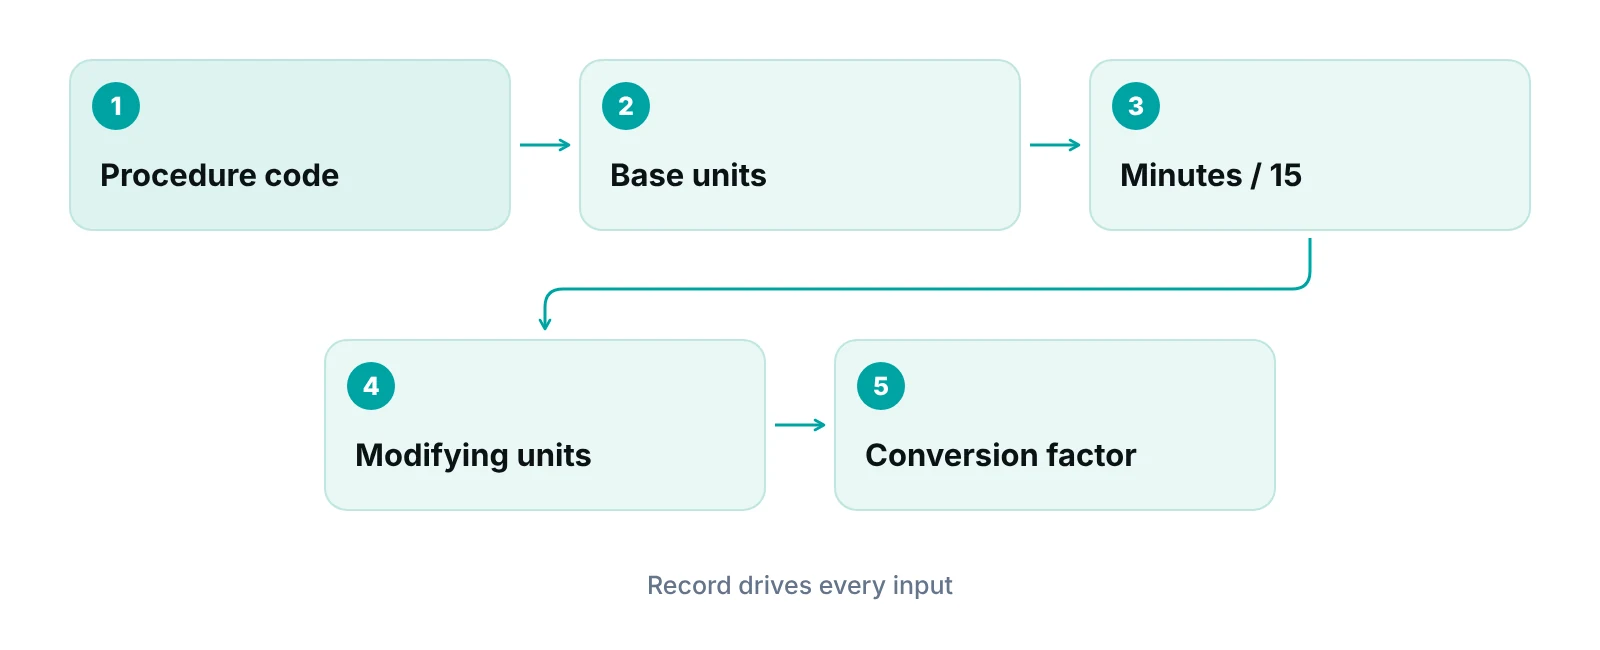
Anesthesia billing pays by units, not by a flat fee. Each claim adds base units for the procedure, time units (anesthesia minutes divided by 15) and any modifying units, then multiplies the total by a conversion factor. Payment modifiers (AA, QK, QX, QY, QZ, AD) show who delivered the care and who supervised it.
Most specialties bill a code and get a fee. Anesthesia groups, CRNAs and anesthesiologist assistants bill a code and a clock, and the claim only pays correctly when the code, the minutes and the modifier all agree. That is why anesthesia denials and underpayments often trace back to the record, not the claim form.
This guide is for practice managers, group administrators and billing leads at anesthesia practices who are deciding how to run billing. It replaces an older version of this post that was written for hospitals and used a wrong time-unit example. Below you will find the formula, a worked example, the modifiers, what commercial payers do differently, and how to choose between in-house, outsourced and hybrid billing. For the specialty-level view, see anesthesia billing and RCM support.
Key takeaways
- The payment formula is (base units + time units + modifying units) x conversion factor, and time is counted in 15-minute units.
- Medicare conversion factors differ by locality and change every year, so a single national dollar figure is rarely the number on your claim.
- The payment modifier (AA, QK, QX, QY, QZ or AD) must match the staffing model documented in the anesthesia record.
- Qualifying circumstances and physical status modifiers are treated differently by Medicare and commercial payers, so check each contract.
- Time documentation is the main audit exposure: start and stop times, signatures and the supervising role must be in the record.
How anesthesia payment works
Anesthesia is priced with its own formula, separate from the work-RVU model used for most office services. The American Society of Anesthesiologists (ASA) writes it as (base units + time units + modifying units) x conversion factor. Noridian, a Medicare Administrative Contractor, shows the same idea in its fee schedule notes: (base units + billed minutes / 15) x conversion factor gives the allowed amount.
The three kinds of units
- Base units are fixed values assigned to each anesthesia CPT code (00100 to 01999). CMS publishes them each year; its Anesthesiologists Information Center notes that base units were unchanged for calendar year 2026.
- Time units come from the minutes on the anesthesia record. The ASA’s example turns 139 minutes into 9.3 time units, which is 15-minute units rounded to one decimal place.
- Modifying units are extra units for physical status or qualifying circumstances. Whether they are paid depends on the payer, as covered below.
The conversion factor turns units into dollars. It is not one number. Noridian lists a different conversion factor for each Medicare locality and separate tables for qualifying alternative payment model participants, and the figures change by calendar year.
Why a single "average rate" is misleading
Commercial contracts negotiate their own conversion factors, often several times the Medicare figure. An example that mixes a commercial conversion factor with Medicare base units, or the reverse, will not match what any payer actually remits. Always price a claim with the conversion factor from the payer and year that apply to the date of service.
A worked example, step by step
The easiest way to check a remittance is to rebuild the claim from the record. The ASA’s published example uses CPT 01230 (6 base units), 139 minutes of anesthesia time, a P2 physical status modifier worth 0 units, and two qualifying circumstance codes. The total is 18.3 units, priced at a $72.00 conversion factor to give $1,317.60.
- Base units for the procedure code: 6.
- Time: 139 minutes divided by 15, rounded to one decimal, is 9.3 units.
- Modifying units: P2 adds 0, +99100 adds 1 and +99140 adds 2, so 3 units.
- Total: 6 + 9.3 + 3 = 18.3 units.
- Multiply by the conversion factor: 18.3 x $72.00 = $1,317.60.
A Medicare claim works the same way but with a Medicare conversion factor and no payment for qualifying circumstances (see the table below). As an illustration only, take a procedure with 5 base units and 75 minutes of anesthesia time. That is 75 / 15 = 5 time units, or 10 units in total. Using the 2026 Nevada participating-provider conversion factor of $20.27, the allowed amount would be 10 x $20.27 = $202.70. The 5 base units here are a made-up round number for the example, not the value of a real code.
Payment modifiers: AA, QK, QX, QY, QZ and AD
The payment modifier tells the payer who performed the service and how much supervision was involved. It goes in the first modifier position on an anesthesia code. Blue Cross Blue Shield of Minnesota’s policy states that these modifiers are required on anesthesia codes and that other CPT codes billed with them are denied.
| Modifier | What it means | Who reports it | Typical payment basis |
|---|---|---|---|
| AA | Anesthesia performed personally by the anesthesiologist | Anesthesiologist | Full rate |
| QK | Medical direction of two, three or four concurrent procedures | Anesthesiologist | Reduced (part-time) rate |
| QY | Medical direction of one qualified nonphysician anesthetist | Anesthesiologist | Reduced (part-time) rate |
| QX | Nonphysician anesthetist service with medical direction | CRNA or anesthesiologist assistant | Reduced (part-time) rate |
| QZ | CRNA service without medical direction | CRNA | Full rate |
| AD | Medical supervision of more than four concurrent procedures | Anesthesiologist | Reduced (part-time) rate |
Source: American Society of Anesthesiologists, Anesthesia Payment Basics: Codes and Modifiers (updated 2024); Blue Cross Blue Shield of Minnesota, Anesthesia Services reimbursement policy 001 (effective 12/01/2023). Payment basis shown is that commercial policy; confirm each payer’s percentages.
Some payers also ask for monitored anesthesia care modifiers. The ASA lists QS, G8 and G9 for monitored anesthesia care when a payer requires them, and notes modifier 22 for added work such as limited airway access. Which of these a payer wants varies, so keep a payer-by-payer modifier sheet.
If your group uses a care-team model, the claim must also match the record. In the Minnesota policy, the anesthesia record must name the professionals who provided the service and carry both the CRNA and the anesthesiologist signatures when both are involved. Modifier logic in other specialties is covered in our guide to modifiers 25 vs 59, but anesthesia modifiers follow their own rules.
Physical status and qualifying circumstances: where payers differ
Physical status modifiers (P1 to P6) and qualifying circumstance codes are where Medicare and commercial payers most often disagree. The ASA states that CMS does not recognize qualifying circumstance codes for additional payment, although many private payers do. The Minnesota policy goes the other way for its plan: it states that these codes carry a Status B indicator on the Medicare fee schedule and that it gives no added reimbursement for them.
| Code | Meaning | Units (ASA page) | Treatment in one commercial policy |
|---|---|---|---|
| P1, P2, P6 | Physical status 1, 2 and 6 | Not stated on source page | No units added |
| P3 | Physical status 3 | Not stated on source page | 1 unit |
| P4 | Physical status 4 | Not stated on source page | 2 units |
| P5 | Physical status 5 | Not stated on source page | 3 units |
| +99100 | Patient younger than 1 or older than 70 | 1 | No added payment |
| +99116 | Total body hypothermia | 5 | No added payment |
| +99135 | Controlled hypotension | 5 | No added payment |
| +99140 | Emergency conditions | 2 | No added payment |
Sources: American Society of Anesthesiologists, qualifying circumstances (2020 Relative Value Guide values); Blue Cross Blue Shield of Minnesota, Anesthesia Services policy 001 (effective 12/01/2023). The right-hand column describes one payer, not a rule for all payers.
Two reporting limits are worth putting in your coding checklist. The ASA says +99100 should not be reported with a pediatric-specific anesthesia code such as 00326, and +99116 and +99135 should not be reported with cardiac procedures on cardiopulmonary bypass, where the bypass itself may cause the condition. Several qualifying circumstance codes can be reported on one case when the clinical facts support them.
This is also why an old rule of thumb such as “emergency modifier adds 2 units” is misleading. Emergency status is reported with the +99140 qualifying circumstance code, not a payment modifier, and a payer may or may not pay it.
Conversion factors change by year and locality
Medicare anesthesia conversion factors move every year, sometimes mid-year, and they differ by locality. Noridian’s page shows that the 2024 rates were updated for dates of service from March 9, 2024 under the Consolidated Appropriations Act, 2024, and that the 2025 fees were updated under Section 3206 of the American Relief Act, 2025. At the national level, the ASA reports a 2025 anesthesia conversion factor of $20.3178.
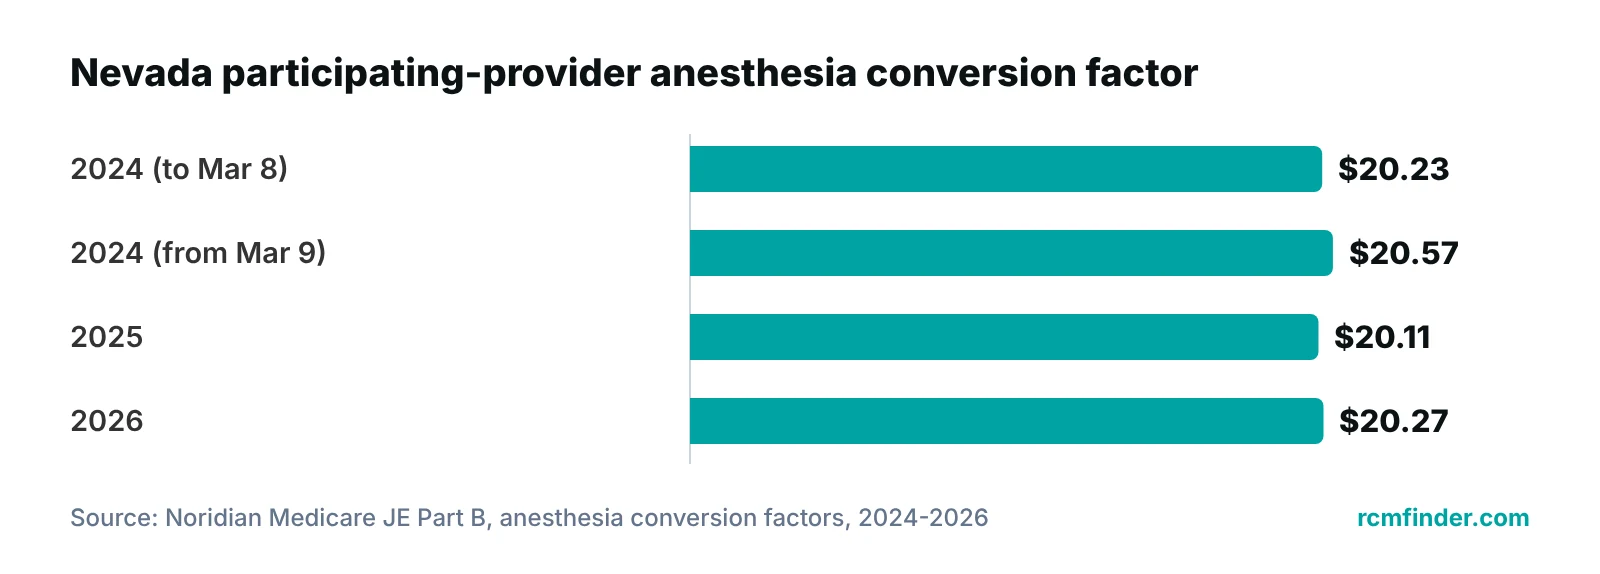
Locality matters too. For 2026, Noridian lists participating-provider conversion factors of $20.27 for Nevada, $20.34 for Hawaii and the Pacific Islands, $21.26 for the Los Angeles and Orange County area, and $22.79 for Santa Clara County. Non-participating and limiting-charge amounts are listed separately. The takeaway: load conversion factors by payer, locality and date of service, and review them each January and whenever Congress changes the Medicare schedule mid-year.
Older versions of this article cited a $70 conversion factor and a 3% rise in anesthesia rates from 2021 to 2023. Neither holds up as a Medicare figure, so both have been removed. A conversion factor in that range is plausible only in a negotiated commercial contract.
Documentation and denials: what usually goes wrong
Most anesthesia claim problems start in the record, not the claim. The Minnesota policy defines anesthesia time as running from when the provider begins preparing the patient until the patient is safely under postoperative care, requires time to be documented, and warns that claims are subject to post-payment audit and recovery if guidelines are not followed. Payers define time slightly differently, so confirm the definition in each contract.
- Time mismatch. Minutes on the claim do not match the start and stop times in the record. Payers report time in minutes on the 837P and convert to units themselves.
- Wrong or missing payment modifier. A QK on a case that was not run concurrently, or a QZ where a physician was directing, will not survive review.
- Unsigned or unclear roles. The record does not show who delivered the care and who directed it.
- Modifier in the wrong position. Payment modifiers belong in the first position and physical status modifiers in the second, in the Minnesota policy.
- Late filing. Anesthesia claims follow the same payer filing deadlines as anything else; see our guide to medical billing time limits.
When a claim does deny, work the reason code rather than resubmitting blindly. Our denial management guide shows how to sort denials by cause, and clean claim practices show how to catch problems before submission. Anesthesia for procedures sedated in an emergency department follows different coding logic, covered in coding moderate sedation.
“Billing for time-based services is only as accurate as the clock in the clinical record.”
A practice management system can help here by checking that required fields are present before a claim goes out and by flagging payments that come in below the expected amount. A practice management system that tracks claims by stage with data-completeness checks and underpayment flags gives the billing lead a place to see which cases are stuck and who owns them.
In-house, outsourced or hybrid: choosing how to bill
The right model depends on volume, how many payers and hospitals you bill, and whether you have someone who knows anesthesia rules. Anesthesia is a niche, so a general biller often struggles with units, modifiers and care-team claims. The table below compares the three common setups; it is a decision aid, not a ranking.
| Question | In-house team | Outsourced billing | Hybrid |
|---|---|---|---|
| Who owns coding and charge capture? | Your staff | Billing partner, from your records | Your staff capture charges; partner codes and submits |
| Specialty knowledge needed | You hire and train for it | Ask for proof of anesthesia experience | Needed on both sides |
| Best fit | Stable, larger groups with a skilled lead | Small or growing groups, or turnover | Groups that want control of A/R but not claim work |
| Main risk | Single point of failure if a biller leaves | Weak handoff of time records and schedules | Unclear ownership between teams |
| What to ask | Who audits time and modifiers? | How are anesthesia records received and checked? | Who owns each denial and appeal? |
If you outsource, the important questions are practical. Ask how the vendor receives anesthesia records, who checks start and stop times against the claim, how it handles care-team modifiers, and how it reports denials and A/R. Ask any vendor to sign a Business Associate Agreement before it sees patient data. If you are comparing partners, the medical billing services overview shows what a full-service arrangement covers, and denial management services covers the appeal side. Some groups also hand payer enrollment to specialists; see our guide to insurance credentialing for group practices.
See where your anesthesia claims leak
Get a free practice audit of how your units, modifiers and time records flow into claims. Pricing is quoted only after the audit.
Our recommendations
- Rebuild a sample of claims from the record. Each month, take ten paid claims and recalculate base, time and modifying units from the anesthesia record. Compare the result with the remittance.
- Keep a payer-by-payer rules sheet. List how each payer treats qualifying circumstances, physical status units, time rounding and care-team modifiers. Review it every January and after any mid-year fee change.
- Load conversion factors by locality and date of service. Do not use one number for the whole group. Store the factor that applies to each payer, locality and period.
- Check the payment modifier against the staffing model. Before submission, confirm that the modifier reflects who delivered the care and who directed it, and that the record shows both roles.
- Treat time as the audit item. Make start time, stop time and signatures required fields in the record. A missing time is a missing payment.
- Write down who owns each denial. Assign a named owner to every denied anesthesia claim, with a due date, so that appeals are not lost between teams.
Anesthesia claims depend on complete time and role data, and a claim-centred practice management system can check for it.
RCM Finder's portal tracks claims by stage with an owner, runs data-completeness checks before submission and flags payments that fall below the expected amount. It is a practice management system, not an EHR, and works alongside the EHR you already use.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Anesthesia billing is a units problem: base plus time plus modifying units, times a conversion factor that depends on payer, locality and year. Get the record, the modifier and the payer rules aligned and the math takes care of itself. If you want a second set of eyes on your process, start with a medical billing services conversation or a free practice audit, and use the revenue calculator to size the gap.
Frequently asked questions
How do you calculate anesthesia billing?
Add the base units for the anesthesia code, the time units (minutes divided by 15) and any modifying units, then multiply by the conversion factor. Noridian’s fee schedule notes use the form (base units + billed minutes / 15) x conversion factor. The conversion factor depends on the payer, locality and year.
How long is an anesthesia time unit?
A time unit is 15 minutes. The ASA’s example converts 139 minutes into 9.3 time units. Practices report minutes on the claim, and payers convert them to units. Some commercial policies define when the clock starts and stops, so check each contract.
What is the difference between QK, QX, QY, QZ and AA?
AA means the anesthesiologist personally performed the service. QK is medical direction of two to four concurrent cases, and QY is direction of one qualified nonphysician anesthetist. QX is the CRNA or anesthesiologist assistant service under direction, and QZ is a CRNA service without direction. AD is supervision of more than four concurrent cases.
Does Medicare pay for qualifying circumstances codes like 99140?
According to the ASA, CMS does not recognize qualifying circumstance codes for additional payment, though many private payers do. At least one commercial plan also states that it does not pay them. Check each payer’s policy and contract before assuming the units will be paid.
Do physical status modifiers add payment?
It depends on the payer. In one commercial policy, P3 adds 1 unit, P4 adds 2 and P5 adds 3, while P1, P2 and P6 add none. Medicare behavior was not verified for this article, so confirm in the payer’s policy. Report the modifier in the second position when the payer requires it.
Can an outside billing company handle anesthesia claims?
Yes, if it has anesthesia experience and a clear process for receiving records and checking time, units and modifiers. Ask how it audits time, who owns denials, and whether it will sign a Business Associate Agreement before accessing patient data.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Anesthesia Payment Basics Series: Codes and Modifiers — American Society of Anesthesiologists (2024)
- Anesthesia Payment Basics Series: Qualifying Circumstances — American Society of Anesthesiologists (2019 (RVG 2020 values))
- Anesthesia Conversion Factors — Noridian Healthcare Solutions (Medicare JE Part B) (2024-2026)
- Anesthesiologists Information Center — Centers for Medicare & Medicaid Services (2026)
- CMS proposes a small increase in anesthesia payments in 2026 — American Society of Anesthesiologists (2025)
- Anesthesia Services reimbursement policy 001 — Blue Cross and Blue Shield of Minnesota (2023)
Disclaimer: This article is educational. It is not legal, coding, billing or compliance advice. Payer rules, conversion factors and modifier requirements vary by payer, contract, locality and year, so confirm them against current payer and CMS publications before submitting claims.
