

Multi-specialty medical billing is hard because one team applies several specialties’ codes, edits and payer rules to a shared patient base. Groups keep claims clean by enrolling every provider with every payer, checking code pairs before submission, and giving each claim stage one owner.
The old advice for groups was to buy software and train staff. That is part of it, but the failures usually sit at the edges between departments. The sections below follow a claim through those edges and cite CMS rules where they exist.
Key takeaways
- Rules change by setting, provider type and specialty, so one checklist for all departments fails.
- Medicare does not allow office visits to be billed as split or shared; facility visits use modifier FS.
- Enroll each provider with each payer and link them to the group before booking their patients.
- Check NCCI code pairs before submission, and use modifier 25 rather than 59 on E/M services.
- Report denials by specialty so the fix reaches the right team.
What multi-specialty medical billing actually means
Multi-specialty medical billing is billing for a group where cardiology, orthopedics, primary care and other specialties share one tax ID, one front desk and often one patient list. The hard part is not volume. It is that each specialty brings its own codes, its own edits and its own payer habits to the same billing team.
A single-specialty practice builds one set of habits and repeats it. A multi-specialty group has to hold several sets at once and still send one clean claim per visit. Mistakes tend to come from the places where specialties touch each other: a patient seen by two departments, a provider who just joined, a procedure billed next to an office visit.
This guide covers those touch points, in the order a claim meets them. If you want to see how a single specialty handles its own rules first, browse the specialty billing pages and come back here for the group-level view.
Why a general checklist fails a group
A generic billing checklist assumes one workflow. In a group, the same rule can apply differently by setting, by provider type and by payer. For example, Medicare allows a split or shared visit in a hospital or emergency department but not in an office. A checklist that says only “use the right modifier” cannot tell a biller which case they are in.
Where the rules change: setting, provider and specialty
The rule a claim follows depends on where the service happened, who performed it and which specialty billed it. The table lists six situations that groups meet often, using Medicare rules that CMS publishes. Commercial payers set their own policies, so treat the table as the Medicare baseline.
| Situation | What the Medicare rule says | Why it matters to a group |
|---|---|---|
| Split or shared visit in a hospital, ED or skilled nursing setting | A physician and a non-physician practitioner (NPP) in the same group both perform the visit. Report modifier FS. The claim goes out under the NPI of the practitioner who did the substantive portion. | The billing team needs to know who did the larger part of the visit, so the note and the claim must agree. |
| Office visit shared between a physician and an NPP | CMS says office visits cannot be billed as split or shared. | A hospital-based habit applied to the clinic creates a billing error. |
| Substantive portion test (2024 onward) | For most facility E/M visits it means more than half of total time, or a substantive part of the medical decision making. | Documentation must show time or decision making, not just two signatures. |
| New versus established patient | A patient is new only if no professional service came from the physician, or from another physician of the same specialty in the same group, in the previous three years. | A patient seen by cardiology may still be new to dermatology in the same group, because the lookback is specialty-based. |
| Critical care by more than one specialty | Practitioners from more than one specialty may provide critical care at the same time if the services are not duplicative, and each may bill their own initial critical care code. | Two departments can bill the same day. Same-specialty colleagues in one group combine their time instead. |
| Code pairs that bundle | NCCI edits flag code pairs that should not be reported together, and some can be unbundled only with an NCCI-associated modifier. | Two specialties billing for one patient on one date can trip an edit neither team knew existed. |
Source: CMS, Evaluation and Management Services, MLN006764 (May 2026); Noridian Medicare, NCCI page.
“The note, the modifier and the NPI on the claim should tell the same story. If any one disagrees, the claim is a denial waiting to happen.”
Split or shared visits, step by step
CMS defines a split or shared visit as one that both a physician and an NPP in the same group perform in a facility setting. The booklet lists hospital inpatient, hospital outpatient and emergency department visits, and skilled nursing facility visits other than those a physician must perform in full. It states plainly that office and nursing facility visits cannot be billed this way. See the CMS E/M booklet for the current table.
- Confirm the setting is a facility setting, not an office.
- Decide who performed the substantive portion, using time or medical decision making as documented.
- Add modifier FS to the claim.
- Bill under that practitioner’s NPI.
- Keep the documentation that supports the choice with the claim.
Enroll every provider, then link them to the group
A new provider cannot bill under the group until they are enrolled and tied to it with each payer. For Medicare Part B, that means an individual enrollment (CMS-855I) and a reassignment (CMS-855R) that lets the group submit claims and receive payment for what the provider performed. CMS training slides state that both the practitioner and the group’s authorized or delegated official must sign to add a reassignment. Ending one needs only one signature.
In a multi-specialty group this step repeats for every new hire, for every payer. Each payer has its own timeline, so a status list per payer is the safest record. We recommend tracking enrollment as a status per provider and per payer, not as a one-time project. The credentialing and payer enrollment services page explains what that work involves, and our guide to credentialing for group practices walks through the sequence.
Ask before the first patient is scheduled
For each new provider and each payer, confirm the effective date of the enrollment and the reassignment before you book that provider’s patients. Dates differ by payer, and your own payer contacts are the authority.
Coding edits that show up when specialties overlap
NCCI procedure-to-procedure edits exist to prevent improper payment when incorrect code combinations are reported. They matter more in a group because two specialties may each bill a correct code that the edit table pairs together. CMS publishes one table for practitioners and another for outpatient hospital services, and updates them quarterly.
| Modifier indicator | What it means | What your biller does |
|---|---|---|
| 0 | The two codes should never be reported together on the same date of service. The column one code is eligible for payment and the column two code is denied. | Do not append a modifier. Fix the coding or accept the denial. |
| 1 | The codes may be reported together only in defined circumstances, with an NCCI-associated modifier. | Check the record. Add the modifier only if the documentation shows a distinct service. |
| 9 | The edit does not apply. | Nothing to do for this pair. |
Source: Noridian Medicare, National Correct Coding Initiative page (CMS NCCI policy).
Two modifier rules trip up groups that combine office visits and procedures. Per the Noridian summary of CMS policy, modifier 59 or an X{EPSU} modifier should not be appended to E/M services. When a separate E/M service is reported with a non-E/M service on the same date, modifier 25 is the modifier used. The same page says exceptions to bundling must be documented in the patient’s medical record.
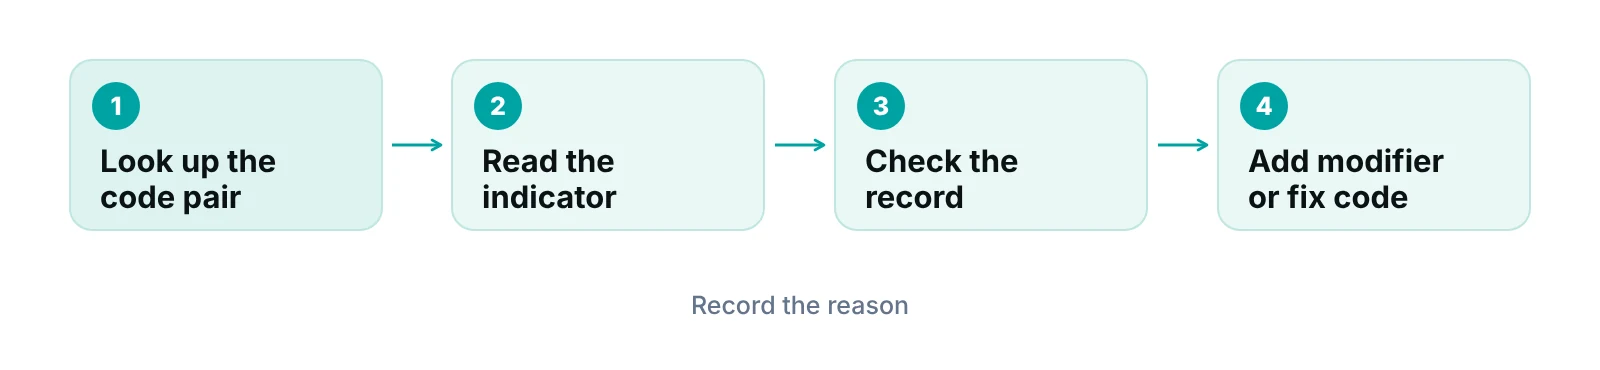
This is where specialty knowledge counts. A biller who knows dermatology will recognise a skin procedure next to an office visit. The same biller may not recognise the edit pattern in a cardiology or orthopedic claim. Our post on common medical billing mistakes lists the errors that cause most rejections, and medical billing denial management covers what to do after one lands.
One patient, several departments: keeping the claim trail clean
Patients in a group often see more than one specialty in a week. Each visit is a separate claim with its own provider, its own diagnosis and possibly its own payer rules. The billing risk is not the number of claims. It is that the data entered at the front desk is reused by every department.
- Insurance details entered once should carry to every department the same day, so one correction fixes all open visits.
- Referral and authorization records should name the department and provider they cover, not just the patient.
- Charges should be entered by the rendering provider and specialty, so the claim carries the right NPI and the right place of service.
- A shared diagnosis list helps, but each claim should still list only the diagnoses that support that visit.
Charge capture is the usual weak point because it sits between the clinical team and the billing team. Our guide to charge entry in medical billing explains how to catch a missing or mismatched charge before it becomes a late claim.
Patient statements
Patients seen in several departments often get several statements. That is a communication problem more than a coding one. We recommend deciding on one statement format and one phone number for billing questions, and writing both on every statement. Check state rules on statement content with your own compliance advisor.
Build a workflow that works for every specialty
The workflow that scales is one shared claim pipeline with specialty-specific checks added at set points. The pipeline stays the same for every department. Only the checks change. This avoids running five separate billing processes under one roof.
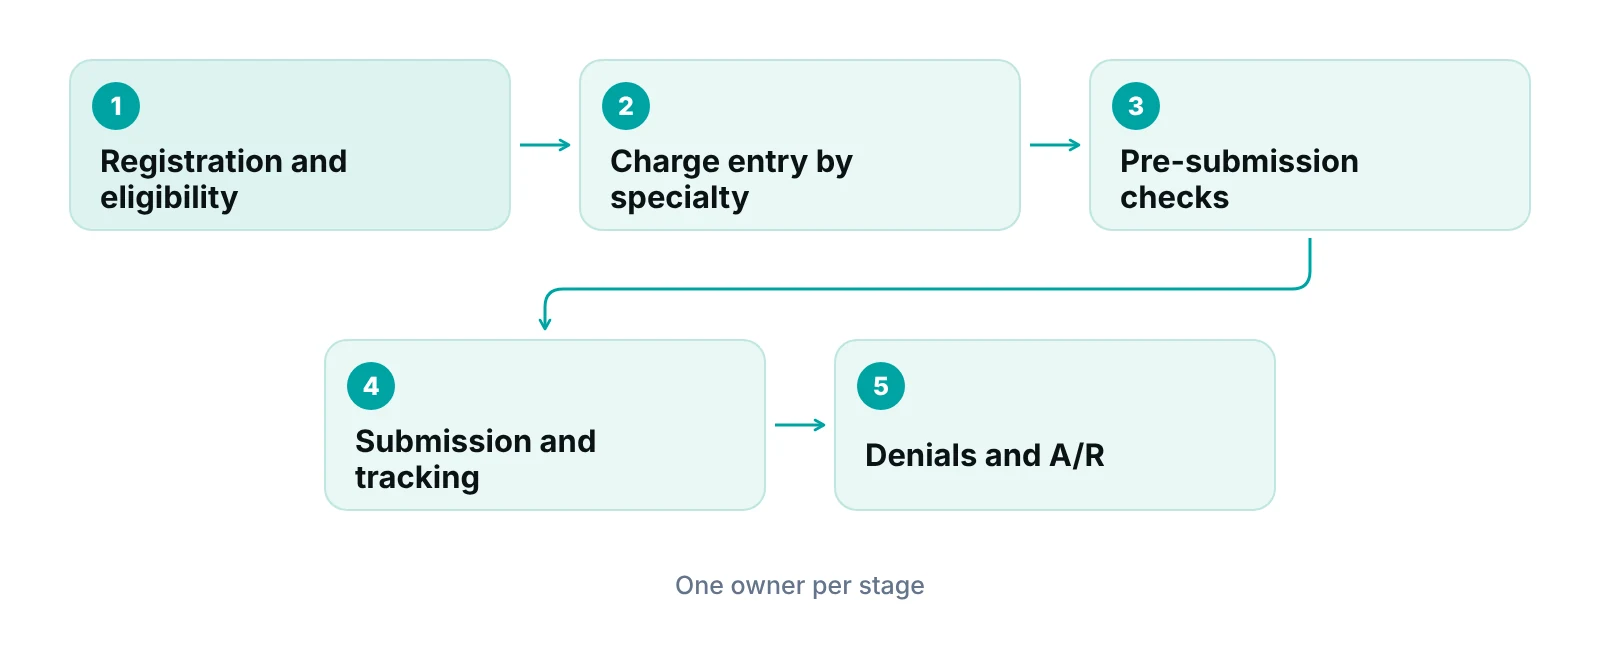
| Stage | Check | Who should own it |
|---|---|---|
| Provider setup | Enrollment and reassignment status per provider and per payer | Credentialing lead or billing manager |
| Registration | Insurance, referral and authorization named by department | Front desk lead |
| Charge entry | Rendering provider, specialty and place of service on every charge | Charge entry staff |
| Pre-submission | NCCI pair check, modifier review, split or shared visit test | Coder or billing lead |
| Follow-up | Denials sorted by specialty and by payer, with an owner for each | Denial and A/R team |
| Monthly review | Denial reasons and days in A/R by specialty and by provider | Practice manager |
Software helps when it keeps a claim at a known stage with a named owner. A practice management system that tracks claims by stage lets a manager see which specialty has claims stuck at which step. It does not replace coders or your EHR.
See where your group’s claims stall
Ask for a free practice audit. Request a review of how your claims move from charge to payment and where each specialty slows down.
In-house, outsourced or mixed: how to decide
There is no single right model. A group can keep billing in-house, hand all of it to a billing company, or split the work by stage or by specialty. The right choice depends on whether you can hire and keep coders who know each specialty, and on how well you can see what is happening to your claims today.
- In-house suits groups with enough claim volume per specialty to keep a coder busy and a manager with time to review reports.
- Full outsourcing suits groups that want fixed processes and regular reporting without recruiting a team.
- A mixed model keeps registration and charge entry in-house and sends denials or A/R follow-up to a specialist team.
Questions to ask any billing partner
- Which specialties do your coders handle today, and who reviews coding for ours?
- How do you track enrollment and reassignment status for each provider and payer?
- What reports will we receive, and how often?
- Will your team work inside the EHR we already use?
- Will you sign a Business Associate Agreement before you access patient data?
- How is pricing structured, and what happens if we want to leave?
For a longer look at what to compare, read our overview of medical billing and coding companies. If you want a team to handle claims across specialties, see our medical billing services. If your group includes neurology, our neurology billing guide shows what a single specialty needs on its own.
Our recommendations
- Track enrollment per provider and per payer. Keep a simple status list showing each provider, each payer, and the dates enrollment and reassignment took effect. Review it before scheduling a new provider’s patients.
- Write a one-page rule sheet for each setting. For each department, note where it bills (office, hospital, ED) and which rules apply there, including split or shared visits and any payer-specific policies.
- Run an NCCI check on every multi-code claim. Look up each code pair, read the modifier indicator, and add a modifier only when the record supports a distinct service.
- Make charge entry specialty-aware. Require rendering provider, specialty and place of service on every charge, and reject charges that are missing any of them.
- Split denial reports by specialty. A group-wide denial rate hides which department has the problem. Report reasons by specialty and by payer each month.
- Give each stage one owner. Name one person for each stage of the claim, and write the name next to the stage on your checklist.
Give each claim stage one owner, whatever the specialty.
Our portal tracks each claim by stage with an assigned owner, and specialty-aware billing logic is applied per claim. Reporting dashboards let a manager compare stages across departments.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Multi-specialty medical billing works when one pipeline carries every department’s claims and each specialty adds its own checks at set points. Start with enrollment, then edits, then ownership. If you want an outside review of where your claims slow down, see our medical billing services or our denial management services, or run your numbers in the revenue calculator.
Frequently asked questions
What is multi-specialty medical billing?
It is billing for a practice that offers several medical specialties under one organization. Each specialty uses its own codes, edits and payer rules, and the billing team has to apply the right set to every claim while keeping one process for the whole group.
Why is multi-specialty billing harder than single-specialty billing?
One team must know several coding patterns at once. Rules also change by setting and provider type. For example, Medicare allows split or shared visits in facility settings but not in offices, and the new-patient lookback depends on specialty within the group.
Does each provider need to be enrolled separately?
For Medicare Part B, yes. Each practitioner enrolls individually, and a reassignment lets the group bill for their services. Both the practitioner and the group’s authorized or delegated official sign to add a reassignment. Other payers have their own enrollment steps.
When do I use modifier 25 or modifier 59?
Per the Noridian summary of CMS policy, modifier 25 is used when a separate E/M service is reported with a non-E/M service on the same date. Modifier 59 or X{EPSU} should not be appended to E/M services. Your coder should confirm against the record and payer policy.
Should a multi-specialty group outsource billing?
It depends on your volume per specialty, your ability to hire coders who know each one, and how clearly you can see your claims today. Many groups outsource all of it, some keep front-end work in-house and outsource denials and A/R, and some stay fully in-house.
How do I know which specialty causes the most denials?
Report denials by specialty, by provider and by payer, and review them monthly. A group-wide rate hides local problems. Track the reason on each denial so the fix goes to the right team.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Evaluation and Management Services, MLN006764 (May 2026) — CMS (2026)
- National Correct Coding Initiative (NCCI) — Noridian Healthcare Solutions (Medicare Administrative Contractor) (2026)
- 855I, 855R Enrollment and Policy Overview — CMS (hosted by HHS)
- CMS Transmittal 12246 (CR 13366), NCCI PTP edits Version 30.0 — CMS (2024)
Disclaimer: This article is educational and is not legal, coding or compliance advice. Payer rules vary and change; check current CMS and payer policy and your own compliance advisor before acting.
