
Fall ICD-10 codes sit in W00-W19 and describe how a fall happened; they are never first-listed. For a ground-level fall, choose W01.0XX- (slip, trip or stumble, no object struck), W01.1- (object struck) or W18.30- (same-level fall, unspecified). List the injury code first, then the fall code, then place and activity codes.
Most coding errors on falls come from treating the fall code as the diagnosis. It is not. The injury (a fracture, a head injury, a sprain) is what the visit is for, and the fall code is secondary context. This guide covers which same-level fall codes exist, how to read them, how they are sequenced and what documentation lets a coder pick a specific one instead of the unspecified default. It is written for practice managers, billers and coders, and it uses the FY 2027 ICD-10-CM Official Guidelines (effective October 1, 2026) as its base.
Key takeaways
- Fall codes (W00-W19) are external cause codes and are never first-listed; the injury code goes first.
- W01.0XX- covers slips and trips with no object struck, W01.1- with an object struck, and W18.30- is the unspecified fallback.
- Unspecified usually signals missing documentation, so query the provider before defaulting.
- Seventh characters should match the associated injury code; place and activity codes follow the fall code.
- Reporting rules vary by payer and state, and codes change each October 1, so check FY 2027 files.
What fall ICD-10 codes do and do not do
A fall code is an external cause of morbidity code. It records the circumstances of an injury, not the injury itself. Chapter 20 of ICD-10-CM covers external causes (V00-Y99), and falls sit in the W00-W19 range, according to a Highmark provider article (February 2026). The injury itself is coded from Chapter 19 (S00-T88), per the table of contents of the FY 2027 guidelines.
The FY 2027 guidelines state that external cause of morbidity codes are “never to be recorded as a principal diagnosis.” That sentence appears in the hurricane-aftermath section, and Highmark’s 2026 article says the same thing in general terms: these codes “should never be sequenced as the principal or first-listed diagnosis.” In practice, a claim with only W18.30XA and no injury or condition code is a coding error.
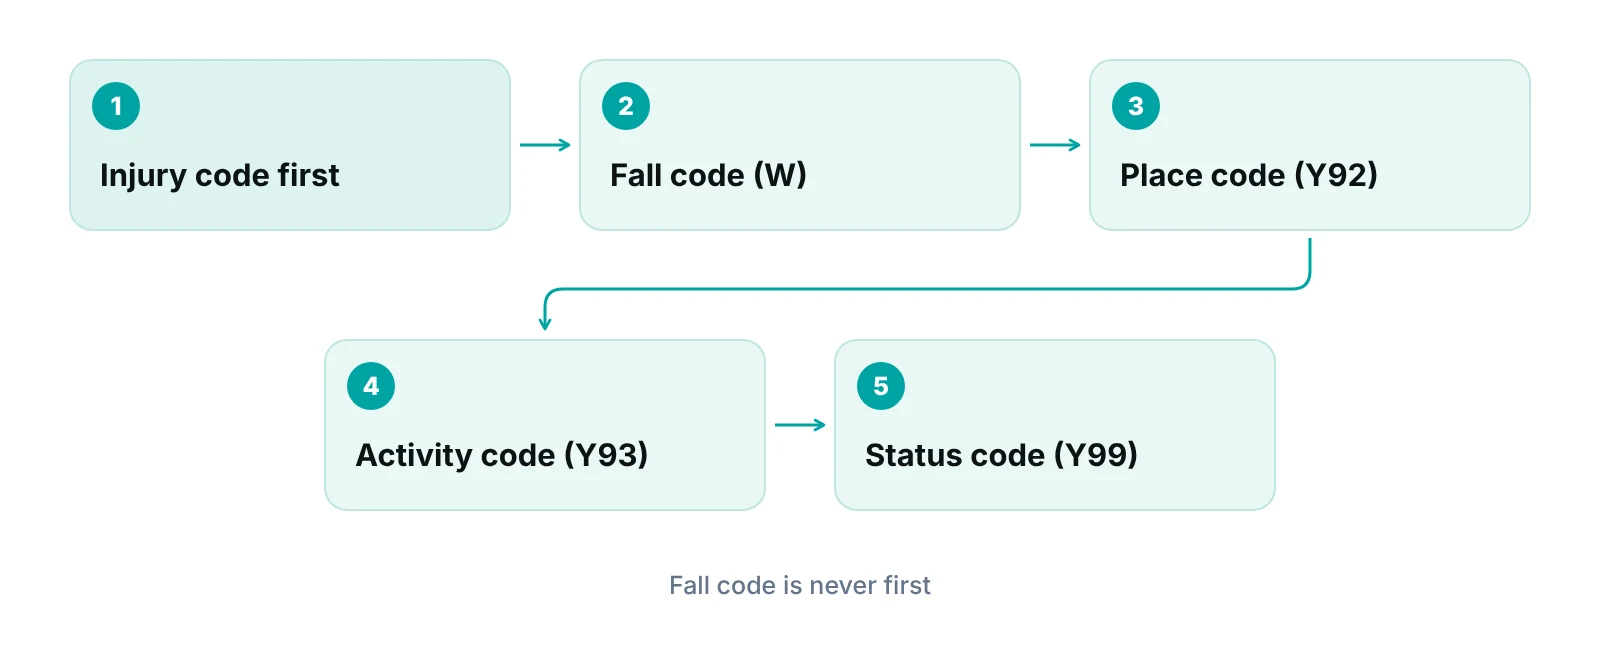
Highmark also notes that the same codes can describe the type of event, where it happened and what the patient was doing. That is why one fall can produce up to four related codes: the injury, the fall itself, the place (Y92) and the activity (Y93). A fifth, the external cause status code (Y99), is listed in the guidelines and used when status adds information.
Quick definitions
Injury code: what is wrong with the patient (Chapter 19, S00-T88). Fall code: how it happened (W00-W19). Place code (Y92) and activity code (Y93): where and during what. Only the injury code can be first-listed.
Which code fits a ground-level fall
Pick the most specific fall category the record supports, and use the unspecified code only when the record truly does not say. The categories below were checked against the AAPC code listing for W01 (2026) and the code page for W18.30XA; both are secondary mirrors of the official tabular list, so confirm final code selection in your encoder.
| Code or range | Meaning | Use it when the record says | Watch for |
|---|---|---|---|
| W01.0XXA | Fall on same level from slipping, tripping or stumbling, without striking an object | Patient slipped or tripped and hit nothing on the way down | Excludes1 notes send ice and snow to W00.0 and unspecified same-level falls to W18.30 |
| W01.1- (6th and 7th characters vary) | Same mechanism, with subsequent striking against an object | Patient slipped or tripped and hit furniture, a counter or another object | Choose the final characters from the tabular list; the object struck decides the code |
| W00.0 | Fall due to ice or snow | Weather or surface ice is documented as the cause | Listed as an exclusion at W01, so do not report both for the same event |
| W18.30XA | Fall on same level, unspecified, initial encounter | The note says only that the patient fell and gives no mechanism | Overused as a default; query the provider first |
| W18.4- | Slipping, tripping or stumbling without falling | The patient lost balance but did not fall | Not a fall code, so do not use it for a true fall |
| W18.0-, W18.1-, W18.2- | Fall due to bumping an object, off a toilet, or in a shower or bathtub | The setting or mechanism is one of these | These are separate categories; they are not W01 or W18.30 |
Source: AAPC W01 code listing (2026); Unbound Medicine ICD-10-CM page for W18.30XA (accessed October 2026). Confirm in the FY 2027 tabular list.
Some guides call W18.30XA the most frequently used fall code. That is a habit, not a coding rule, and it points coders at the least informative option. The better rule is the reverse: the unspecified code is a signal that the record is missing something.
A fall that follows a collision
A fall after bumping into another person is not a W18.3- code. In the ICD-10-CM External Cause Index (April 2022 edition), the entry for an accident between two pedestrians, with fall, points to W03. Check the index and tabular list for your date of service before assigning it. An earlier version of this post listed W18.31XA as a collision code; that descriptor was wrong and has been removed.
How to read a code like W01.0XXA
Every character in W01.0XXA does a job: the category, the mechanism, a placeholder and a final character that tells the payer which encounter this is. A short read of each piece prevents most formatting rejections.
- W01.0 names the mechanism: same-level fall from slipping, tripping or stumbling, with no object struck.
- XX are placeholders. The FY 2027 guidelines say the X is used as a placeholder to allow for future expansion, and that where a placeholder exists the X must be used for the code to be valid.
- A is the seventh character. In the California inpatient reporting manual (2020 edition), initial encounter applies “while the patient is receiving active treatment for the condition,” and the external cause seventh character should match the one on the associated injury code.
The California manual is a state reporting rule for inpatient data, not a national payer rule. Treat it as a worked example of the seventh-character logic and confirm what your own payers expect. For a broader overview of what each code set does, see our explainer on how CPT, ICD-10 and HCPCS codes differ.
Sequencing and reporting rules
The injury goes first, the fall code follows, and place, activity and status codes come after the fall code. Chapter 20 of the FY 2027 guidelines has separate subsections for place of occurrence, activity, status, multiple external causes and the case where a reporting format limits how many external cause codes fit.
| Code type | Role | What the sources say | Typical mistake |
|---|---|---|---|
| Injury (S00-T88) | First-listed diagnosis when the visit is for the injury | External cause codes are never recorded as the principal diagnosis (FY 2027 guidelines) | Leaving the injury off and billing only the fall |
| Fall (W00-W19) | How the injury happened | Code to the highest specificity available, for example slipping on ice rather than a general fall (Highmark, 2026) | Defaulting to W18.30XA |
| Place (Y92) | Where it happened | California’s manual: report once, at the initial encounter, and do not report Y92.9 | Repeating the place code on every follow-up visit |
| Activity (Y93) | What the patient was doing | Highmark: use activity codes to refine the fall, such as hiking | Adding an activity the note never states |
| Status (Y99) | Patient’s status at the time | Listed in the FY 2027 guidelines table of contents as external cause status | Assigning it without documentation |
Source: CDC/NCHS FY 2027 ICD-10-CM Official Guidelines (2026); Highmark Coding Corner (2026); California HCAI Inpatient Data Reporting Manual (2020).
Highmark’s article adds two practical points. When an event has several external factors, such as a fall from a bicycle while exercising, report all relevant external cause codes. And avoid reporting two external causes that are explicitly excluded from being reported together; it also advises a manual review alongside automated encoders because software can misread context.
“The injury explains why the patient was seen. The fall code explains how it happened. Keep those two jobs apart on the claim.”
Is reporting required?
It depends on who is asking. California requires external cause coding for inpatient discharges under its reporting manual, with specific sequencing and Y92 rules. Highmark’s article mentions regulatory compliance as one reason these codes matter but does not name payer requirements. Read each payer’s coding policy and your state’s data-reporting rules before deciding that the codes are optional.
What documentation lets a coder pick a specific fall code
A coder can only report what the clinician wrote. Most unspecified fall codes are a documentation gap, not a coding choice. A short, repeatable set of details in the note is usually enough to move from W18.30XA to a specific code.
- Mechanism: slipped, tripped, stumbled, bumped into an object, or lost consciousness first.
- Surface or cause: ice or snow, a wet floor, a rug, a step.
- Object struck: furniture, a counter, a wall, nothing.
- Place: home, clinic, street, workplace.
- Activity: walking, exercising, working, getting out of bed.
- Injury detail: the specific site and type, so the injury code can be specific too.
A simple intake prompt for the front desk or nurse covers most of these fields. Teams that also review notes before submission catch gaps earlier; our guides to claim scrubbing and clean claim basics show where that check fits.
Query, do not guess
If the note says only “patient fell,” send a short query to the provider asking how and where. Do not infer a mechanism, an object or an activity from the injury.
Falls with an unclear cause
A patient may fall because of weakness, dizziness or another condition. The fall code describes the event; the underlying condition is coded separately when the provider documents it. For that side, see our guides to ICD-10 codes for weakness and back pain coding, and the dog bite ICD-10 guide for another external-cause example.
Common fall coding mistakes and fixes
| Mistake | Why it is a problem | Fix |
|---|---|---|
| Billing only a W code | External cause codes are never the principal diagnosis (FY 2027 guidelines) | List the injury code first |
| Calling W18.31XA a collision code | The Index points a fall after a pedestrian collision to W03 | Check the Index and tabular list; do not copy descriptors from old posts |
| Defaulting to W18.30XA | It means a same-level fall with no further detail | Query for mechanism, surface and object |
| Mixing up the final character | Seventh characters should match the associated injury code (California manual) | Copy the encounter character from the injury code |
| Marking fall codes “billable: yes” and stopping there | Billability says nothing about sequencing or payer policy | Check the payer’s policy for secondary external cause codes |
| Using code lists from older code years | Codes and descriptors are revised each October 1 | Check the FY 2027 files for dates of service on or after October 1, 2026 |
Source: CDC/NCHS FY 2027 ICD-10-CM Official Guidelines (2026); CDC/NCHS External Cause of Injuries Index (2022); California HCAI (2020).
A periodic internal review catches these before payers do. Our overview of medical coding audits explains how practices sample claims, and the post on billing versus coding roles explains who should own the fix.
Why falls show up so often in coding queues
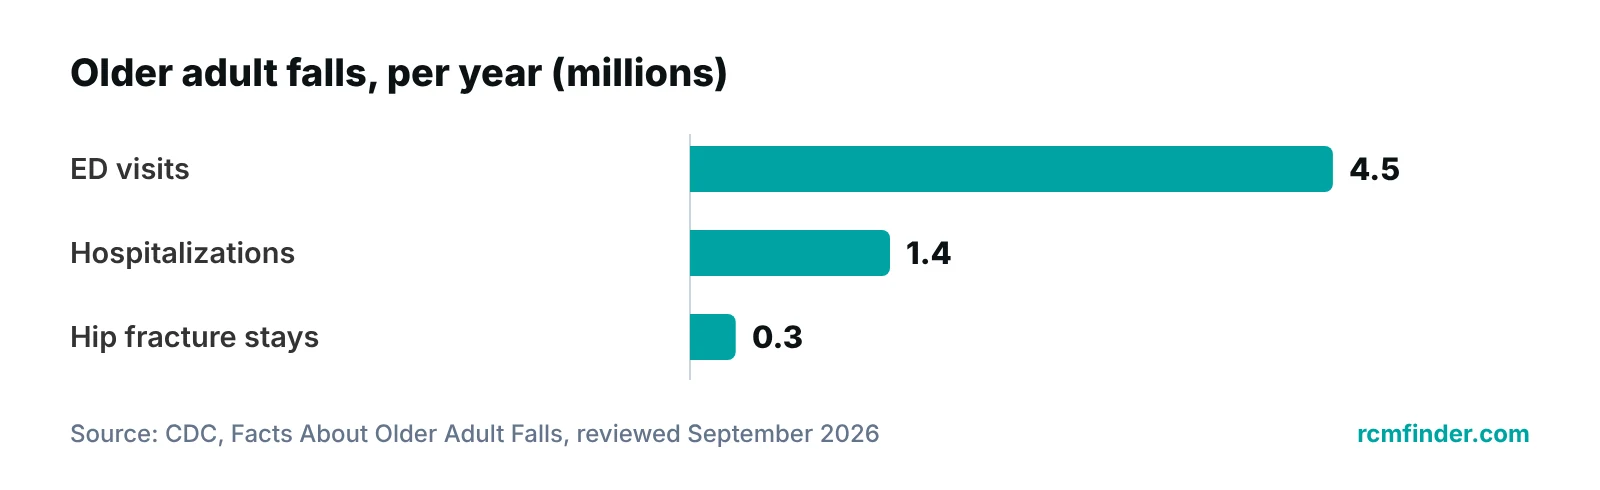
Falls are common in the older adult population most practices serve, and that volume reaches coding queues. The CDC (page reviewed September 2026) says more than one out of four older people falls each year. It reports about 4.5 million emergency department visits a year for falls (CDC WISQARS data) and about 1.4 million hospitalizations, plus nearly 319,000 hospitalizations a year for hip fractures.
The CDC’s National Center for Health Statistics reported 41,400 unintentional fall deaths among adults 65 and older in 2023, a rate of 69.9 per 100,000 population (NCHS Data Brief 532, June 2025). An earlier version of this post cited 36 million falls, 32,000 deaths and $50 billion in costs; those figures could not be confirmed against current CDC pages and were removed.
Practices with a large older-patient base can see this volume daily. Our page on geriatrics billing and RCM support covers the wider workflow, and our medical billing and coding support is there if the coding backlog is the problem.
A practical next step
Pull ten recent fall encounters and check three things: is the injury code first, is the fall code more specific than W18.30XA where the note allows it, and do the final characters match? That small review shows whether the issue is documentation, coding or claim setup. If denials are already coming back, our denial management services can help sort them by cause.
Want a second pair of eyes on your coding?
Request a free practice audit and we will look at where coding gaps and claim errors are costing you time.
Our recommendations
- Make the injury code first, every time. Add a scrubber or encoder rule that rejects any claim where the first-listed diagnosis is in V00-Y99.
- Treat W18.30XA as a query trigger. When the unspecified code is the best fit, send the provider a one-line question about how and where the fall happened before the claim goes out.
- Add fall fields to intake. Capture mechanism, surface, object struck, place and activity in a structured field or template so the coder does not have to infer them.
- Match the seventh character to the injury. Use the encounter character from the injury code on the external cause code, then check payer policy for exceptions.
- Re-check code lists each October. Replace saved code lists and cheat sheets when the new fiscal year files are published, and date every internal reference sheet.
Bottom line
Fall coding comes down to three habits: list the injury first, pick the most specific fall code the note supports, and re-check code lists each October. If your team wants help building that routine, see our medical billing and coding support and denial management services, or review the fall workflow for geriatrics practices.
Frequently asked questions
What is the ICD-10 code for a ground-level fall?
There is no single code. W01.0XX- fits a slip, trip or stumble with no object struck, W01.1- fits one with an object struck, and W18.30- is the unspecified same-level fall. Choose the most specific one the note supports, and list the injury code first.
Can a fall code be the first-listed diagnosis?
No. The FY 2027 guidelines say external cause codes are never recorded as a principal diagnosis, and Highmark’s 2026 article says the same. List the injury or condition first and add the fall code as secondary. A claim carrying only a fall code and no injury or condition code is incomplete and should be fixed before submission.
When should I use W18.30XA?
Only when the record says the patient fell on the same level and gives no mechanism, surface or object. If the note is that thin, ask the provider for detail first. The unspecified code works as a last resort, not a default. Track how often it appears in your own claims; a high share usually points to a documentation habit that can be fixed at intake.
Are fall codes required by every payer?
Not necessarily. California requires external cause coding for inpatient discharges under its reporting manual, but payers differ. Read each payer’s coding policy and your state’s reporting rules before treating the codes as optional.
Do I report Y92 and Y93 on every visit?
California’s inpatient manual says place of occurrence is reported once, at the initial encounter. Activity and status codes are also tied to the first treatment encounter reported. Confirm the rule for your payer and setting, because this example comes from a state inpatient manual and not from a national payer policy.
How common are falls among older adults?
The CDC says more than one out of four older people falls each year. It reports about 4.5 million emergency department visits and 1.4 million hospitalizations a year for older adult falls. NCHS counted 41,400 unintentional fall deaths among adults 65 and older in 2023. Check the CDC pages for the latest figures.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- ICD-10-CM Official Guidelines for Coding and Reporting, FY 2027 — CDC/NCHS (2026)
- Coding Corner: Understanding External Cause Codes — Highmark (2026)
- California Inpatient Data Reporting Manual, External Causes of Morbidity — California HCAI (formerly OSHPD) (2020)
- ICD-10-CM W01 Fall on same level from slipping, tripping and stumbling — AAPC (2026)
- W18.30XA – Fall on same level, unspecified — Unbound Medicine ICD-10-CM (2026)
- ICD-10-CM External Cause of Injuries Index — CDC/NCHS (2022)
- Facts About Older Adult Falls — CDC (2026)
- Unintentional Fall Deaths in Adults Age 65 and Older: United States, 2023 (NCHS Data Brief 532) — CDC/NCHS (2025)
Disclaimer: This article is educational and is not legal, coding or compliance advice. Code descriptors and reporting rules change each fiscal year and vary by payer and state; confirm against the current ICD-10-CM files and your payer policies before billing.
