

Timely filing limits are set by the payer, not by one state rule. Medicare allows one calendar year from the date of service, Medicaid programs publish their own limits under a federal 12-month rule, and commercial plans set theirs by contract. Read the payer's contract or manual before relying on any chart.
Search results for this topic are full of state tables. Most of them mix up two different clocks: how long a practice has to send a claim, and how long a payer has to pay it. This guide separates them, shows where each limit comes from, and ends with a routine that keeps claims from going late. For next steps after a claim is sent, see our accounts receivable guide and clean claims guide.
Key takeaways
- A timely filing limit is the last day a payer accepts a first claim, and the payer or program sets it, not usually the state.
- Medicare: one calendar year from the date of service (42 CFR 424.44). A timeliness denial cannot be appealed.
- Medicaid: the federal rule requires claims within 12 months of service; your state manual has the working detail.
- Commercial limits live in the contract, and some states add rules on top. Do not copy one plan’s number to another.
- Payer payment windows such as 30 or 45 days bind the insurer, not the practice.
What is a timely filing limit?
A timely filing limit is the last day a payer will accept a first claim for a service. It is counted from a start date, usually the date of service, and it ends on a fixed day. After that day the payer can deny the claim as late.
The word “state” in the search phrase is misleading. Most filing limits are not set by your state. Medicare sets its own. Each state Medicaid program sets its own. Commercial plans set theirs in the provider contract, and only some states put a rule on top of the contract. So the first job is to ask which payer you are billing, not which state you are in.
Filing deadlines are not payment deadlines
Many online lists of “state billing time limits” mix two different clocks. One clock tells the practice how long it has to send a claim. The other tells the payer how long it has to process and pay one. A rule that says an insurer must pay within 30 or 45 days is not a deadline for you. Keep the two apart in your own tracking.
Who sets the clock: Medicare, Medicaid or the contract?
Medicare and Medicaid publish a fixed rule. Commercial plans and most managed plans leave the number to the contract. The table below shows where each limit comes from and how the clock starts.
| Payer type | Source of the limit | Limit | What starts the clock |
|---|---|---|---|
| Original Medicare (Part B and institutional) | Federal regulation, 42 CFR 424.44 | 1 calendar year after the date of service (services on or after Jan 1, 2010) | Date of service; for institutional claims with a span of dates, the through date |
| State Medicaid fee-for-service | Federal minimum rule in 42 CFR 447.45, then the state Medicaid manual or bulletin | Federal rule: no later than 12 months from the date of service. Read your state manual for the working rule. | Date of service; a state may define it differently for institutional and professional claims |
| Commercial plans | Your provider contract, plus any state rule that applies to that plan | Set by contract; see the state examples below | Usually the date of service; read the contract for the exact trigger |
| Secondary payers | Your contract with the secondary payer | Often counted from the primary payer’s payment or notice, not from the service date | Primary payer’s explanation of benefits or notice; confirm in the contract |
Source: eCFR, 42 CFR 424.44 and 42 CFR 447.45; CMS Claims Processing Manual, Chapter 1 (2024); Michigan MDHHS bulletin MSA 16-37 (2016). Commercial and secondary rows summarize contract practice; confirm in each contract.
Original Medicare
Under 42 CFR 424.44, a Medicare claim for services on or after January 1, 2010 must be filed no later than the close of the period ending one calendar year after the date of service. The CMS Claims Processing Manual, Chapter 1, section 70 tells contractors to deny a claim for untimely filing when the receipt date is more than 12 months after the service. It also says a timeliness denial is not an initial determination, so it cannot be appealed. A Medicare administrative contractor (Noridian) page adds that a claim has to reach the payment floor to count, so a claim that is rejected on entry does not stop the clock. Fix it and resubmit inside the same year.
There are narrow exceptions. They cover an error or misrepresentation by a Medicare employee or contractor, retroactive Medicare entitlement, and retroactive disenrollment from a Medicare Advantage plan or PACE. Each has its own conditions in 42 CFR 424.44(b). Treat them as a rescue route, not a workflow.
State Medicaid
The federal rule at 42 CFR 447.45 says the Medicaid agency must require providers to submit all claims no later than 12 months from the date of service. States then publish the details in provider manuals and bulletins. Michigan is one example. A Michigan Department of Health and Human Services bulletin (MSA 16-37) sets a one-calendar-year limit, uses the line-level from date for professional claims and the through date for institutional claims, and lists exception routes such as retroactive eligibility and delayed Medicare processing. It also says late claims sent without an exception remark are denied. Your own state’s manual may differ, so read it rather than rely on a list.
Commercial plans: where state rules and contracts meet
For commercial plans the contract is the starting point. Some states add a rule that limits what a plan can put in the contract. The examples below show how different the pieces can be. They are examples, not a complete state list, and they can change.
| Example | What the source says | Applies to | What to check |
|---|---|---|---|
| Texas (Texas Department of Insurance) | Preferred and nonpreferred providers must file within 95 days of the service. Late claims are forfeited unless a certified catastrophic event caused the delay. For hospitals the 95 days starts at discharge. | Plans and provider contracts covered by the SB 418 rules (contracts renewed on or after Aug 16, 2003) | Whether the plan and your contract fall under that rule, and the current text of the Texas rules |
| California (one plan’s provider guide) | Claims are due within 180 days of the date of service or the period stated in the contract, whichever is greater. When the plan is secondary, the limit is 90 days from the primary payer’s payment or notice. | One California plan’s contracted providers | Your own contract and plan policy; do not copy this number to other plans |
| Michigan Medicaid | One calendar year from the date of service, with a short list of exceptions and a remark requirement for late claims. | Michigan Medicaid and the programs listed in the bulletin | The current Michigan provider manual and bulletin |
Source: Texas Department of Insurance, SB 418 and HB 610 comparison (2015); Blue Shield of California provider guide on AB 1455 (2024); Michigan MDHHS bulletin MSA 16-37 (2016).
The Texas document is a good illustration of why the state alone does not answer the question. The same state publishes two sets of rules, and which one applies depends on when the provider’s contract was renewed. In the California example, the number comes from a payer’s provider guide, and it already carries a “whichever is greater” clause that points back to the contract.
“A filing limit is only useful if it lives where the billing team works. A deadline in a PDF binder does not stop a late claim.”
Billing patterns also differ by specialty. A surgical practice with global periods, a behavioral health practice with recurring visits and a radiology group billing the technical and professional components all move claims through different steps before submission. See the specialty billing pages for how those workflows differ, then match the deadline to the payer, not the specialty.
Filing limit, payment deadline and appeal deadline are three different clocks
Every claim runs against three clocks. Missing the first costs you the claim. Missing the third costs you the second chance. The payer’s own payment deadline is the one you do not control, but it tells you when to start chasing.
| Clock | Who it binds | Example from a primary source | Why it matters to you |
|---|---|---|---|
| Filing limit | The practice | Medicare: 1 calendar year after the date of service (42 CFR 424.44) | Missing it usually ends the claim |
| Payer payment or decision deadline | The payer | Medicaid: the agency must pay 90% of clean practitioner claims within 30 days and 99% within 90 days of receipt (42 CFR 447.45). One California plan’s guide gives 45 working days for HMO claims. | Tells you when an unpaid claim is overdue and needs a status check |
| Appeal deadline | The practice | Set by each payer’s policy. A Medicare timely filing denial has no appeal rights. | A denied claim has its own, shorter window; do not assume the filing limit applies |
Source: eCFR, 42 CFR 424.44 and 447.45; CMS Claims Processing Manual, Chapter 1 (2024); Blue Shield of California provider guide on AB 1455 (2024).
This is where the old “45 days” and “30 days” figures in many state lists come from. Those figures are payer processing windows. They tell you when a payer is late, not when you are late. For the denial side of the story, see our guide to medical billing denial management.
Why claims actually go past the limit
Claims rarely miss a limit because nobody knew the number. They miss it because they sit somewhere nobody is looking. Four places cause most of the trouble:
- Charges not entered. The visit happened but the charge never reached the billing queue. Nothing is late yet because nothing exists.
- Held claims. A claim waits for a missing authorization, a coding question or a provider signature, and the hold has no end date.
- Rejected claims nobody saw. The clearinghouse rejects a claim for a data error. If no one reads the rejection report, the claim looks submitted when it never reached the payer. Our post on clearinghouse rejection codes explains how to read those reports, and how clearinghouses handle claims covers what the clearinghouse does and does not confirm.
- Secondary and COB claims. The primary pays, the secondary clock starts from that payment or notice in many contracts, and the balance is forgotten. See coordination of benefits in medical billing.
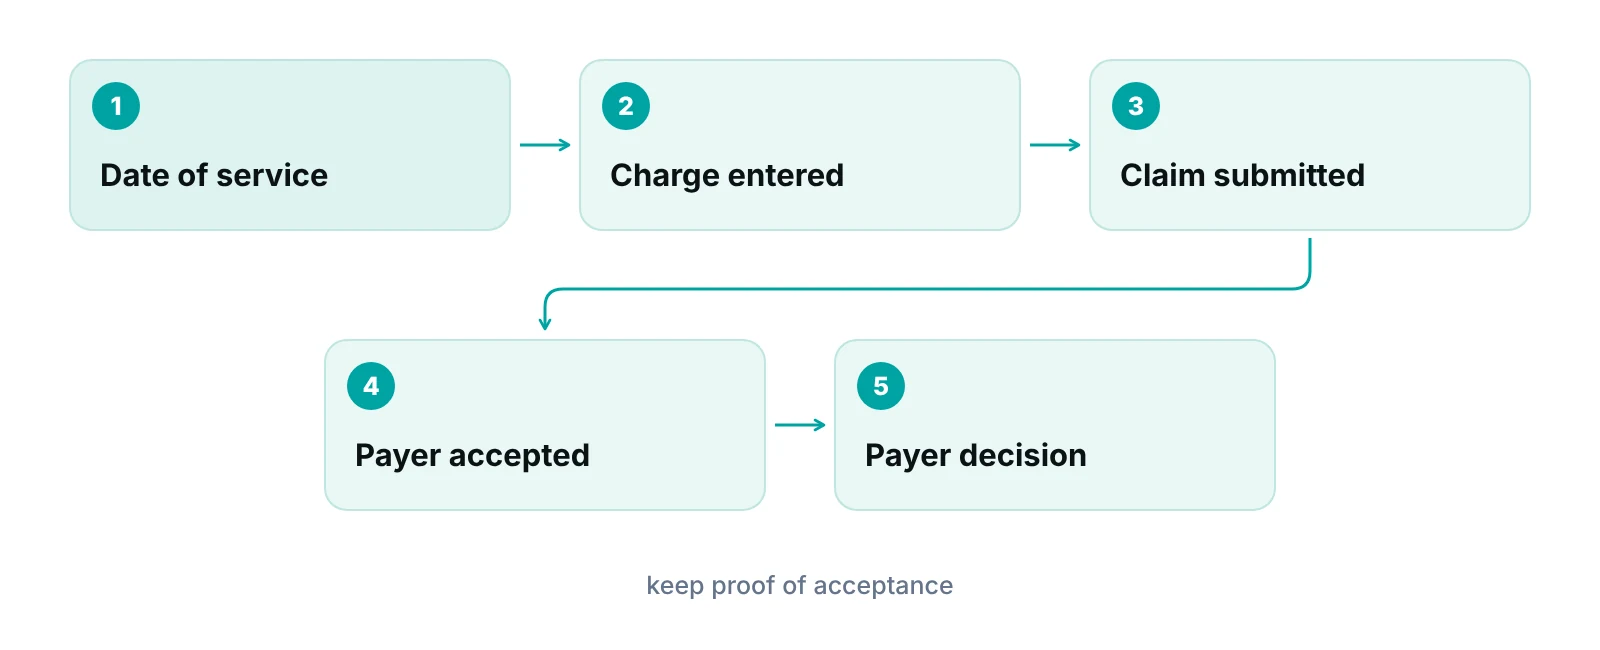
The fix is visible ownership. A claim that is waiting should show who is waiting on what, and since when. Our accounts receivable guide covers aging and the follow-up routine that catches claims after they are sent.
How to protect the deadline in your own practice
The practical answer is a short routine that makes lateness visible before it happens. You do not need a state-by-state list for this. You need a payer-by-payer list, taken from contracts and manuals you have actually read.
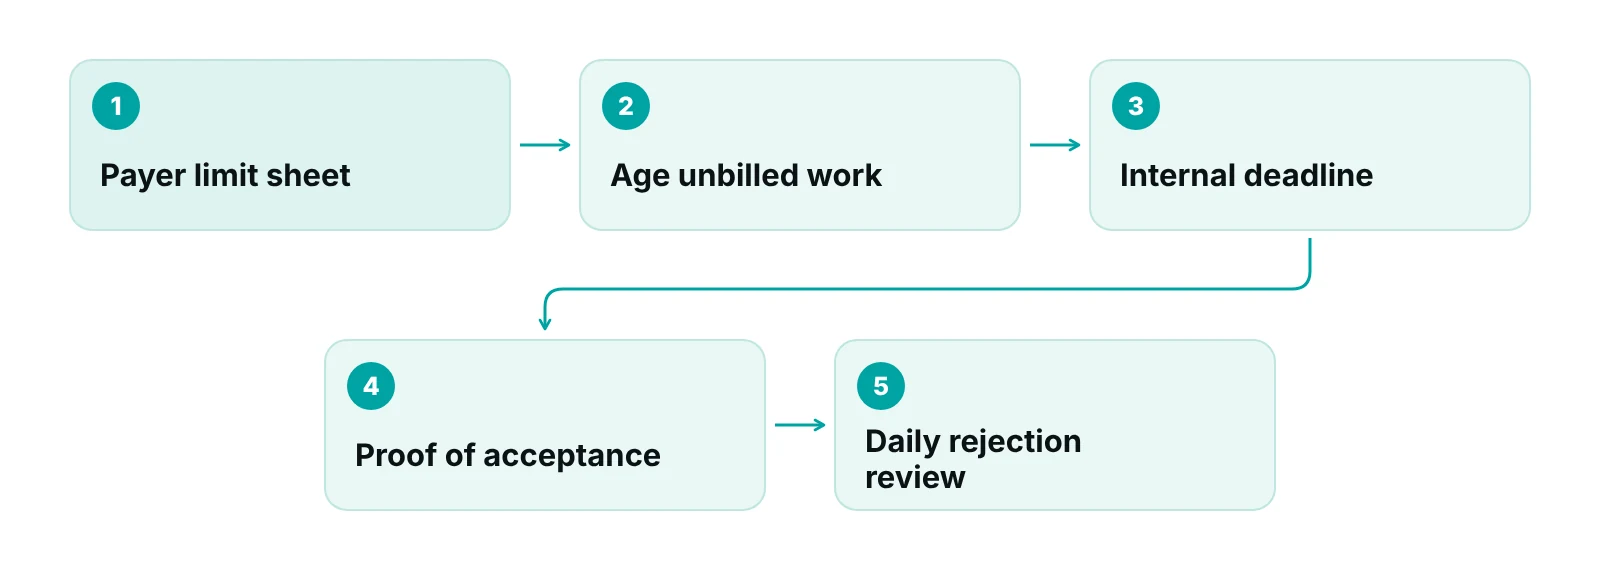
- Build a payer limit sheet. For each payer, record the filing limit, what starts the clock, the secondary-claim rule, the corrected-claim rule and the appeal window. Put the contract section or manual page next to each entry.
- Age unsent work by date of service. Report charges not yet billed and claims on hold the same way you report A/R: by days since service, against the limit for that payer.
- Set an internal deadline well before the limit. Choose a number that leaves time for a rejection to be fixed and resent. The right buffer depends on your payer mix and your clearinghouse turnaround.
- Keep proof of acceptance. Save the clearinghouse acceptance report or payer acknowledgment, not just the submission record. It is the evidence you need if a payer says it never received the claim.
- Review rejections daily. A rejected claim has not been filed. Assign an owner and a next date to every rejection.
- Review the sheet when contracts renew. Limits and secondary rules change at renewal, and so do payer policies mid-year.
Tracking claims by stage helps because a late claim is almost always one that stopped moving. A practice management system that tracks claims by stage with an owner on each claim lets a manager see which claims have not left a pre-submission stage, and workflow rules can flag claims for review. It is a claims system, not an EHR, and it works with the EHR you already use.
Use payer language when you ask
When you call a payer rep or read a portal notice, ask for the filing limit, the start date it uses and where the policy is published. Note the reference in your payer sheet. A phone answer without a reference is hard to rely on later.
What to do when a claim is already late
Check first whether the claim is actually late. Then check whether an exception applies. Only after that decide whether it is a write-off. The order matters because many “late” claims turn out to have an earlier submission on record.
- Find the first submission. Look for a clearinghouse acceptance report, a payer acknowledgment or an earlier remittance. Proof of an earlier accepted claim may change the answer.
- Identify the payer type. Medicare timeliness denials are not appealable under CMS Chapter 1. Medicaid and commercial payers have their own processes, which you should confirm in the manual or contract.
- Check the exceptions. Medicare exceptions are listed in 42 CFR 424.44(b). Michigan Medicaid’s bulletin lists its own. A commercial contract may allow a late-filing review for payer error or a coordination of benefits delay. Confirm what yours allows.
- Submit with the exception documented. If an exception applies, include the required remark or form for that payer. The Michigan bulletin shows late claims without a remark are denied.
- Record the root cause. Whether the claim is recovered or written off, note why it was late so the same gap does not repeat.
Write-off rules for a timely filing denial depend on your payer contract and applicable law, so confirm them with the payer and a qualified advisor before adjusting or billing the patient. If late claims are recurring, a medical billing services partner or an internal charge-capture review can help close the gap.
Not sure which claims are close to their limit?
A free practice audit looks at your charge-to-claim timing, rejections and A/R by payer, and shows where claims sit before they are sent.
Our recommendations
- Read the contract, then the manual. Start with the payer contract and the Medicare or Medicaid manual that applies to the claim. Treat any third-party list of state limits as a prompt to check, never as the answer.
- Make one payer limit sheet. List each payer’s filing limit, start date, secondary rule, corrected-claim rule and appeal window, with the source page beside each. Give one person ownership and review it at renewal.
- Age unbilled work. Report charges not yet billed and claims on hold by days since the date of service, against each payer’s limit, not just by total days.
- Count acceptance, not sending. Treat a claim as filed only when the clearinghouse or payer has accepted it. Review rejection reports every working day.
- Set an internal deadline well inside the limit. Pick a buffer that leaves room to fix and resend a rejected claim. Adjust it when a payer or clearinghouse slows down.
- Document every late-claim reason. When a claim is recovered or written off, record the cause. A short monthly review of those causes shows which step needs fixing.
A practice management system built around claims, not charts.
RCM Finder's portal tracks every claim by stage with an owner and applies workflow rules that flag claims for review. It is a claims system, not an EHR.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Timely filing is mostly a tracking problem. Find the limit for each payer from its contract or manual, count the days from the right start date, and keep proof the claim was accepted. If late claims are a recurring cost, our denial management services and medical billing services can help you find where claims stall, and you can estimate what unbilled work is worth with the revenue calculator.
Frequently asked questions
How long do I have to file a Medicare claim?
For services on or after January 1, 2010, a Medicare claim must be filed within one calendar year after the date of service under 42 CFR 424.44. A claim denied for untimely filing is not appealable under the CMS manual. Narrow exceptions exist, such as an error by a Medicare contractor. Confirm the details with your contractor.
Is there one timely filing limit for each state?
No. Medicare and each state Medicaid program set their own limits, and commercial plans set theirs by contract. Some states add rules that apply to certain plans, as Texas does. The practical approach is a payer-by-payer list built from contracts and manuals, not a single state number.
Are the 30-day and 45-day state deadlines I see online filing limits?
Usually not. Many of those figures are payer payment or decision windows, which bind the insurer. A filing limit binds the practice. Medicaid’s federal prompt-pay standard is one example of a payer clock. Check whether a figure binds you or the payer before putting it on your calendar.
What is the timely filing limit for secondary claims?
It depends on the secondary payer’s contract or policy. Some payers count from the primary payer’s payment or notice date instead of the date of service. One California plan’s provider guide, for example, gives 90 days from the primary’s payment or notice. Confirm each payer’s rule and keep the primary’s remittance on file.
Can I bill the patient if a claim is denied for late filing?
Not automatically. Whether you can depends on your payer contract, program rules and state law. Check the contract and program rules, and get advice, before sending a statement. This post is general information, not legal advice.
Does a rejected claim count as filed?
Usually not. A Medicare contractor page explains that a rejected claim never enters processing and must be corrected and resubmitted within the filing period. Treat a claim as filed only after the payer or clearinghouse accepts it, and keep the acceptance report.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- 42 CFR 424.44 – Time limits for filing claims — eCFR / U.S. Government (current)
- Medicare Claims Processing Manual, Chapter 1, section 70 (Rev. 12909) — CMS (2024)
- Timely Filing (Part B, Jurisdiction F) — Noridian Healthcare Solutions (Medicare administrative contractor) (n/d)
- 42 CFR 447.45 – Timely claims payment — eCFR / U.S. Government (current)
- Bulletin MSA 16-37: Timely filing of Medicaid claims — Michigan Department of Health and Human Services (2016)
- SB 418 and HB 610 prompt pay comparison — Texas Department of Insurance (2015)
- Provider guide on AB 1455 timelines — Blue Shield of California (2024)
Disclaimer: This post is general educational information about medical billing operations. It is not legal, coding or compliance advice. Filing limits, exceptions and state rules vary by payer, contract and program and can change. Confirm requirements in your payer contracts, current manuals and with a qualified advisor before acting.
