
Moderate sedation CPT codes 99151-99157 are chosen by three facts: who gives the sedation, whether the patient is under 5 or 5 and older, and the documented intraservice minutes. The physician doing the procedure reports 99151-99153, a different physician reports 99155-99157, and sedation under 10 minutes is not reported.
Most readers arrive with one question: which sedation code goes on the claim, and how many units? This guide answers it in order. We cover the code families, who may report them, how to count minutes, the Medicare exception called G0500, and the checks that keep these lines from coming back denied. Emergency department cases have their own workflow, so we cover them in our guide to coding moderate sedation in the emergency department instead of repeating them here.
The AMA owns the official CPT wording, so we describe each code in our own words. The rules below come from a CMS transmittal, GI-society and American College of Surgeons coding guidance, and three payer policies we read in October 2026. Some of those sources date from 2017 and 2023, so confirm against the current CPT book and each payer before you act.
Key takeaways
- Two families: 99151-99153 when the physician doing the procedure also sedates; 99155-99157 when a different physician sedates.
- Age splits only the first 15-minute code: under 5 (99151, 99155) versus 5 or older (99152, 99156). The add-ons have no age split.
- Under 10 minutes is not reported. The first add-on unit starts at minute 23, then one more every 15 minutes.
- Medicare GI endoscopy uses G0500 instead of 99152 for patients 5 and older.
- Many denials trace to missing times, a missing observer note, or a payer-specific rule on place of service or code choice.
What do moderate sedation CPT codes 99151-99157 cover?
They cover moderate sedation given by a physician or other qualified health care professional, counted in time and split by patient age. There are two families. 99151, 99152 and add-on 99153 are for the clinician who also performs the procedure. 99155, 99156 and add-on 99157 are for a different clinician who provides the sedation for someone else’s procedure (GI CPT Advisors, 2017).
Each family has an initial code for the first 15 minutes of intraservice time and an add-on for each further 15 minutes. Only the initial code is split by age. The published descriptors list no age qualifier for the add-ons.
| Code | Who provides the sedation | Patient age | What it counts | Type |
|---|---|---|---|---|
| 99151 | Same physician or qualified professional who performs the procedure | Younger than 5 | First 15 minutes | Initial code |
| 99152 | Same physician or qualified professional who performs the procedure | 5 or older | First 15 minutes | Initial code |
| +99153 | Same physician or qualified professional who performs the procedure | No age split | Each additional 15 minutes | Add-on |
| 99155 | A different physician or qualified professional | Younger than 5 | First 15 minutes | Initial code |
| 99156 | A different physician or qualified professional | 5 or older | First 15 minutes | Initial code |
| +99157 | A different physician or qualified professional | No age split | Each additional 15 minutes | Add-on |
| G0500 | Same physician, Medicare GI endoscopy | 5 or older | First 15 minutes, used in place of 99152 | Initial code (HCPCS) |
Source: American College of Surgeons, ACS Bulletin (January 2017); GI CPT Advisors, 2017 CPT Coding Update; CMS Transmittal 3763 (2017). CPT is a trademark of the AMA.
What these codes do not cover
Moderate sedation codes are not for pain-control medication alone, minimal sedation (anxiolysis), deep sedation or monitored anesthesia care. Anesthesia services fall under codes 00100-01999 (GI CPT Advisors, 2017). Our anesthesia billing guide covers that side.
Who reports which code: the physician doing the procedure or someone else?
The physician or qualified professional who performs the diagnostic or therapeutic procedure and also provides the sedation reports 99151, 99152 and 99153. A different physician or qualified professional, such as an anesthesiologist, reports 99155, 99156 and 99157. When a different clinician sedates, the proceduralist reports only the procedure code (American College of Surgeons, 2017).
What is the independent trained observer rule?
For the same-physician codes, an independent trained observer must be present to help monitor the patient’s level of consciousness and physiological status. The sedating physician supervises and directs that observer, and GI-society guidance says this is usually a registered nurse (GI CPT Advisors, 2017).
The observer rule does not apply the same way to every code. Moda Health’s policy notes that the 99155-99157 descriptors do not mention an observer (Moda Health). Even so, at least one Medicaid plan policy expects documentation of an observer for both families (Louisiana Healthcare Connections). The safe habit is to document an observer in every case and then read the payer’s policy.
Can the place of service change payment?
Yes, for some payers. A Blue Cross Minnesota commercial policy effective October 2, 2023 limits 99155-99157 to facility settings and says they are not eligible for reimbursement in a nonfacility setting such as a physician office (Blue Cross Minnesota). The Louisiana Healthcare Connections policy takes the same position. Medicare and other payers may differ, so build the rule per payer.
Emergency departments add their own workflow and documentation questions. We cover them in our guide to coding moderate sedation in the emergency department, so this post stays on the general rules.
How do you count moderate sedation time?
Count intraservice time, not total time in the room. It starts when the sedating agent is given. It ends when the procedure is finished, the patient is stable for recovery, and the sedating clinician stops continuous face-to-face contact (American College of Surgeons, 2017). GI-society guidance adds that this clock is separate from the procedure’s own intraservice time (ASGE).
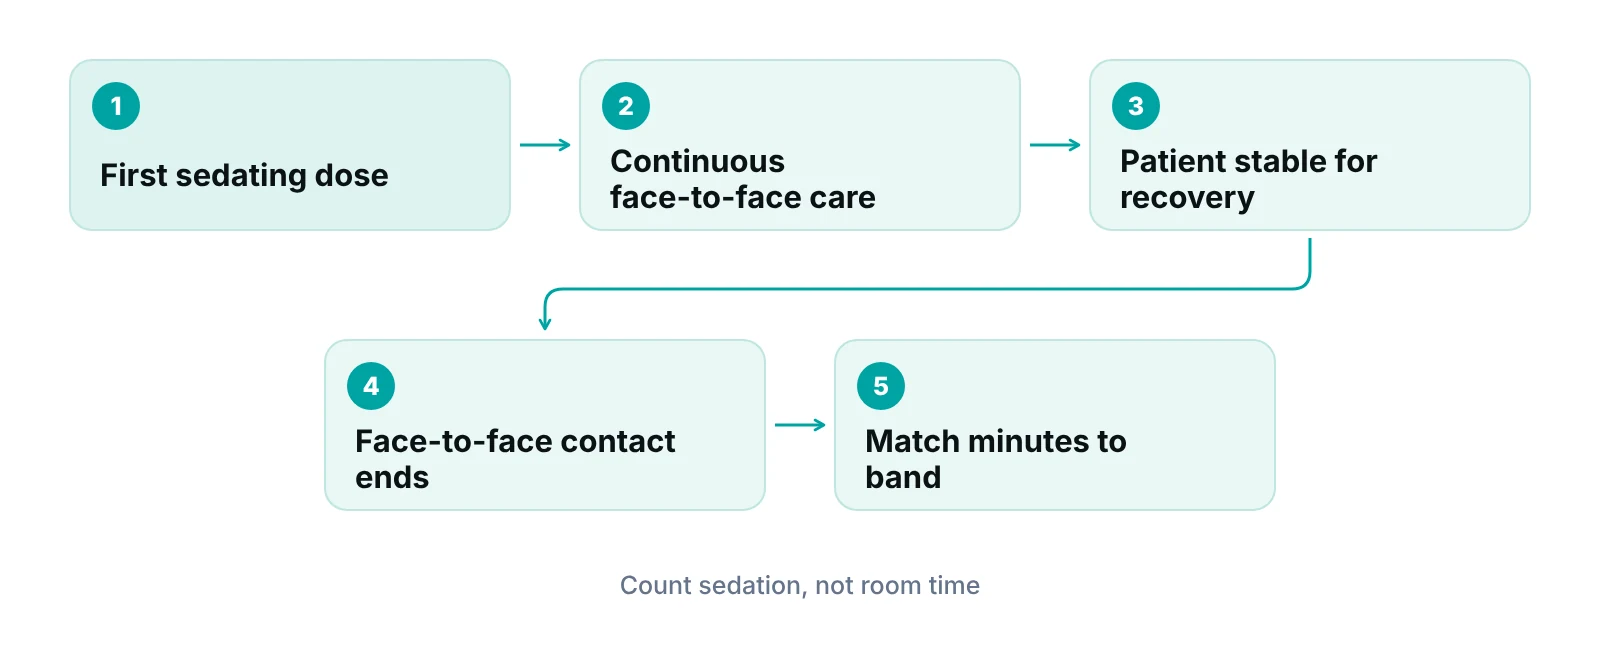
If the total is under 10 minutes, do not report moderate sedation at any age. From 10 minutes, the initial code covers 10 to 22 minutes. The published band tables then add one add-on unit at minute 23, and one more for each further 15 minutes (GI CPT Advisors, 2017). The table below extends that pattern past 82 minutes.
| Intraservice minutes | Same physician, under 5 | Same physician, 5 or older | Different physician (under 5 / 5 or older) |
|---|---|---|---|
| Under 10 | Not reported | Not reported | Not reported |
| 10 to 22 | 99151 | 99152 | 99155 / 99156 |
| 23 to 37 | 99151 + 99153 x1 | 99152 + 99153 x1 | 99155 / 99156 + 99157 x1 |
| 38 to 52 | 99151 + 99153 x2 | 99152 + 99153 x2 | 99155 / 99156 + 99157 x2 |
| 53 to 67 | 99151 + 99153 x3 | 99152 + 99153 x3 | 99155 / 99156 + 99157 x3 |
| 68 to 82 | 99151 + 99153 x4 | 99152 + 99153 x4 | 99155 / 99156 + 99157 x4 |
| 83 to 97 | 99151 + 99153 x5 | 99152 + 99153 x5 | 99155 / 99156 + 99157 x5 |
| 98 or longer | One more 99153 for each further 15 minutes | One more 99153 for each further 15 minutes | One more 99157 for each further 15 minutes |
Source: GI CPT Advisors, 2017 CPT Coding Update (same-physician bands to 82 minutes, then one add-on per further 15 minutes); ACS Bulletin (January 2017). The different-physician column applies the same initial-plus-15-minute structure. For Medicare GI endoscopy, G0500 replaces 99152.
Worked examples
- 8 minutes, any age: nothing is reported, because the total is under 10.
- 33 minutes, patient 42, same physician: 99152 plus one unit of 99153. The last 3 minutes do not create another unit (Physicians Practice, 2017).
- 45 minutes, patient 3, same physician: 99151 plus two units of 99153.
- 60 minutes, patient 7, anesthesiologist sedates for another physician’s procedure: 99156 plus three units of 99157.
Age changes only the first line. A 4-year-old and a 40-year-old with the same 45 minutes of sedation by the same physician both get two units of 99153. The initial code is the only difference: 99151 for the child, 99152 for the adult.
What changes for Medicare GI endoscopy: G0500 instead of 99152?
For Medicare patients 5 or older, when the same physician provides sedation for a GI endoscopic service, report G0500 instead of 99152 for the first 15 minutes. Add 99153 for additional time as the bands require. G0500 is not used under age 5 (CMS Transmittal 3763; American College of Surgeons, 2017). Which endoscopic services qualify is CMS’s decision, so ask your coder to pull the current list rather than relying on a memorized one.
Other payers differ. Moda Health’s policy, updated April 2026, denies 99152 with GI endoscopy procedures and requires G0500 (Moda Health). The American College of Surgeons notes that non-Medicare payers may recommend different codes (American College of Surgeons, 2017). Keep a payer-by-payer rule instead of one global setting.
One more Medicare detail matters for screening colonoscopy. When modifier 33 is on a G0500 or 99153 line, CMS tells contractors not to apply deductible or coinsurance. When the screening turns diagnostic and modifier PT is used, only the deductible is waived. Without either modifier, both still apply (CMS Transmittal 3763).
If you run a GI practice, our gastroenterology billing and RCM support page shows how we think about the wider claim, of which sedation is one line.
Is moderate sedation bundled into the procedure code?
Under CPT, no longer. Since January 1, 2017, CPT does not define moderate sedation as an inherent part of any procedure, so it is reported separately when the rules are met (Physicians Practice, 2017). The American College of Surgeons reports that CPT lowered the work values of many procedure codes at the same time, by 0.10 for most GI endoscopy codes and 0.25 for most other codes, because sedation payment moved to the sedation codes (American College of Surgeons, 2017).
Payer policy does not always follow CPT. Moda Health notes that some contracts on a 2016 or earlier fee schedule do not pay 99151-99157 with procedures on the old Appendix G list (Moda Health). The Louisiana Healthcare Connections policy still refers to Appendix G procedures too (Louisiana Healthcare Connections). If a sedation line denies as bundled, ask which edit or contract term applies before you rebill.
Which sedation claims get denied, and what should you check first?
A handful of causes explain most sedation problems we would look at first. The table lists them with the check that catches each one. We do not quote a national denial rate for sedation codes because we found no sourced figure.
| Denial trigger | Why it happens | Check before submitting |
|---|---|---|
| 99152 on a GI endoscopy claim | Medicare, and some other payers, want G0500 as the initial code | Confirm the payer rule and that the patient is 5 or older; report G0500, not 99152, where required |
| Sedation time missing, or under 10 minutes | The units cannot be rebuilt from the note, or no code applies | Find a start time and an end time in the record; report nothing under 10 minutes |
| No observer in the note | The same-physician codes require an independent trained observer; some payers ask for one in both families | Look for the observer’s name or role and a statement that the patient was monitored |
| 99155-99157 from an office setting | Some payers pay the different-physician codes only in facility settings | Compare the place of service with the payer’s policy before billing |
| Sedation billed alongside anesthesia services | Deep sedation and monitored anesthesia care belong to anesthesia codes, not moderate sedation | Match the documented level of sedation and the billing clinician to the code family |
| Add-on without the matching initial code | +99153 and +99157 are listed in addition to an initial code from the same family | Pair 99153 with 99151, 99152 or G0500, and 99157 with 99155 or 99156 |
Source: CMS Transmittal 3763 (2017); Moda Health policy RPM048 (updated April 2026); Blue Cross Minnesota payment policy (effective October 2023); Louisiana Healthcare Connections policy LA.PP.015 (reviewed April 2026). These are examples, not every payer’s rule.
These checks work best as edits that run before submission, which is what claim scrubbing rules are for. A periodic sample review, as described in our overview of medical coding audits, shows whether the edits are catching the right claims.
Not sure where your sedation claims stall?
A free practice audit looks at how your procedure notes, coding and claim edits line up, so you can see which of the checks above need work first.
What should the procedure note show to support the codes?
The note must let an auditor rebuild the units without guessing. Payer policies and society guidance point to the same items:
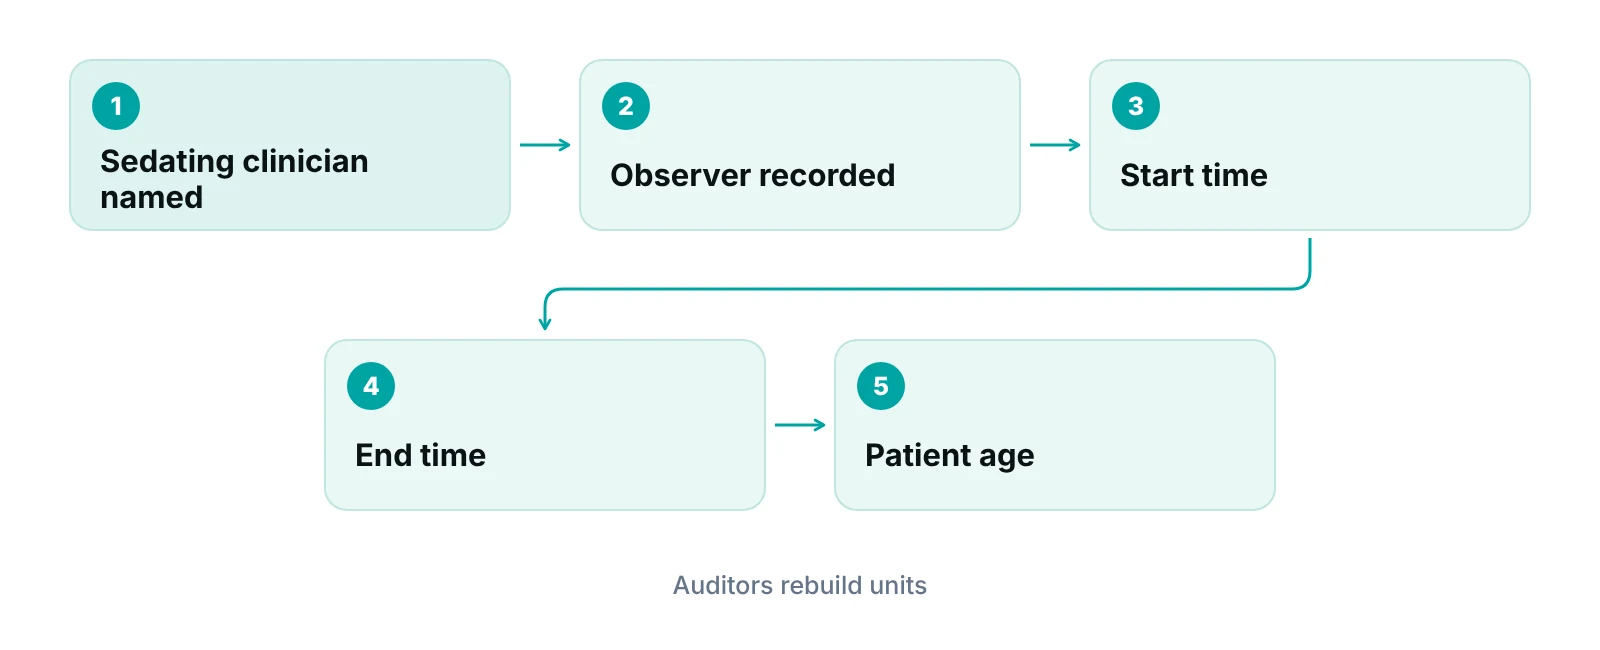
- Who provided the sedation. The record should identify the professional or professionals who provided it (Blue Cross Minnesota).
- Start and end times. The start is the first sedating dose and the end is when the patient is stable and face-to-face contact stops. GI-society guidance describes time-tracker entries or a short line such as “mod sed 28 min” in the procedure report (GI CPT Advisors, 2017).
- The observer. Name or describe the independent trained observer. One plan’s policy says a note that the nurse continuously monitored the patient supports billing, while a note that the physician monitored personally does not (Louisiana Healthcare Connections).
- Patient age. The initial code depends on whether the patient is under 5.
- Level of sedation. The note should be consistent with moderate sedation and not deep sedation or monitored anesthesia care.
Remember what the codes already include. Payer policy lists assessment before sedation, starting IV access, giving the agents, monitoring oxygen saturation, heart rate and blood pressure, and recovery until the patient is stable as integral to the sedation service, not billable separately (Louisiana Healthcare Connections). Our post on why clear documentation protects revenue explains the wider habit.
What should you do next?
Pull your last 20 sedation claims and compare them with the denial table above: age against the initial code, minutes against the band, observer against the note, and place of service against each payer’s policy. If your team prefers to hand coding and follow-up to specialists, our medical billing services include coding support and claim follow-up.
Put a number on denied and delayed claims
Use our revenue calculator to estimate what repeat denials cost before you decide which process to fix first.
Our recommendations
- Put sedation fields in the procedure template. We would add required fields for the sedating clinician, first-dose time, end time, observer and level of sedation. Most of the denial triggers above are visible in the note before a coder ever opens the claim.
- Write a one-page payer sheet. For each payer you bill most, record whether it wants G0500 or 99152 for GI endoscopy, whether it pays 99155-99157 in an office, and whether it expects an observer for both families.
- Turn the rules into claim edits. We would flag G0500 on patients under 5, an add-on without its initial code, sedation lines with under 10 documented minutes, and 99155-99157 from office places of service.
- Keep anesthesia-provider cases separate. If an anesthesia professional provides deep sedation or monitored anesthesia care, the claim belongs under anesthesia codes. Check the documented level of sedation before assigning a sedation family.
- Let the coder set the units. The clinician documents times; the coder converts them to units from the band table. Disagreements go back to the clinician for the record, not into a guess.
- Re-check each January. CPT and CMS update annually. Compare the descriptors, the G0500 qualifying procedures and your payer sheet with the new books each January, then audit a small sample.
Bottom line
Moderate sedation CPT codes reward careful role, age and time documentation: the physician doing the procedure uses 99151-99153, a different physician uses 99155-99157, and Medicare GI endoscopy uses G0500 in place of 99152. Fix the note template and the claim edits first, then audit a sample. If sedation lines keep coming back, our denial management services can work them by cause, or you can talk to our team.
Frequently asked questions
What is the difference between 99152 and 99156?
Both are initial codes for the first 15 minutes of sedation in a patient 5 or older. 99152 is reported by the same physician who performs the procedure. 99156 is reported by a different physician who provides the sedation. The time bands are the same, and the add-on is 99153 for the first and 99157 for the second.
How many minutes of sedation do you need to bill?
At least 10 minutes of intraservice time. Under 10 minutes, nothing is reported at any age. Ten to 22 minutes is the initial code alone. The first add-on unit starts at minute 23, and each further 15 minutes adds one more, according to the published GI-society and ACS band tables.
Can I bill 99153 by itself?
No. 99153 is an add-on code listed in addition to an initial code from the same family: 99151, 99152 or, for Medicare GI endoscopy, G0500. The different-physician add-on, 99157, pairs the same way with 99155 or 99156. Without an initial code, there is nothing for the add-on to attach to.
Do 99155-99157 need an independent trained observer?
The CPT descriptors for the different-physician codes do not mention one, according to Moda Health’s policy. The same-physician codes do require it. Some payers still expect an observer to be documented for both families, so record one in every case and check each payer’s policy before relying on the descriptor alone.
Should Medicare GI endoscopy use 99152 or G0500?
For Medicare patients 5 or older, when the endoscopist provides the sedation for a qualifying GI endoscopic service, CMS instructs G0500 in place of 99152. Add 99153 for extra time. Some other payers also require G0500, others do not, so confirm each payer. G0500 is not used under age 5.
Can I report these codes when an anesthesiologist gives propofol?
Usually not. GI-society guidance says propofol sedation by an anesthesia professional is typically deep sedation, reported with anesthesia codes, and that moderate sedation codes are not for deep sedation or monitored anesthesia care. Match the code to the documented level of sedation and the billing clinician, and check the payer’s policy.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- 2017 CPT Coding Changes (ACS Bulletin, Vol. 102, No. 1) — American College of Surgeons (2017)
- 2017 CPT Coding Update: Moderate Sedation 99151-99157 and G0500 — GI CPT Advisors for ACG, AGA and ASGE (2017)
- Moderate Sedation for GI Services — ASGE (2017)
- Transmittal 3763, CR 10075: Payment for Moderate Sedation Services Furnished with Colorectal Cancer Screening Tests — CMS (2017)
- Coding for Moderate Sedation is Different in 2017 — Physicians Practice (2017)
- Moderate (Conscious) Sedation, RPM048 — Moda Health (2026)
- Administration of Moderate (Conscious) Sedation, Anesthesia Services-002 — Blue Cross Minnesota (2023)
- Moderate Conscious Sedation, LA.PP.015 — Louisiana Healthcare Connections (2026)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. CPT codes are owned by the AMA, and code descriptors, payer policies and federal rules change and vary by payer and state. Verify current requirements with the official CPT manual, your payers and your counsel before you act.
