
Medicare sequestration is a 2% cut to Medicare fee-for-service payments for services on or after April 1, 2013, paused from May 2020 to March 2022. As of October 2026 it is in effect. It reduces Medicare's payment, not the patient's share, and appears on the remittance as CARC 253.
You open a Medicare remittance and the payment is a little short. The adjustment line reads CARC 253. Nothing is wrong with the claim. It is sequestration, a 2% cut taken from Medicare’s payment.
This guide explains what the cut is, whether it still applies, how to calculate it and how to post it. For the wider picture of Medicare payment changes, see our post on Medicare payment cuts.
Key takeaways
- Sequestration cuts Medicare fee-for-service payments by 2%, for dates of service or discharge on or after April 1, 2013.
- It was paused May 1, 2020 to March 31, 2022, ran at 1% April to June 2022 and has been 2% since July 1, 2022.
- The 2% comes off Medicare’s payment after deductible and coinsurance; the patient’s share does not change.
- It appears as CARC 253: claim level for Part A institutional claims, line level for Part B and outpatient claims.
- Medicare Advantage plans follow their provider contracts, so read each one.
What is sequestration in medical billing?
Sequestration is an automatic 2% reduction in what Medicare pays on fee-for-service claims. It comes from the Budget Control Act of 2011. A sequestration order was issued on March 1, 2013, and the reduction applies to claims with dates of service or discharge on or after April 1, 2013 (Noridian Medicare, CMS Transmittal 2739).
It is not a denial, a coding error or a payer policy a practice can negotiate. It is a statutory cut taken from the final Medicare payment. Contractor guidance based on CMS instructions says the law provides no exemptions for drugs or any other item or service under fee-for-service Medicare (CGS Medicare).
Three terms to know
- Sequestration: the across-the-board cut, capped at 2% for Medicare by statute.
- CARC 253: the claim adjustment reason code that reports the cut on the remittance.
- Date of service or discharge: the date that decides whether a claim is reduced, not the date Medicare processes it.
It applies to Original Medicare payments under both Part A and Part B. Our explainer on Medicare Part A versus Part B covers what each part pays for.
Is the Medicare 2% sequestration still in effect in 2026?
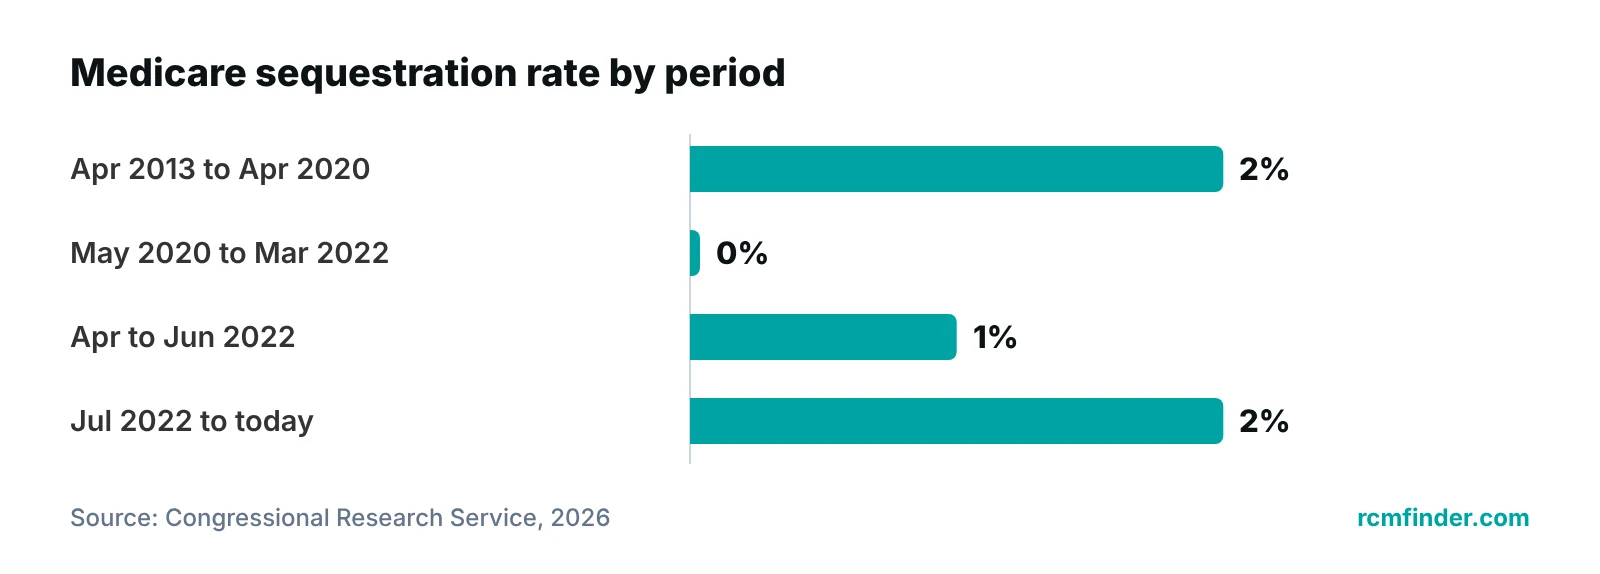
Yes. As of October 2026, Medicare fee-for-service payments are still reduced by 2%. The cut was paused from May 1, 2020 through March 31, 2022, ran at 1% from April 1 to June 30, 2022, and has been 2% since July 1, 2022.
| Period | Medicare reduction | What set it |
|---|---|---|
| April 1, 2013 to April 30, 2020 | 2% | Budget Control Act of 2011; sequestration order of March 1, 2013 |
| May 1, 2020 to March 31, 2022 | 0% (suspended) | CARES Act, extended by P.L. 116-260, P.L. 117-7 and P.L. 117-71 |
| April 1 to June 30, 2022 | 1% | P.L. 117-71 (December 10, 2021) |
| July 1, 2022 to today (October 2026) | 2% | Statutory 2% limit returned |
| Fiscal year 2032 | 2% for the full 12 months the order is in effect | P.L. 117-328, then P.L. 119-75 (February 3, 2026) |
| Fiscal year 2033 | 2% for the first five months, then 0% for the remaining seven | P.L. 119-75 (February 3, 2026) |
Source: Congressional Research Service (2026); Public Law 117-71 (2021); CGS Medicare (2022); Noridian Medicare.
Congress has extended the Medicare cut several times. The Congressional Research Service reports that the Consolidated Appropriations Act, 2023 (P.L. 117-328) extended Medicare reductions through fiscal year 2032, and the Consolidated Appropriations Act, 2026 (P.L. 119-75, enacted February 3, 2026) extended them into fiscal year 2033. The Office of Management and Budget lists Medicare at 2.0% in its April 2026 report for fiscal year 2027 and says Medicare sequestration begins in April of the fiscal year.
The statute caps the Medicare reduction at 2% a year, with the 2022 and fiscal year 2033 schedules as written exceptions (2 U.S.C. 901a). A contractor page updated July 7, 2026 still describes the reduction as 2% (First Coast Service Options).
A separate 'Statutory PAYGO' cut is not part of the 2%
A different law, Statutory PAYGO, can trigger an additional sequester when its scorecards show a deficit. The Congressional Research Service notes that in November 2025, P.L. 119-37 set both PAYGO scorecards to zero. The contractor pages we checked list only the 2% reduction. Watch CMS and your Medicare Administrative Contractor (MAC) for any new order.
How is the Medicare 2% sequestration calculated?
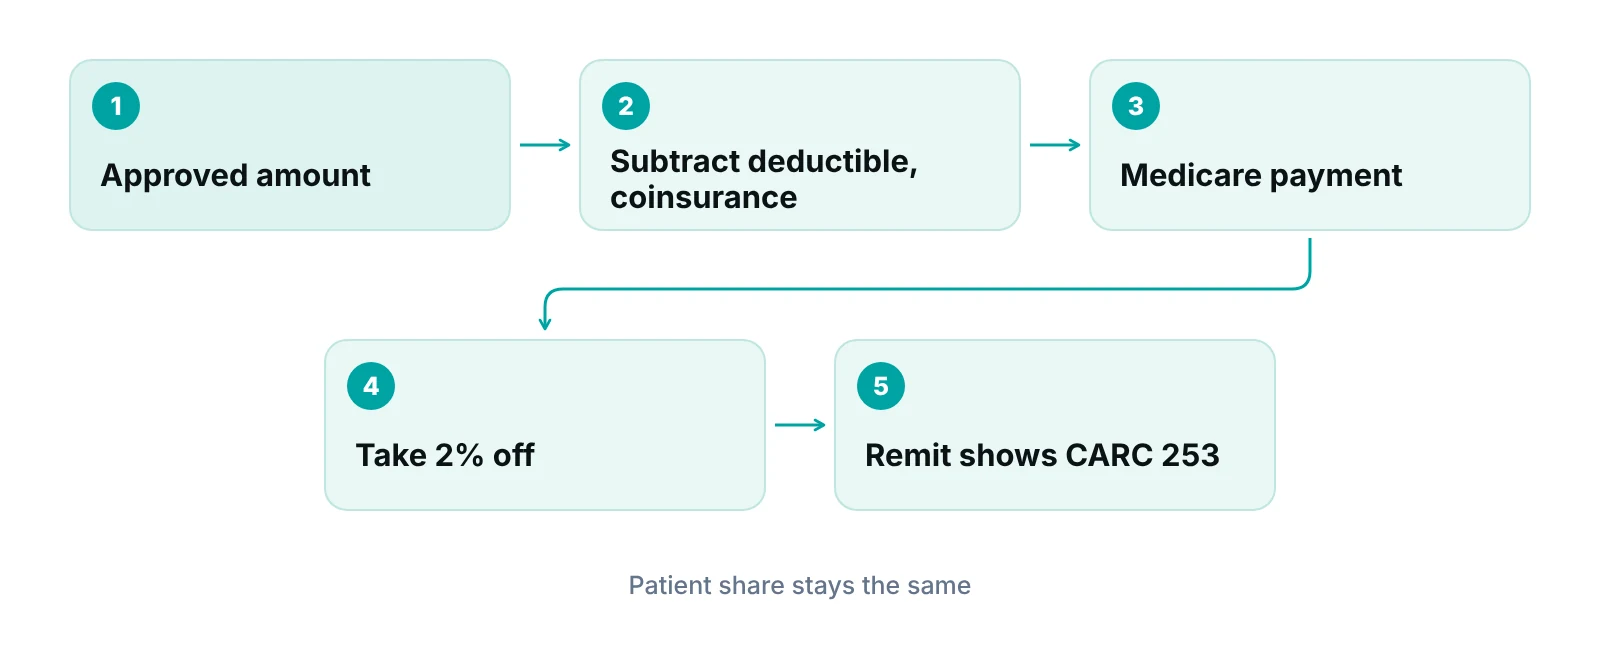
Medicare takes 2% of its own payment after it sets the approved amount and subtracts the deductible, coinsurance and any Medicare Secondary Payer adjustment. Fee schedules are unchanged, and the patient’s deductible and coinsurance are not reduced (CGS Medicare).
| Step | Deductible already met | Deductible partly unmet |
|---|---|---|
| Medicare approved amount | $100.00 | $100.00 |
| Patient deductible still owed | $0.00 | $50.00 |
| Patient coinsurance (20% of the rest) | $20.00 | $10.00 |
| Medicare payment before sequestration (80%) | $80.00 | $40.00 |
| Sequestration (2% of Medicare’s payment) | $1.60 | $0.80 |
| Medicare pays the practice | $78.40 | $39.20 |
| Patient owes | $20.00 | $60.00 |
Illustrative amounts. The $100 / $50 / $39.20 example follows the CGS Medicare Q&A (2022); the 80/20 split is a standard Part B illustration.
In both examples the patient’s share is the same with or without sequestration. Only the Medicare payment shrinks.
Unassigned claims and rentals
On unassigned claims, Medicare’s payment to the beneficiary is reduced by 2%. In the CGS example, a $36.00 reimbursement becomes $35.28. The non-participating provider still collects the full amount from the patient, subject to the limiting charge (CGS Medicare). For rental equipment and multi-day supplies, the “FROM” date of service controls: a rental payment with a FROM date on or after April 1, 2013 is reduced regardless of when the rental began.
What it costs a practice over a year
The loss is 2% of what Medicare pays, not 2% of total revenue. If Medicare paid a practice $1,000,000 in a year before sequestration, the cut would be $20,000. A practice whose patients are mostly on Original Medicare, such as many geriatrics practices, sees a larger share of revenue affected than one with a mixed payer base. You can model your own payer mix with our revenue calculator.
What does sequestration look like on a remittance (CARC 253)?
It appears as claim adjustment reason code (CARC) 253, “Sequestration – reduction in federal payment,” on both the electronic remittance advice (ERA) and the paper remittance. Institutional Part A claims show it at the claim level. Part B professional and outpatient institutional claims show it at the line level (CGS Medicare).
CMS created CARC 253 effective June 3, 2013, and told contractors to use it in place of the earlier CARC 223 on sequestration-reduced claims (CMS Transmittal 2739). If you still see CARC 223 mapped in an old payment-posting rule, check that the rule also handles 253. Our guide to reading an ERA explains how adjustment codes and amounts are laid out.
How to post it
- Post the Medicare payment exactly as received.
- Post the CARC 253 amount to its own sequestration adjustment category. Do not mix it with denials, contractual write-offs or patient balances.
- Leave the patient’s deductible and coinsurance as Medicare reported them; sequestration does not change them.
- On professional claims, expect the adjustment on each paid line and total it to the claim.
- Close the line. A routine CARC 253 amount does not need a denial work queue or an appeal.
Our post on payment posting steps covers the wider posting workflow.
“Sequestration is the one cut on a Medicare remittance that no coding fix or appeal can change. The job is to spot it, post it correctly and plan for it.”
— Awais Afzal, Healthcare Operations & Data Analyst
Which payments does sequestration apply to, and which does it not?
It applies to Original Medicare fee-for-service payments. For Medicare Advantage, CMS cut its payments to plans by 2%, but what a plan pays your practice follows your contract with that plan.
| Payment | Is the 2% applied? | What to know |
|---|---|---|
| Original Medicare claims (Part A and Part B) | Yes, to Medicare’s payment | Dates of service or discharge on or after April 1, 2013; no exemption for drugs |
| Patient deductible and coinsurance | No | Not reduced; only Medicare’s payment is |
| Unassigned claims | Yes, to Medicare’s payment to the patient | CGS example: $36.00 becomes $35.28 |
| Durable medical equipment rentals | Yes, by the FROM date | FROM date on or after April 1, 2013 is reduced, whenever the rental began |
| Medicare Advantage plans | Yes, at the plan level | Payments to contracted providers follow the plan contract; plans may not change benefits or cost sharing to offset it |
| Part D low-income subsidy and reinsurance payments | No | Exempt from sequestration under CMS’s 2013 plan payment memo |
Source: CGS Medicare (2022); First Coast Service Options (2026); CMS plan payment memo (May 1, 2013).
Under CMS’s May 1, 2013 memo, the effect on payments to contracted providers is “governed by the terms of the contract” between the plan and the provider, and for non-contract providers it is at the plan’s discretion whether to apply a reduction. Read each Medicare Advantage contract and the plan’s payment policy so you know what its remittances should show.
Specialty mix changes how much you notice the cut. See how revenue cycle needs differ across practices on our specialties hub, and for the broader fee-schedule picture read our post on Medicare payment cuts.
How should a practice plan for and manage the 2% cut?
Treat it as a fixed discount on Medicare fee-for-service payments. Build it into expected payment, post it as its own adjustment, keep it out of denial and appeal queues, and forecast with it.
Expected payment and underpayment checks
If your system flags a Medicare claim as underpaid because it paid less than the allowed amount minus patient share, the 2% will trip that check on every claim. Expected Medicare payment should be the payment after deductible and coinsurance, less 2%. Our portal’s underpayment detection compares payments to expected amounts, which is why we load the reduction into the expected figure first.
Forecasting and A/R
Forecast Medicare revenue net of the 2%, and recheck the rate when Congress acts. The reduction is applied to claims by date of service or discharge, so a claim keeps its rate even if Medicare processes it later. Do not let sequestration amounts sit in your open balance: a 2% shortfall that is really a CARC 253 adjustment will inflate aging if it is left on the account. Our A/R guide covers how to keep follow-up focused on real unpaid claims.
Is the 2% hiding real underpayments in your A/R?
Our free practice audit reviews a sample of your claims, remittances and A/R aging, and shows whether adjustments like CARC 253 are posted correctly and what needs follow-up.
What not to do
- Do not appeal CARC 253. It is not a payer decision on the claim.
- Do not add the 2% to the patient’s balance on your own. Patient cost-sharing is not reduced, and the CMS contractor pages we reviewed do not describe billing the patient for the reduction. Confirm with your MAC or compliance advisor if a case is unclear.
- Do not assume Medicare Advantage or commercial plans apply the same rule. Read the contract.
- Do not rely on a coding change to avoid it. The reduction applies to the payment, not to a code.
Posting, expected payment and A/R follow-up work best as one connected process, which is how our revenue cycle management service approaches Medicare remittances.
Our recommendations
- Give CARC 253 its own adjustment code. We post sequestration to a dedicated adjustment category, so it never blends into denials, contractual write-offs or patient balances.
- Set the expected Medicare payment net of the 2%. We calculate expected payment as the Medicare payment after deductible and coinsurance, less 2%, so underpayment checks fire on real shortfalls only.
- Keep CARC 253 out of denial and appeal queues. We close routine sequestration lines at posting and send only unexplained shortfalls to follow-up.
- Forecast Medicare revenue net of the cut. We model Medicare income at 98% of the pre-sequestration payment and review the assumption whenever Congress changes the schedule.
- Read every Medicare Advantage contract. Plans are not required to pass the 2% through the same way. We note each plan’s treatment in the payer profile and check remittances against it.
- Brief patient-collections staff. We tell front-desk and collections teams that the patient’s deductible and coinsurance do not change with sequestration, and we route questions about billing the patient to a manager.
A sequestration reduction can look like an underpayment.
The portal compares each payment with the expected amount and flags the gap, so you can review whether a reduction like this explains it and check it against the remittance.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Medicare sequestration is a 2% cut to Medicare’s own payment that is still in effect in October 2026, reported as CARC 253 and unaffected by the patient’s share. Post it separately, plan expected payment around it and keep it out of denial work. For help keeping Medicare remittances clean, see our end-to-end revenue cycle management and A/R management services, or start with a free practice audit.
Frequently asked questions
What is sequestration in medical billing?
Sequestration is an automatic 2% reduction in Medicare fee-for-service payments, under the Budget Control Act of 2011. It applies to claims with dates of service or discharge on or after April 1, 2013, apart from the 2020 to 2022 pause. It lowers Medicare’s payment after the deductible and coinsurance, and it appears on the remittance as CARC 253.
Is Medicare sequestration still in effect in 2026?
Yes. As of October 2026 the Medicare reduction is 2%. It was paused from May 1, 2020 to March 31, 2022, was 1% from April 1 to June 30, 2022, and returned to 2% on July 1, 2022. The Congressional Research Service reports that P.L. 119-75, enacted February 3, 2026, extends it into fiscal year 2033.
What is CARC 253?
CARC 253 is the claim adjustment reason code for sequestration, with the description “Sequestration – reduction in federal payment.” It appears on the ERA and paper remittance, at the claim level for institutional Part A claims and at the line level for professional and outpatient institutional claims. CMS created it effective June 3, 2013, replacing CARC 223 for these reductions.
Does sequestration reduce the patient's copay or deductible?
No. Contractor guidance says beneficiary deductible and coinsurance payments are not reduced; the 2% comes out of Medicare’s payment after the approved amount, deductible and coinsurance are applied. On unassigned claims, Medicare’s payment to the beneficiary is reduced instead, for example from $36.00 to $35.28.
Can we bill the patient for the 2% sequestration amount?
The CMS contractor guidance we reviewed does not describe billing patients for the reduction, and it says patient deductible and coinsurance are unchanged. Do not create a patient balance from a CARC 253 amount on your own. If a case is unclear, check with your Medicare Administrative Contractor or compliance advisor.
Does the 2% sequestration apply to Medicare Advantage?
CMS reduced its payments to Medicare Advantage plans by 2%, but its 2013 memo says the effect on payments to contracted providers is governed by the contract between the plan and the provider. For non-contract providers, applying a reduction is at the plan’s discretion. Check each plan’s contract and remittances.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Sequestration Q&A — CGS Administrators (Medicare Administrative Contractor) (2022)
- Federal sequestration payment reductions — First Coast Service Options (Medicare Administrative Contractor) (2026)
- Sequestration History — Noridian Healthcare Solutions (Medicare Administrative Contractor) (2026)
- CMS Manual System Pub 100-04, Transmittal 2739 (CR 8378) — CMS (2013)
- Medicare Advantage and Part D payment reductions memo — CMS (2013)
- The Annual Mandatory Spending Sequester Through FY2033 (R48880) — Congressional Research Service (2026)
- FY 2027 BBEDCA 251A Sequestration Report — Office of Management and Budget (2026)
- 2 U.S. Code 901a – Enforcement of budget goal — Legal Information Institute (Cornell Law School) (2026)
- Protecting Medicare and American Farmers from Sequester Cuts Act (Public Law 117-71) — U.S. Government Publishing Office (2021)
- Statutory PAYGO and Budget Reconciliation Legislation (IN12564) — Congressional Research Service (2026)
- Sequestration notice (COPE24619) — CGS Administrators (Medicare Administrative Contractor) (2022)
Disclaimer: This article is general educational information about Medicare billing operations. It is not legal, coding, billing-compliance or financial advice. Medicare rules, payer contracts and congressional schedules change, and Medicare Advantage and commercial plans set their own payment terms. Confirm requirements with CMS, your Medicare Administrative Contractor, your payer contracts and qualified advisors before acting.
