
Psychiatry medical billing combines an E/M visit or a diagnostic evaluation with timed psychotherapy add-ons, and each claim must prove both services. Evaluations use 90791 or 90792. A medication visit with therapy uses an E/M code plus 90833, 90836 or 90838, with separate times in the note.
The older version of this post talked about industry trends. This rewrite focuses on what decides whether a psychiatry claim gets paid: the codes, the pairing rules and the documentation. It is written for practice owners and billing managers, and it points to payer-specific checks wherever rules differ.
Key takeaways
- Evaluations are 90791 (no medical services) or 90792 (with), reported once per day.
- Psychotherapy add-ons ride on an E/M visit and are chosen by documented minutes, with nothing reported under 16 minutes.
- When an add-on is billed, the E/M level is chosen by medical decision making, not time.
- Telehealth changes place of service (POS 02 or 10) and brings an in-person requirement after December 31, 2027.
- Most denials are visible in the note before submission, so check time and pairing first.
Which codes does psychiatry medical billing use?
Most psychiatry claims come from three families: a diagnostic evaluation (90791 or 90792), an office E/M visit, and a psychotherapy add-on that rides on that E/M visit. Interactive complexity is an add-on, and crisis psychotherapy is a separate, less common service.
The codes below are described in plain words because the AMA owns the official CPT wording. The rules come from Medicare contractor pages. Commercial payers often follow the same pattern but not always, so read each payer’s policy. For a wider code list, see our mental health CPT codes guide and the behavioral health coding cheat sheet.
| Code | What it covers | Rule that matters |
|---|---|---|
| 90791 | Diagnostic evaluation without medical services | Reported once per day; not on the same day as an E/M service by the same clinician |
| 90792 | Diagnostic evaluation with medical services (adds the medical assessment) | Same once-per-day limit; the note needs history, mental status, diagnosis and an initial treatment plan |
| 90832, 90834, 90837 | Stand-alone psychotherapy by 16 to 37, 38 to 52, or 53+ minutes | Nothing under 16 minutes is reported; the note must show the time |
| 90833, 90836, 90838 | Psychotherapy add-ons on an E/M visit, same three time bands | Must be submitted with an E/M service by an MD, DO or non-physician practitioner |
| 90785 | Interactive complexity add-on (for example a third party or a family conflict that complicates the visit) | Add-on only; contractors list slightly different allowed pairings, so check yours |
| 90839, 90840 | Crisis psychotherapy: first 60 minutes, then each added 30 | Life-threatening situation only; not billed with other psychotherapy codes; once per day |
Source: Noridian Healthcare Solutions, CGS Administrators and First Coast Service Options (Medicare contractor pages, reviewed October 2026)
How do you bill an E/M visit and psychotherapy on the same day?
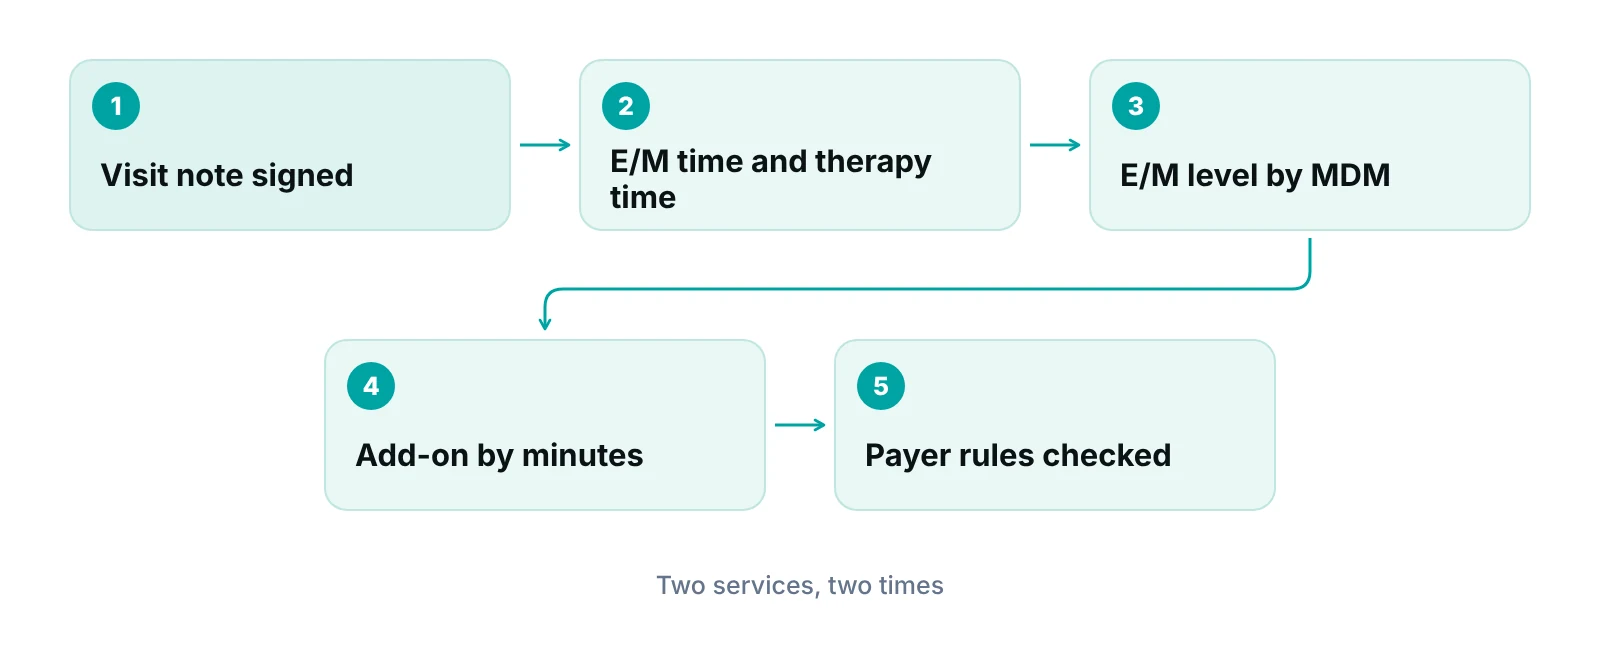
Bill the E/M visit and attach one psychotherapy add-on (90833, 90836 or 90838) when both services are significant, separately identifiable and documented with separate time. The add-on is chosen by psychotherapy minutes alone, and the E/M level is chosen separately.
First Coast, a Medicare contractor, says the add-ons attach to the office, hospital and home or residence E/M families, and that no psychotherapy code is reported for a session under 16 minutes (First Coast Service Options). Its time bands are 16 to 37 minutes for 90833, 38 to 52 for 90836, and 53 or more for 90838.
Choosing the E/M level
The American Psychiatric Association’s quick guide to the 2021 office E/M changes says the E/M level must be based on medical decision making (MDM) when psychotherapy is added, and that time cannot be used to select the E/M level in that case. A level is met when two of the three MDM elements meet or exceed it; moderate MDM maps to 99204 or 99214 (American Psychiatric Association).
Documenting two services in one visit
The note should show the E/M work and the therapy work as two pieces, each with its own time. CGS Administrators asks for exact start and stop times and a note per encounter (CGS Administrators). Noridian says to document E/M time separately from psychotherapy time, not as one combined total (Noridian Healthcare Solutions).
A 2014 American Academy of Family Physicians example shows the cost of skipping this: a note listed 45 minutes of total face-to-face time for a 99213 plus 90836, the contractor asked for records, no answer came back, and the payment was recouped (AAFP Family Practice Management). The article is old, so treat it as an illustration, not current policy. For a closer look at one add-on, see our 90836 CPT code guide.
“If the note shows one block of time, the claim can only show one service. Two services need two clear times.”
What are the rules for evaluations, interactive complexity and crisis visits?
A new-patient evaluation is billed as 90791 or 90792, once per day, and not on the same day as an E/M service by the same clinician. Interactive complexity (90785) and crisis psychotherapy (90839, 90840) have their own narrow rules.
- 90791 or 90792: CGS lists the required elements as a medical and psychiatric history, mental status exam, initial diagnosis, an assessment of the patient’s capacity to respond to treatment, and an initial treatment plan. Noridian adds that these codes should not be billed “incident to” (CGS, Noridian).
- 90785: Noridian describes it as an add-on for visits made harder by factors such as a third party (a child welfare or probation officer, for example) or family members in conflict. CGS notes it does not affect E/M level selection.
- 90839 and 90840: Noridian limits crisis psychotherapy to a presenting problem that is life-threatening to the patient or others and needs immediate attention, with a once-per-day limit and no other psychotherapy code on the same claim.
Because the allowed pairings for 90785 differ slightly between contractor pages, build the check into your claim rules instead of relying on memory. A payer-specific edit table is worth keeping for the five or six payers that make up most of your volume.
Eligibility problems often surface here too, because behavioral health benefits are frequently managed by a separate carve-out. Our behavioral health eligibility verification guide explains what to confirm before the first visit.
How does telehealth change psychiatry billing in 2026?
Telehealth does not change the code choice, but it changes the place of service, the home-visit rules and a coming in-person requirement. Use POS 02 when the patient is somewhere other than home and POS 10 when the patient is at home.
CMS’s telehealth FAQ (updated October 9, 2026) says Medicare telehealth flexibilities run through December 31, 2027, that behavioral health telehealth can be received at home with audio-only allowed, and that the in-person visit requirement for mental health telehealth takes effect after December 31, 2027. Patients who began home-based mental health telehealth on or before that date are treated as established and need at least one in-person visit every 12 months after it (CMS). Dates like these have moved before, so confirm them again before you build a policy around them.
Noridian’s page lists psychotherapy codes 90832 to 90838 as payable with POS 02 and POS 10. For modifier and payer-specific questions, see our telehealth billing guide.
Where do psychiatry claims get denied, and how do you stop it?
Most psychiatry denials trace back to time, pairing or level mismatches that were visible in the note before the claim left. Fixing the cause at the front of the process costs less than appealing the claim later.
| Problem | Why it triggers | Check before submitting |
|---|---|---|
| Psychotherapy under 16 minutes billed | Medicare contractors do not allow psychotherapy codes under 16 minutes | Read the minutes in the note, not the schedule slot |
| Combined time in the note | E/M and therapy time are not separable, so the add-on lacks support | Confirm two times, or start and stop times for each service |
| More than one unit of 90832 to 90838 | First Coast says services over one unit are denied outside POS 52 | Bill one unit; use the right family or code for longer sessions |
| Evaluation and E/M on the same day | 90791 and 90792 are not reported with an E/M by the same clinician that day | Choose one, based on what the visit was |
| High E/M level with an add-on | One California Medi-Cal plan denies add-ons with 99204, 99205, 99214 or 99215 when time justification is weak | Check each payer’s published policy for add-on edits |
| Wrong level of service | CERT lists wrong level and unclear time as common errors | Audit a sample of E/M plus add-on claims each month |
Source: First Coast Service Options; Noridian Healthcare Solutions (CERT notes); Blue Shield of California Promise policy PI0061 (effective July 1, 2025); CGS Administrators
The Blue Shield of California Promise policy is one plan’s rule, not a national one (Blue Shield of California Promise). It is useful as an example of why a payer’s own bulletin matters more than a general code list.
Tracking each denial by reason makes patterns visible. A practice management system that tracks claims by stage can show which claims are waiting, who owns them and which ones were paid below the expected amount, and its data-completeness checks can flag a missing time entry before submission. Our denial management guide covers appeal steps in more depth.
Should a psychiatry practice bill in-house or outsource?
Keep billing in-house when one trained person owns it and denials are low and understood. Consider outsourcing or a hybrid when the same denials keep returning, coding questions pile up, or a single biller leaving would stop cash flow.
| Option | Fits best when | Watch for |
|---|---|---|
| In-house | A stable, trained biller; clear payer mix; few denials | Single point of failure; training and software costs; limited time for old A/R |
| Outsourced | Billing is behind, turnover is high, or coding changes outpace the team | Ask who sees and fixes denials, whether you keep access to your data, and who signs a BAA |
| Hybrid | Front desk and charge entry stay in-house; claims, denials and A/R are handled outside | Clear handoffs; one owner for each stage; weekly reporting |
Whichever route you choose, ask any vendor to sign a Business Associate Agreement before it touches patient data, to show its denial reporting, and to explain how it checks notes for time. If you want a review of how your claims perform today, medical billing services for psychiatry can start with a free practice audit. See our behavioral health billing and RCM guide for the wider revenue cycle view, and the behavioral and mental health RCM operations page for how specialty-specific billing logic works.
Want a second look at your psychiatry claims?
A free practice audit reviews code selection, note support and denial patterns, and shows where claims stall. Pricing is quoted after you have seen it.
Our recommendations
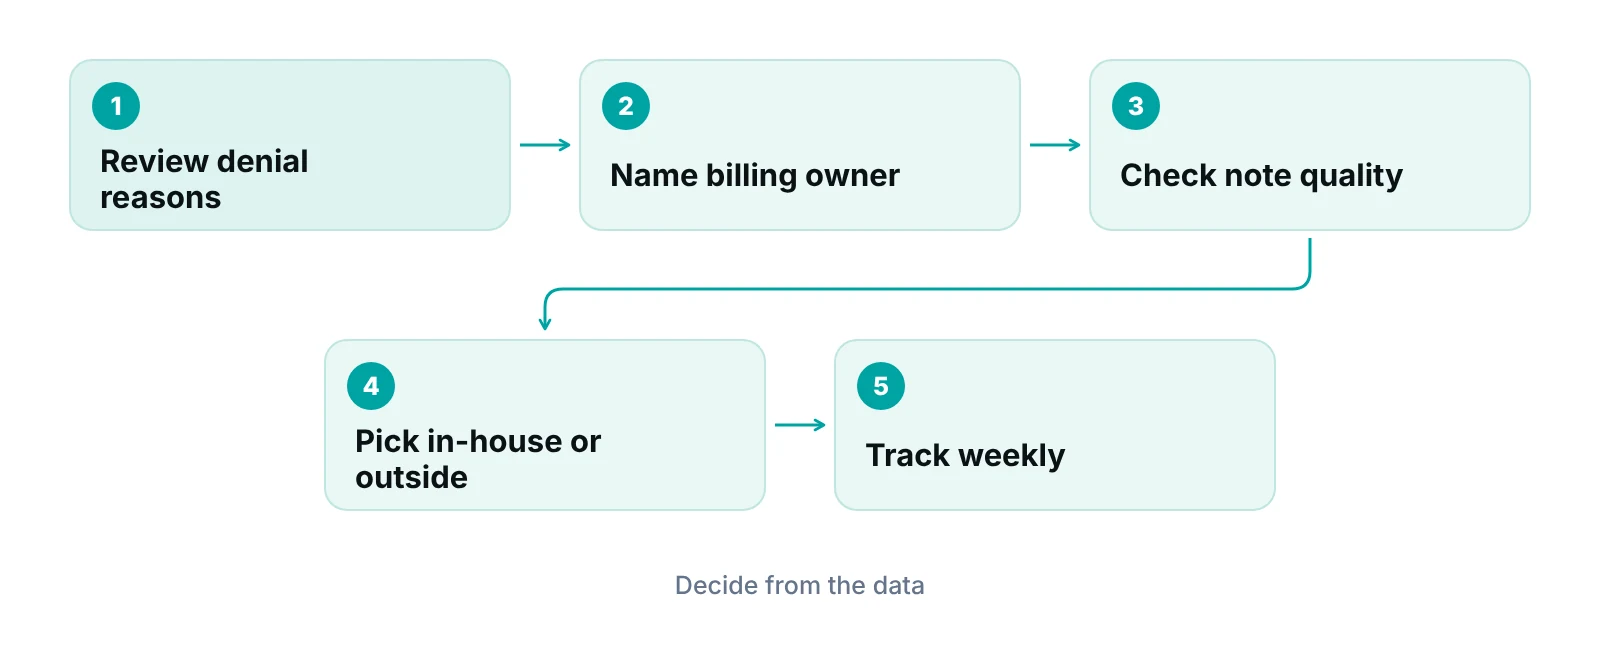
- Document two times, not one. Train clinicians to record the E/M portion and the psychotherapy portion separately, with start and stop times for therapy.
- Choose the E/M level by decision making. When a therapy add-on is on the claim, review the E/M level against MDM instead of total visit time.
- Keep a payer edit sheet. List add-on, evaluation and telehealth rules for your top payers, and update it when a bulletin arrives.
- Audit a small sample monthly. Pull a handful of E/M plus add-on claims each month and compare the note to the code. Fix the template when the same gap repeats.
- Track denials by reason. Count denials by cause, assign an owner for each, and review the list weekly.
- Ask vendors the plain questions. Before outsourcing any part of billing, ask for a signed BAA, access to your own data and a sample denial report.
Track every psychiatry claim by stage, with an owner.
The RCM Finder portal flags missing data before submission and highlights payments below the expected amount, so repeat denial patterns are easier to see.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Psychiatry medical billing is paid when the note proves two services, the codes match the minutes and the payer’s own edits are checked. If denials keep returning, a free practice audit or denial management services can help find the cause, and the revenue calculator shows what unpaid claims may cost.
Frequently asked questions
What is the difference between 90791 and 90792?
Both are psychiatric diagnostic evaluations. Noridian describes 90791 as an evaluation without medical services and 90792 as one with medical services, which adds a medical assessment. Both are reported once per day and are not billed on the same day as an E/M service by the same clinician.
Which E/M codes can psychotherapy add-ons be billed with?
First Coast lists the office, hospital and home or residence E/M families as the ones the add-ons attach to. CGS says 90833, 90836 and 90838 must be submitted with an E/M service by an MD, DO or non-physician practitioner. Check each payer for further limits.
Can a psychiatrist bill E/M by time when adding psychotherapy?
The American Psychiatric Association’s quick guide says time cannot be used to select the E/M level when psychotherapy is added; the level is set by medical decision making. The psychotherapy add-on is then chosen by its own documented minutes.
Is there a minimum time for psychotherapy codes?
Medicare contractors such as First Coast and CGS say psychotherapy is not reported under 16 minutes. The documented minutes must fit a time band, and the note should show start and stop times or total therapy time.
How should telepsychiatry visits be coded?
CMS’s October 2026 telehealth FAQ says to use POS 02 when the patient is not at home and POS 10 when at home. The FAQ also says an in-person visit requirement for mental health telehealth starts after December 31, 2027. Confirm payer rules, which may differ.
When does it make sense to outsource psychiatry billing?
Consider it when denials repeat, coding questions pile up or one person’s absence would stop claims. Ask for a signed Business Associate Agreement, access to your data and denial reports. A free practice audit can show where your claims stand first.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Mental health (Medicare specialty page) — Noridian Healthcare Solutions (2026)
- Psychotherapy services — First Coast Service Options (2026)
- Psychotherapy checklist — CGS Administrators (2026)
- Quick Guide to 2021 Office Outpatient E/M Coding Changes — American Psychiatric Association (2021)
- Psychotherapy with E/M add-ons policy PI0061 — Blue Shield of California Promise (2025)
- Potential pitfall in Medicare billing — AAFP Family Practice Management (2014)
- Medicare telehealth FAQ (updated October 9, 2026) — CMS (2026)
Disclaimer: This article is for education only. It is not legal, coding, compliance or medical advice. CPT is owned by the AMA, and payer rules, Medicare contractor policies and telehealth dates change. Confirm each code with the current CPT book and the payer before billing.
