
Medicare Part A vs Part B is a split between inpatient and outpatient coverage. Part A, hospital insurance, helps pay for inpatient hospital care and skilled nursing stays. Part B, medical insurance, covers doctor services, outpatient care and preventive services. In 2026 the Part A deductible is $1,736 and the Part B deductible is $283.
Providers rarely struggle with the definitions. The trouble starts when patient status, enrollment timing and each year’s new dollar amounts meet at the front desk and in the billing queue. This guide explains how the two parts differ, gives the verified 2026 costs, and shows where the split affects claims. It is general information, not legal, coding or compliance advice. Payer and Medicare Administrative Contractor rules can vary.
Key takeaways
- Part A helps cover inpatient care; Part B covers doctor services, outpatient care and preventive services.
- Patient status, inpatient or outpatient, decides which part pays.
- 2026: Part A deductible $1,736 per benefit period; Part B deductible $283 and standard premium $202.90.
- October 15 to December 7 is for changing plans, not first-time Part A or B enrollment.
- Replace any 2022 or 2025 cost figures in scripts and handouts.
What Medicare Part A and Part B each cover
Part A pays for inpatient care. Part B pays for most everything else a provider delivers outside an admission. Medicare describes Part A as helping cover inpatient care in hospitals, plus skilled nursing facility stays, end-of-life care and care at home after a hospital stay. Part B covers doctor and other provider services, outpatient care, home health care, medical equipment and many preventive services (per Medicare.gov).
Parts A and B together make up Original Medicare. Part C (Medicare Advantage) is a private plan that bundles Parts A and B, usually with Part D drug coverage. Part D covers prescription drugs. This guide stays on Parts A and B because they decide how a fee-for-service Medicare claim is paid.
| Care setting | Part A (hospital insurance) | Part B (medical insurance) |
|---|---|---|
| Formal inpatient admission | Covers the inpatient stay | Covers doctor services during the stay |
| Outpatient visit, outpatient surgery or observation | Pays nothing | Covers doctor services and hospital outpatient services such as surgery, lab tests and IV medicines |
| Skilled nursing facility | Covers stays; coinsurance applies from day 21 | See Part A |
| End-of-life care and care at home after a hospital stay | Covered under Part A | Home health care also listed under Part B |
| Medical equipment and preventive services | Not the main payer | Covers equipment such as mobility aids and hospital beds, plus screenings, vaccines and annual wellness visits |
Source: Medicare.gov, Parts of Medicare and Inpatient or outpatient hospital status (accessed October 2026).
Notice what the table shows. The department a patient walks into does not decide the part. The patient’s status does, which is why the next section matters more for billing than the coverage lists.
Patient status decides whether Part A or Part B pays
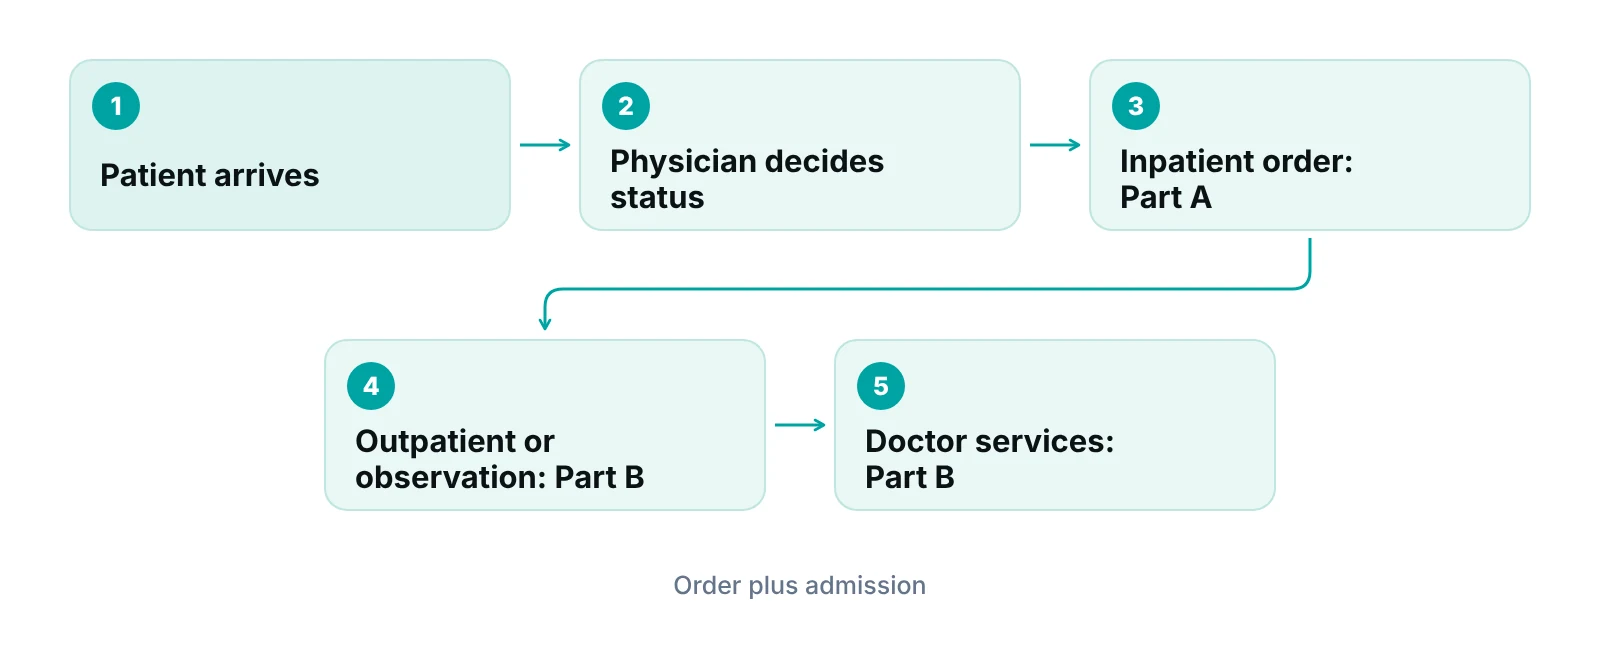
A patient is an inpatient only after a doctor’s order and a formal hospital admission. Everyone else in the hospital is an outpatient. Medicare.gov says inpatient admission is generally appropriate when a patient is expected to need two or more midnights of medically necessary hospital care, and that both the order and the formal admission are required (Medicare.gov).
What changes when a patient is an inpatient
- Part A covers the inpatient stay and, for most hospitals, related outpatient services from the 3 days before admission.
- Part B still covers the doctor’s services during the stay.
- If an inpatient order is later changed to outpatient, Part A pays nothing. The doctor and hospital must agree, and the hospital must tell the patient in writing before discharge.
What changes when a patient is in observation
Observation is an outpatient service used while a doctor decides whether to admit or discharge. A patient stays an outpatient even if they stay overnight, and Part A pays nothing. Part B covers the doctor services and hospital outpatient services. If observation lasts more than 24 hours, the hospital must give the patient a Medicare Outpatient Observation Notice (MOON), which explains status and its cost effects.
“Check patient status before anything else. It decides which Medicare part pays and what the patient owes.”
Status disputes are where Part A and Part B confusion turns into denied or reduced payment. Our guide to the two-midnight rule and inpatient versus observation covers the admission decision in detail, and how to verify Medicare coverage before you bill covers the front-end checks.
2026 Part A costs: deductible, coinsurance and premium
In 2026 the Part A inpatient deductible is $1,736 per benefit period. After the deductible, days 1 to 60 cost the patient $0 per day, days 61 to 90 cost $434 per day, and days 91 to 150 (lifetime reserve days) cost $868 per day. After day 150 the patient pays all costs. Skilled nursing facility coinsurance for days 21 to 100 is $217.00 per day. These amounts come from the CMS 2026 Medicare Parts A and B premiums and deductibles fact sheet and Medicare.gov.
Most people pay no Part A premium. Medicare.gov says people generally qualify for premium-free Part A if they or a spouse paid Medicare taxes for generally at least 10 years. Otherwise the 2026 Part A premium is $311 or $565 a month. CMS applies the $311 rate to people with at least 30 quarters of Medicare-covered employment (or a spouse with 30 or more), and the $565 rate to people with fewer than 30 quarters.
Do not reuse last year's figures
These amounts change every year. The 2026 Part A deductible is up from $1,676 in 2025, and the 2026 Part B premium is up from $185.00 in 2025. If a patient handout, script or template still shows 2022 or 2025 numbers, replace it. Older articles on the web, including an earlier version of this one, listed 2022 figures.
2026 Part B costs: premium, deductible and 20% coinsurance
In 2026 the standard Part B premium is $202.90 a month and the annual deductible is $283. After the deductible, the patient usually pays 20% of the Medicare-approved amount for covered services if the provider accepts assignment (per the CMS fact sheet and Medicare.gov). Collecting that 20% share correctly matters to a practice’s cash flow.
| Cost | Part A | Part B |
|---|---|---|
| Monthly premium | $0 for most people; $311 or $565 otherwise | $202.90 standard; higher with income |
| Deductible | $1,736 per benefit period | $283 per year |
| Coinsurance, base | $0 for days 1 to 60 after the deductible | Usually 20% of the Medicare-approved amount after the deductible |
| Coinsurance, longer stays | $434 per day (days 61 to 90); $868 per day (days 91 to 150) | Not applicable |
| Skilled nursing facility | $217.00 per day (days 21 to 100) | Not applicable |
Source: CMS, 2026 Medicare Parts A & B Premiums and Deductibles; Medicare.gov, Medicare costs (accessed October 2026).
Higher-income Part B premiums
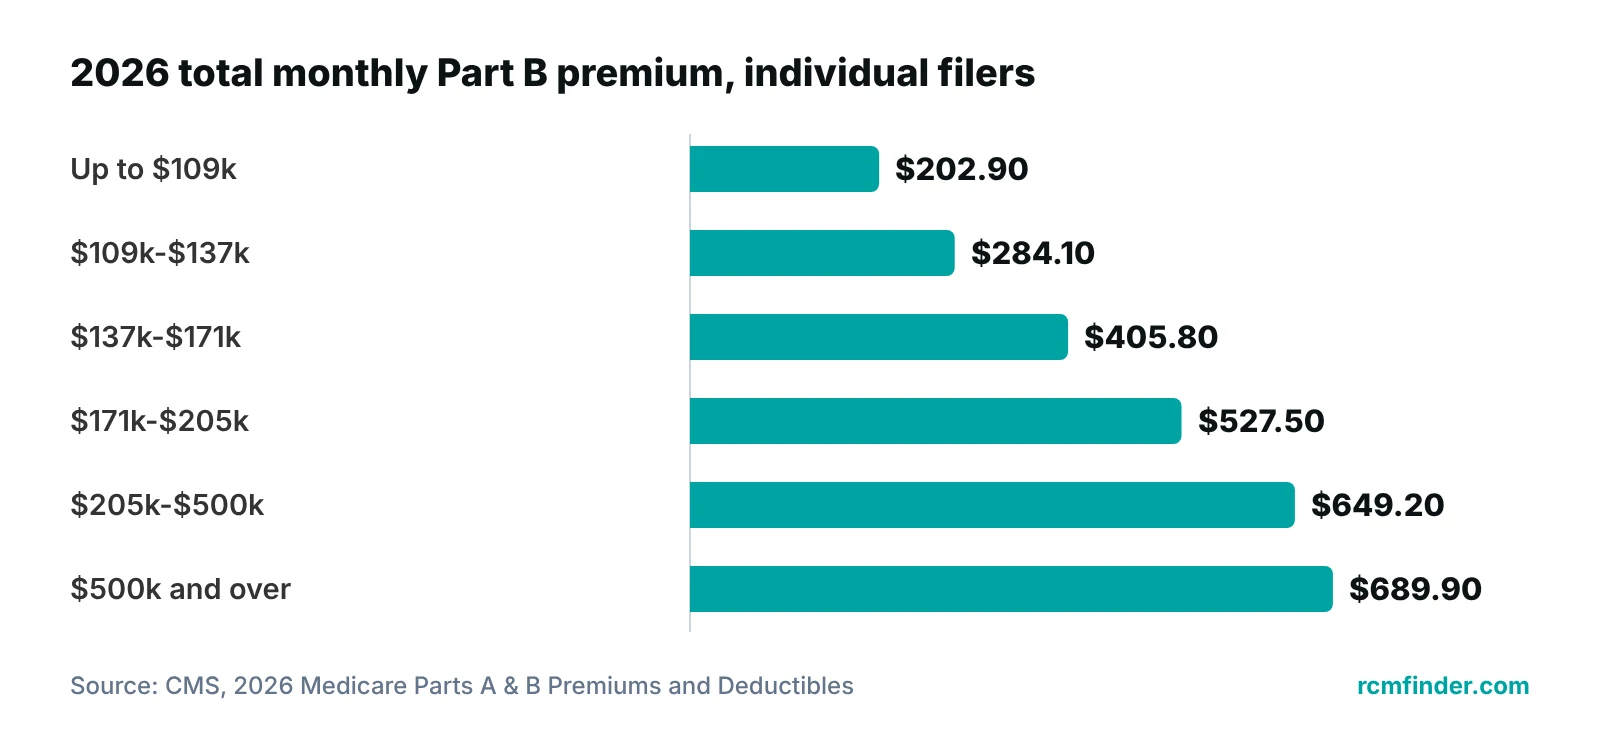
Part B premiums rise with income through the income-related monthly adjustment amount (IRMAA). For 2026 CMS lists a total monthly premium of $202.90 for individuals with modified adjusted gross income up to $109,000 (joint filers up to $218,000), rising to $689.90 at $500,000 or more for individuals ($750,000 or more for joint filers). The premium is paid by the patient; the deductible and the 20% share are what a practice collects at the point of service.
Who is eligible and when people enroll
Most people enter Medicare at 65, but people under 65 can qualify through disability. Per Medicare.gov, a person under 65 with a disability must receive disability benefits from Social Security or the Railroad Retirement Board, and gets Part A and Part B automatically after 24 months of those benefits. People with ALS who already receive disability benefits should already have both parts. Enrollment for end-stage renal disease (ESRD) is not automatic: the person must contact Social Security. Timing depends on dialysis or transplant, so send ESRD questions to Social Security.
Part A is automatic at 65 for people already receiving Social Security benefits. Part B depends on when benefits began: those who started at least 4 months before turning 65 get both parts automatically; others get Part A and choose Part B (Social Security Administration and Medicare.gov).
| Period | Dates | What it is for |
|---|---|---|
| Initial Enrollment Period | 7 months: 3 months before the month a person turns 65, through 3 months after | First chance to sign up for Parts A and B without a late penalty |
| General Enrollment Period | January 1 to March 31 each year | People who missed their initial window; coverage starts the month after sign-up; a penalty may apply |
| Special Enrollment Period | Depends on the situation; with employer group coverage, up to 8 months after coverage or work ends | Signing up outside the usual windows without a penalty in qualifying cases |
| Open Enrollment (Oct 15 to Dec 7) | October 15 to December 7 each year | Changing Medicare Advantage or drug plans for the next year. It is not for first-time Part A or B enrollment |
| Medicare Advantage Open Enrollment | January 1 to March 31 | People already in a Medicare Advantage plan can switch plans or return to Original Medicare |
Source: Medicare.gov, When does Medicare coverage start and Joining a plan; Social Security Administration (accessed October 2026).
The Part B late enrollment penalty is monthly, applies for as long as the person has Part B and goes up the longer they wait (Medicare.gov). Social Security notes that enrolling during the General Enrollment Period typically carries a lifelong penalty. If a patient reports a recent Medicare start date or a gap in Part B, treat it as a prompt to confirm eligibility before the visit.
What the Part A and Part B split means for your billing team
The split changes who collects what, and when. A hospital deals with the Part A deductible per benefit period and with day-based coinsurance. A physician practice deals mostly with the Part B deductible and the 20% share. The same patient can generate both kinds of balances in one episode, and an inpatient stay will also generate Part B professional services. For the mechanics of building each claim, see our guides to billing and coding Medicare fee-for-service claims and Medicare billing for providers.
Where Part A and Part B errors usually start
- Status is unclear or changes late, so the claim goes to the wrong part.
- Patient responsibility is quoted from an outdated deductible or coinsurance table.
- Medicare Advantage is mistaken for Original Medicare, so the wrong payer is billed.
- Late Part B enrollment or a recent start date is missed at registration.
- Outpatient services before an admission are not tied to the stay.
If your team spends time chasing these, the fix is usually process, not volume. Strong front-end checks and clean claims support Medicare reimbursement, and a medical billing service or an in-house team can own the follow-up. A practice management system that tracks claims by stage with an owner helps you see which Medicare claims are stuck and why.
Practices that see many older patients meet these rules daily. Our geriatrics billing and revenue cycle page shows how those patient mixes affect the revenue cycle.
Not sure where Medicare claims leak revenue?
Ask for a free practice audit. We review how your front end, coding and follow-up handle Medicare claims and tell you where to look first.
Our recommendations
- Update every patient-facing cost script each January. We recommend replacing deductible and coinsurance figures as soon as CMS publishes the new year’s amounts, and dating every handout so old numbers do not circulate.
- Confirm Medicare status before the visit. We recommend checking Part A and Part B entitlement at scheduling and again at registration. Our guide to verifying Medicare coverage walks through the steps.
- Make patient status a checkpoint, not an afterthought. We recommend a rule that billing reviews the inpatient or observation status and the order date before a hospital claim is released.
- Separate Original Medicare from Medicare Advantage at intake. We recommend capturing the plan type at registration, because Medicare Advantage plans can have different costs and coverage from Original Medicare.
- Track Part B balances separately. We recommend reporting the deductible and 20% balances as their own line, so slow patient collections do not hide inside general A/R.
- Use a plain-language script for patients. We recommend a short script that explains the part, the deductible and what the patient may owe, without quoting a total you cannot confirm.
Track Medicare claims by stage so Part A and Part B follow-up has an owner.
RCM Finder's portal tracks each claim by stage with an assigned owner and flags underpayments against expected amounts, so stuck Medicare claims are visible.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Part A and Part B are not interchangeable, and patient status decides which one pays. Verify status and enrollment first, quote only current-year costs, and give your billing team a clear process for each part. If you want an outside review of how your Medicare claims flow, our revenue cycle management service starts with a free practice audit, and the revenue calculator gives a quick view of what slow Medicare follow-up could cost you.
Frequently asked questions
What is the main difference between Medicare Part A and Part B?
Part A is hospital insurance. It helps cover inpatient hospital care, skilled nursing facility stays, end-of-life care and care at home after a hospital stay. Part B is medical insurance. It covers doctor and other provider services, outpatient care, medical equipment and many preventive services. Patient status, inpatient or outpatient, often decides which part pays.
What are the 2026 Part A and Part B deductibles?
For 2026, CMS lists a Part A inpatient deductible of $1,736 per benefit period and a Part B annual deductible of $283. The standard Part B premium is $202.90 a month. Most people pay no Part A premium. These figures change each year, so check the current CMS fact sheet before quoting a patient.
Does Part A cover observation stays?
No. Observation is an outpatient service, so Part A pays nothing even if the patient stays overnight. Part B covers the doctor services and hospital outpatient services. If observation lasts more than 24 hours, the hospital must give the patient a Medicare Outpatient Observation Notice explaining status and costs.
When can someone enroll in Part B?
The Initial Enrollment Period lasts 7 months, starting 3 months before the month a person turns 65. The General Enrollment Period runs January 1 to March 31, with coverage starting the month after sign-up and a possible late penalty. Special Enrollment Periods apply in some situations, such as employer group coverage.
Is October 15 to December 7 the time to enroll in Part A or Part B?
No. October 15 to December 7 is the Open Enrollment period for changing Medicare Advantage or drug plans for the next year. First-time Part A and Part B enrollment follows the Initial, General or Special Enrollment Periods. Medicare Advantage plan members also have a January 1 to March 31 window to switch plans.
Who qualifies for Medicare before age 65?
People under 65 with a disability who receive Social Security or Railroad Retirement Board disability benefits get Part A and Part B automatically after 24 months of benefits. People with ALS who receive disability benefits should already have both parts. ESRD enrollment is not automatic and goes through Social Security.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- 2026 Medicare Parts A & B Premiums and Deductibles — CMS (2026)
- Medicare costs — Medicare.gov (2026)
- Inpatient or outpatient hospital status affects your costs — Medicare.gov (2026)
- Parts of Medicare — Medicare.gov (2026)
- When does Medicare coverage start? — Medicare.gov (2026)
- Joining a plan — Medicare.gov (2026)
- How do I sign up for Medicare? — Medicare.gov (2026)
- When to sign up for Medicare — Social Security Administration (2026)
Disclaimer: This article is general educational information, not legal, coding or compliance advice. Medicare amounts and rules change, and payer and Medicare Administrative Contractor policies vary. Confirm current figures with CMS and Medicare.gov.
