
GV and GW modifiers go on Part B claims for patients in a hospice election. GV marks care related to the terminal illness by an attending physician who is not employed or paid by the hospice. GW marks a service unrelated to the terminal illness. Without one of them, Medicare denies the claim.
Many guides, including an earlier version of this one, get GV backwards and call it the modifier for a non-attending physician. It is the opposite. The mix-up leads to wrong claims and avoidable denials. This guide follows the Medicare Claims Processing Manual, Chapter 11 and CMS provider education, and it is written for billers, front-desk leads and practice owners who see an occasional hospice patient, such as a geriatrics practice or a primary care office.
Key takeaways
- A hospice election waives Part B payment for care related to the terminal illness, with one exception: the designated attending physician, if not employed or paid by the hospice.
- GV = attending physician, not hospice-employed or paid under arrangement, service related to the terminal prognosis. GW = service not related to the terminal prognosis.
- For dates of service on or after January 1, 2002, CMS tells contractors to deny Part B claims for hospice enrollees that carry neither GV nor GW.
- Contractors also deny GW on services that are in fact related, and GV from a physician the hospice employs or pays under arrangement.
- Ask every Medicare patient whether they are in hospice, record the answer, and check who is the designated attending physician before you pick a modifier.
What GV and GW modifiers do on a hospice patient's claim
They tell the Medicare contractor why a Part B service for a hospice enrollee should be paid separately. When a patient elects hospice, they waive Medicare payment for care related to their terminal illness. The hospice is paid to cover that care. The Claims Processing Manual, Chapter 11 makes one exception: the professional services of the patient’s attending physician, who may be a nurse practitioner or physician assistant.
In the CMS provider education podcast on this topic, CMS explains that services related to the terminal prognosis are included in the hospice payment and are not paid separately. For dates of service on or after January 1, 2002, contractors are told to deny Part B claims submitted without a GV or GW modifier. That is the real rule behind the modifiers. It applies to Part B claims for patients in a hospice period, not to every hospice service.
Two points keep this simple. GV is about who is billing and whether the care is related. GW is about whether the care is unrelated. You need both answers before you choose.
Who counts as the attending physician
The attending physician is the person the patient names when they elect hospice. Under 42 CFR 418.3, that person is a doctor of medicine or osteopathy, a qualifying nurse practitioner or a qualifying physician assistant, and the patient identifies them as having the most significant role in determining and delivering their medical care.
The Notice of Election carries this designation. Chapter 11 says the designated attending physician may be an independent physician, a hospice physician, a nurse practitioner or a physician assistant. A nurse practitioner or physician assistant who serves as attending may not certify or recertify the terminal illness.
Employment matters. If the attending physician is employed by the hospice, the hospice bills for those services and the physician may not also be paid under Part B for them. Chapter 11 states this in its overview. If the attending is not a hospice employee and is not working under arrangement, Medicare pays those services under the physician fee schedule instead of counting them as hospice services.
Check the election before you bill
The designated attending physician is named on the hospice’s Notice of Election. Ask the patient or the hospice who it is. Do not assume the physician who saw the patient most recently holds that role.
GV: the attending physician's related care
Use GV when you are the designated attending physician, you are not employed by the hospice or paid under arrangement with it, and the service relates to the patient’s terminal prognosis. This is the only route for Part B to pay for related care during a hospice election.
A nurse practitioner or physician assistant who is the designated attending and not employed by the hospice can bill Part B for services a physician would otherwise furnish. The Medicare Benefit Policy Manual, Chapter 9 pays these services at 85 percent of the physician fee schedule amount. The services must be medically reasonable and necessary and must not relate to certifying the terminal illness.
Contractors check GV against the facts. Per CMS, a GV claim is denied if the billing physician is employed by the hospice, is a hospice nurse practitioner, or works under arrangement with the hospice.
GW: services unrelated to the terminal illness
Use GW when the service is not related to the patient’s terminal prognosis. The definition in CMS’s provider education turns on the service, not on the title of the person billing.
CMS gives a simple example. A hospice enrollee has closed treatment of a metatarsal fracture, CPT 28470, in a physician’s office. If the fracture is unrelated to the terminal prognosis, the physician appends GW. Without GW, the claim is treated as related and is in error because it falls under the hospice benefit.
The reverse also matters. CMS tells contractors to deny GW services that are in fact related to the terminal prognosis. A modifier does not change the clinical facts. The note should show why the condition is unrelated, so a reviewer can follow the reasoning.
“A modifier states a conclusion. The medical record has to show why the conclusion is true.”
GV and GW side by side
The table below shows the two definitions from CMS provider education in one place. Use it as a quick check, then test your own scenario against the next section.
| Question | GV | GW |
|---|---|---|
| What it says about the service | Related to the terminal prognosis | Not related to the terminal prognosis |
| Who bills | Designated attending physician, not employed or paid under arrangement by the hospice | Defined by the service, not by the billing provider’s title |
| What it asks of the record | Show the patient’s election and the attending designation | Show why the condition is unrelated to the terminal illness |
| Common denial trigger | Billing physician is hospice-employed, a hospice nurse practitioner or under arrangement | Service is in fact related to the terminal prognosis |
| Claim type | Part B professional claim | Part B professional claim |
Source: CMS, Hospice Related Services – Part B, Medicare Learning Network podcast transcript (ICN 908995, 2014).
Which modifier fits which scenario
Most errors happen at the edges. These scenarios cover the cases a small practice meets most often. They apply the CMS rules above and are not a substitute for your Medicare Administrative Contractor’s (MAC’s) guidance.
| Scenario | Modifier | Where the service is billed |
|---|---|---|
| Designated attending physician, not hospice-employed, sees the patient for a condition related to the terminal illness | GV | Part B claim to the MAC |
| Any physician treats a condition unrelated to the terminal illness, such as a fractured foot in a cancer patient | GW | Part B claim to the MAC |
| Physician who is not the designated attending sees the patient for the terminal illness | Neither modifier makes this payable by Part B | Contact the hospice about an arrangement |
| Physician employed by the hospice provides attending care | GV is not valid | Hospice bills (Part A) |
| Nurse practitioner or physician assistant is the designated attending and not hospice-employed | GV | Part B claim, paid at 85 percent of the fee schedule |
Source: CMS Medicare Claims Processing Manual Ch. 11 (Section 10); Medicare Benefit Policy Manual Ch. 9 (Section 40.1.3); 42 CFR 418.304; CMS MLN (2014).
For the row on the non-attending physician, the CMS source says related services are included in the hospice payment and are not paid separately. The hospice pays physicians it uses under arrangement. If a specialist is needed for the terminal illness, the practice and the hospice should settle the arrangement before the visit.
Why hospice modifier claims get denied
Denials usually trace to a missing hospice status check, not to coding skill. CMS tells contractors to deny three patterns: a Part B claim with no GV or GW, a GW on a service that is related, and a GV from a hospice-employed physician, hospice nurse practitioner or arrangement physician. Recovery Auditors also run automated reviews on these claims.
CMS gives a second example. A patient was on hospice from August 1 to August 31, 2010. A diagnostic colonoscopy, CPT 45378, billed to Part B on August 3 with no modifiers was incorrect. For separate payment, the service must be unrelated to the terminal prognosis, or the attending physician must be entitled to separate payment, which GV or GW shows.
| Error | Why it fails | Fix |
|---|---|---|
| No modifier on a hospice patient’s Part B claim | Service is treated as related and included in the hospice payment | Check hospice status before billing; add GV or GW only when it fits |
| GV used by a non-attending physician | GV is for the designated attending only | Confirm the designation on the Notice of Election |
| GV used by a hospice-employed physician or hospice nurse practitioner | Their services are billed by the hospice | Route to the hospice |
| GW on a service tied to the terminal illness | Contractor denies GW on related services | Review the diagnosis and the note before adding GW |
| Billing after a revocation without checking dates | Coverage resumes only after a written revocation takes effect | Confirm the effective date with the patient or hospice |
Source: CMS, Hospice Related Services – Part B (MLN podcast transcript, 2014); CMS Claims Processing Manual Ch. 11.
Catch hospice status at the front desk
The cheapest fix is at scheduling and check-in. CMS asks physicians to ask the beneficiary or legal representative whether they are enrolled in hospice and to document the answer in the medical record. It also asks practices to tell patients and families to contact the hospice for needed care, because if the hospice does not arrange a service, the patient may be financially responsible.
Hospice status can change between visits. CMS notes that a patient can revoke the election at any time. The revocation must be in writing and signed, and a verbal revocation is not acceptable. After revocation, Medicare resumes coverage of the benefits that were waived. The patient can re-elect later while still eligible, which requires a prognosis of six months or less if the illness runs its normal course, per 42 CFR 418.3.
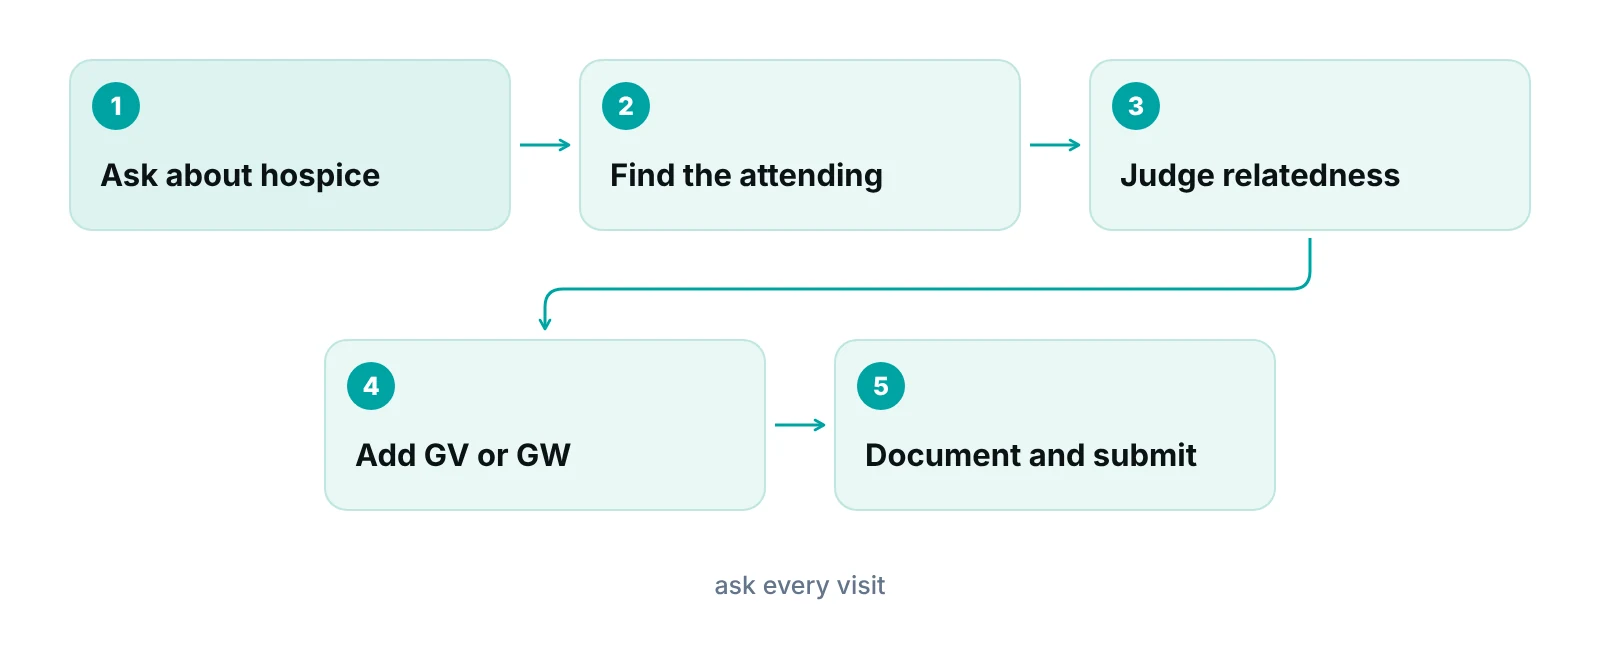
A medical billing service or an in-house coder can add this check as a hold rule: any Medicare patient flagged as in hospice goes to review before the claim leaves. Pairing it with a good eligibility process also helps. See our guides on how Medicare Part A and Part B differ and building clean claims.
How this fits with other hospice and modifier topics
GV and GW sit on professional claims. Hospice drug, equipment and palliative visit billing follow different rules. For palliative visit coding that is separate from hospice, see our guide to palliative care CPT codes. For hospice-related equipment payment changes, read our post on CMS hospice payment and DME.
If your office also bills other modifiers on the same visit, keep them separate in the review step. Our comparison of modifiers 25 and 59 shows how those two are tested. A hospice claim can carry them as well as GV or GW, so the checks stack.
Want a second reader on hospice-patient claims?
A free practice audit looks at where Medicare claims with special status, such as hospice, hold up or come back denied.
Our recommendations
- Ask about hospice at every Medicare visit. Record the answer in the chart. CMS asks physicians to do this, and the answer decides whether GV, GW or neither applies.
- Keep the attending designation on file. Ask the hospice or patient who the designated attending is, and store it with the insurance record. Update it when the patient changes hospice.
- Decide relatedness with the clinician, not the biller. A coder cannot tell if a condition relates to the terminal illness. Have the treating clinician state it in the note before GW is added.
- Hold hospice patients' claims for review. Set a review step for any Medicare claim from a patient flagged as in hospice. One minute here avoids a denial and a resubmission later.
- Tell families who to call. CMS asks practices to tell patients to contact the hospice for needed care. It protects the patient from surprise bills.
- Check your MAC's page each year. Rules about hospice billing are in the manuals, but the MAC’s local articles show how it applies them. Re-read both when you update your billing procedures.
Bottom line
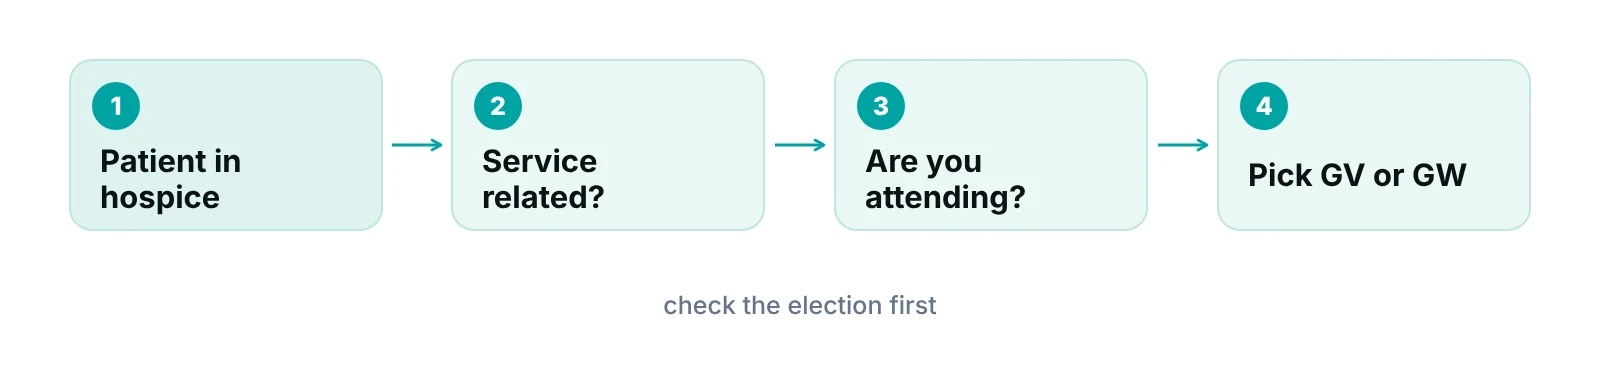
The test is short. First ask whether the patient is in a hospice election. Then ask whether you are the designated attending physician and whether the service is related. GV covers the attending’s related care. GW covers unrelated services. Everything else needs the hospice. If denials on these claims keep coming back, our denial management services can trace them to the cause, and the contact page is the quickest way to ask us a question. If a hospice patient’s visits are driving your denial rate, our revenue calculator can help you size the cost.
Frequently asked questions
What does the GV modifier mean?
GV is used by the patient’s designated attending physician when the service is related to the terminal illness and the physician is not employed by the hospice or paid under arrangement. It lets Part B pay for that related care. A nurse practitioner or physician assistant who is the designated attending and not hospice-employed can use it as well.
What does the GW modifier mean?
GW says the service is not related to the patient’s terminal prognosis. For example, a physician treats a broken bone in a patient whose hospice diagnosis is cancer, and the fracture is unrelated. The note should show why. Contractors deny GW on services that are in fact related to the terminal illness.
Is a modifier required on every claim for a hospice patient?
It is required on Part B claims for services to a patient in a hospice election. For dates of service on or after January 1, 2002, CMS tells contractors to deny such claims without GV or GW. Claims the hospice itself submits for its own services follow different billing rules.
Can a doctor who is not the attending physician use GV?
No. GV is for the designated attending physician. A physician who is not the attending and treats the terminal illness cannot get Part B payment by adding a modifier. Related services are included in the hospice payment, so the practice should contact the hospice about an arrangement.
What if the patient revokes hospice?
After a valid revocation, Medicare resumes the benefits that were waived. CMS says the revocation must be in writing and signed, with an effective date, and that a verbal revocation is not acceptable. Confirm the effective date before you decide whether GV, GW or neither applies to a visit.
Where do I find the official rules?
Start with the Medicare Claims Processing Manual, Chapter 11, and the Medicare Benefit Policy Manual, Chapter 9, both on CMS.gov. Your Medicare Administrative Contractor also publishes local articles on hospice Part B billing. Read the current version, because manuals are revised.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Medicare Claims Processing Manual, Chapter 11 – Processing Hospice Claims — CMS (accessed 2026-10-14)
- Hospice Related Services – Part B (MLN podcast transcript, ICN 908995) — CMS (2014)
- Medicare Benefit Policy Manual, Chapter 9 – Coverage of Hospice Services — CMS (accessed 2026-10-14)
- 42 CFR 418.3 Definitions — eCFR (accessed 2026-10-14)
- 42 CFR 418.304 Payment for physician, nurse practitioner, and physician assistant services — Legal Information Institute (Cornell), reproduces CFR (accessed 2026-10-14)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. CPT is a trademark of the American Medical Association, and the code references here are our own summaries. Medicare rules, payer rules and contractor articles change, so check the current CMS manuals and your Medicare Administrative Contractor before you bill.
