
Modifier 91 tells a payer that a clinical diagnostic lab test was repeated on the same day because a new result was truly needed. It fits only when the repeat is medically necessary and documented. It does not fit a rerun caused by a specimen problem, an equipment problem or a result check.
A common mistake with modifier 91 is assuming that any second run of a test is a billable repeat. It is not. The modifier exists for a second, separate result the patient’s care required. This guide covers the rule as Medicare contractors and the NCCI lab chapter describe it, with the situations where it does not apply. For the wider lab picture, see our laboratory billing and coding guide.
Key takeaways
- Modifier 91 reports a repeat clinical diagnostic lab test on the same day to get a subsequent, medically necessary result.
- It is not for specimen problems, equipment problems or reruns that only confirm a result.
- Bill the repeat on its own line with a quantity of one, with 91 on the repeat line only.
- NCCI and MUE edits can still apply, so check panels and units before you submit.
- The record must show why the second result was needed.
What modifier 91 means
Modifier 91 is the “repeat clinical diagnostic laboratory test” modifier. It marks a lab test that was performed more than once on the same day for the same patient to obtain subsequent results (Noridian Medicare). It is used with tests paid under the clinical laboratory fee schedule.
The modifier answers one payer question: why is this code on the claim twice for one date of service? Without it, the second line can look like a duplicate and be denied or bundled. With it, you are telling the payer the repeat was deliberate.
Medicare contractors cite the Medicare Claims Processing Manual, Chapter 16, section 100.5.1, “Tests Performed More Than Once on the Same Day,” for this rule (Noridian; section title in the CMS manual). The code descriptor itself belongs to the AMA’s CPT book, so use that for the exact wording and read it with your payer’s policy.
Medicare sources, other payers may differ
The contractor articles we reviewed are Medicare guidance. Commercial and Medicaid plans often follow the same logic, but each can add its own edits, documentation asks or modifier order. Check the payer’s published policy before you build a billing rule around this page.
When modifier 91 is correct
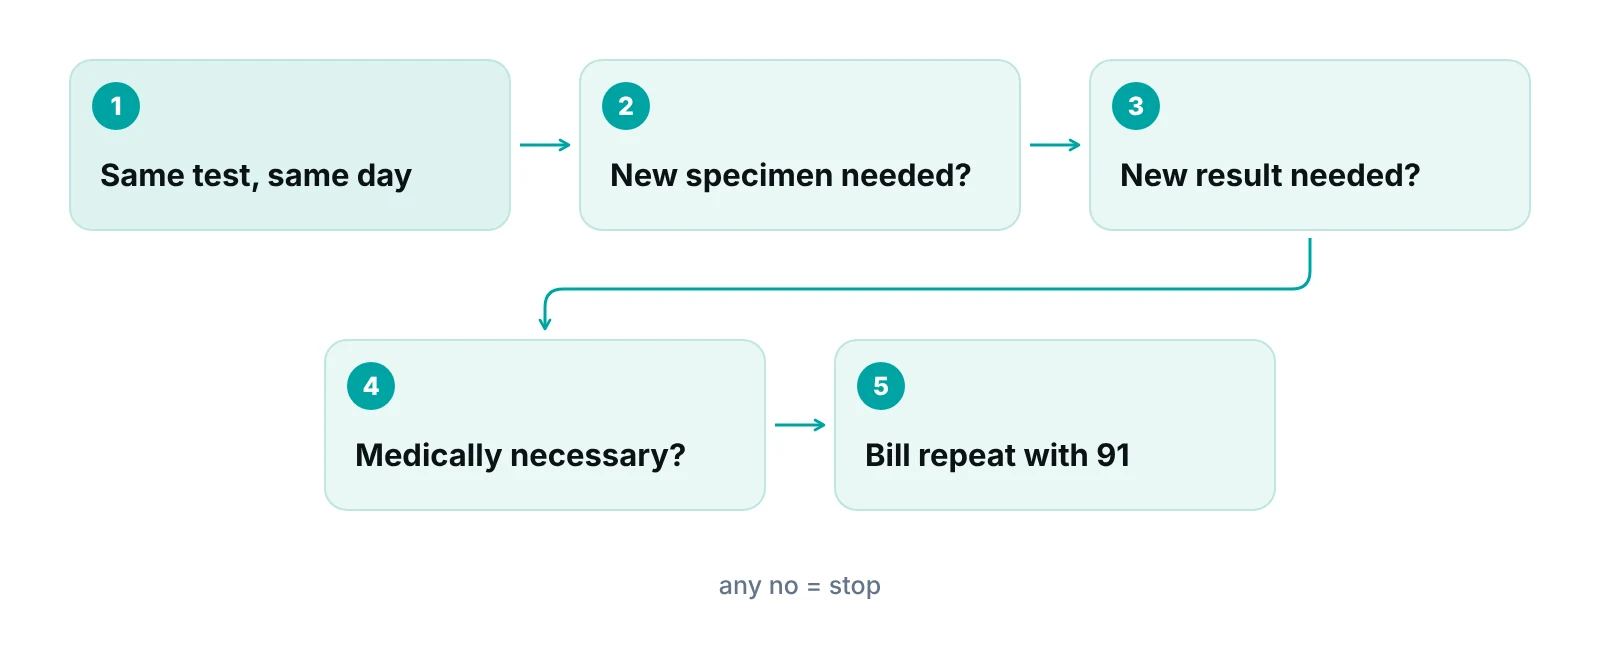
Use modifier 91 when the same lab test is legitimately run again on the same day to get another result. First Coast Service Options lists three conditions: a single service (the same CPT code) is ordered for the same beneficiary, the specimen is collected more than once in a single day, and the service is medically necessary (First Coast Service Options, 2026).
Notice what links those conditions. The second result has to be needed, not merely possible. The order, the collection time and the note should all show why a later value was wanted.
A worked example
First Coast’s own example is a potassium check. A patient’s potassium was tested more than once after potassium replacement and low-dose insulin therapy. After the initial value, a subsequent test was ordered and performed on the same date. The claim carries code 84132 on line 1, and 84132 with modifier 91 on line 2 (First Coast Service Options).
The pattern matters more than the code. A first result, a clinical reason to look again, a second order and a second collection. That is the story the record should tell if a reviewer asks.
CLIA-waived tests
If the lab holds a valid certificate of waiver for the test, Noridian says to append modifier QW (Noridian Medicare). Neither page we reviewed set out the order in which QW and 91 should appear, so confirm sequencing with your payer or clearinghouse rather than guessing.
When modifier 91 is not the answer
Do not use modifier 91 when a test is rerun because of a specimen problem, an equipment problem, or to confirm a first result. Noridian says it may not be used when tests are rerun to confirm initial results, and lists specimen and equipment problems, or any case where one normal reportable result is all that is needed (Noridian).
The NCCI laboratory chapter says the same thing from the edit side. A repeat run to verify an abnormal result is reported as one unit of service, not two, and repeat testing done to confirm initial results because of specimen or equipment trouble is not separately reportable (NCCI Policy Manual, Chapter X, 2017 Medicare edition; 2026 Medicaid edition).
That is the core of the “not duplicate, not a specimen error” rule. If the lab would have reported only one result had everything gone right, the second run is a lab quality step, not a service.
| Situation | Modifier 91? | What the sources say |
|---|---|---|
| New specimen drawn later because the care team needs a second value (for example after treatment given between draws) | Yes, if medically necessary and documented | Subsequent medically necessary test, same code, specimen collected more than once that day |
| Sample compromised or too small, so the lab runs it again | No | Specimen problems are excluded; one reportable result is all that is billed |
| Instrument or quality-control problem forces a rerun | No | Equipment problems are excluded |
| Abnormal result rerun to verify it | No | NCCI: report one unit of service, not two |
| A standard code already describes the series (for example glucose tolerance or evocative/suppression testing) | No | Bill the series code; do not add 91 to individual results |
| Component of a panel repeated the same date, repeat is medically necessary | Possible | NCCI names an NCCI-associated modifier for this; the Medicaid edition names 59 or 91 |
| Same analyte measured by a second method | Generally no | NCCI does not pay twice for the same result unless both methods are medically necessary |
Source: Noridian Medicare (page updated May 2025); First Coast Service Options (2026); CMS NCCI Policy Manual Chapter X, 2017 Medicare edition and 2026 Medicaid edition.
Edge case: a standard code that already covers the series
If your lab is tempted to put 91 on tests that belong to a series code, stop and check the code set first. Glucose tolerance and evocative or suppression testing are the examples Noridian gives. The series code is the correct claim; the modifier is not a workaround.
How NCCI and MUE edits treat repeat lab tests
NCCI and MUE edits are why a repeat line can still deny even when your reason is sound. A medically unlikely edit (MUE) is the maximum units of service a provider would report under most circumstances for a single beneficiary on a single date of service (CMS). A second unit on one line can exceed that cap. First Coast tells billers to review MUEs to make sure units are coded correctly (First Coast).
The NCCI laboratory chapter has a specific passage on panels. NCCI pairs each panel code with its component test codes. If a component is repeated on the same date and the repeat is medically reasonable and necessary, an NCCI-associated modifier can bypass the edit. The 2017 Medicare edition names modifier 91 for this repeat testing, and the 2026 Medicaid edition names 59 or 91 (2017 Medicare edition; 2026 Medicaid edition).
If your team also uses modifier 59, our guides on modifiers 25 vs 59 explain how it differs. The key point here is that a modifier opens the door to payment only when the record supports the repeat.
Two things NCCI warns against
- Splitting services across dates. The 2017 Medicare edition cautions against performing services on different dates of service to avoid MUE or NCCI procedure-to-procedure edits.
- Using several claim lines with modifiers to get around MUEs. The same edition warns that frequent use of this approach may indicate incorrect unit reporting.
| Rule | What it says | Where it comes from |
|---|---|---|
| Same-day repeat tests | Medicare contractors cite Claims Processing Manual Ch. 16, section 100.5.1 for tests performed more than once on the same day | Noridian; CMS manual table of contents |
| Verification reruns | A repeat to verify a result is reported as one unit, not two | NCCI Ch. X, section A |
| Confirmation reruns | Repeat testing to confirm initial results because of specimen or equipment problems is not separately reportable | NCCI Ch. X, section C |
| Duplicate methods | The same result is not paid twice, even by two methods, unless both are medically necessary | NCCI Ch. X, hematology section H.2 |
| Panel components | A repeated component can be reported with an NCCI-associated modifier when the repeat is medically necessary | NCCI Ch. X, section C |
| Unit limits | An MUE caps units for one beneficiary on one date of service | CMS MUE guidance |
Source: CMS NCCI Policy Manual Chapter X (2017 Medicare edition; 2026 Medicaid edition); Medicare Claims Processing Manual Ch. 16; CMS medically unlikely edits page; Noridian Medicare.
How to build the claim line by line
Put every service from that day on one claim, give each test its own line with a quantity of one, and add modifier 91 to the repeat line only. First Coast’s checklist asks you to bill all same-day services on the same claim, report each on a separate line with a quantity of one, append 91 to the repeat procedure and document its use in the medical record (First Coast). Noridian’s example shows the first line with no modifier and later lines with 91 (Noridian).
| Line | Code | Modifier | Units | Note |
|---|---|---|---|---|
| 1 | 84132 | none | 1 | Initial potassium result |
| 2 | 84132 | 91 | 1 | Repeat potassium, same date, own line |
| 3 (if needed) | 84132 | 91 | 1 | Later documented repeat; subsequent lines carry 91 |
| Waived test | Any waived code | QW added | 1 | Add QW when the lab holds a valid certificate of waiver; confirm modifier order with the payer |
| Avoid | 84132 | none | 2 | Two units on one line; First Coast asks for a quantity of one per line |
Source: First Coast Service Options (2026) potassium example; Noridian Medicare (2025). Code 84132 is used here only as First Coast’s example.
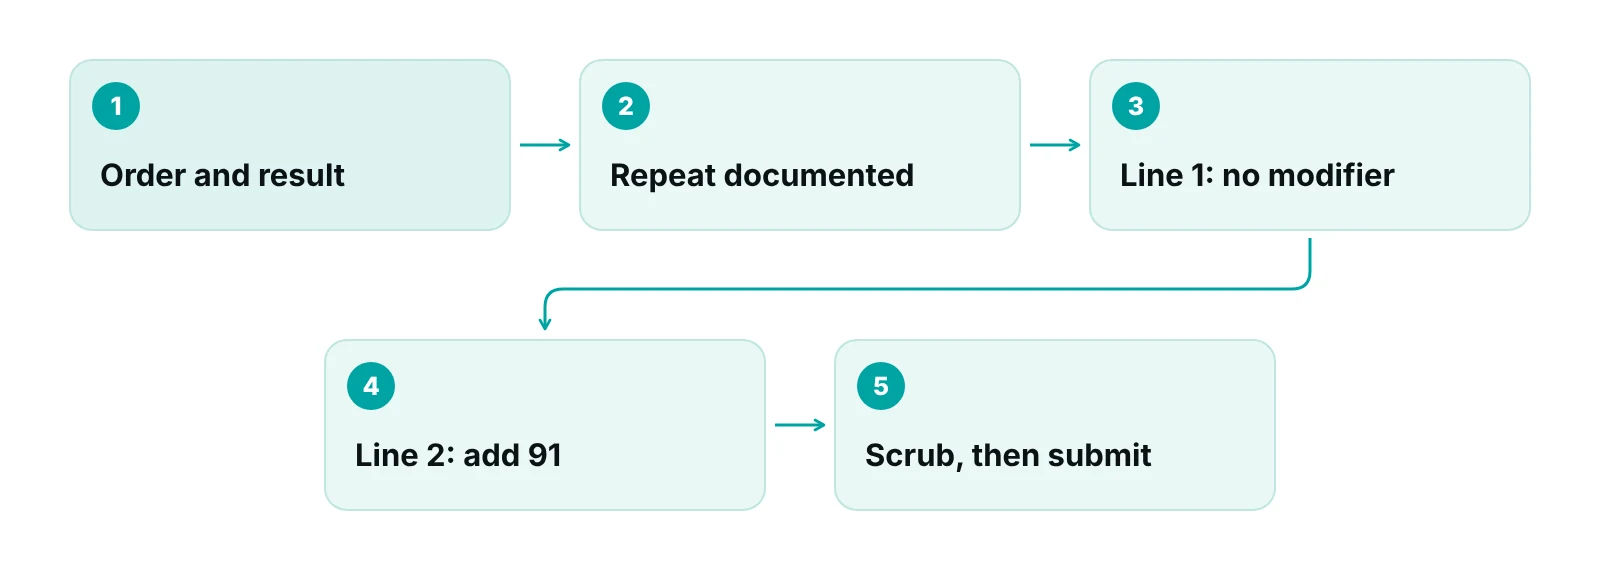
Many repeat-test problems can be caught before submission. A pre-submission check for two lines with the same code and date, a missing modifier, or a missing note is cheap compared with an appeal. We cover this in our claim scrubbing guide, and a practice management system that tracks claims by stage can hold a flagged claim for a person to review before it goes out.
Documentation that supports a repeat
The record has to show a reason for the second result. First Coast asks billers to document the use of the modifier in the medical record, and medical necessity is one of its three criteria. A modifier with no clinical note behind it is an audit finding waiting to happen.
For lab claims specifically, documentation also decides what the lab can bill at all. Our post on documentation rules for pathology and laboratory claims covers the broader record requirements. If your organization is a laboratory or does pathology work, the same discipline applies across pathology billing and RCM.
A practical record for a same-day repeat has four things:
- Two separate orders or an order that clearly calls for serial testing, with the reason for the second value.
- Separate collection times for each specimen.
- Both results, reported against the correct line on the claim.
- A short note tying the second result to a clinical decision.
These are our recommended habits, not a payer requirement. Your payer’s own policy controls what it will accept.
What a reviewer will ask
Why was the first result not enough? Was the second sample really a new collection? Would a single result have been reported if everything had gone right? If your record answers those three, the modifier usually holds.
If a modifier 91 line is denied
Start with why it denied. A bundling or duplicate denial usually means the repeat line reached the payer without the modifier, or the modifier did not survive the claim edit. A medical necessity denial means the record did not explain the repeat. Our overview of denial management in medical billing walks through the triage.
Appeal only when the record supports the repeat. If the second run was a specimen or equipment problem, the right outcome is the denial, and the fix is upstream: train staff not to bill reruns, and stop the line at charge entry. Charge entry and coding review are part of our medical billing services.
Want a second set of eyes on your lab claims?
Our free practice audit reviews how same-day repeat tests reach the claim and where they stall. Pricing, if you want help afterwards, is quoted after the audit.
Our recommendations
- Make the question 'would one result have been reported?'. We would build this single question into charge review. If one clean result would have been enough, the repeat is a lab quality step and does not get modifier 91.
- Block reruns at the source. We would ask the lab to flag a rerun by reason code (specimen, equipment, verification, new clinical need) so billing sees why a second result exists before charge entry.
- One test, one line, one unit. We would never bill a repeated lab test as two units on one line. Each result gets its own line with a quantity of one, and 91 sits on the repeat.
- Match the modifier to the record. We would not release a 91 line without a documented reason for the second value in the chart. The note is the audit defense.
- Check panels before adding 91. We would check whether the repeated test is a panel component, because NCCI edits pair panel codes with their components and the modifier rules differ by edition.
- Scrub for same-code, same-date lines. We would run a pre-submission check for any code appearing twice on a date of service without a modifier or a note. It catches the missing-modifier and missing-note cases before the payer does.
Hold a repeat-test claim for review before it goes out.
Our portal tracks each claim by stage with an owner and runs data-completeness checks before submission. Workflow rules can flag a claim for review or hold it at a stage, so a same-day repeat line can be checked by a person first.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Modifier 91 is for a second, medically necessary result of the same lab test on the same day. It is not for specimen errors, equipment problems, verification reruns or duplicate methods, and it does not replace a series code. If you want help checking how repeat tests reach your claims, start with our medical billing services or denial management services, or talk to our team.
Frequently asked questions
What is modifier 91 used for?
Modifier 91 reports a repeat clinical diagnostic laboratory test performed more than once on the same day for the same patient to obtain subsequent results. It is used with tests paid under the clinical laboratory fee schedule, and the repeat has to be medically necessary and documented.
Can I use modifier 91 when a specimen is contaminated or too small?
No. Medicare contractor guidance says modifier 91 is not for testing problems with the specimen or the equipment, or for a rerun that only confirms the first result. In those cases one reportable result is all that is billed, so the rerun does not get a second line.
How do I list modifier 91 on the claim?
Bill all same-day services on one claim. Put each test on its own line with a quantity of one. Leave the first line without a modifier and add 91 to the repeat line. Document the reason in the record, and check units against the medically unlikely edit for the code.
Does modifier 91 apply to panels?
Sometimes. NCCI pairs panel codes with their component tests, and says an NCCI-associated modifier can bypass the edit when a component is repeated on the same date and the repeat is medically necessary. The 2017 Medicare edition names 91, and the 2026 Medicaid edition names 59 or 91. Confirm with your payer.
Is modifier 91 the same as modifier 59?
No. Modifier 91 identifies a repeat lab test on the same day. Modifier 59 flags a distinct service that would otherwise be bundled. NCCI names both for repeated panel components, but they answer different questions. Our modifier 25 vs 59 guide explains 59 in more detail.
What if my payer does not follow Medicare on modifier 91?
Follow the payer’s published policy. The sources behind this page are Medicare contractor and CMS NCCI documents. Commercial and Medicaid plans can set their own edits, documentation asks and modifier order, so check each plan’s lab policy before you set a billing rule.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Modifier 91 (Repeat clinical diagnostic laboratory test) — Noridian Healthcare Solutions (Medicare JF Part B) (2025)
- Utilizing modifier 91: Repeat clinical laboratory tests — First Coast Service Options (Medicare) (2026)
- NCCI Policy Manual for Medicare Services, Chapter X: Pathology and Laboratory Services (2017 edition) — CMS (2017)
- Medicaid NCCI Policy Manual, Chapter X: Pathology and Laboratory Services — CMS (2026)
- Medicare Claims Processing Manual, Chapter 16: Laboratory Services — CMS (2026)
- Medically Unlikely Edits — CMS (via HHS guidance portal)
Disclaimer: This article is educational and is not legal, coding, clinical or compliance advice. CPT is owned by the American Medical Association and payer rules vary. The guidance cited is from Medicare contractors and CMS; confirm each rule in your payer's current policy and the current CPT and NCCI editions before you bill.
