
Modifier 52 tells a payer that a procedure was deliberately reduced by the provider, so the code is billed but not all of it was done. It does not apply to E/M services, and it is not the same as modifier 53, which reports a procedure stopped for the patient's well-being.
Modifier 52 is short to type and easy to misuse. The previous version of this guide gave several wrong examples, including assistant surgeon roles and anesthesia timing as the line between 52 and 53, so this edition has been rebuilt from Medicare contractor pages and CMS instructions. For related modifier explanations, see our guides to modifier 59 and modifier 25 vs 59.
Key takeaways
- Modifier 52 reports a service the provider chose to reduce, where the basic service is still identifiable.
- It is not for E/M codes, elective cancellations or procedures that were stopped for the patient’s well-being.
- Modifier 53 is for a procedure stopped because of extenuating circumstances; 73 and 74 are facility modifiers.
- Medicare Part B wants the words reduced services and a brief reason in Item 19, with the full reason in the record.
- Payment is reduced, and the amount varies by payer, so check the payer’s policy.
What modifier 52 means
Modifier 52 is the “reduced services” modifier. It tells the payer that a service was partly reduced or left out, while the procedure code still describes the service that was started. Medicare’s Part B contractor Noridian describes it as covering partial reduction, cancellation or discontinuation of services for which anesthesia is not planned (Noridian Medicare, updated 2025).
The point of the modifier is honesty on the claim. The code says what the service normally is. The modifier says the patient did not get all of it, and the payment should reflect that. Without it, the payer sees a full procedure and pays for a full procedure, which creates an overpayment you may have to return later.
Priority Health’s provider manual puts the same idea simply: the modifier lets a provider report a reduced service without changing the identity of the basic service (Priority Health provider manual). The code descriptors themselves belong to the AMA’s CPT book, so confirm the exact wording there and in your payer’s policy.
Medicare and commercial payers differ
Most of the detail in this guide comes from Medicare contractor pages, plus two commercial or managed-care payment policies used as examples. Other payers can set their own percentages, documentation asks and edits. Treat the payer’s current policy as the final word.
When to use modifier 52
Use modifier 52 when the physician or practitioner deliberately reduces or leaves out part of a procedure, the procedure is still recognizable as the code you are billing, and anesthesia was not planned. The decision to reduce is a clinical one, and the record has to show it.
Three conditions that usually have to be true
- The service performed is a reduced version of the coded service, not a different service. Commonwealth Care Alliance’s payment policy says the basic service must still be identifiable.
- No separate code describes the part that was completed. The same policy says modifier 52 is not appropriate when a separate code describes the portion of the procedure that was done.
- The reduction was the provider’s choice, not a response to a threat to the patient. Threat to the patient’s well-being points to modifier 53 instead.
A worked example from Medicare guidance
Noridian’s own example is bilateral fundus photography (CPT 92250) performed on only one eye. The contractor says to report the code with modifier 52 and not to use the RT or LT side modifiers in that case (Noridian Medicare). The code is built for both eyes, one eye was done, so the claim carries 52.
The same logic applies to any code written for a complete service. If the descriptor assumes both sides, a full set of views or a complete study and the provider chose to do less, modifier 52 is the candidate. If the descriptor already allows for a partial or one-sided service, it is not.
“A modifier does not explain itself. The claim, the code and the chart note have to tell the same story about what was and was not done.”
When not to use modifier 52
Do not use modifier 52 with evaluation and management (E/M) codes. Noridian calls it inappropriate with E/M services, and both Priority Health and Commonwealth Care Alliance say the same (Noridian; Priority Health; Commonwealth Care Alliance).
There are several other cases that look like reduced services but are not. The table below sorts the common ones.
| Situation | Modifier 52? | What to check instead |
|---|---|---|
| Provider chooses to do part of a procedure; no anesthesia planned | Yes, if the code still describes the service | Reason in the note; reduced services statement on the claim |
| Code descriptor already allows a partial or one-sided service | No | Report the code as written, or use the side modifier the payer asks for |
| A separate code describes the part that was completed | No | Bill the code for what was actually done |
| Procedure ended because of a threat to the patient’s well-being | No | Modifier 53 for physician services |
| Facility stopped an outpatient procedure after the patient was prepared | No, for hospital outpatient and ASC claims | Modifier 73 or 74, depending on anesthesia timing |
| Procedure cancelled by choice before it started | No | Medicare guidance says elective cancellation should not be reported |
| Any E/M code | No | Choose the E/M level the documentation supports |
Source: Noridian Medicare (2025); Commonwealth Care Alliance payment policy; CMS Transmittal 442 (2005); Johns Hopkins Health Plans policy RPC019. Payer rules vary.
On the elective cancellation row: CMS’s 2005 instruction on discontinued services says the elective cancellation of a procedure should not be reported (CMS Transmittal 442). Commonwealth Care Alliance gives a matching rule, that modifier 52 should not report elective cancellation before anesthesia induction, sedation or surgical preparation in the operating suite.
Radiology is the specialty where this comes up most often in Medicare guidance, because Noridian notes that discontinued radiology procedures are reduced under modifier 52 as well. Our radiology billing and operations page covers how imaging practices handle modifiers and payer rules more broadly.
Modifier 52 vs modifier 53 (and 73 and 74)
The difference is the reason and the setting. Modifier 52 is a reduced service chosen by the provider. Modifier 53 is a discontinued procedure because of extenuating circumstances that threatened the patient’s well-being. Modifiers 73 and 74 are for discontinued procedures in hospital outpatient departments and ambulatory surgery centers (ASCs).
The older version of this guide treated anesthesia timing as the dividing line between 52 and 53. That is not how Medicare describes them. For physician services the question is why the procedure ended. Anesthesia timing matters mainly for the facility modifiers: CMS’s instruction says 73 is for a procedure stopped after the patient was prepared and taken to the procedure room but before anesthesia, and 74 is for one stopped after anesthesia was given or the procedure had started (CMS Transmittal 442, 2005). CMS counts local, regional block, moderate sedation, deep sedation and general anesthesia as anesthesia for this purpose.
| Modifier | Reason / timing | Who reports it | Payment example |
|---|---|---|---|
| 52 Reduced services | Provider reduces or leaves out part of a service; no anesthesia planned | Physician or practitioner; facilities for discontinued radiology and non-anesthesia procedures under Medicare | Medicare: charge reduced by the share not provided; 50% reduction for discontinued radiology and other non-anesthesia procedures |
| 53 Discontinued procedure | Stopped because of extenuating circumstances that threatened the patient’s well-being | Physician services; CMS says not approved for outpatient hospital services | Payer-specific; one plan’s policy pays 25% of the allowed amount |
| 73 Discontinued before anesthesia | Patient prepared and in the procedure room; stopped before anesthesia | Hospital outpatient department or ASC; not physicians | One plan policy pays 50% of the allowed amount (CMS: hospital may receive 50% of OPPS) |
| 74 Discontinued after anesthesia or start | Stopped after anesthesia was given or the procedure began | Hospital outpatient department or ASC; not physicians | CMS: hospital may receive the full OPPS amount; one plan policy pays 100% |
Source: Noridian Medicare (2025); CMS Transmittal 442 (2005); Commonwealth Care Alliance payment policy; Johns Hopkins Health Plans policy RPC019. Plan figures are examples, not Medicare rules.
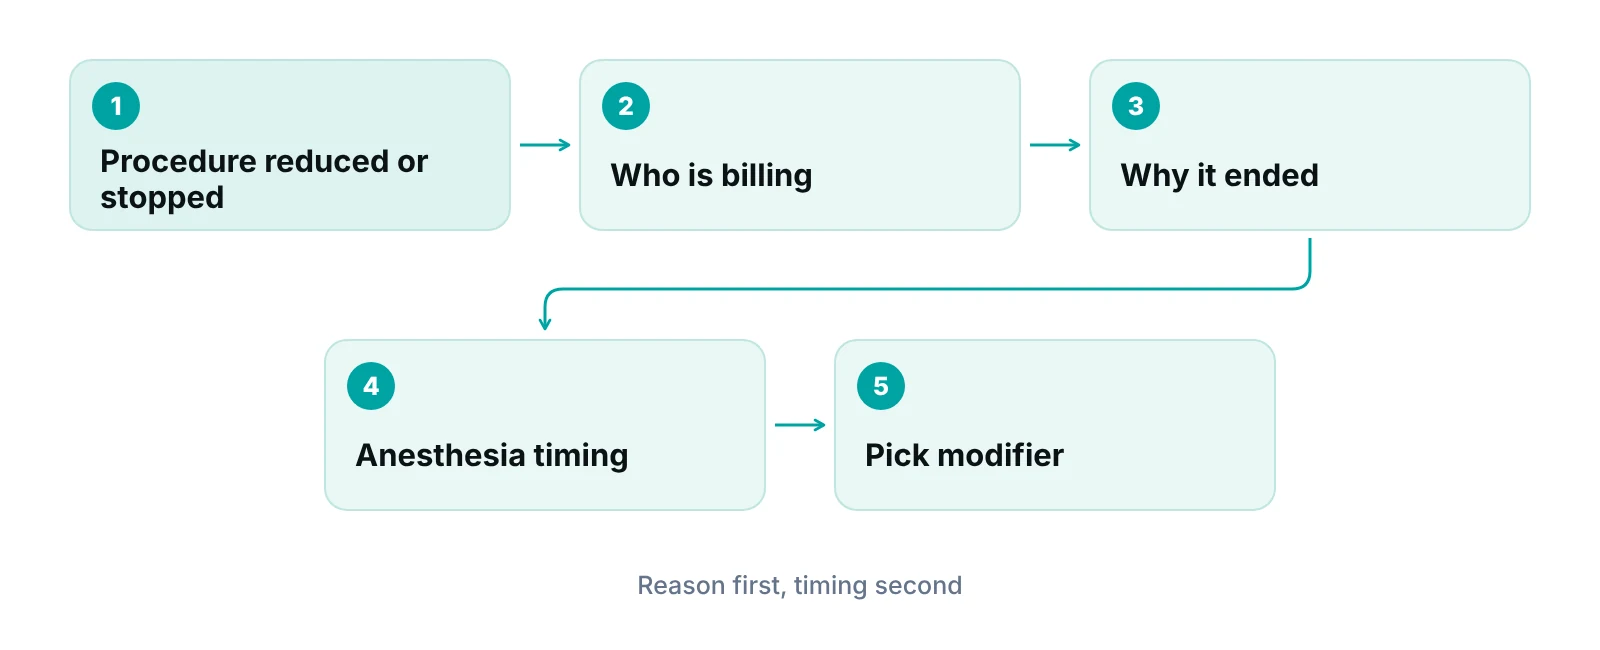
Commonwealth Care Alliance’s policy adds a useful rule for both 52 and 53: report them with a single procedure code and do not use them where a separate code describes the completed portion. It also says modifier 53 is not valid with E/M or time-based codes (CCA payment policy). A Johns Hopkins Health Plans policy adds that 73 and 74 are not to be reported by physicians and are not used on add-on codes (Johns Hopkins Health Plans).
If your billing team is also sorting out other modifiers that explain why a line looks unusual, our guides to modifier 91 for repeat lab tests, modifier 59 and modifier 79 cover those separately. They solve different problems from 52.
How to report modifier 52 on the claim and in the chart
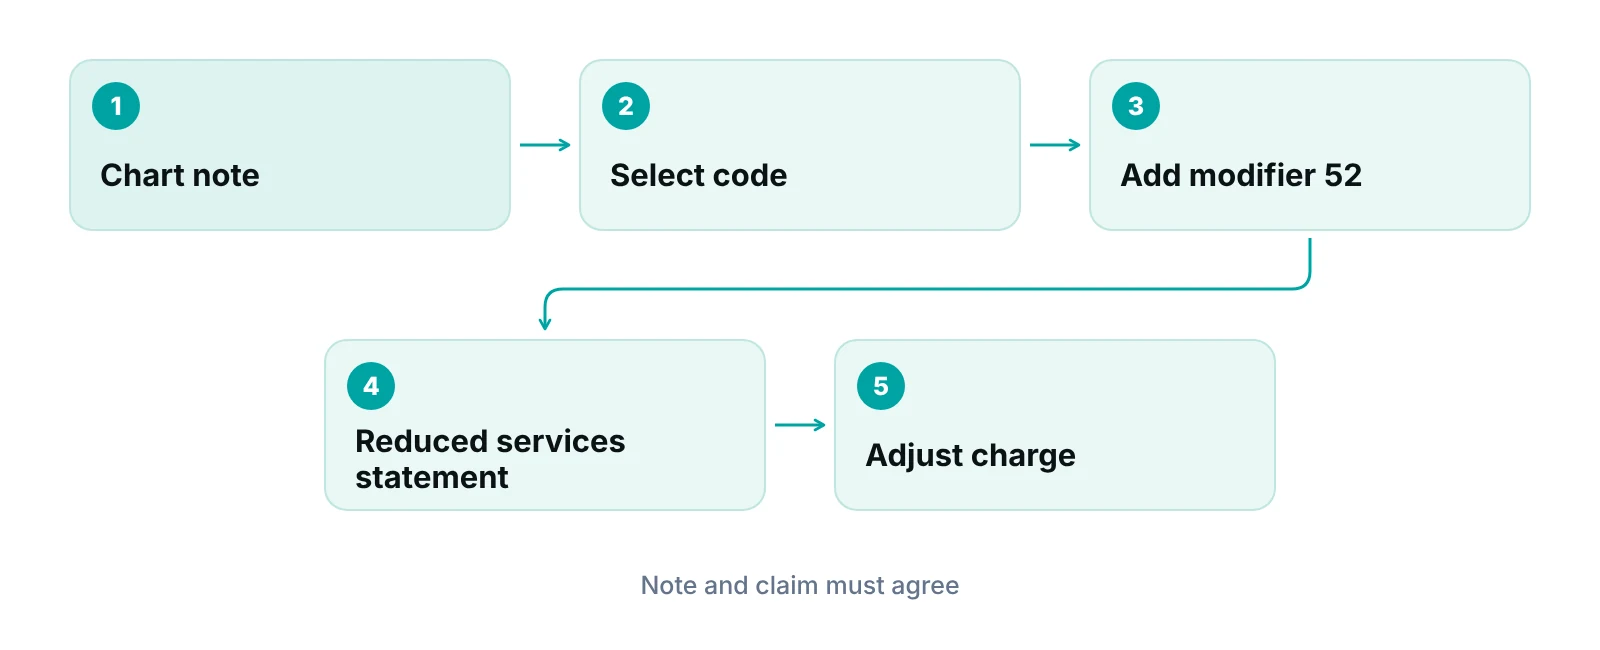
For Medicare Part B, put the words “reduced services” with a brief reason in Item 19 of the CMS-1500 or the electronic equivalent, and keep the complete reason in the patient’s record. That is Noridian’s instruction (Noridian Medicare). Other payers may ask for it in a different field or attach a report, so check the payer’s claim instructions.
What the chart note should say
- What the code normally includes and what was actually done.
- Who decided to reduce the service, and the clinical reason.
- That the reduction was not caused by a threat to the patient, which would point to modifier 53.
- The date, the provider and the setting, so the claim lines match the note.
Noridian also says that if a claim goes to redetermination, you should send a separate, concise statement explaining why the reduction was needed, with the operative report or chart notes (Noridian Medicare). A note written clearly on the day is far easier than one reconstructed months later.
Do not use the old shortcut
Older guides, including a previous version of this post, said modifier 52 can report an assistant surgeon or co-surgery role. It cannot. Those roles have their own modifiers, so confirm them in the current CPT book and your payer’s policy rather than using 52 as a catch-all.
How modifier 52 affects payment
Modifier 52 lowers the payment, and the amount depends on the payer. Under Medicare Part B, Noridian says to reduce the normal charge by the percentage of the service not provided. If 75% of the service was provided, reduce the billed amount by 25%, and Medicare pays the lower of the actual charge or the fee schedule allowance (Noridian Medicare).
Noridian also states that since January 1, 2008 contractors have applied a 50% payment reduction to discontinued radiology procedures and other procedures that do not require anesthesia (Noridian Medicare). That is a fixed rule for that group of procedures, separate from the proportional method above.
| Payer or policy | Payment rule for modifier 52 | Notes |
|---|---|---|
| Medicare Part B (Noridian) | Reduce the charge by the share of service not provided; Medicare pays the lower of charge or fee schedule | Example on the page: 75% provided means reduce the charge by 25% |
| Medicare Part B, discontinued radiology and non-anesthesia procedures | 50% reduction applied by contractors since Jan 1, 2008 | Facilities report the discontinuation with 52 as well |
| Priority Health (commercial and other plans) | 50% of the base fee schedule | Other adjustments such as multiple-procedure or bilateral pricing may still apply |
| Commonwealth Care Alliance | 50% of the allowed amount for the unmodified procedure | Modifier 53 is 25% in the same policy |
Source: Noridian Medicare (2025); Priority Health provider manual; Commonwealth Care Alliance payment policy. Figures are payer examples and can change.
The practical point: a reduced-service line should be priced on purpose. Billing a full charge and waiting for the payer to cut it creates avoidable adjustments. Billing a charge that already reflects the reduction, where the payer expects it, keeps expected payment and actual payment closer together.
This matters for denials too. A modifier 52 line with no reason, or a reduced service billed with a full-service code and no modifier, may be held for records, cut or denied. That is why many practices set the claim up to carry the reason before it ever reaches the payer.
Common modifier 52 mistakes
Most modifier 52 problems come from using it as a general-purpose adjustment. These are the patterns worth checking for in a claim review.
- Using 52 with E/M codes. Medicare and the payer policies above all say it is inappropriate there.
- Using 52 when 53 applies. If the procedure stopped because of the patient’s condition, the reason matters, and the modifier follows the reason.
- Using 52 for assistant or co-surgery roles. That is a different modifier family. Check the current CPT book.
- Adding RT or LT on top of 52 for a one-sided bilateral code. Noridian’s bilateral example says not to use RT or LT with 52 in that case.
- Facility claims with 52, 73 and 74 mixed up. Discontinued radiology and non-anesthesia procedures use 52 under the Medicare rule, while other discontinued outpatient procedures use 73 or 74.
- No reason in Item 19 or the chart. The reason is the whole case for the reduced payment.
- Billing the full charge. The reduced-service charge should reflect the share of the service actually provided where the payer expects that.
Many of these can be caught before submission by a claim scrubber or a rules check. Our overview of claim scrubbing and clean claim practices covers how those checks work, and our guide to modifier 25 vs 59 is a good companion for other commonly misused modifiers.
Catching modifier 52 problems before the claim goes out
The cheapest time to fix a modifier 52 error is before submission. A practice with a written rule for it can route every 52 line to a person who checks the reason, the charge and the code before release. If you outsource billing, ask what that step looks like; our medical billing services include coding support and claim scrubbing.
A practice management system that tracks claims by stage can also hold a claim at a review stage when a certain modifier appears, assign an owner, and run data-completeness checks before the claim is sent. That turns a billing rule into a step that happens every time.
When a reduced-service claim is denied or cut more than expected, the denial usually points back to missing documentation or a wrong modifier choice. Our medical billing denial management guide explains how to work those denials and appeals.
Want a second set of eyes on your modifier edits?
A free practice audit looks at how reduced-service and discontinued-procedure lines move through your billing today. There is no obligation.
Our recommendations
- Write one rule for modifier 52 and share it. We recommend a one-page rule that states when 52 is allowed, when 53 or 73/74 applies, and what the note must say. Billers, coders and providers should all work from the same page.
- Ask for the reason at charge entry. We recommend making the clinical reason a required field whenever a charge carries modifier 52. A reason captured on the day is easier than one chased after a denial.
- Block 52 on E/M lines. We recommend a hard stop in your billing system or scrubber for modifier 52 on any E/M code. It is one of the few rules every source above agrees on.
- Review the first 20 lines after any new payer contract. We recommend sampling reduced-service claims for each payer and comparing actual payment with the payer’s published rule. Percentages differ and are easy to miss.
- Keep a payer-by-payer cheat sheet. We recommend recording where each payer wants the reason (Item 19, an attachment or a note field) and how it prices 52 versus 53, 73 and 74. Review it each year when payer policies change.
- Train front-end staff on the difference between 52 and 53. We recommend a short training example for each, because the clinical reason, not the paperwork, decides which modifier applies.
Hold modifier 52 claims for review before they go out.
Our portal tracks each claim by stage with an owner and runs data-completeness checks before submission. Workflow rules can flag a claim for review or hold it at a stage, so a reduced-service line can be checked by a person first.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Modifier 52 works when the reduction was the provider’s choice, the code still describes the service, and the note and claim agree. When the reason is patient safety, a different modifier applies. If reduced-service claims are being cut or denied, our denial management services can help trace why, or you can talk to our team about your claim workflow.
Frequently asked questions
What does modifier 52 mean in medical billing?
Modifier 52 means reduced services. It tells the payer the provider chose to do less than the full procedure described by the code, and the base code still describes what was started. For Medicare Part B, it applies where anesthesia was not planned. The payer then adjusts payment for the reduced work.
What is the difference between modifier 52 and modifier 53?
Modifier 52 is a reduced service chosen by the provider. Modifier 53 is a procedure stopped because of extenuating circumstances that threatened the patient’s well-being. The reason for the change decides the modifier, not the timing alone. CMS also says 53 is not approved for outpatient hospital services.
Can modifier 52 be used with E/M codes?
No. Medicare contractor guidance calls modifier 52 inappropriate with evaluation and management codes, and payer policies from Priority Health and Commonwealth Care Alliance say the same. If an E/M visit was shorter or simpler, the answer is to code the level the documentation supports.
How much does modifier 52 reduce payment?
It depends on the payer. Medicare Part B says to reduce the charge by the share of the service not provided, and contractors apply a 50% reduction to discontinued radiology and other non-anesthesia procedures. Some plans pay 50% of the allowed amount. Always check the payer’s current policy.
Where does the reason for modifier 52 go on the claim?
For Medicare Part B, enter reduced services with a brief reason in Item 19 of the CMS-1500 or the electronic equivalent, and keep the full reason in the patient’s record. Other payers may ask for an attachment or a different field, so check each payer’s claim instructions.
Can facilities use modifier 52?
Under Medicare guidance, facilities use modifier 52 for discontinued radiology procedures and other procedures that do not require anesthesia. For other discontinued hospital outpatient or ASC procedures, CMS points to modifiers 73 and 74, based on whether anesthesia was given or the procedure had started.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Modifier 52: Partially Reduced or Eliminated Services (JF Part B) — Noridian Healthcare Solutions (Medicare) (2025)
- Modifier 52: Partially Reduced or Eliminated Services (JE Part B) — Noridian Healthcare Solutions (Medicare) (2025)
- Modifier 52, reduced services — Priority Health (2025)
- Payment Policy: Reduced Services and Discontinued Procedures — Commonwealth Care Alliance (2022)
- Transmittal 442, Change Request 3507: Use of Modifiers for Discontinued Services — CMS (2005)
- RPC019 Discontinued Procedures — Johns Hopkins Health Plans (n/d)
Disclaimer: This article is educational and is not legal, coding, clinical or compliance advice. CPT is owned by the American Medical Association, payer rules vary, and the figures cited are examples from named payers. Confirm each rule in the payer's current policy and the current CPT book before you bill.
