

Behavioral health eligibility verification is the process of confirming a patient’s active coverage, behavioral-health-specific benefits, and any prior-authorization requirements before the first session — not after. Mental health and substance use benefits are frequently carved out to a separate payer. Skipping this step is one of the most preventable reasons a clean session turns into a denied claim.
Every hour you spend on a billing discrepancy is an hour not spent with a patient. The same is true of every call about a session that wasn’t covered after all.
In behavioral health, carve-outs and session limits are the rule, not the exception. Eligibility problems are one of the most common reasons that hour gets lost. They also show up as a clinical problem before they show up as a financial one. A client can’t start treatment, or stops mid-course, because nobody confirmed what their plan would pay for.
How Much Does a Missed Eligibility Check Actually Cost a Practice?
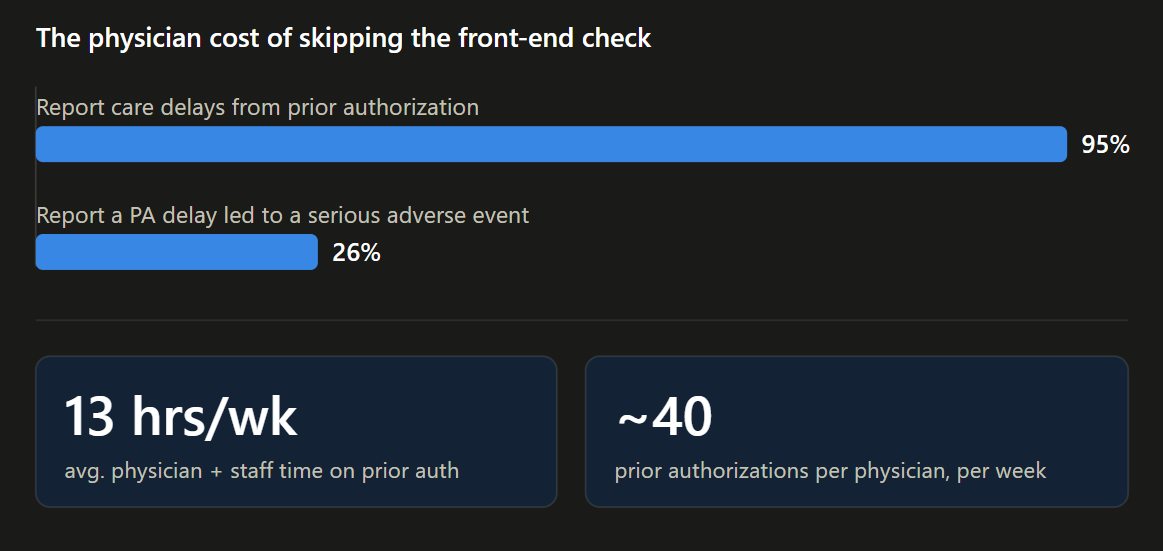
A missed or rushed eligibility check costs a practice in two ways: staff time reworking the resulting denial, and physician time lost to prior-authorization follow-up. Change Healthcare’s claims-data research, cited in MGMA’s denial-management guidance, puts the average cost of reworking a single denied claim between $25 and $118. Nationally, physicians report losing an average of 13 hours a week to prior authorization alone.
That second figure comes from the AMA’s 2025 Prior Authorization Physician Survey, published May 2026 (1,000 U.S. physicians). In it, 95% of respondents reported care delays tied to prior authorization.
Another 26% reported that a delay led to a serious adverse event for a patient in their care. Neither figure is behavioral-health-specific; the survey covers medicine broadly. But they’re a conservative floor for a specialty where prior authorization and carve-out coordination are the norm, not the exception.
How Is Behavioral Health Eligibility Verification Different From a Standard Medical Check?
Behavioral health eligibility verification has to confirm a second layer that a standard medical check doesn’t. That means checking whether mental health and substance use benefits are carved out to a separate managed behavioral health organization (MBHO), and what session limits apply. It also means confirming whether the specific service — psychiatric evaluation, therapy, medication management, IOP (intensive outpatient program), telehealth — requires prior authorization. The name printed on a patient’s insurance card isn’t always who processes the behavioral health claim.
That carve-out mismatch is the single most common reason a “verified” patient still gets denied. Front desk confirms active medical coverage. But the behavioral-health benefit often sits with a different administrator entirely, with its own session caps and prior-auth rules.
For substance use disorder programs, verification also has to account for 42 CFR Part 2. That’s the federal rule governing how SUD treatment records can be shared, including with the payer processing the claim.
| Reason code | What it means | How verification prevents it |
|---|---|---|
| CO-27 | Expenses incurred after coverage terminated | Re-verify at every visit for patients near a plan-year boundary or known coverage lapse |
| CO-31 | Patient cannot be identified as our insured | Confirm the carve-out/MBHO payer directly — not just the medical plan on the card |
| PR-1 / PR-2 | Deductible or coinsurance — patient responsibility | Calculate and communicate patient responsibility before the session, not on the statement |
| CO-197 | Precertification or authorization absent | Confirm prior-auth requirement and session limits before the visit is scheduled |
| Standard CMS/X12 Claim Adjustment Reason Codes (CARC), current as of the 2026 code set. | ||
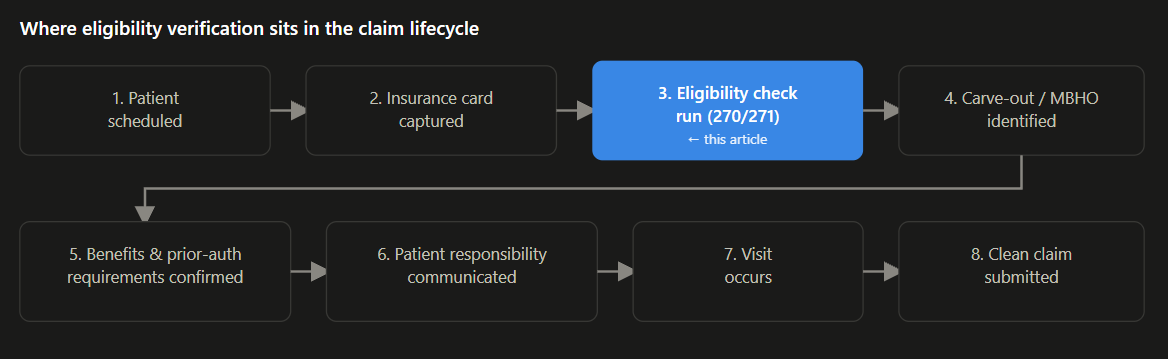
Highlighted step is the subject of this article — see the Behavioral Health Billing RCM pillar for the full lifecycle, intake through payment posting.
RCM Finder behavioral health claim lifecycle, intake through payment posting. Eligibility verification (step 3) is upstream of every step that follows.
How Often Should Coverage Be Re-Verified During Treatment?
Coverage should be re-verified at minimum monthly for any patient in ongoing treatment — not just once at intake. Re-check immediately whenever a plan year turns over, a patient mentions a job or insurance change, or treatment crosses a session-limit threshold. A benefit that was active in January isn’t guaranteed to still be active in July.
Ownership matters as much as cadence. Front desk is usually best positioned to capture the insurance card and flag anything that’s changed since the last visit. Billing is usually best positioned to own the 270/271 query itself and track session limits against utilization.
It should also flag when a patient is approaching a cap. The failure mode usually isn’t picking the wrong owner. It’s leaving the handoff between the two undefined, so re-verification only happens when someone remembers.
In-House, Outsourced, or Automated: What’s the Real Difference?
The difference isn’t just who does the check. It’s whether verification happens in real time against the payer, through a 270/271 transaction or a live portal query. Or whether it relies on a stored eligibility record that can be days or weeks stale by the time the patient is seen.
Manual, phone-based verification is real-time too, but it doesn’t scale. It takes roughly the same staff-minutes on patient 200 as it did on patient one.
Consider a 12-provider behavioral health group running roughly 40 new-patient intakes a week. That’s well above what most practices in this space report. Even so, it’s still about four claims a week needing rework. Multiply that across a year against the $25–$118 rework-cost range cited above, and the front-end check stops looking like an administrative nicety.
| Manual (staff, one at a time) | Automated / outsourced | |
|---|---|---|
| Verification method | Phone or payer portal, per patient | Real-time 270/271 query at scale |
| Typical turnaround | Same-day to 24+ hours, staff-dependent | Real-time to same-day |
| Re-verification cadence | Often intake-only | Scheduled re-checks (plan-year turnover, monthly for active patients) |
| Staff time required | Scales directly with patient volume | Scales independent of front-desk headcount |
| Visibility into status | Sits in one staff member’s inbox or notes | Tracked in a shared dashboard |
| Clean-claim rate | Monthly claim volume (illustrative) | Est. claims reworked/month | Est. monthly rework cost* |
|---|---|---|---|
| 80% | 300 | 60 | $1,500–$7,080 |
| 90% | 300 | 30 | $750–$3,540 |
| 95% | 300 | 15 | $375–$1,770 |
| *Based on the $25–$118 per-claim rework-cost range (Change Healthcare research, via MGMA). Illustrative — run your own volume through the Revenue Calculator. | |||
Expert Recommendations for Behavioral Health Eligibility Verification
- Verify 48–72 hours before every new-patient intake. If the payer or plan can’t be reached, verify again within 24 hours of the visit. A same-day-only check leaves no room to resolve a carve-out mismatch before the patient arrives.
- Track session-limit and prior-auth-lapse denials as their own category, separate from coding denials, and review the count monthly. More than a handful of claims in that bucket means the gap is upstream of billing, not inside it.
- Re-verify at every plan-year turnover, and at minimum monthly for any patient still in active treatment. Deductibles reset and carve-out vendors change. A benefit active in January isn’t guaranteed to still be active in July.
- Above roughly 15–20 behavioral health intakes a week, manual, one-at-a-time eligibility checks stop being the efficient option. That’s typically the volume where automated or outsourced verification starts paying for itself in recovered staff time. RCM Finder’s Free Practice Audit can confirm where that threshold sits for your own volume.
Trust & Track Record
RCM Finder’s behavioral health clients run eligibility and benefits verification inside a HIPAA-compliant workflow. It operates under a signed Business Associate Agreement, with data encrypted in transit and at rest. Verification status is visible in real time through the same dashboards in our own practice management system used for claims and A/R. Confirmed EHR integrations include PrognoCIS, eClinicalWorks, and Athenahealth.
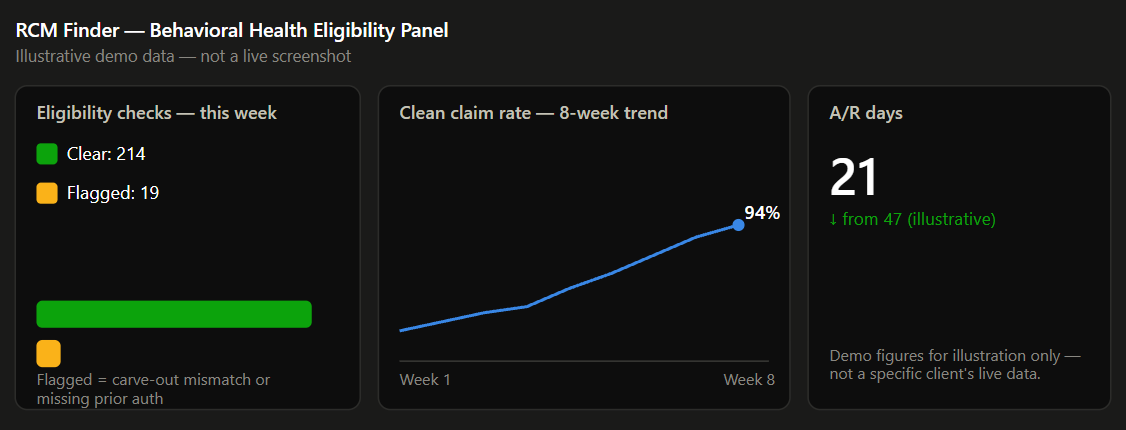
“Illustrative mock of the RCM Finder dashboard in our own practice management system view for behavioral health eligibility tracking. Demo data, not a live screenshot or a specific client’s results.”
The Bottom Line
Behavioral health eligibility verification isn’t a back-office detail. It’s the checkpoint that decides whether a course of treatment stays funded long enough to work, and it’s one piece of the broader Behavioral Health Billing RCM picture, from intake through payment posting.
If you’re not certain how many of last month’s denials trace back to a missed coverage gap, the Free Practice Audit answers that directly. It’s a review of your last 30 days of claims, billing leaks, and front-end bottlenecks — at no cost. The next hour you’d lose to a billing call goes back to a patient instead.
