
Cataract co-management, intravitreal drug claims, OCT limits and Medicare Advantage step therapy, handled with front-desk staff, patient marketing and a claims portal built on CMS and MAC rules.
By Awais Afzal | Healthcare Operations & Data Analyst
Published October 12, 2026 · Last reviewed October 12, 2026 · Next review April 12, 2027
Quick answer
Ophthalmology billing services manage the claims an eye practice creates: eye exam and E/M visits, cataract surgery with co-management modifiers 54 and 55, intravitreal drug claims with correct units and JW or JZ, OCT frequency limits and Medicare Advantage step therapy. RCM Finder pairs that billing with front-desk assistants, patient marketing and a claims portal.
On this page
Ophthalmology billing needs a specialist because one eye practice runs several billing models at once: routine vision visits, medical eye exams, 90-day cataract surgery packages and injected drugs billed by the milligram. Each has its own rules, and imaging limits change by Medicare Administrative Contractor (MAC).
CMS's CY 2025 fee schedule fact sheet extended modifier 54 to every 90-day global surgery where the surgeon expects to provide only the operation, even when the transfer is informal. For 2026, the CY 2026 final rule fact sheet (October 31, 2025) sets the conversion factor at $33.40 for clinicians who are not qualifying APM participants, up from $32.35. It also applies a -2.5% efficiency adjustment to work RVUs of services that are not time-based; E/M visits are exempt.
Revenue in an eye practice leaks at the handoffs: a retina patient switches plans, a co-management letter never reaches the chart, a drug line goes out without JZ. We run all four pillars against one set of payer rules.
Our healthcare digital marketing builds demand for cataract, glaucoma and retina care through local SEO, Google Ads and reputation work.
Our virtual medical assistants for eye practices work on your practice's time zone. They sort medical and vision coverage, start drug and surgery authorizations, and check step therapy history and scan dates.
Our end-to-end ophthalmology revenue cycle management covers coding support, claim scrubbing, denial management and A/R follow-up, with added checks for 54 and 55, RT and LT, drug units and JW or JZ.
Our practice management system tracks every claim by stage, applies specialty-aware billing logic per claim, checks data completeness before submission and flags payments below the expected amount.
Find where your eye care claims leak
We review recent visit, surgery and injection claims, denials and authorization logs, then show what to fix first. Pricing is quoted after the audit.
Each service line has its own coding, frequency or documentation rule. Codes are in our own words (the AMA owns CPT descriptors); check the current code set and your MAC's article.
| Service line | Code examples (our wording) | Billing rule to check | Common denial or leak |
|---|---|---|---|
| Office visits | 92002, 92012 (intermediate); 92004, 92014 (comprehensive); or E/M such as 99204 | Comprehensive visit: all 12 exam elements plus a plan (AAO) | Elements missing; payer frequency edits on eye codes |
| Refraction | 92015 (glasses or contact lens prescription test) | Excluded by Medicare; GY modifier; ABN optional (GX) | Fee not collected because the patient was not told |
| Cataract surgery | 66984 (lens removal with implant); 66982 (complex) | 90-day global; 66982 needs a non-routine device or technique in the op note (CGS) | Complex code without the device documented |
| Co-managed post-op care | Surgery code with 54 (surgeon) or 55 (post-op provider) | Written transfer and consent; surgery date as date of service; care dates in Item 19 | 55 billed before a post-op visit; 54 missing when a transfer was expected |
| Intravitreal injection | 67028 plus drug: J0178 (aflibercept, 1 mg), J2778 (ranibizumab, 0.1 mg), J2777 (faricimab, 0.1 mg) | Units match the dose; RT or LT on each drug line if eyes get different drugs; JZ, or a JW line | Missing JW or JZ; overfill billed |
| OCT imaging | 92133 (optic nerve); 92134 (retina) | WPS: glaucoma 1 or 2 tests a year; retina 1 per eye every 2 months, monthly during injections | Scans over the limit; both codes reported together |
| Oculoplastics in a hospital outpatient department | 15820 to 15823, 67900 to 67904, 67906, 67908; 64612, 64615 with J0585 to J0588 | Medicare prior authorization since July 1, 2020; ASC and office cases excluded | No approval, so hospital and physician claims deny |
Sources: AAO; CMS manuals, MLN907166 (2025), JW/JZ FAQ and OPD program; First Coast; Palmetto GBA; Noridian; MCD A56453, A53387, A56916, L34760 (checked October 2026); AAPC. Rules vary by MAC and payer.
Office visits can be reported with eye codes (920xx) or E/M codes. The AAO fact sheet says a comprehensive eye visit needs all 12 exam elements and a started or continued plan; an intermediate visit needs at least three. An AAO coding article notes that some commercial payers apply frequency edits to eye codes but not E/M. We set the rule per payer.
Medicare does not cover routine eye exams for glasses, and the Benefit Policy Manual excludes refractions by any practitioner. The exclusion does not reach physician services for eye disease, such as glaucoma or cataracts. First Coast says the GY modifier marks a statutorily excluded service and no ABN is needed. Medicare covers one pair of glasses after cataract surgery with an implanted lens and glaucoma tests once every 12 months for high-risk patients. See our ABN billing guide.
Under WPS LCD L34760 (revision effective June 26, 2025; Part B in Indiana, Michigan, Iowa, Kansas, Missouri and Nebraska), glaucoma usually needs one or two OCT tests a year. Retinal disease allows at most one exam per eye every two months, or one per eye each month during active injections. CGS article A56692 uses similar limits. The AAO advises against reporting 92133 and 92134 together. Other MACs may differ.
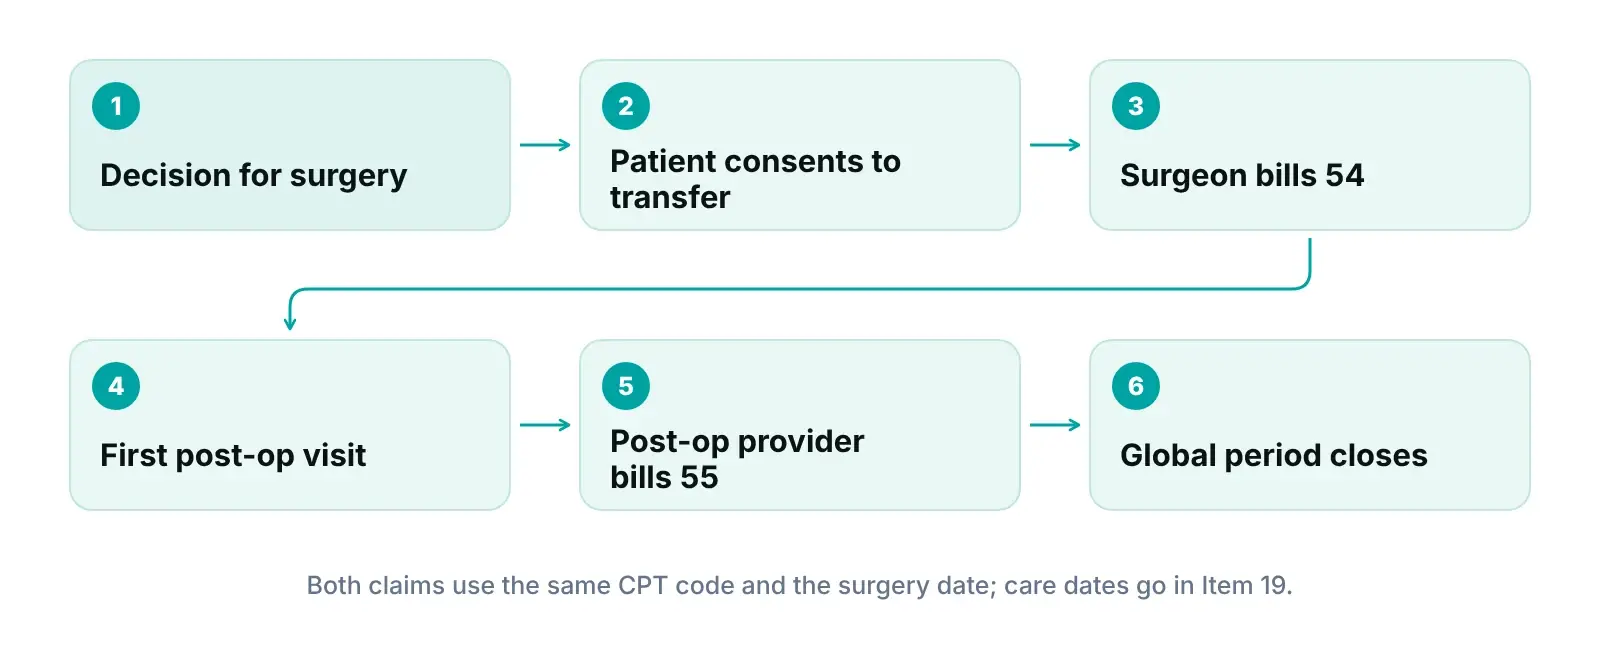
Cataract surgery is paid as a 90-day global package. When another doctor takes over post-op care, the surgeon bills modifier 54 and the post-op provider bills 55, backed by a written transfer.
CMS's global surgery booklet (December 2025) says the package covers the day before surgery, the day of surgery and 90 days after. Modifier 57 marks the decision-for-surgery visit and 24 an unrelated post-op visit. For another procedure inside an open global period, CMS defines 58 (staged), 78 (unplanned return to the operating room) and 79 (unrelated).
Both co-managing doctors bill the same code and the surgery date. The transfer must be documented, and the new doctor must see the patient before billing. Palmetto GBA, a Medicare contractor, values cataract post-op care at 20% of the package and asks for the patient's written consent and care dates in Item 19. It says co-management should not be routine and bans quid pro quo arrangements.
Under CGS article A56453, complex cataract surgery (66982) needs a device or technique not used in routine surgery, such as iris hooks or a capsular support ring, named in the op note. With a premium lens, Palmetto says the patient pays for added refractive testing and the lens cost difference. See our cataract surgery CPT codes guide and our guide to getting paid for co-managed post-op care.
Each intravitreal injection is billed as two lines: the injection (67028) and the drug, in units that match the dose. Commercial, Medicare Advantage and Medicaid plans may require prior authorization for anti-VEGF drugs, and some add step therapy.
Palmetto article A53387 (effective July 1, 2026) lists J0178, J0177 and biosimilar Q-codes for aflibercept. When each eye gets a different drug, RT or LT goes on the drug line. Coding for intravitreal bevacizumab depends on the MAC; in 2022 the AAO reported that Novitas said J9035 should not be used. See our J-codes billing guide.
For a single-dose container, CMS's JW and JZ FAQ requires a JW line for any discarded amount and, since July 1, 2023, JZ when nothing is discarded. Under 42 CFR 414.904, Part B generally pays these drugs at 106% of average sales price; biosimilars get their own ASP plus 6% (8% if qualifying) of the reference product's. CMS posts new payment limits each quarter, so we check drug payments against the current file.
Under a policy in a 2018 CMS fact sheet, Medicare Advantage plans may apply step therapy to Part B drugs from January 1, 2019. Under 42 CFR 422.136, it applies only to new administrations, with a lookback of at least 365 days. The AAO notes a plan may require bevacizumab (Avastin) before aflibercept (Eylea) or ranibizumab (Lucentis), and it opposes the practice.
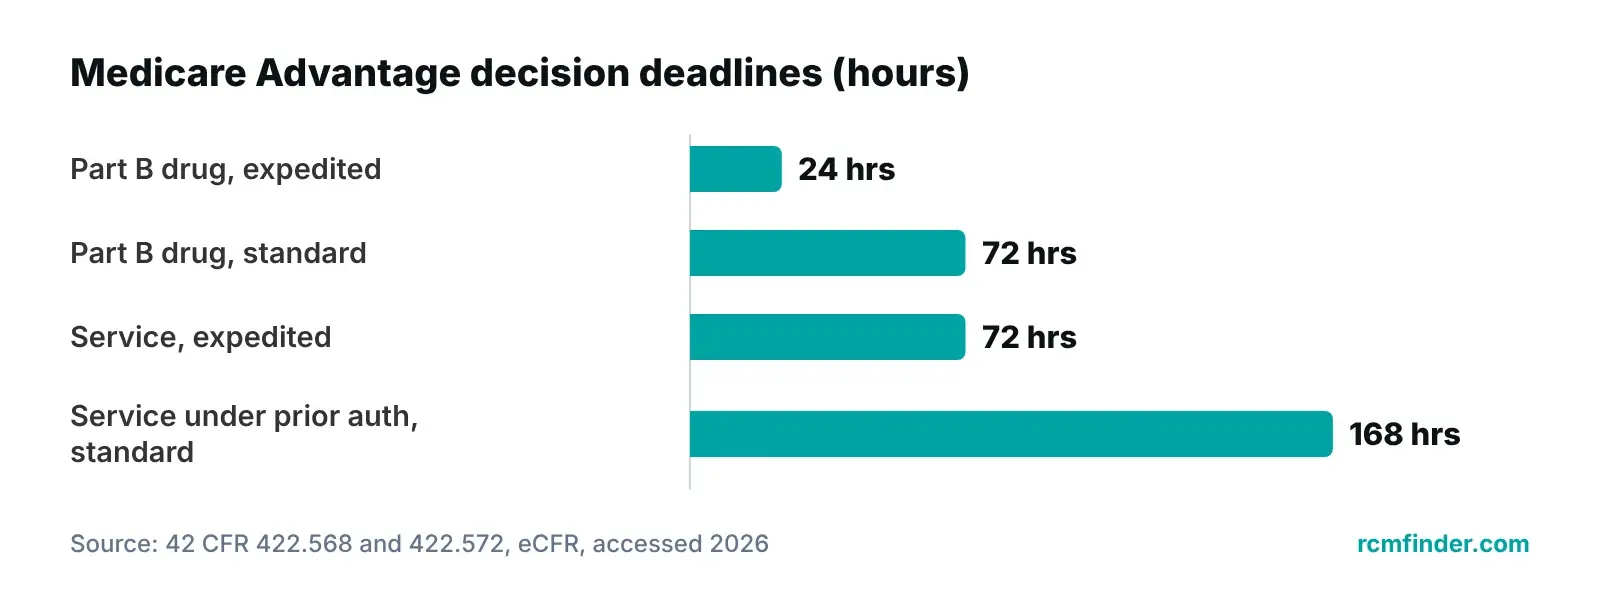
Plans must decide standard Part B drug requests within 72 hours and expedited ones within 24 hours, with no extensions, under 42 CFR 422.568 and 422.572. From January 1, 2026, other services under prior authorization get seven calendar days, and the CMS-0057-F rule requires a specific denial reason, though it excludes drugs. A 2023 CMS fact sheet adds a transition of at least 90 days for patients mid-treatment who switch plans.
In the AMA’s 2025 survey of 1,000 physicians across specialties, released May 2026, physicians reported 40 prior authorizations and 13 hours of physician and staff time each week.
Under a CMS program, hospital outpatient blepharoplasty and botulinum toxin injections have needed Medicare prior authorization since July 1, 2020 (Noridian lists the codes). Per the CMS FAQ, related physician claims deny without it; ASC and office cases are excluded.
| Rule | Source | What the VMA checks |
|---|---|---|
| MA step therapy for Part B drugs: new administrations only, 365-day lookback or longer | 42 CFR 422.136 | Last drug and dose date per eye |
| Plan may require a lower-cost drug and a documented failed response first | AAO retina page | Prior drugs and response charted before the request |
| MA Part B drug decisions: 72 hours standard, 24 hours expedited | 42 CFR 422.568, 422.572 | Request time logged; follow-up at the deadline |
| Other MA services under prior auth: 7 calendar days standard from 2026; specific denial reason | 42 CFR 422.568; CMS-0057-F | Surgery request sent at the decision; denial reason saved |
| Plan switch: at least 90-day transition for an active course of treatment | CMS-4201-F fact sheet (2023) | Plan change asked at each visit |
| Hospital outpatient blepharoplasty and botulinum toxin need approval | CMS OPD program; Noridian | Site of service; approval on file |
| OCT limits: retina 1 per eye every 2 months, monthly during injections | WPS LCD L34760 (2025) | Last scan date per eye |
Sources: eCFR 42 CFR 422.136, 422.568, 422.572 (October 2026); CMS (2023, 2024, 2026); AAO; Noridian; WPS L34760. Check each member's plan.
For the full workflow, read our prior authorization guide and our tips to speed up medication prior authorization.
See what drug and authorization delays cost
Enter your claim volume and denial rate to estimate what your eye practice is losing, then bring the numbers to your audit.
Eye practices grow through local search, reviews and referring optometrists, and each channel has rules.
HHS guidance says tracking tools on login or appointment pages can collect protected health information, and a cookie banner is not a HIPAA authorization. A 2024 court order vacated part of it, but we still keep tracking off scheduling forms unless the vendor signs a BAA. The FTC's 2024 rule bans fake reviews and incentives tied to review sentiment.
With optometrists, we build a fast referral path but never promise post-op care in return. For optometry partners, see our guides to optometry billing services and managing an optometry practice.
Stay in-house if you have experienced eye care coders and front-desk time for authorizations. Use a billing-only vendor if claims are your only gap. Choose a combined partner when problems span scheduling, authorizations, billing and growth. Either way, judge an ophthalmology billing company on its work with your service lines, technology that shows every claim, and fees explained in writing.
| Job | In-house team | Billing-only vendor | Four-pillar partner (RCM Finder) |
|---|---|---|---|
| Drug prior authorization and step therapy | Front desk, between calls | Usually left to the practice | VMA checks history and tracks each request |
| Drug units, JW or JZ, payment limits | Depends on one biller | Fixed after the fact | Checked before submission and after payment |
| Co-management letters and dates | Paper, often missing | Bills what it receives | VMA collects letters; RCM checks dates |
| Vision or medical coverage | Sorted at check-in | Usually out of scope | Sorted at scheduling |
| Patient growth and reviews | Separate agency, or nobody | Not included | Marketing tied to booked consults |
| Reporting | EHR reports | Claim reports only | Portal and dashboards, consult to paid claim |
| Cost structure | Salaries, benefits, turnover | Varies; ask how fees are set | Quoted after a free practice audit |
We start with a free audit and change nothing until you see the findings. We build our billing pipeline around how claims actually move through a practice: registration, charge entry, submission, payment and follow-up. For ophthalmology, we add the checks on this page.
We review recent visit, cataract, injection and imaging claims, denials and authorization logs.
We put a Business Associate Agreement in place before accessing patient data. Then we work inside your existing EHR (for example PrognoCIS, eClinicalWorks or athenahealth).
Your MAC's articles and your plans' drug, surgery and step therapy rules become a pre-visit checklist and portal rules.
VMAs sort coverage, start authorizations and collect transfer letters. Claims are scrubbed, submitted and worked through denials and A/R.
We review denials by reason, A/R days, drug underpayments, authorizations cleared in advance and new consults.
Talk to us about your eye practice
Tell us your service lines, your MAC and your hardest payer. We will tell you honestly whether we fit.
Any billing vendor that handles your patients' data is a HIPAA business associate and needs a Business Associate Agreement before any access. HHS names billing and claims processing as business associate work. The minimum necessary standard limits use to what each task needs, and the Security Rule's technical safeguards require access control, audit controls, integrity, person or entity authentication and transmission security.
Co-management also raises anti-kickback questions. In Advisory Opinion 11-14 (2011), OIG said it would not sanction one ophthalmology group's plan, relying on its certifications: no co-management agreements, transfers only when clinically appropriate and requested by the patient, and disclosure of extra fees. The opinion protects only that group.
We use role-based access, audit logging and encrypted (HTTPS) connections, and we put a Business Associate Agreement in place before accessing patient data. For your side, use our HIPAA compliance checklist.
We would rather tell you now than after you sign. Here is where we fit and where we do not.
A good fit if you are
Probably not a fit if you are
What we would do first if we were running your practice's revenue cycle tomorrow.
We ask why the patient is coming in. A glasses check goes to the vision plan or self-pay; a disease visit goes to medical insurance.
We note the last drug and dose date per eye. If the gap passes the plan's lookback, we check its preferred drug first.
Units match the dose, JZ or JW is present, and payment matches the current quarter's limit.
The transfer letter, consent and care dates belong in both charts before the 54 and 55 claims go out.
We bill 66982 only when the note names the device or technique that made the case complex.
Glaucoma and retina limits differ. We keep the last scan date per eye in front of the scheduler.
They cover coding support, claim scrubbing, submission, denial management and A/R follow-up for eye exams, E/M visits, cataract and other surgery, intravitreal injections and imaging. A strong service also sorts vision and medical coverage at scheduling, clears drug and surgery authorizations, and checks drug units and co-management dates before claims go out. RCM Finder adds front-desk assistants, patient marketing and a claims portal, so one team owns the work from booking to payment.
Ask for experience with your service lines, such as cataract co-management, anti-VEGF drugs and oculoplastics. Ask how they handle JW and JZ modifiers, step therapy and your MAC's OCT limits. Confirm they sign a Business Associate Agreement before any access, show you claims by stage and explain fees in writing. We put a Business Associate Agreement in place before accessing patient data and quote pricing after a free practice audit.
The surgeon bills the surgery code with modifier 54, and the doctor who takes over post-op care bills the same code with modifier 55. Both use the surgery date as the date of service. CMS requires a documented transfer of care, and the post-op provider must see the patient before billing. Palmetto GBA values cataract post-op care at 20% of the global package and asks for the assumed-care date in Item 19.
Yes, for separately payable Part B drugs from single-dose containers. Since July 1, 2023, CMS has required JZ when nothing is discarded, and a discarded amount goes on a separate line with JW. Since October 1, 2023, claims missing these modifiers can be returned as unprocessable. Overfill cannot be billed. The rules do not apply to multiple-dose containers or to drugs packaged into hospital outpatient or ASC payment.
Yes. Since January 1, 2019, Medicare Advantage plans may apply step therapy to Part B drugs, but only to new administrations, with a lookback of at least 365 days. A plan may require a lower-cost drug such as bevacizumab first. Plans must decide standard Part B drug requests within 72 hours and expedited ones within 24 hours, with no extensions. Check the last dose date before every new request.
No. Medicare excludes routine eye exams for glasses or contacts and refractions by any practitioner. It still covers physician services for eye disease, such as glaucoma or cataracts, and one pair of glasses or contacts after cataract surgery with an implanted lens. A refraction can be reported with the GY modifier; an ABN is not required, though a voluntary one uses GX. Tell patients about the fee before the visit.
Tell us about your practice. A member of our operations team replies within one business day.
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Tell us about your practice
About the author: Awais Afzal
Healthcare Operations & Data Analyst, RCM Finder
Awais has spent more than 16 years in healthcare digital marketing and clinical operations management. He builds data-driven revenue cycle blueprints for high-ticket medical practices and leads product development of the RCM Finder portal. More about our team.
How we write: every figure, code and rule on this page was checked against the primary source listed below and independently fact-checked before publishing. We re-review this page every six months. Last reviewed October 12, 2026; next review April 12, 2027.
We use cookies to understand how our site is used and to measure our advertising. You can accept or reject non-essential cookies. See our Privacy Policy.