
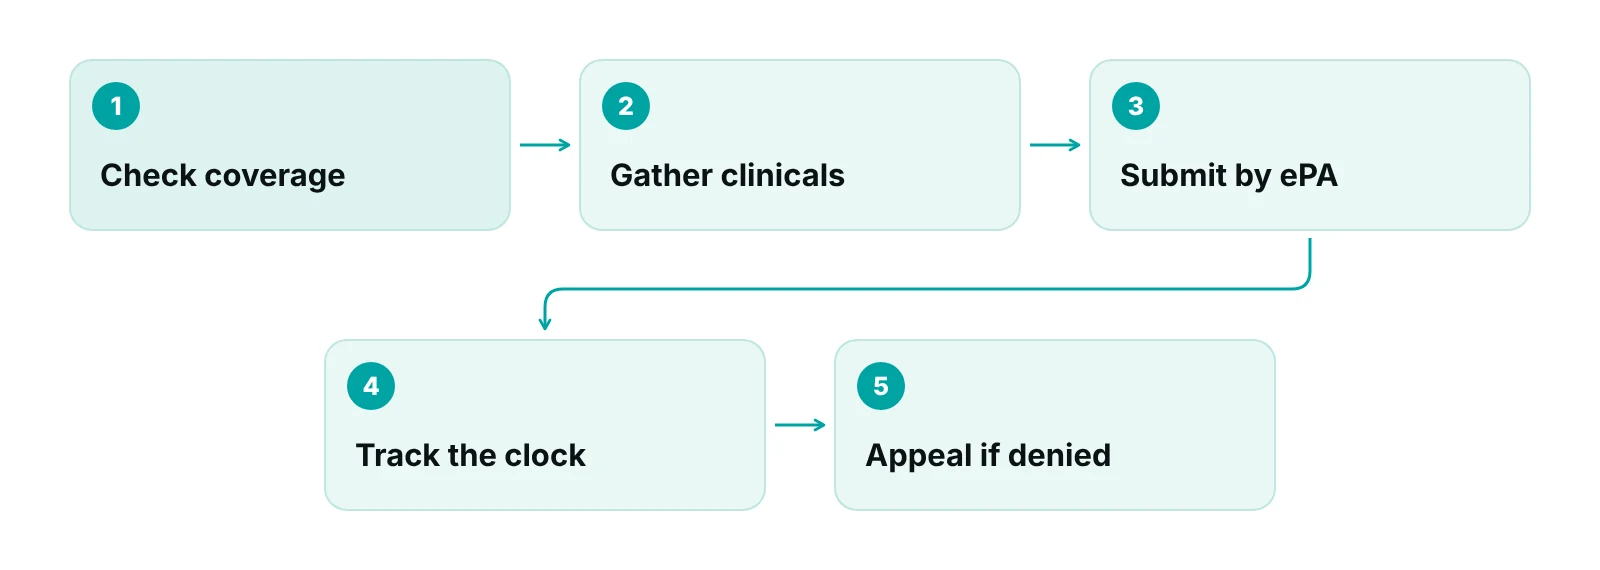
To speed up prior authorization for medication, send a complete request the first time, use electronic prior authorization where the payer supports it, track each request against the payer's deadline and give every case a named owner. Medicare Part D plans have 72 hours for a standard decision and 24 hours for an expedited one.
Prior authorization for medication is a process problem more than a payer problem. Practices that decide who owns each request, what goes in the first submission and when to follow up spend less time on hold. Below, we walk through the steps in the order a request moves, with the federal timelines that apply to Medicare Part D and the places where drug requests differ from medical-benefit authorizations. This guide is for practice owners and managers. It is not clinical advice.
Key takeaways
- Most delays come from incomplete requests and unowned follow-up, which a practice controls.
- Medicare Part D sets 72 hours (standard) and 24 hours (expedited) for coverage determinations; other payers differ.
- CMS says its 2024 prior authorization rule (CMS-0057-F) does not cover drugs.
- Electronic prior authorization removes fax and phone steps where the payer supports it.
- Every open request needs a name, a due date and a next action.
Why medication prior authorization stalls
Most delays come from the practice’s side of the desk: an incomplete first request, a request sent through the wrong channel, or a pending case nobody owns. Payer review time matters, but you cannot change it. You can change what you send and how you follow up.
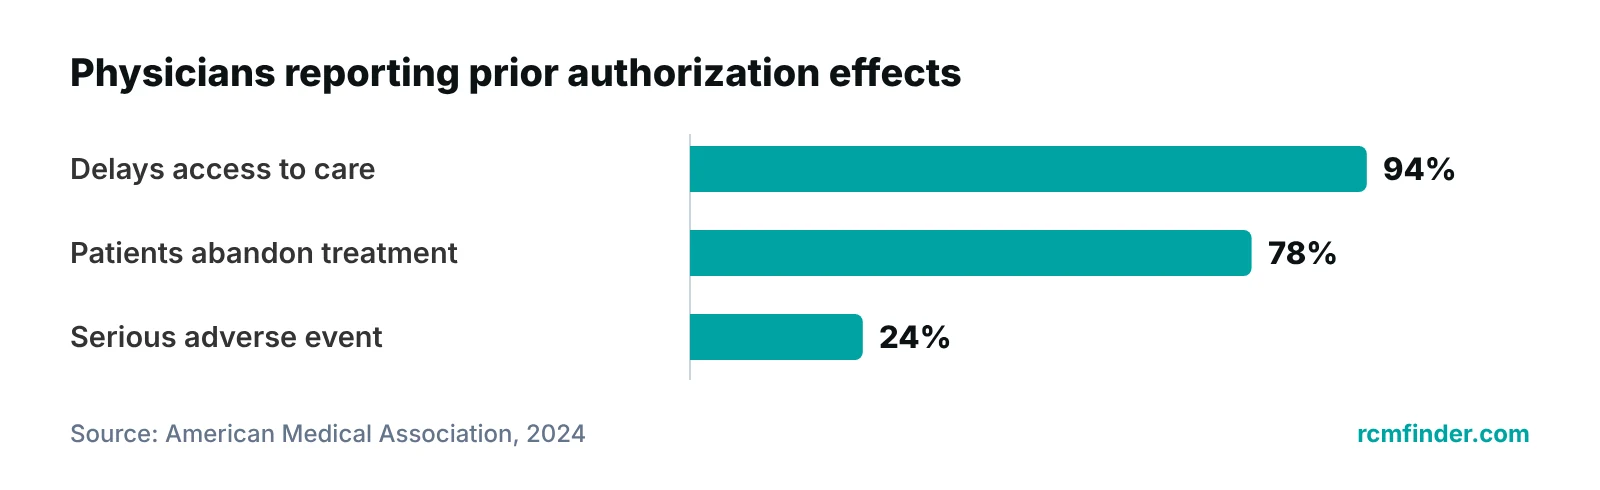
The burden is real. In the AMA’s prior authorization physician survey (reported in July 2024), 94% of physicians said prior authorization always, often or sometimes delays patients’ access to necessary care. Practices reported completing an average of 43 prior authorizations per physician each week, using about 12 hours of physician and staff time. And 78% said it often or sometimes leads patients to abandon a recommended course of treatment.
This post covers medications, meaning drugs billed through a pharmacy benefit or a Part D plan. For the wider process, including medical-benefit services such as imaging and procedures, start with our complete prior authorization guide for providers. Drugs run on different timelines and different electronic systems, which is why they need their own playbook.
Know the clock before you start
For Medicare Part D drug plans, a standard coverage determination has a 72-hour clock and an expedited one has a 24-hour clock, according to CMS’s Part D appeals flowchart. Commercial and Medicaid plans set their own timelines, so ask each major payer for its standard and urgent turnaround in writing and keep the answers in one reference sheet.
| Request type | Standard | Expedited | When the clock starts |
|---|---|---|---|
| Drug coverage determination | 72 hours | 24 hours | When the plan receives the request |
| Formulary or tiering exception | 72 hours | 24 hours | When the plan receives the prescriber’s supporting statement |
| Payment (reimbursement) request | 14 days | Not listed in the chart | When the plan receives the request |
| Plan misses the deadline | Treated as an adverse decision | Treated as an adverse decision | Plan must forward the case to the independent review entity within 24 hours |
Source: CMS, Part D appeals flowchart; 42 CFR 423.572 (eCFR text via Cornell LII)
Two details save time. First, on an exception request the clock does not start until the plan has the prescriber’s supporting statement, so a request without one is not really in the queue. Second, a Part D plan that misses its deadline is treated as having issued an adverse decision and must forward the case to the independent review entity (see 42 CFR 423.572). If you track the clock, you will know when that happens.
Medicare timelines are not universal
These numbers apply to Medicare Part D plans. Medicare Advantage, Medicaid managed care and commercial plans can differ, and state law may add rules. Confirm each payer’s current policy before you promise a patient a date.
Send a complete request the first time
A complete first submission is the single biggest lever you control. Each “need more information” round trip restarts your own follow-up cycle, and on an exception request the plan’s clock may not run at all until the supporting statement arrives.
Build one checklist per payer and per drug class, then stop reinventing it for each patient. The table below shows what staff should have in hand before anyone opens the payer portal.
| Item to confirm | Why it matters | Who usually owns it |
|---|---|---|
| Active coverage and the correct pharmacy-benefit plan | A request sent to the medical plan, or to an old plan, is a wasted day | Front desk or authorization coordinator |
| Exact drug, strength, quantity and days supply | Mismatches with the e-prescription cause rework | Prescriber and coordinator |
| Diagnosis code that supports the drug | Reviewers match the diagnosis to the plan’s criteria | Prescriber and coder |
| Prior drugs tried, dates, doses and outcomes | Step therapy criteria usually ask for this | Clinical staff |
| Relevant labs, notes or test results attached | Missing records are a common reason for a request to be pended | Clinical staff |
| Prescriber supporting statement (for exceptions) | The Part D clock starts when it is received | Prescriber |
Source: RCM Finder operations checklist; the Part D exception-statement rule is from 42 CFR 423.572
Eligibility errors upstream undo all of this. If the patient’s plan changed since the last visit, the request goes to the wrong place. Our guides on patient insurance verification and automating eligibility checks explain how to catch it at scheduling.
Use electronic prior authorization where the payer supports it
Electronic prior authorization (ePA) lets the prescriber start and answer a plan’s questions from inside the prescribing workflow, instead of by fax, phone or a separate portal. For Medicare Part D, the standard behind it is NCPDP SCRIPT, and CMS’s e-prescribing requirements page explains how the rules are set.
- CMS says Part D sponsors could use NCPDP SCRIPT version 2017071 for ePA from January 1, 2021, and had to use it from January 1, 2022.
- A June 2024 CMS rule replaces that version with NCPDP SCRIPT 2023011 for transmissions that include ePA, beginning January 1, 2028.
- The same rule requires the NCPDP Real-Time Prescription Benefit standard (version 13) for prescriber real-time benefit tools that Part D sponsors support, beginning January 1, 2027.
What this means for a practice manager: ask your EHR vendor whether ePA is turned on for your prescribers, and ask your top payers and pharmacy benefit managers which drugs they accept through ePA. These rules govern Part D plans. They do not tell you what a commercial plan or your specific EHR supports today.
The big federal prior authorization rule does not cover drugs
CMS’s 2024 interoperability and prior authorization final rule (CMS-0057-F) sets 72-hour and seven-day decision timeframes for covered payers, but CMS states that it does not apply to prior authorization decisions for drugs. Do not assume those deadlines protect a medication request. See the CMS fact sheet.
Ask for an expedited review the right way
Request an expedited review only when the patient’s situation is urgent, and make the prescriber’s reasoning explicit. A Part D plan has 24 hours to decide an expedited request once it is accepted as one, as the CMS flowchart shows. Each plan sets its own criteria for what qualifies as urgent, so a vague “please rush” is weaker than a clear clinical reason.
- Mark the request as urgent in the portal or ePA field, not only in a free-text note.
- Put the prescriber’s reason in one or two plain sentences at the top of the supporting statement.
- Phone the plan after submitting an urgent request, and note the reference number and the name of the person you spoke with.
- Ask the plan whether a temporary supply is possible, and ask the pharmacy what it can do while the decision is pending. Rules differ by plan.
Do not mark routine refills as urgent. It makes your genuinely urgent requests harder to prioritize.
Track every request and give it an owner
Every open authorization needs a named owner, a submitted date, a due date based on that payer’s clock and a next action. Without those four fields, requests sit pending until the patient calls the pharmacy and finds out nothing happened.
- Log the submission date, the channel (ePA, portal, fax) and the reference number.
- Set a follow-up date from the payer’s timeline, not from a generic rule.
- Review the open list at the start of each day, oldest first.
- Record the outcome and the reason for any denial or pend, so the next request for the same drug starts smarter.
- Tell the patient and the pharmacy when a decision arrives, in the same hour.
A spreadsheet can do this for a small volume. At higher volume, many practices move to a practice management system that tracks claims by stage with an owner on every item. Our billing portal follows this model for claims, and the same discipline applies to authorizations in any tool you choose.
“If nobody's name is next to the request, it is not being worked. Check this first in any authorization workflow.”
When the answer is no: appeal with a plan
Read the denial reason before doing anything else, then decide between a corrected resubmission, a peer-to-peer conversation or a formal appeal. Many denials are fixable errors or missing records, and the denial letter tells you which.
In Medicare Part D, the first appeal level is a redetermination. CMS lists 7 days for a standard redetermination and 72 hours for an expedited one, with a filing deadline of 65 days from the date of the notice. After that comes the independent review entity, which has the same 7-day standard and 72-hour expedited timeframes. These are Part D rules. Check your commercial and Medicaid plans’ appeal rights separately, because deadlines and steps differ.
Pattern review matters as much as the individual appeal. If the same payer denies the same drug for the same missing item, fix the checklist. Our posts on medical billing denial management and insurance denial tips show how to turn denial reasons into process fixes.
Who should own medication prior authorization?
Give authorizations to one person or a small team so they learn payer rules and drug criteria. Whether that is an employee, a shared role or an outsourced team depends on your volume, your drug mix and how much clinical staff time you are losing today.
| Option | Works best when | Watch out for |
|---|---|---|
| Clinical staff do it between patients | Very low volume | Highest interruption cost; follow-up slips |
| One trained in-house coordinator | Steady volume and stable staff | Single point of failure during leave or turnover |
| Remote virtual medical assistant | Volume swings, or no budget for a full-time hire | Needs clear scripts, access and a daily review |
| Outsourced prior authorization service | High volume across many payers or drug classes | Needs a written process, reporting and a Business Associate Agreement |
Any outside partner that handles patient information must sign a Business Associate Agreement before accessing it. See our HIPAA compliance checklist for medical practices for what to ask. If you want help from our side, we offer prior authorization services and a virtual medical assistant for the front desk. Our team works with the EHR you already use.
Drug-heavy specialties feel this first. Practices that prescribe infusions, biologics or injectables, such as those in rheumatology, often have the largest authorization queues, so the ownership and tracking steps above pay off there.
See where your authorizations are getting stuck
A free practice audit looks at your current process, your payer mix and your open requests, then shows where the delays come from. Pricing, if you want help, is quoted after the audit.
Our recommendations
- Write down each payer's turnaround. We keep one reference sheet with standard and urgent timelines per payer, and we update it when a payer changes.
- Build a checklist per drug class. We list the attachments that each payer asks for, so staff attach them before the first submission.
- Turn on ePA before adding people. We ask the EHR vendor and top payers about ePA first, because it removes fax and phone steps that no extra hire can make faster.
- Put a name and a due date on every request. We never let a pending authorization sit without an owner, a due date and a next action.
- Separate urgent from routine. We reserve expedited requests for urgent clinical need and write the reason in plain words.
- Review denials every month. We group denial reasons by payer and drug, and then change the checklist instead of repeating the same appeal.
Track every authorization by stage with an owner.
Our portal tracks claims by stage with an owner, a role-based permission model and an audit log. The same discipline of one owner and one due date per item applies to authorizations.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Faster medication approvals come from a complete first request, electronic submission where available, a payer-specific clock and a named owner for every open case. If your team is stretched, our prior authorization services and denial management services can take on the tracking and follow-up. You can also size the cost of delays with our revenue calculator, or start with a free practice audit.
Frequently asked questions
How long does prior authorization for medication take?
It depends on the plan. For Medicare Part D, CMS lists 72 hours for a standard coverage determination and 24 hours for an expedited one. Commercial and Medicaid plans set their own timelines, which can be longer or shorter. Ask each payer for its turnaround and track requests against that date.
How do you get a medication prior authorization approved faster?
Send a complete request the first time, use electronic prior authorization if the payer supports it, include the prescriber’s reasoning and attach records the plan’s criteria ask for. Then track the due date and follow up on that date, not when the patient calls.
What is the difference between a standard and an expedited request?
An expedited request is for urgent situations and has a shorter decision clock. In Medicare Part D that clock is 24 hours instead of 72. Each plan sets its own criteria for urgency, so the prescriber should state the clinical reason clearly.
Does the CMS prior authorization rule speed up drug approvals?
Not directly. CMS states that its 2024 interoperability and prior authorization final rule (CMS-0057-F) does not apply to prior authorization decisions for drugs. Medication requests follow Part D, Medicaid or commercial plan rules instead.
What should I do if a medication prior authorization is denied?
Read the denial reason first. Fix any missing information and resubmit, ask for a peer-to-peer conversation if the plan offers one, or file an appeal. In Part D, the first appeal is a redetermination, filed within 65 days of the notice. Other plans have their own deadlines.
Can a virtual assistant handle medication prior authorizations?
Yes, for the administrative work: gathering records, submitting requests, tracking due dates and following up. The prescriber still supplies clinical judgment and signs statements. Any vendor with access to patient data needs a Business Associate Agreement and role-based access.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Exhausted by prior authorization, many patients abandon care: AMA survey — American Medical Association (2024)
- Medicare Part D appeals and grievances flowchart — Centers for Medicare & Medicaid Services (2026)
- 42 CFR 423.572 Timeframe and notice requirements for expedited coverage determinations — eCFR via Cornell Legal Information Institute (2026)
- CMS Interoperability and Prior Authorization final rule (CMS-0057-F) fact sheet — Centers for Medicare & Medicaid Services (2024)
- E-Prescribing Standards and Requirements — Centers for Medicare & Medicaid Services (2024)
Disclaimer: This article is general education for practice managers, not legal, coding, clinical or compliance advice. Prior authorization rules vary by payer, plan type and state, and they change. Confirm current requirements with each payer and your compliance adviser.
