
Podiatry Specialty

Podiatry Billing Services, Front Desk and Growth in One Plan

Routine foot care rules, nail and callus coding, diabetic shoe paperwork and contractor-specific checks, plus patient marketing, remote front-desk staff and a claims portal for podiatry practices.
  • Works inside your current EHR
  • US practice time zone, every shift
  • Weekly KPI reporting, or on your schedule
Podiatry billing dashboard showing routine foot care claims, class findings on file, denials by reason and A/R days

Quick answer

Podiatry billing services manage the claims a foot and ankle practice creates: routine foot care, nail debridement, callus paring, ingrown nail surgery, diabetic foot exams and diabetic shoes. They check Medicare coverage rules, class findings, toe modifiers and visit frequency before each claim goes out. RCM Finder adds front-desk assistants, marketing and a claims portal.

Disclaimer: This page is educational and is not legal, coding or compliance advice. Medicare manuals, contractor policies, fee schedule rules and plan policies change often and vary by contractor, state and plan. Verify every code, limit and rule against current CMS documents, your Medicare contractor’s guidance, your payer contracts and the current CPT and HCPCS code sets before billing.

Why podiatry billing is different

Podiatry billing is different because Medicare excludes most routine foot care and pays for it only when the chart proves a covered reason. One visit can mix covered care, excluded care, a procedure and an office visit.

Federal auditors have noticed. In a December 2025 report, the HHS Office of Inspector General (OIG) found that 49 of 100 sampled podiatrist claims for routine foot care related to a systemic condition, from 2019 and 2020, did not comply with Medicare requirements, about $4.4 million of $18.2 million paid.

A second report on 2019 claims, summarized in its highlights, found 44 of 100 sampled modifier 25 office visits noncompliant, about $39.6 million of $222.5 million paid. Errors were insufficient documentation, incorrect coding, and a visit that was not significant and separately identifiable.

The American Podiatric Medical Association replied on December 5, 2025 that modifier 25 is often clinically justified and that 2019 data may not reflect current practice. Either way, your record must show why the claim was right.
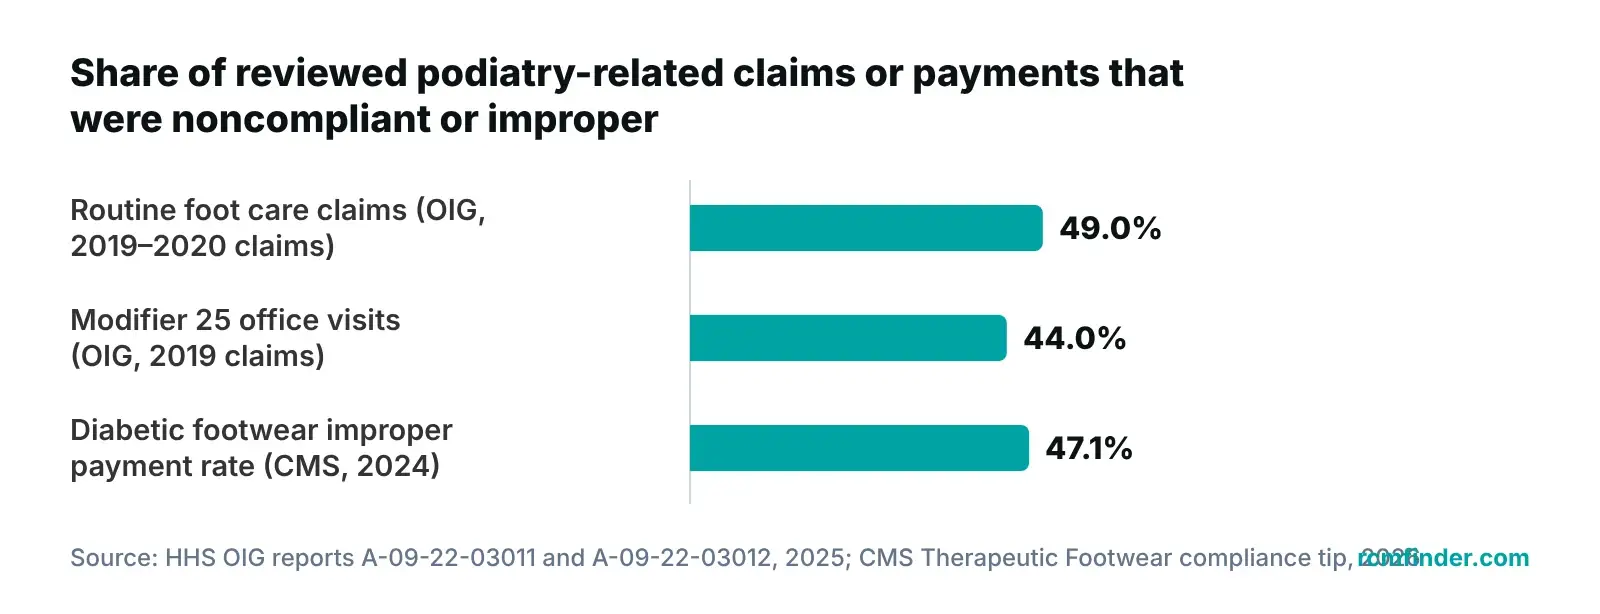
Bar chart of OIG and CMS error rates: routine foot care claims, modifier 25 visits and therapeutic footwear payments
Three different measures: OIG sampled claims from 2019–2020; CMS measured footwear payments in 2024.

What changed for 2026, and what is proposed for 2027

CMS’s CY 2026 fee schedule final rule fact sheet (October 31, 2025) set the conversion factor at $33.40 for clinicians who are not qualifying APM participants, up from $32.35, and applied a -2.5% efficiency adjustment to non-time-based services. E/M visits are exempt.

The CY 2027 proposed rule fact sheet (July 14, 2026) projects $32.84 for the same group as the one-year 2.50% increase expires. Check the final rule before budgeting. For ulcer care, see our wound care coding guide.

The four pillars, built for a podiatry practice

A podiatry practice needs patients and referrers who find you, a front desk that gathers the right facts, billing that knows the exclusion rules, and software that shows every claim. We run all four on one set of payer rules.

Pillar 1 · Healthcare Marketing

Healthcare Marketing for podiatry practices

Our healthcare digital marketing reaches people with heel pain, ingrown toenails and diabetic foot concerns through local SEO, Google Ads and reputation work, plus the doctors and facilities that refer high-risk feet.

  • Pages for heel pain, ingrown nails and diabetic foot checks
  • A referral path for primary care and nursing facilities
  • KPI: new patients and referrals by source
Explore Healthcare Marketing
Pillar 2 · Virtual Medical Assistants

Virtual Medical Assistants for podiatry front desks

Our virtual medical assistants for podiatry practices work on your practice’s time zone. They verify coverage, record each patient’s managing physician, log the last foot care date and chase shoe paperwork.

  • Coverage and plan type checked before each visit
  • Managing MD or DO and last-seen date recorded
  • Last debridement date checked against the 60-day limit
  • KPI: visits cleared before the date of service
Explore Virtual Medical Assistants
Pillar 3 · End-to-End RCM

End-to-End RCM for podiatry claims

Our end-to-end podiatry revenue cycle management covers coding support, claim scrubbing, denial management and A/R follow-up, with extra checks for class findings, toe modifiers, nail and lesion counts and same-day visits.

  • Q modifiers matched to documented class findings
  • Toe modifiers checked on nail procedures
  • Modifier 25 visits reviewed against the note
  • KPI: denials by reason and A/R days
Explore End-to-End RCM
Pillar 4 · Practice Management System

Practice Management System for podiatry billing

Our practice management system tracks every claim by stage, applies specialty-aware billing logic per claim, checks data completeness before submission and flags underpayments.

  • Claims tracked by stage, per claim
  • Workflow rules that hold claims missing a field you choose
  • Client portal for practices and billing companies
  • Early access: appointment booking with a calendar view
Explore Practice Management System

Find where your foot care claims leak

We review recent foot care, nail, callus and shoe claims and denials, then show what to fix first.

Get a Free Practice Audit

Routine foot care: the Medicare exclusion and its exceptions

Medicare treats cutting corns and calluses, trimming or debriding nails, and hygienic foot care as routine and does not cover them unless an exception applies. The Novitas routine foot care LCD (L35138) points to Chapter 15, Section 290 of the Medicare Benefit Policy Manual for the exceptions.

Systemic conditions and active care

Routine care may be covered when a metabolic, neurologic or peripheral vascular disease makes nonprofessional trimming hazardous, per Noridian. Novitas adds conditions such as chronic venous insufficiency, lymphedema and Raynaud’s disease.

For asterisk conditions, Novitas requires active care by an MD, DO or non-physician practitioner for the underlying disease in the six months before the service. Noridian names an MD or DO only. Novitas article A52996 puts the last-visit date in line 19 of the CMS-1500.

Class findings and the Q modifiers

Noridian’s routine foot care article defines the class findings that Q7, Q8 and Q9 report:

  • Class A: nontraumatic amputation of the foot or an integral skeletal portion. One finding is Q7.
  • Class B: absent posterior tibial pulse, absent dorsalis pedis pulse, or advanced trophic changes (three required). Two findings are Q8.
  • Class C: claudication, temperature changes, edema, paresthesias and burning. One Class B plus two Class C is Q9.

Contractors differ on Q modifiers. Novitas requires one on routine foot care claims that meet an exclusion. Noridian’s article A57954 ties them to its vascular diagnosis group, with none for neuropathy-only codes. Our routine foot care guide and podiatry modifiers post cover the basics.
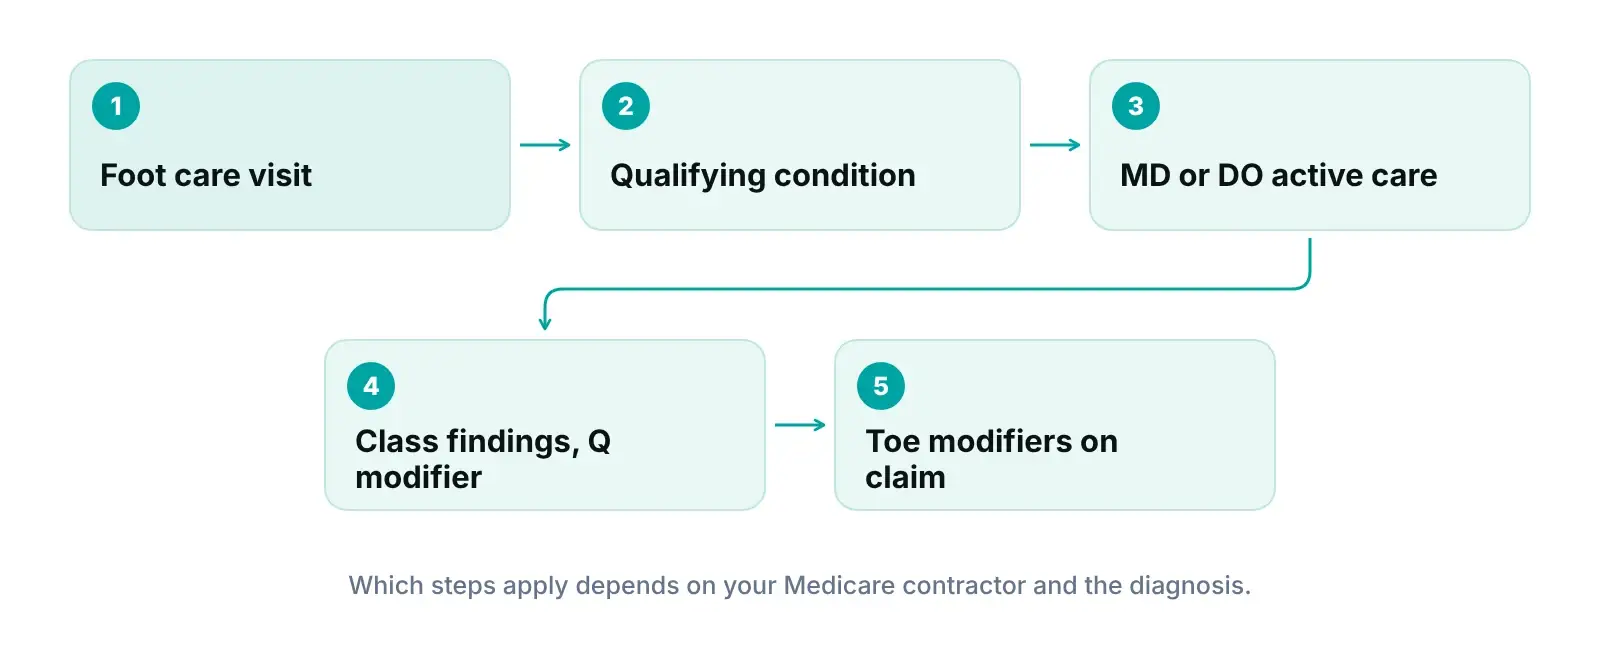
Diagram of routine foot care claim steps from qualifying condition and active care to class findings and toe modifiers
The checks a routine foot care claim passes before it is submitted to Medicare.

Painful mycotic nails without a systemic condition

Noridian covers debridement of fungal nails when records show clinical evidence of mycosis plus marked limitation of walking, pain or infection (ambulatory patients), or pain or infection (nonambulatory). Novitas’ LCD L35013 treats debridement as an adjunct to antifungal treatment and expects options to be reviewed at the first visit.

Frequency limits to know

Novitas allows routine foot care and nail debridement no more often than every 60 days, with no more than six debridement sessions per 12 months absent medical review. Novitas also limits a repeat avulsion of the same toe to every 8 months without a KX-supported exception. Separately, the national coverage determination for diabetic foot evaluations allows one every six months.

Podiatry codes, modifiers and denial triggers

Each podiatry service has its own frequency, count or paperwork rule. Codes are described in our own words (the AMA owns CPT descriptors); check the current code set and your contractor.

Podiatry service families: code examples, billing rules and typical denial triggers
ServiceCode examples (our wording)Billing rule to knowTypical denial trigger
Nail debridement11720 (1–5 nails); 11721 (6 or more)Once per 60 days; six sessions per 12 months; B35.1 on the claim with another listed diagnosis (Novitas)Chart says only “nails debrided”
Nail trimming11719 (normal nails); G0127 (dystrophic nails)Trimming is not debridementTrim billed as debridement
Corn and callus paring11055 (one lesion); 11056 (2–4); 11057 (more than 4)One code per date of service, by total lesions; not 11305–11308 for feet (Novitas)Lesion locations not recorded
Ingrown nail surgery11730 (avulsion); 11732 (added avulsion); 11750 (nail and matrix excision); 11765 (toe nail fold excision)Digit modifier required; same toe avulsion within 8 months needs KX; repeat excision needs KXNo digit modifier; repeat procedure without KX support
Same-day office visitE/M with modifier 25Significant and separately identifiable; E/M for routine foot conditions not payable except the diagnosing visit (Novitas)Note repeats the procedure note
Toe and foot locationLT, RT; TA and T1–T4 (left toes); T5–T9 (right toes)Required on foot care claims (Novitas); use instead of 59 for different digitsDigit modifier missing or on the wrong side
Diabetic foot evaluationExam and treatment for loss of protective sensation (NCD 70.2.1)Every six months at most; monofilament testing documented; no other foot specialist visit betweenSensory test not recorded
Diabetic shoes and insertsA5500 (depth shoe); A5501 (custom-molded shoe)Billed to the DME MAC with KX; certification and visits on schedule; annual limitsNo KX; certification signed late

Sources: Novitas LCDs L35138, L35013, L34887, DME MAC LCD L33369 and articles A52996, A56640, A52998 (2019–2026); Noridian JF modifier 59 page (2025); CMS NCD 70.2.1; CMS Therapeutic Footwear compliance tip (2026); HHS OIG A-09-22-03012 (2025); AAPC code pages for plain-language meanings. Rules vary by contractor and payer.

Documenting nail debridement and callus paring

Under L35138, the record needs a detailed description of the feet, not a list of findings. It must identify each nail and lesion location, and describe debridement beyond “nails debrided.” Nursing home residents need a current, dated, signed facility order; standing orders do not count.

The Novitas mycotic nail policy (LCD L35013) asks for each nail’s size, thickness, color and local pathology, with six nails documented for 11721. Noridian’s podiatry documentation page adds signature attestations for illegible signatures.

Modifiers 25, 59 and the toe series

Noridian describes modifier 25 as a significant, separately identifiable E/M with its own history, exam and decision-making. Modifier 59 is a last resort and does not replace the T1–T9 anatomic modifiers, per Noridian. Ingrown nail repeats follow article A52998. Our modifiers 25 vs 59 guide has examples.

Your Medicare contractor sets the details

The Novitas LCDs above apply to Jurisdictions H and L, including Texas, Pennsylvania, New Jersey and Maryland. Other contractors differ. In 2024, APMA reported that Palmetto stopped accepting non-physician practitioners as the qualifying active-care provider. Pull your own contractor’s policies before setting claim edits.

Diabetic foot care, therapeutic shoes and DME

Diabetic foot care has two rule sets: a physician service for patients who have lost protective sensation, and a shoe benefit billed to a DME contractor.

The diabetic foot evaluation

National Coverage Determination 70.2.1 covers a foot evaluation every six months at most for diabetic sensory neuropathy with loss of protective sensation. The diagnosis rests on 5.07 monofilament testing at five plantar sites per foot; absent sensation at two or more sites on either foot supports it. Coverage does not apply if the patient saw a foot care specialist for another reason in the interim.

CMS defined G0245 and G0246 (initial and follow-up evaluations) and G0247 (routine foot care for these patients) in a 2005 transmittal written for facility billing. Ask your contractor how professional claims are edited.

Therapeutic shoes and inserts

LCD L33369, used by the DME MACs, covers depth shoes and custom-molded shoes (A5501, for a deformity a depth shoe cannot fit) for patients with diabetes. Depth shoes are reported with A5500. Noridian’s guide says the certifying physician must be an MD or DO who manages the diabetes. A podiatrist can prescribe or supply.

  • Qualifying condition: amputation, past ulcer, pre-ulcerative callus, neuropathy with callus, deformity or poor circulation.
  • Visits: a physician visit on diabetes within six months before delivery, plus a supplier evaluation and fit check.
  • Statement: signed on or after the visit and within three months before delivery.
  • Yearly limit: one pair of custom-molded shoes plus two inserts, or one pair of depth shoes plus three inserts.

The CMS therapeutic footwear compliance tip (March 2026) reports a 47.1% improper payment rate for 2024, with insufficient documentation behind 85.5% of improper payments. Other orthopedic shoes and supportive foot devices are generally excluded, per Noridian’s exclusions page. See our DME modifiers guide.

Pre-visit checks, ABNs and prior authorization

Most podiatry denials are visible before the patient arrives, such as a frequency limit, a missing physician date or an approval never requested.

ABNs and the non-coverage modifiers

CMS’s MLN006266 booklet (May 2025) says providers must give an Advance Beneficiary Notice (form CMS-R-131) when they expect Medicare to deny a service as not reasonable and necessary. GA reports a required notice, GZ reports an expected denial with no notice, and GY reports a service that is never covered. Notices are allowed for services with LCD frequency limits. See our ABN billing guide.

Plan approvals

In KFF’s analysis of 2024 data (January 2026), Medicare Advantage insurers denied 7.7% of 52.8 million prior authorization determinations in full or in part. Only 11.5% of denials were appealed; 80.7% of appeals were partly or fully overturned. Since January 2026, CMS-0057-F requires MA, Medicaid and CHIP plans to decide standard requests within seven calendar days. See our prior authorization guide.

Pre-visit checklist: rules our VMAs check before a podiatry visit
RuleSourceWhat the VMA checks before the visit
Asterisk diagnoses need MD or DO active care in the prior six monthsNovitas L35138; Noridian (2025)Managing physician’s name and last-seen date recorded
Routine foot care no more often than every 60 daysNovitas L35138 and L35013Last visit date checked before booking; ABN flagged if too soon
Class findings documented when a Q modifier is neededNoridian A57954; Novitas A52996Clinician alerted when findings are missing
Loss of protective sensation: one evaluation per six monthsNCD 70.2.1Prior foot care visits in the last six months checked
Diabetic shoes: physician visit within six months; certification signed within three months of deliveryNoridian JF (2025)Visit, signature and delivery dates tracked
Nursing home residents: dated, signed facility orderNovitas L35138Order obtained before the visit
MA, Medicaid and CHIP plans decide in 7 calendar days (standard) or 72 hours (expedited)CMS-0057-F (in effect January 1, 2026)Request and due dates logged

Sources: Novitas LCDs L35138 and L35013 and article A52996; Noridian JF podiatry and shoe pages (2025); Noridian article A57954 (2025); CMS NCD 70.2.1; CMS-0057-F fact sheet (2024). Always check your own contractor and plan.

Eligibility is a separate step; our insurance verification guide covers it.

See what denied foot care claims cost you

Enter your claim volume and denial rate to estimate what your practice is losing.

Open the Revenue Calculator

In-house team, billing-only vendor or four-pillar partner?

Stay in-house if your staff already track visit dates, class findings and shoe paperwork well. Use a billing-only vendor if claims are your only gap. Choose a combined partner when problems start at the front desk.

Decision table: which model fits a podiatry practice?
JobIn-house teamBilling-only vendorFour-pillar partner (RCM Finder)
Coverage rule checks (active care, 60-day limit)Front desk, between callsOften left to the practiceVMA checks before every visit
Documentation of nails, lesions and class findingsClinician templates, quality variesCoded from the note as writtenClaims held when a field you choose is empty
Diabetic shoe paperworkTracked by hand, if at allUsually not includedDates tracked; orders chased from the certifying physician
Referral and patient growthA separate agency, or nobodyNot includedMarketing tied to booked first visits
Cost structureSalaries, benefits, turnoverVaries; ask how fees are setQuoted after a free practice audit

How it works

We start with a free audit and change nothing until you see the findings. We build our billing pipeline around how claims actually move through a practice: registration, charge entry, submission, payment and follow-up. For podiatry, we add the checks on this page.

  1. 1

    Free practice audit

    We review recent foot care, nail, callus and shoe claims, denials and eligibility logs.

  2. 2

    Business Associate Agreement and access

    We put a Business Associate Agreement in place before accessing patient data. Then we work inside your existing EHR (for example PrognoCIS, eClinicalWorks or athenahealth).

  3. 3

    Contractor rule map

    Your Medicare contractor’s LCDs and articles and your main plans’ policies become a pre-visit checklist and portal rules.

  4. 4

    Front desk and billing go live

    VMAs verify coverage and track dates. Claims are scrubbed, submitted and worked through denials and A/R.

  5. 5

    Weekly KPI review

    We review denials by reason, A/R days, visits cleared before the date of service and shoe orders pending.

Talk to us about your podiatry practice

Tell us your Medicare contractor and your hardest denial. We will say honestly whether we fit.

Call +1 (302) 556-2288

Compliance: what to ask any podiatry billing company

Any billing vendor that handles your patients’ data is a HIPAA business associate. Get a Business Associate Agreement before access, and ask how access is logged.

HHS guidance lists billing and claims processing as business associate work; for electronic data, the agreement must require the vendor and its subcontractors to follow the Security Rule. The minimum necessary standard limits each use to what the task needs, and the technical safeguards cover access control, audit controls, integrity, authentication and transmission security.

  1. Will you and your subcontractors sign a Business Associate Agreement before any access?
  2. How do you limit access, and can we see the audit log?
  3. What coding credential and podiatry experience do your coders have?
  4. How do you handle class findings, toe modifiers and the 60-day limit?
  5. How do you track diabetic shoe certifications and delivery dates?
  6. Can we export our data if we leave?

We use role-based access, audit logging and encrypted (HTTPS) connections, and we put a Business Associate Agreement in place before accessing patient data. For your own side, use our HIPAA compliance checklist for medical practices.

Marketing carries risk too. HHS guidance on online tracking says tools on appointment pages may collect protected health information, tracking vendors that handle it generally need a Business Associate Agreement, and cookie banners are not authorizations. A 2024 court order vacated part of it; we keep tracking off forms unless the vendor signs one.

Who this is for, and who it is not for

We would rather tell you now than after you sign. Here is where we fit and where we do not.

A good fit if you are

  • Podiatry practices billing Medicare for routine foot care, nail debridement and diabetic foot care
  • Practices that supply diabetic shoes and inserts
  • Foot and ankle groups with nursing facility patients
  • Billing companies serving podiatry clients that want a shared claims portal

Probably not a fit if you are

  • Hospital- or system-employed podiatrists whose employer controls billing
  • Practices that want claims billed without changing any front-desk step
  • Practices looking for promised collection rates; we report measured KPIs
  • Groups needing a credentialing module or in-portal real-time eligibility today (coming next)

Expert recommendations from our operations team

What we would do first if we were running your practice's revenue cycle tomorrow.

  1. 01

    Count and name before you code

    Nail and callus codes are paid by count. We check the note names each nail and lesion before a code is chosen.

  2. 02

    Record the managing physician

    Asterisk diagnoses depend on active MD or DO care. We capture the physician’s name and last-seen date when scheduling.

  3. 03

    Keep a 60-day clock

    Routine foot care and debridement have a 60-day limit. We check the last date before booking and flag an ABN if needed.

  4. 04

    Match Q modifiers to findings

    A Q modifier should trace to a documented class finding. We return the chart to the clinician when it does not.

  5. 05

    Defend modifier 25 in the note

    A same-day visit needs its own history, exam and decision-making. We review these claims against the note.

  6. 06

    Run the shoe program as a project

    Visits, signatures and delivery dates sit with different people. We track each date and chase the certifying physician.

Frequently asked questions

What do podiatry billing services include?

They cover coding support, claim scrubbing, submission, denial management and A/R follow-up for routine foot care, nail debridement, callus paring, ingrown nail procedures, diabetic foot care and diabetic shoes. A good partner also checks your Medicare contractor’s rules, class findings and visit frequency before each claim. We add front-desk assistants, referral-focused marketing and a claims portal, so one team owns the process from first call to payment.

Does Medicare pay for routine foot care?

Generally no. Cutting corns and calluses, trimming or debriding nails and hygienic care are treated as routine and excluded. Exceptions apply when a systemic condition such as diabetes or peripheral vascular disease makes nonprofessional care hazardous, or when mycotic nails meet pain or walking tests. Rules differ by contractor, and your record has to show the reason for each visit.

What do Q7, Q8 and Q9 mean?

They report class findings for routine foot care. Q7 is one Class A finding, such as a nontraumatic amputation of the foot or part of it. Q8 is two Class B findings, such as an absent pedal pulse. Q9 is one Class B and two Class C findings, such as claudication, edema or burning. Contractors differ on when a Q modifier is required, so check yours.

How often can we debride nails for a Medicare patient?

Under Novitas’ mycotic nail policy, 11720 and 11721 are covered no more often than every 60 days, and no more than six sessions in 12 months without medical review. Other contractors may differ. If a visit may fall inside a limit, CMS allows an ABN that states the frequency limit as the reason for the expected denial.

Who can certify a patient for diabetic shoes?

Under the DME MAC policy, the certifying physician must be an MD or DO who manages the patient’s diabetes. A podiatrist can be the prescribing practitioner who does the foot exam and writes orders, and can be the supplier. The certification statement must be backed by the medical record, with a physician visit on diabetes within six months before delivery.

When should we use modifier 25 on a foot care visit?

Use it when the visit is a significant, separately identifiable service with its own history, exam and decision-making, beyond the usual work of the procedure. Medicare does not pay E/M services for routine foot conditions except the first visit that diagnoses the condition, per Novitas. OIG found 44 of 100 sampled modifier 25 visits noncompliant, so document the separate work.

No cost, no commitment

Get your free practice audit

Tell us about your practice. A member of our operations team replies within one business day.

  • A review of your recent claims, denials and A/R aging
  • Where your front desk and prior authorizations slow payment
  • A prioritized fix list you keep, whether or not you hire us

Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.

Tell us about your practice

RCMFinder Master Intake Form
AA

About the author: Awais Afzal

Healthcare Operations & Data Analyst, RCM Finder

Awais has spent more than 16 years in healthcare digital marketing and clinical operations management. He builds data-driven revenue cycle blueprints for high-ticket medical practices and leads product development of the RCM Finder portal. More about our team.

How we write: every figure, code and rule on this page was checked against the primary source listed below and independently fact-checked before publishing. We re-review this page every six months. Last reviewed October 12, 2026; next review April 12, 2027.

Sources

  1. Routine Foot Care (LCD L35138) — Novitas Solutions, via CMS Medicare Coverage Database (2019 revision (R7, effective 10/17/2019))
  2. Billing and Coding: Routine Foot Care (A52996) — Novitas Solutions, via CMS Medicare Coverage Database (2025 (revision effective 10/01/2025; marked Draft Article))
  3. Debridement of Mycotic Nails (LCD L35013) — Novitas Solutions, via CMS Medicare Coverage Database (2019 revision (effective 09/12/2019))
  4. Billing and Coding: Debridement of Mycotic Nails (A56640) — Novitas Solutions, via CMS Medicare Coverage Database (2019 (revision effective 09/12/2019))
  5. Surgical Treatment of Nails (LCD L34887) — Novitas Solutions, via CMS Medicare Coverage Database (2025 (version 03/14/2025; effective 01/30/2022))
  6. Billing and Coding: Surgical Treatment of Nails (A52998) — Novitas Solutions, via CMS Medicare Coverage Database (2026 (R11 effective 01/01/2026; marked Draft Article))
  7. Billing and Coding: Routine Foot Care (A57954) — Noridian Healthcare Solutions, via CMS Medicare Coverage Database (2025 (revision effective 11/06/2025; marked Draft Article))
  8. Billing and Coding: Routine Foot Care (A57957) — Noridian Healthcare Solutions, via CMS Medicare Coverage Database (2025 (status Retired; revision ending 11/06/2025))
  9. Conditions that Might Justify Coverage (JF Part B podiatry) — Noridian Healthcare Solutions (2025 (updated July 25, 2025))
  10. Exclusions from Coverage (JF Part B podiatry) — Noridian Healthcare Solutions (2025 (updated July 25, 2025))
  11. Podiatry Services Documentation Requirements — Noridian Healthcare Solutions (2025 (updated March 21, 2025))
  12. Modifier 25 — Noridian Healthcare Solutions (2025 (updated May 9, 2025))
  13. Modifier 59 — Noridian Healthcare Solutions (2025 (updated May 9, 2025))
  14. Therapeutic Shoes for Persons with Diabetes: Decision-Making and Ordering — Noridian Healthcare Solutions (2025 (updated July 25, 2025))
  15. Therapeutic Shoes for Persons with Diabetes (LCD L33369) — CGS Administrators and Noridian (DME MACs), via CMS Medicare Coverage Database (2020 (revision effective 01/01/2020))
  16. Therapeutic Footwear compliance tip — CMS Medicare Learning Network (2026 (page modified 03/20/2026; 2024 improper payment data))
  17. Services Provided for the Diagnosis and Treatment of Diabetic Sensory Neuropathy with Loss of Protective Sensation (NCD 70.2.1) — CMS, via Medicare Coverage Database (2002 (effective 07/01/2002))
  18. Transmittal 498, Change Request 3580 (Medicare Claims Processing Manual, Chapter 32, Section 80) — CMS, hosted by HHS (2005 (March 11, 2005))
  19. Medicare Advance Written Notices of Non-coverage (MLN006266) — CMS Medicare Learning Network (2025 (May 2025))
  20. Podiatrists' Claims for Routine Foot Care Services Did Not Comply With Medicare Requirements (A-09-22-03011) — HHS Office of Inspector General (2025 (issued 12/04/2025))
  21. Podiatrists' Claims for Evaluation and Management Services Did Not Comply With Medicare Requirements (A-09-22-03012) — HHS Office of Inspector General (2025 (issued 12/03/2025))
  22. A-09-22-03012 report highlights — HHS Office of Inspector General (2025 (December 2025))
  23. APMA statement regarding OIG report on podiatrists’ evaluation and management claims — American Podiatric Medical Association (2025 (December 5, 2025))
  24. Update: Change to Palmetto Routine Foot Care Policy — American Podiatric Medical Association (2024 (May 13, 2024))
  25. Calendar Year (CY) 2026 Medicare Physician Fee Schedule Final Rule (CMS-1832-F) fact sheet — CMS (2025 (October 31, 2025))
  26. Calendar Year (CY) 2027 Medicare Physician Fee Schedule Proposed Rule fact sheet — CMS (2026 (July 14, 2026))
  27. Medicare Advantage Insurers Made Nearly 53 Million Prior Authorization Determinations in 2024 — KFF (2026 (published January 28, 2026))
  28. CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) fact sheet — CMS (2024 (January 17, 2024))
  29. Business Associates — HHS Office for Civil Rights (undated (accessed 2026-10-11))
  30. Minimum Necessary Requirement — HHS Office for Civil Rights (undated (accessed 2026-10-11))
  31. 45 CFR 164.312 Technical safeguards — eCFR (current (up to date as of 10/07/2026))
  32. Use of Online Tracking Technologies by HIPAA Covered Entities and Business Associates — HHS Office for Civil Rights (2024 (content last reviewed June 26, 2024))
  33. CPT 11055 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-11)
  34. CPT 11056 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-11)
  35. CPT 11057 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-11)
  36. CPT 11719 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-11)
  37. CPT 11720 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-11)
  38. CPT 11721 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-11)
  39. CPT 11730 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-11)
  40. HCPCS G0127 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-11)
  41. HCPCS A5500 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-11)