
Hematology Specialty

Hematology Billing Services, Front Desk and Growth in One Plan

Drug and infusion claims, prior authorization for IV iron, ESAs, IVIG and clotting factor, patient marketing and a claims portal for benign hematology practices, built on CMS rules and your payers' own policies.
  • Works inside your current EHR
  • US practice time zone, every shift
  • Weekly KPI reporting, or on your schedule
Hematology billing dashboard showing drug units billed, infusion authorizations, JW/JZ lines, A/R days and referrals

Quick answer

Hematology billing services manage the claims a benign hematology practice creates: IV iron and other drug units, infusion and injection codes, JW and JZ modifiers, lab values on ESA claims, clotting factor billing, prior authorization and denial appeals. RCM Finder pairs that billing with front-desk assistants, patient marketing and a claims portal, starting with a free audit.

Disclaimer: This page is educational and is not legal, coding or compliance advice. Medicare manuals, NCDs, NCCI edits and commercial payer drug policies change often and vary by contractor and plan. Verify every code, unit, modifier and rule against your Medicare contractor's current documents, your payer contracts and the current CPT and HCPCS code sets before billing.

Why hematology billing is different

In hematology, much of a claim's value sits on the drug line, not the visit. One iron infusion can carry a drug code billed in units, an administration code and a JZ or JW modifier, each with its own rule.

Medicare pays Part B drugs that are not paid on a cost or prospective basis at 106 percent of the average sales price, per CMS's claims processing manual, chapter 17. A units error on a costly drug is not a rounding problem. Under 42 CFR 447.520, states must also require National Drug Codes (NDCs) on Medicaid claims for physician-administered drugs.

This page covers non-malignant hematology: anemias, immune thrombocytopenia (ITP), bleeding and clotting disorders, and iron overload. For cancer care, see our oncology billing services page and oncology CPT codes guide; for anemia of kidney disease, see nephrology billing services.

What changed for hematology billing in 2026

Since January 1, 2026, the CMS-0057-F final rule has required Medicare Advantage, Medicaid and CHIP plans to decide expedited prior authorization requests within 72 hours and standard requests within seven calendar days. The catch for hematology: CMS says the rule does not apply to prior authorization decisions for drugs. Medicare Advantage plans must already decide Part B drug requests within 72 hours, or 24 hours when expedited, with no extensions (42 CFR 422.568 and 422.572). Commercial plan timelines for IV iron, ESAs, immune globulin and clotting factor vary.

CMS raised the clotting factor furnishing fee to $0.265 per unit for 2026 (Transmittal 13379) and set $0.270 for 2027 (Transmittal 13937, August 27, 2026). Plan policies move too: UnitedHealthcare's current commercial ESA, IV iron, immune globulin and clotting factor policies took effect between April and October 2026.
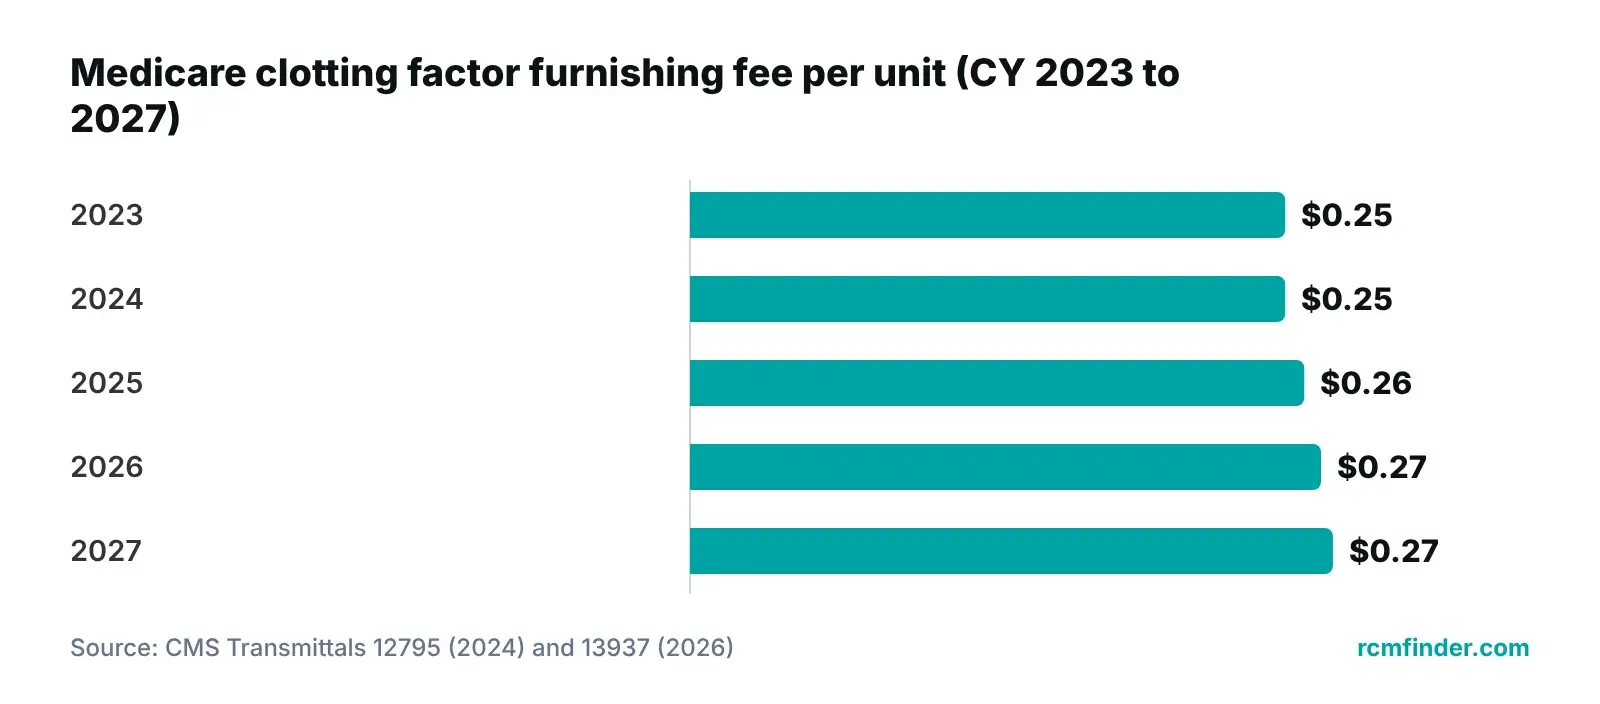
Bar chart of the Medicare clotting factor furnishing fee per unit for hemophilia billing, calendar years 2023 to 2027
The per-unit fee Medicare adds for furnishing clotting factor, from CMS's annual update transmittals.

The four pillars, built for a hematology practice

A hematology practice needs referrals, drugs approved before the chair is booked, claims billed in the right units and software that shows every claim.

Revenue leaks at the handoffs: an infusion booked before approval, an ESA dose with no recent hemoglobin on file, units billed on the wrong unit size. We run all four pillars against one set of payer rules.

Pillar 1 · Healthcare Marketing

Healthcare Marketing for hematology practices

Our healthcare digital marketing builds demand from patients searching for help with anemia, bleeding or clotting problems and from the clinicians who refer to you, through local SEO, Google Ads and reputation work.

  • Location pages and a Google Business Profile per office
  • Referral pages that list which recent labs to send
  • Tracking kept off appointment forms without a BAA
  • KPI: new referrals and booked visits by source
Explore Healthcare Marketing
Pillar 2 · Virtual Medical Assistants

Virtual Medical Assistants for hematology front desks

Our virtual medical assistants for hematology work on your practice's time zone. They check eligibility and which benefit covers a drug, start prior authorizations for IV iron, ESAs, immune globulin and factor, and gather the labs each plan asks for.

  • Drug approvals tracked to a decision
  • Latest hemoglobin, iron studies and platelet counts on file
  • Reauthorization dates kept on a calendar
  • KPI: infusions cleared before the chair date
Explore Virtual Medical Assistants
Pillar 3 · End-to-End RCM

End-to-End RCM for hematology claims

Our end-to-end hematology revenue cycle management covers coding support, claim scrubbing, denial management and A/R follow-up, with extra checks on drug units, JW or JZ, Medicaid NDCs, ESA lab values and NCCI bundling.

  • Units checked against each code's unit size
  • JW, JZ and NDC checked before submission
  • Appeals built from orders, labs and administration records
  • KPI: denials by reason and A/R days
Explore End-to-End RCM
Pillar 4 · Practice Management System

Practice Management System for hematology billing

Our practice management system tracks every claim by stage. It applies specialty-aware billing logic to each claim, checks that data is complete before submission and flags payments below the expected amount.

  • Claims tracked by stage, per claim
  • Underpayment flags against expected amounts
  • Workflow rules that hold a claim missing a lab value or modifier
  • Early access: appointment booking with a calendar view
Explore Practice Management System

Find where your infusion claims leak

We review recent drug and infusion claims, denials and authorization logs, then show where units, modifiers or missing approvals cost you.

Get a Free Practice Audit

Hematology service families: codes, units and denial triggers

Each service family has its own unit, modifier or bundling rule, and the table shows where claims often break. Codes are described in our own words (the AMA owns CPT descriptors); check current code sets and your contractor's guidance before billing.

Hematology service families: code examples, billing nuance and denial triggers
Service familyCode examples (our wording)Billing nuanceTypical denial trigger
IV iron infusionJ1439 ferric carboxymaltose (1 mg); J1756 iron sucrose (1 mg); J1437 ferric derisomaltose (10 mg); Q0138 ferumoxytol, non-ESRD (1 mg)Units equal the dose divided by the code's unit; JZ, or a separate JW line for single-dose wasteUnits copied from another product; JW or JZ missing; non-preferred product without approval
ESAs for anemiaJ0885 epoetin alfa, non-ESRD (1,000 units); J0881 darbepoetin alfa, non-ESRD (1 mcg)Latest hemoglobin or hematocrit (both at Noridian JE) plus EA, EB or EC on every non-ESRD lineLab value or modifier missing; EA with hemoglobin of 10.0 g/dL or more; EC with iron, folate or B-12 deficiency
Drug administration96365 (IV infusion, first hour); 96366 (each added hour); 96374 (IV push); 96372 (injection under the skin or into muscle)One initial code per encounter unless separate IV sites; IV start, port flush and 99211 includedTwo initial codes on one date; 99211 billed with the infusion; physician billing it in a hospital outpatient setting
Therapeutic phlebotomy99195Venipuncture, IV access and drug administration are includedBilled with autologous blood collection, plasmapheresis or exchange transfusion
Bone marrow aspiration and biopsy38220 (aspiration); 38221 (biopsy); 38222 (both)38222 for both on the same iliac bone; 38220 with 38221 only on different bones or at separate encountersBoth single codes for one bone; 38220 billed with bone biopsy code 20220
Clotting factorJ7192 (recombinant factor VIII, not otherwise specified, per IU); factor codes J7177 to J7214Billed per IU; Medicare's furnishing fee ($0.265 per unit in 2026) is built into the payment limitPlan criteria unmet, such as no inhibitor assay on file for FEIBA or NovoSeven
Anticoagulation management93793 (warfarin INR review and dosing); 93792 (home INR monitor training)Medicare home INR: mechanical valve, chronic AF or VTE; 3+ months on warfarin; at most weeklyHome testing started too early or done more than weekly; no face-to-face training on record

Sources: CMS Medicare Claims Processing Manual ch. 17 §40 and ch. 12 §30.5; CMS Transmittals 1412 and 1413 (2008) and 13379 (2025); Noridian JE Part B (2026); NCD 190.11; Medicare NCCI Policy Manual 2026, chapters V and XI; UnitedHealthcare policy 2026D0047AN (2026); AAPC code summaries. Rules vary by MAC and payer.
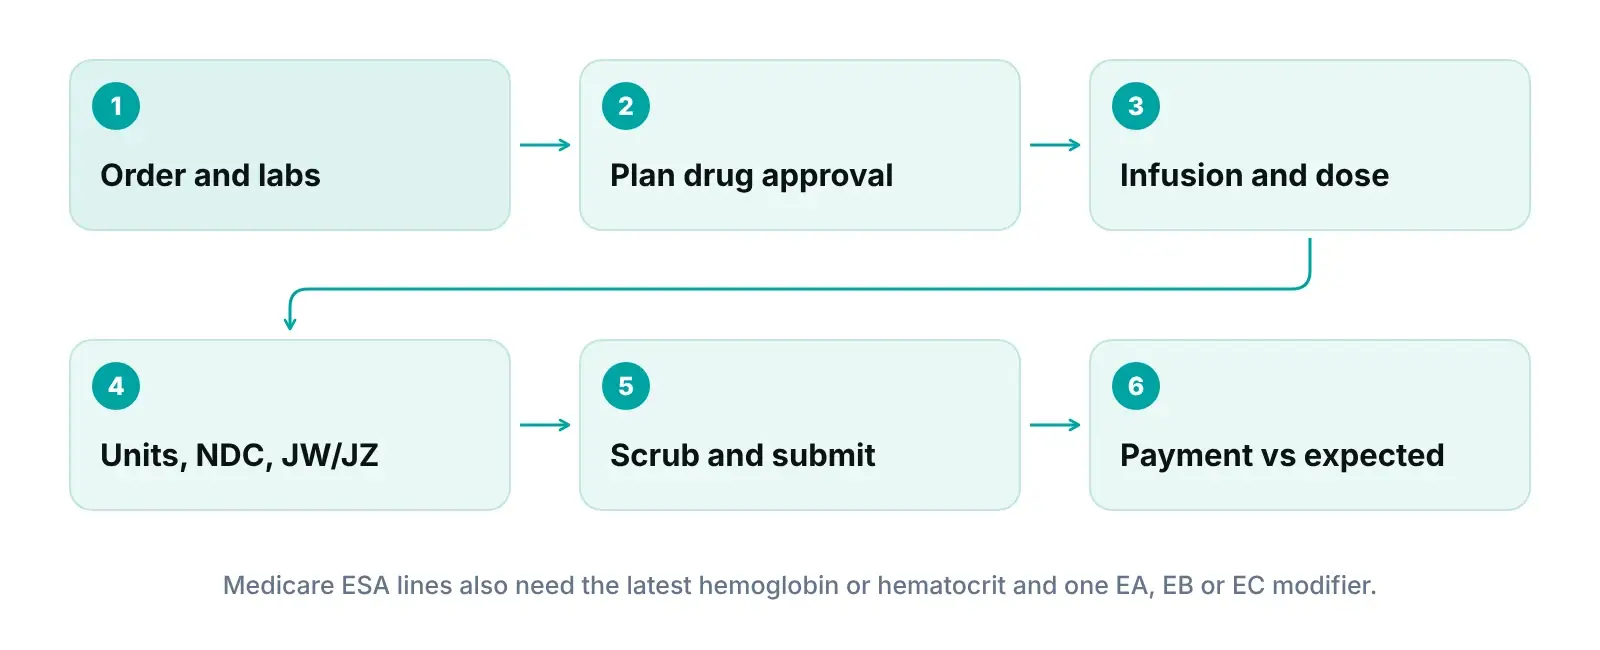
Diagram of a hematology infusion claim moving from order and labs to drug authorization, units and JW/JZ checks, and payment review
How one hematology infusion becomes a clean drug and administration claim.

Units come from the code, not the vial

Drug codes are billed in the unit written into the code. Ferric carboxymaltose (J1439) bills per 1 mg and ferric derisomaltose (J1437) per 10 mg, so 750 mg is 750 units under J1439 but 75 units under J1437. Our guide to J-codes in medical billing explains how drug codes work.

For single-dose containers, CMS's claims manual (chapter 17, section 40) has required the JW modifier since January 1, 2017, for any discarded amount, on its own line. Since July 1, 2023, JZ attests that nothing was discarded. If one billing unit covers both dose and leftover, JW is not allowed. Neither modifier applies to multiple-dose containers.

Administration codes follow NCCI rules

The 2026 NCCI policy manual, chapter XI, allows one initial administration code per encounter unless drugs need separate IV sites. Starting the IV and flushing a port are included, and so is a nurse-level visit (99211). A significant, separately documented E/M visit takes modifier 25. Physicians do not report these codes in facility settings such as a hospital outpatient department. See our 96372 CPT code guide and our guide to home infusion and IVIG billing.

ESA claims need a lab value and a modifier

Since January 1, 2008, every non-ESRD claim for an ESA must report the most recent hemoglobin or hematocrit and one modifier: EA (anemia from chemotherapy), EB (from radiation) or EC (from neither), per CMS Transmittal 1412. On an electronic professional claim, the value goes in loop 2400, MEA segment; professional claims without it are returned as unprocessable. Some contractors ask for more: Noridian (JE Part B) has required both hemoglobin and hematocrit since a June 2025 update and rejects claims missing either.

NCD 110.21 sets Medicare coverage for ESAs in cancer and related neoplastic conditions. Its claim edits (Transmittal 1413) still reach benign practices: contractors deny EA lines reporting hemoglobin of 10.0 g/dL or more, and EC lines carrying listed diagnoses such as iron, folate or B-12 deficiency, hemolysis or bleeding. For uses the NCD does not address, your MAC decides. Lab orders need diagnosis support too; see our CBC ICD-10 code guide.

Phlebotomy and bone marrow: bundling edits

NCCI bundles venipuncture, IV access and drug administration into therapeutic phlebotomy (99195). For bone marrow, NCCI chapter V uses 38222 when aspiration and biopsy share one iliac bone; 38220 and 38221 pair only across different bones or encounters.

Prior authorization and payer rules to check before the infusion

Get the drug approved before the chair is booked, not after a denial. Criteria for IV iron, ESAs, immune globulin and clotting factor differ by plan and product.

Plan rules name products, labs and prior treatments. UnitedHealthcare’s 2026 commercial IV iron policy treats Feraheme, Ferrlecit, INFeD and Venofer as preferred, sets criteria for Injectafer and calls Monoferric not medically necessary for the diagnoses it covers. For Injectafer, it asks for records of iron deficiency anemia, an oral iron failure, intolerance or listed exception, and failure of, or intolerance to, preferred IV products. Its ESA policy prefers Retacrit on medical necessity plans and, for kidney disease without dialysis, starts therapy only below 30% hematocrit.

Hemophilia adds benefit questions. UnitedHealthcare's clotting factor policy requires inhibitor documentation, such as a Bethesda assay, for FEIBA and NovoSeven and generally places non-factor agents such as Hemlibra under the pharmacy benefit. Its immune globulin policy sets platelet criteria for ITP.

The workload is heavy. In the AMA’s 2025 survey of 1,000 physicians, released in May 2026, physicians averaged 40 prior authorizations and 13 hours of physician and staff time each week. For the general process, read our prior authorization guide for providers.

Pre-infusion checklist: payer rules our VMAs check before scheduling
RuleSourceWhat the VMA checks
MA, Medicaid and CHIP plans decide in 72 hours or 7 days, but drugs are excluded; MA Part B drug requests are due in 72 hours (24 if expedited)CMS-0057-F (Jan 1, 2026); 42 CFR 422.568, 422.572Request date and time logged; follow-up when the plan's drug deadline passes
Feraheme, Ferrlecit, INFeD and Venofer are preferred; Injectafer needs criteria; Monoferric is not medically necessaryUnitedHealthcare 2026D0088R (Sept 1, 2026)Product against the plan list; iron deficiency records and oral iron history
Retacrit preferred; kidney disease without dialysis starts below 30% hematocrit, other causes ruled outUnitedHealthcare 2026D0028Y (Apr 1, 2026)Product, recent hematocrit or hemoglobin and iron studies
Medicare non-ESRD ESA lines need the latest hemoglobin or hematocrit (Noridian JE: both) and EA, EB or ECCMS Transmittal 1412 (2008); Noridian JE (2025)Lab value and date passed to billing with the dose
IVIG for ITP: acute needs platelets below 50 × 10⁹/L within 30 days; chronic needs steroid or splenectomy failure, contraindication or intoleranceUnitedHealthcare 2026D0035AV (Oct 1, 2026)Platelet count date and prior ITP treatments
FEIBA and NovoSeven need inhibitor documentation; non-factor agents generally use the pharmacy benefitUnitedHealthcare 2026D0047AN (Oct 1, 2026)Inhibitor assay, use type and which benefit pays
Home INR: mechanical valve, chronic AF or VTE; 3+ months on warfarin; training first; at most weeklyMedicare NCD 190.11Warfarin start date and training record

Sources: CMS-0057-F fact sheet (2024); eCFR 42 CFR 422.568 and 422.572; UnitedHealthcare commercial medical benefit drug policies 2026D0088R, 2026D0028Y, 2026D0035AV and 2026D0047AN (2026); CMS Transmittal 1412 (2008); Noridian JE Part B (2026); NCD 190.11. Commercial rows are one plan's rules; always check the member's current plan.

See what drug denials cost you

Enter your claim volume and denial rate to estimate what delayed approvals and unit errors cost your hematology practice.

Open the Revenue Calculator

Growing a hematology practice without breaking privacy rules

Hematology growth depends on referring clinicians and on patients searching for answers about anemia, bleeding or clotting, and your tracking must respect HIPAA.

We build location pages, condition pages for patients and a simple referral path for primary care, OB-GYN, nephrology and other offices, listing which recent labs to send. We ask real patients for reviews and write responses that never confirm someone is a patient.

HHS guidance on online tracking says tracking tools on login or appointment pages can collect protected health information, and a cookie banner is not a HIPAA authorization. A 2024 court order vacated part of that guidance. Even so, we keep tracking off appointment and referral forms unless the vendor signs a BAA.

  • Referral KPIs: new referrals by office; days from referral to first visit.
  • Patient KPIs: booked visits by source; missed calls.

In-house team, billing-only vendor or four-pillar partner?

Stay in-house if your billers know drug units and infusion rules and your front desk has time for drug approvals. Use a billing-only vendor if claims are your only gap. Choose a combined partner when problems span approvals, billing and growth.

Decision table: which model fits a hematology practice?
JobIn-house teamBilling-only vendorFour-pillar partner (RCM Finder)
Drug prior authorizationFront desk or nurses, between patientsUsually left to the practiceVMA starts each request and tracks it to a decision
Drug units, NDCs and JW/JZDepends on one billerFixed after the factChecked before submission
ESA lab values and modifiersPulled from the chart at billing timeRequested from the practiceCaptured with the dose; claim held if missing
Referral growth and reviewsA separate agency, or nobodyNot includedMarketing pillar tied to booked visits
ReportingEHR reportsClaim reports onlyPortal and dashboards, referral to paid claim
Cost structureSalaries, benefits, turnoverVaries; ask how fees are setQuoted after a free practice audit

We will tell you in the audit if you need only one pillar; our revenue cycle management services and virtual medical assistant services can be contracted separately.

How it works

We start with a free audit and change nothing until you see the findings. We build our billing pipeline around how claims actually move through a practice: registration, charge entry, submission, payment and follow-up. For hematology, we add the drug, infusion and lab-value checks on this page.

  1. 1

    Free practice audit

    We review recent drug and infusion claims, denials and authorization logs, checking units, modifiers and lab values line by line.

  2. 2

    Business Associate Agreement and access

    We put a Business Associate Agreement in place before accessing patient data. Then we work inside your existing EHR (for example PrognoCIS, eClinicalWorks or athenahealth).

  3. 3

    Payer-rule map

    Your plans' drug policies and your Medicare contractor's guidance become a pre-infusion checklist and portal workflow rules.

  4. 4

    Front desk and billing go live

    VMAs start drug approvals and collect labs. Claims are scrubbed, submitted and worked through denials and A/R.

  5. 5

    Weekly KPI review

    Each week we review denials by reason, A/R days, infusions cleared in advance and referrals.

Talk to us about your hematology practice

Tell us your infusion volume, drug mix and hardest payer. We will tell you honestly whether we fit.

Call +1 (302) 556-2288

Compliance: what to ask any hematology billing company

Any billing vendor that handles your patients' data is a HIPAA business associate. Get a Business Associate Agreement before they have any access, and check how they limit and log that access.

HHS guidance names billing and claims processing as business associate work, and subcontractors need their own agreement. The minimum necessary standard limits use to what each task needs. The Security Rule's technical safeguards require access control, audit controls, integrity controls, person or entity authentication and transmission security.

  1. Will you and your subcontractors sign a Business Associate Agreement before any access?
  2. How do you limit access, and can we see the audit log?
  3. Who codes our drug claims, and what coding credential and hematology experience do they hold?
  4. How do you check drug units, NDCs and JW or JZ before submission?
  5. Which payer drug policies do you track, and how often?
  6. Can we export our data if we leave?

We use role-based access, audit logging and encrypted (HTTPS) connections, and we put a Business Associate Agreement in place before accessing patient data. For your own side, use our HIPAA compliance checklist for medical practices.

Who this is for, and who it is not for

We would rather tell you now than after you sign. Here is where we fit and where we do not.

A good fit if you are

  • Independent benign hematology practices with an in-office infusion suite
  • Groups giving IV iron, ESAs, immune globulin or clotting factor under the medical benefit
  • Practices with heavy drug prior authorization volume
  • Billing companies serving hematology clients that want a shared claims portal
  • Practices that want referrals, front desk and billing measured together

Probably not a fit if you are

  • Practices focused on cancer chemotherapy; see our oncology page instead
  • Hospital-employed hematologists whose billing the hospital controls
  • Practices looking for promised collection rates; we report measured KPIs instead
  • Groups that need a credentialing module or in-portal real-time eligibility today (coming next)

Expert recommendations from our operations team

What we would do first if we were running your practice's revenue cycle tomorrow.

  1. 01

    Bill units from the code, not the vial

    We divide every dose by the unit in the HCPCS code and check it against the administration record. Unit sizes differ even between iron products.

  2. 02

    Put JZ or JW on every single-dose drug line

    Each single-dose line gets JZ when nothing was discarded, or a separate JW line for the waste. We ask nurses to chart the discarded amount.

  3. 03

    Capture the latest hemoglobin before every ESA dose

    We pass the most recent hemoglobin and hematocrit to billing with the dose and choose EA, EB or EC from the chart. Under Medicare's ESA edits, an EC line coded with iron deficiency is a predictable denial.

  4. 04

    Approve the product, not just the drug class

    Plans prefer specific iron and ESA products. We check the member's preferred list before the order is final.

  5. 05

    Put reauthorization dates on the calendar

    The UnitedHealthcare IV iron, ESA and immune globulin policies we reviewed cap approvals at 12 months. We start renewals early, with fresh labs.

  6. 06

    Confirm which benefit pays for hemophilia drugs

    Factor products and non-factor agents can sit under different benefits. We confirm the benefit and inhibitor status before the first dose.

Frequently asked questions

What do hematology billing services include?

They cover coding support, claim scrubbing, submission, denial management and A/R follow-up for hematology visits, infusions, injections and procedures such as bone marrow biopsy and therapeutic phlebotomy. Because drug lines have their own unit and modifier rules, a good service also checks drug units, NDCs, JW and JZ modifiers and ESA lab reporting, and starts prior authorizations before the infusion. We add front-desk assistants, patient marketing and a claims portal.

How do we bill units for IV iron such as Injectafer or Venofer?

Divide the dose given by the unit in the HCPCS code. Ferric carboxymaltose (Injectafer, J1439) and iron sucrose (Venofer, J1756) are billed per 1 mg, so 200 mg of iron sucrose is 200 units. Ferric derisomaltose (J1437) is billed per 10 mg. For single-dose vials, report any discarded amount on its own line with JW, or add JZ when nothing was discarded.

What must a Medicare claim for an ESA include?

For patients without end-stage renal disease (ESRD), CMS has required since January 1, 2008, that each ESA line report the most recent hemoglobin or hematocrit and one modifier: EA for anemia from chemotherapy, EB for anemia from radiation, or EC for anemia from neither. On electronic professional claims, the value goes in loop 2400, MEA segment. Claims missing the value or modifier are returned, and EA lines reporting hemoglobin of 10.0 g/dL or more are denied. Noridian JE now asks for both values.

How does Medicare pay for clotting factor for hemophilia?

Clotting factor is billed per international unit with HCPCS codes such as J7192 for recombinant factor VIII not otherwise specified. Medicare also pays a furnishing fee per unit to entities that furnish clotting factor, unless another payment system already covers those costs. The fee is $0.265 per unit for 2026 and $0.270 for 2027, and it is built into the published payment limit for clotting factor codes.

Can we bill an office visit on the same day as an infusion or phlebotomy?

Sometimes. Under the 2026 NCCI manual, a nurse-level visit (99211) is included in drug administration and is not billed separately. A higher-level visit can be billed with modifier 25 when the physician provides a significant, separately identifiable service and documents it. For therapeutic phlebotomy, venipuncture, IV access and drug administration are part of the service and are not billed on their own.

Is it safe to outsource hematology billing under HIPAA?

It can be, if the vendor is treated as a business associate. HIPAA requires a Business Associate Agreement before the vendor receives patient data, and that agreement must require the vendor to safeguard it. The Security Rule's technical safeguards include access control and audit controls. We put a Business Associate Agreement in place before accessing patient data, and we use role-based access, audit logging and encrypted (HTTPS) connections.

No cost, no commitment

Get your free practice audit

Tell us about your practice. A member of our operations team replies within one business day.

  • A review of your recent claims, denials and A/R aging
  • Where your front desk and prior authorizations slow payment
  • A prioritized fix list you keep, whether or not you hire us

Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.

Tell us about your practice

RCMFinder Master Intake Form
AA

About the author: Awais Afzal

Healthcare Operations & Data Analyst, RCM Finder

Awais has spent more than 16 years in healthcare digital marketing and clinical operations management. He builds data-driven revenue cycle blueprints for high-ticket medical practices and leads product development of the RCM Finder portal. More about our team.

How we write: every figure, code and rule on this page was checked against the primary source listed below and independently fact-checked before publishing. We re-review this page every six months. Last reviewed October 12, 2026; next review April 12, 2027.

Sources

  1. Medicare Claims Processing Manual, Chapter 17: Drugs and Biologicals — CMS (Chapter rev. 13379 (issued 08-21-25); §40 rev. 13108 (effective 01-01-25))
  2. Medicare Claims Processing Manual, Chapter 12: Physicians/Nonphysician Practitioners (Section 30.5) — CMS (accessed 2026-10-10 (section 30.5 rev. effective 01-01-25))
  3. NCD 110.21: Erythropoiesis Stimulating Agents (ESAs) in Cancer and Related Neoplastic Conditions — CMS Medicare Coverage Database (Version 1, effective 07/30/2007 (maintenance updates through 10/2024))
  4. Transmittal 1412 (CR 5699): Hematocrit or Hemoglobin Reporting on ESA Claims and New Modifiers for Non-ESRD ESA Use — CMS (2008)
  5. Transmittal 1413 (CR 5818): Erythropoiesis Stimulating Agents (ESAs) in Cancer and Related Neoplastic Conditions — CMS (2008)
  6. Oncology/Hematology specialty page (JE Part B) — Noridian Healthcare Solutions (Medicare contractor) (Last updated January 28, 2026)
  7. NCD 190.11: Home Prothrombin Time/International Normalized Ratio (PT/INR) Monitoring for Anticoagulation Management — CMS Medicare Coverage Database (Version 2, effective 03/19/2008)
  8. Transmittal 13379 (CR 14196): Annual Clotting Factor Furnishing Fee Update 2026 — CMS (via HHS guidance portal) (2025 (issued August 21, 2025; effective January 1, 2026))
  9. Transmittal 13937 (CR 14580): Annual Clotting Factor Furnishing Fee Update 2027 — CMS (via HHS guidance portal) (2026 (issued August 27, 2026; effective January 1, 2027))
  10. Transmittal 12795 (CR 13742): Annual Clotting Factor Furnishing Fee Update 2025 — CMS (2024 (issued August 15, 2024))
  11. Medicare NCCI Policy Manual, Chapter V (CPT 30000-39999) — CMS (2026 (revision date 1/1/2026))
  12. Medicare NCCI Policy Manual, Chapter XI (CPT 90000-99999) — CMS (2026 (revision date 1/1/2026))
  13. 42 CFR 447.520: FFP: Conditions relating to physician-administered drugs — eCFR (current (accessed 2026-10-10))
  14. CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) fact sheet — CMS (2024)
  15. 42 CFR 422.568 Standard timeframes and notice requirements for organization determinations — eCFR (current (up to date as of 10/07/2026))
  16. 42 CFR 422.572 Timeframes and notice requirement for expedited organization determinations — eCFR (current (up to date as of 10/07/2026))
  17. AMA survey: Prior authorization reform pledge falls short with physicians — American Medical Association (2026)
  18. Intravenous Iron Replacement Therapy (Injectafer & Monoferric), Commercial and Individual Exchange Medical Benefit Drug Policy 2026D0088R — UnitedHealthcare (2026 (effective September 1, 2026))
  19. Erythropoiesis-Stimulating Agents, Commercial Medical Benefit Drug Policy 2026D0028Y — UnitedHealthcare (2026 (effective April 1, 2026))
  20. Immune Globulin (IVIG and SCIG), Commercial Medical Benefit Drug Policy 2026D0035AV — UnitedHealthcare (2026 (effective October 1, 2026))
  21. Clotting Factors, Coagulant Blood Products, & Other Hemostatics, Commercial Medical Benefit Drug Policy 2026D0047AN — UnitedHealthcare (2026 (effective October 1, 2026))
  22. Business Associates — HHS Office for Civil Rights (2026 (content last reviewed July 30, 2026))
  23. Minimum Necessary Requirement — HHS Office for Civil Rights (2013 (content last reviewed July 26, 2013))
  24. 45 CFR 164.312 Technical safeguards — eCFR (current (accessed 2026-10-10))
  25. Use of Online Tracking Technologies by HIPAA Covered Entities and Business Associates — HHS Office for Civil Rights (2024 (content last reviewed June 26, 2024))
  26. HCPCS J1439 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  27. HCPCS J1756 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  28. HCPCS J1437 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  29. HCPCS Q0138 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  30. HCPCS J0885 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  31. HCPCS J0881 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  32. HCPCS J7192 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  33. CPT 96365 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  34. CPT 96366 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  35. CPT 96374 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  36. CPT 96372 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  37. CPT 99195 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  38. CPT 38220 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  39. CPT 38221 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  40. CPT 38222 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  41. CPT 93792 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)
  42. CPT 93793 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-10)