
Dermatology Specialty

Dermatology Billing Services, Front Desk and Patient Growth in One Plan

Same-day visits, biopsies, Mohs and pathology claims, biologic prior authorization, patient marketing and a claims portal for dermatology practices, built on CMS rules and your payers' own policies.
  • Works inside your current EHR
  • US practice time zone, every shift
  • Weekly KPI reporting, or on your schedule
Dermatology billing dashboard with denials by reason, modifier 25 claims, biologic authorizations, A/R days and new patients

Quick answer

Dermatology billing services handle the claims a skin practice creates: same-day visits with modifier 25, biopsies coded by technique, destruction counts, Mohs stages and blocks, dermatopathology, and the line between cosmetic and medically necessary care. RCM Finder pairs that billing with front-desk assistants who start biologic approvals, patient marketing and a claims portal.

Disclaimer: This page is educational and is not legal, coding or compliance advice. Medicare LCDs, billing articles, fee schedule rules and commercial payer policies change often and vary by contractor and plan. Verify every code, limit and rule against your Medicare contractor's current documents, your payer contracts and the current CPT and HCPCS code sets before billing.

Why dermatology billing is different

Dermatology billing is different because many visits pair an exam with minor procedures, and each lesion can carry its own code, diagnosis and coverage rule. Many practices also sell cosmetic services Medicare never covers.

The same-day pattern draws audits. In a November 2025 HHS-OIG report, about 61.5% of Medicare-paid dermatology E/M claims in 2019 and 2020 included a same-day minor procedure by the same dermatologist. Of 100 sampled visits, 10 did not meet Medicare requirements, and OIG estimated $62,915,655 in overpayments. A March 2026 OIG work plan item adds an audit of same-day visits paid without modifier 25.
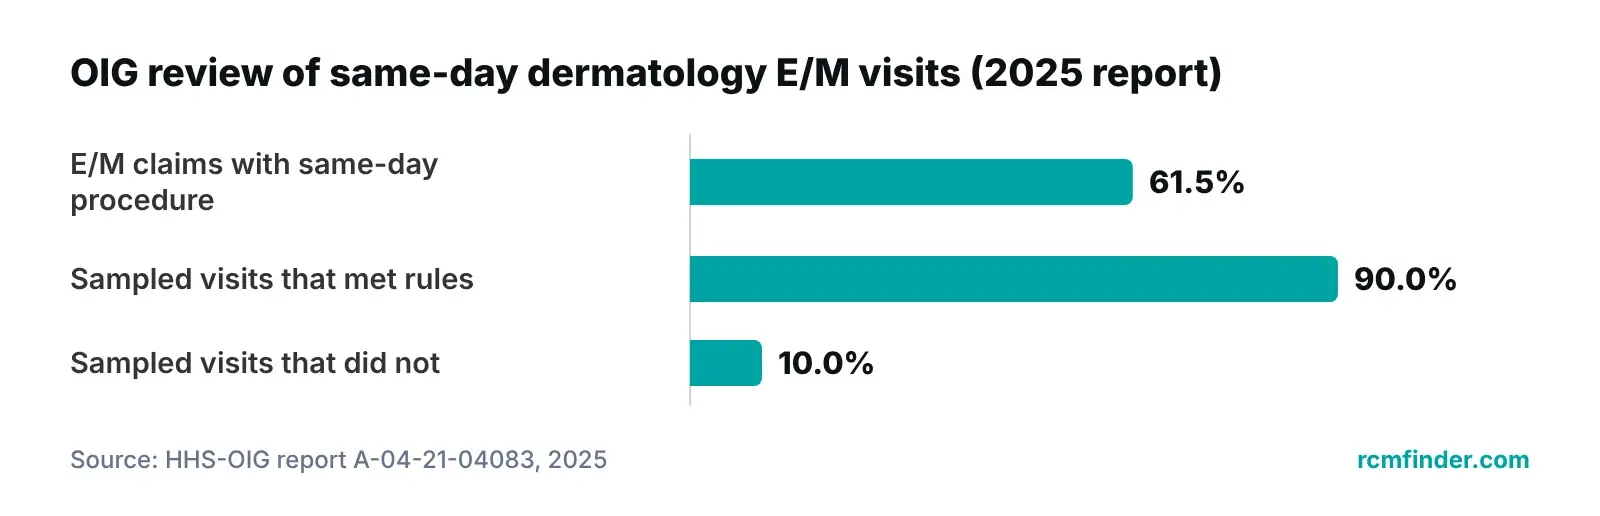
Bar chart of HHS-OIG 2025 findings on dermatology E/M visits billed on the same day as minor procedures
Medicare dermatology claims only. The 90% and 10% bars are shares of OIG's 100-visit sample.

What changed in 2026, and what may change in 2027

In its CY 2026 Physician Fee Schedule final rule fact sheet (October 31, 2025), CMS set the conversion factor at $33.40 for clinicians who are not qualifying APM participants, up from $32.35. It applied a -2.5% efficiency adjustment to services that are not time-based; E/M visits are exempt.

The four pillars, built for a dermatology practice

Revenue leaks at the handoffs: a cosmetic removal booked as medical, a Mohs case booked before the biopsy report arrives, a biologic prescribed before approval. We run all four pillars against one set of payer rules.

Pillar 1 · Healthcare Marketing

Healthcare Marketing for dermatology practices

Our healthcare digital marketing builds demand for medical visits and any cosmetic services you offer, through local SEO, Google Ads and reputation work.

  • A Google Business Profile and location page per office
  • Pages for skin checks, eczema, psoriasis and acne
  • Before-and-after photos only with written authorization
  • KPI: booked visits by source
Explore Healthcare Marketing
Pillar 2 · Virtual Medical Assistants

Virtual Medical Assistants for dermatology front desks

Our virtual medical assistants for dermatology run your front desk on your practice's time zone, from eligibility checks to biologic and phototherapy approvals.

  • Cosmetic or medical flagged at booking
  • Referring biopsy report on file before Mohs
  • Approvals tracked to a decision
  • KPI: visits cleared before the date of service
Explore Virtual Medical Assistants
Pillar 3 · End-to-End RCM

End-to-End RCM for dermatology claims

Our end-to-end dermatology revenue cycle management covers coding support, claim scrubbing, denial management and A/R follow-up, with lesion-level checks on every claim.

  • Modifier 25 only with a documented separate visit
  • One primary biopsy code, add-ons for the rest
  • Mohs stages, blocks, repair and 26 or TC checked
  • KPI: denials by reason and A/R days
Explore End-to-End RCM
Pillar 4 · Practice Management System

Practice Management System for dermatology billing

Our practice management system tracks every claim by stage, applies specialty-aware billing logic per claim and checks data completeness before submission.

  • Rules that hold a claim missing a pathology report
  • Underpayment flags against expected amounts
  • Client portal for practices and billing companies
  • Early access: appointment booking with a calendar view
Explore Practice Management System

Find where your dermatology claims leak

We review recent same-day visits, biopsy and Mohs claims and authorization logs, then show what to fix first. Pricing is quoted after the audit.

Get a Free Practice Audit

Dermatology service families: codes, rules and denial triggers

Most dermatology denials trace to a few rules: a visit not separate from the procedure, more than one primary biopsy code, a wrong destruction count, pathology billed on Mohs margins, or cosmetic work billed as medical. Codes are described in our own words (the AMA owns CPT descriptors).

Dermatology service families: code examples, billing rules and typical denial triggers
Service familyCode examples (our wording)Billing ruleTypical denial trigger
Visit on the day of a minor procedureOffice E/M with modifier 25; procedure with a 0- or 10-day globalDecision to treat is included; a separate visit must be significant and separately identifiableVisit billed for the decision to treat; G2211 with a modifier 25 visit
Skin biopsy11102/11103 (tangential); 11104/11105 (punch); 11106/11107 (incisional)One primary code, chosen in order (incisional, punch, tangential); others as add-onsMore than one primary biopsy code; biopsy of a lesion removed at that visit
Premalignant lesion destruction17000 (first lesion); 17003 (2nd to 14th, each); 17004 (15 or more)Medicare covers actinic keratosis destruction without lesion or patient limits17004 billed with 17000 or 17003
Benign lesion removal11300–11313 (shave removal); 17110 (up to 14); 17111 (15 or more)Covered only with a documented reason such as bleeding, pain or diagnostic doubtRemoval for appearance alone; unlisted diagnosis
Mohs surgery17311/17312 (head, neck, hands, feet, genitalia); 17313/17314 (trunk, arms, legs); 17315 (blocks past five)One physician as surgeon and pathologist; Appropriate Use Criteria applySurgical pathology on margin tissue; trunk or limb lesion without a listed indication
Dermatopathology88302–88309 (surgical pathology by level); 88331 (frozen section)Global only if you prepare and read the slide; 26 for the reading aloneGlobal billed when an outside lab made the slide; Mohs claim without CLIA coverage
Phototherapy96910 (UVB with tar or petrolatum); 96912 (PUVA); 96913 (4–8 hour severe cases); 96920–96922 (excimer laser)Medicare covers PUVA only after conventional treatment failsNo documented failure of other treatment; sessions past the approved count
Self-injected biologicsDupilumab, secukinumab, risankizumab and similar drugsOn a self-administered drug list, so not Part BBilled to Part B as an office drug

Sources: CMS 2026 NCCI Policy Manual ch. 3; CMS Claims Processing Manual ch. 12 §30.6.6; CMS Transmittal 13015 (2024); AAD Dermatology World (2018); CMS Transmittal 1165 (2007); NCD 250.4 and 250.1; WPS DERM-008 coding guideline (2009, archived); Noridian LCDs L34233 and L35702 and articles A57161 and A56514 (2025–2026); Noridian modifier 26 page; Mass General Brigham Health Plan policy 043 (2025); Novitas A53127 (2026). Rules vary by contractor and payer.
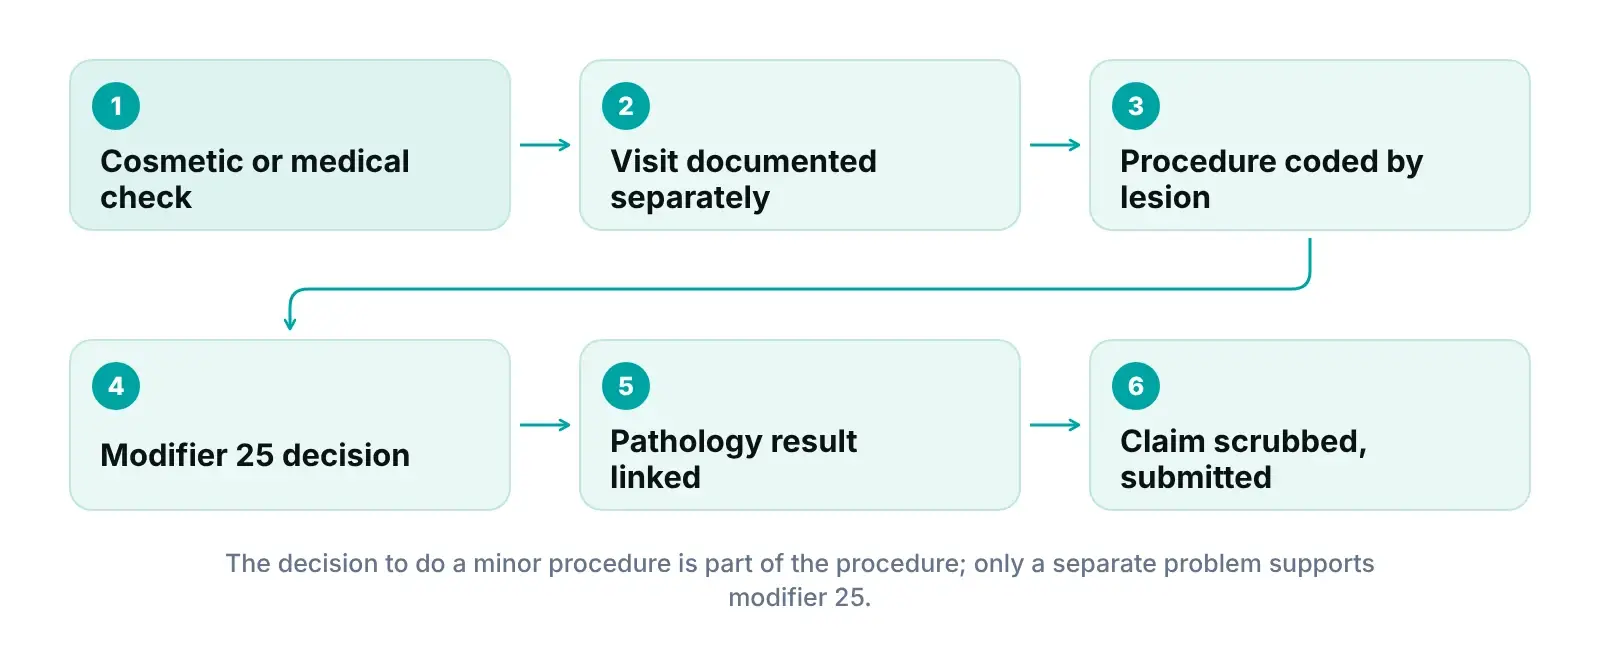
Diagram of a dermatology visit moving from cosmetic or medical check to modifier 25 decision, lesion coding and claim
How a same-day dermatology visit and procedure become a clean claim.

Modifier 25: the visit must be separate from the decision

The 2026 NCCI Policy Manual says the decision to perform a minor procedure is part of that procedure's payment, and new-patient status alone does not justify a separate visit. The CMS claims processing manual adds that different diagnoses are not required, but both services must be documented. Under a December 2024 CMS transmittal, G2211 is not paid with a modifier 25 visit unless an annual wellness visit, vaccine administration or Part B preventive service is on the same day. See our explainer on modifier 25 vs 59.

Biopsies and destructions are coded by lesion

Since 2019, skin biopsies are coded by technique, each with a first-lesion code and an add-on, as a Nevada Medicaid notice lists. The American Academy of Dermatology's Dermatology World explains that only one primary biopsy code is reported, chosen in this order: incisional, then punch, then tangential. NCCI folds a biopsy into the removal code when that lesion is removed at the same encounter. For actinic keratoses, NCD 250.4 covers destruction without restrictions based on lesion or patient characteristics.

Mohs surgery: one physician, two roles

Noridian's Mohs LCD (L35702) follows the 2012 Appropriate Use Criteria and requires one physician to act as surgeon and pathologist. Its billing article (A56514) says billing surgical pathology codes on Mohs margin tissue is inappropriate, and it denies those Mohs claims. NCCI allows a pre-Mohs biopsy and frozen section with modifier 59, XS, XU or 58, and repairs, grafts and flaps are billed separately; see our skin graft CPT codes guide. A 2007 CMS transmittal places the Mohs codes under CLIA edits. Other MACs may differ.

Dermatopathology: who prepared the slide, who read it

Noridian applies modifier 26 to pathology readings billed apart from the technical component, which CMS MLN Matters SE0587 defines as staff, supplies and equipment. Bill globally only when your practice prepares and reads the slide. See our pathology CPT codes guide.

Diagnosis coding decides medical necessity

Noridian's benign lesion billing article (A57161) lists diagnoses that pay alone and others that need a complicating diagnosis, and treats any unlisted code as unsupported. See our guides to eczema ICD-10 codes and ICD-10 codes for skin tags.

Cosmetic or medically necessary: decide before the procedure

Decide whether a service is cosmetic or medically necessary when it is booked, document the reason, and tell the patient the price before the procedure.

Under 42 CFR 411.15(h), Medicare excludes cosmetic surgery, except prompt repair of accidental injury or improving the function of a malformed body member. Noridian's benign skin lesion LCD (L34233) covers removal only when the record shows a reason such as bleeding, intense itching, pain, inflammation, an obstructed orifice or vision, diagnostic doubt or repeated trauma. Removal for appearance alone is the patient's cost.

When to use an ABN, and which modifier goes on the claim

Chapter 30 of the CMS claims processing manual says ABNs are not required for statutorily excluded care such as cosmetic surgery, though CMS encourages voluntary notices. It rejects routine or blanket notices. Use the ABN (form CMS-R-131) when a covered service may be denied as not reasonable and necessary. CGS, a Medicare contractor, lists the claim modifiers:

  • GA: a required ABN was given and is on file.
  • GZ: denial is expected as not reasonable and necessary, and no ABN was given.
  • GX: a voluntary ABN was given for a service Medicare never covers.
  • GY: the service is statutorily excluded or not a Medicare benefit.

Our guide to dermatology services covered by insurance and ABN guide for medical billing go deeper.

Biologics, phototherapy and other approvals to clear before the visit

Start prior authorization when the visit or prescription is planned. In dermatology that usually means self-injected biologics for psoriasis and atopic dermatitis, and phototherapy.

Novitas's self-administered drug exclusion list (A53127) includes dupilumab, secukinumab, risankizumab and subcutaneous ustekinumab, among others. Drugs on these lists are self-administered more than 50% of the time, so Part B does not cover them as office drugs. For Medicare patients, coverage runs through the Part D plan, which CMS gives 72 hours for a standard decision and 24 hours for an expedited one.

For medical services, the CMS-0057-F rule has required Medicare Advantage, Medicaid and CHIP plans since January 1, 2026 to decide expedited requests within 72 hours and standard ones within seven calendar days; drugs are excluded. In the AMA's 2025 survey of 1,000 physicians (released May 2026), physicians averaged 40 prior authorizations and 13 hours of physician and staff time per week.

For phototherapy, Medicare's psoriasis NCD (250.1) covers PUVA only for intractable, disabling psoriasis that has not responded to conventional treatment. Commercial plans set their own rules. Mass General Brigham Health Plan's 2025 policy, for example, requires approval for photochemotherapy and excimer laser and allows up to 36 initial photochemotherapy treatments within 16 weeks.

Pre-visit checklist: dermatology payer rules our VMAs check before the visit
RuleSourceWhat the VMA checks before the visit
Benign lesion removal needs a documented medical reason; cosmetic removal is the patient's costNoridian LCD L34233 (2025)Reason for the visit; if cosmetic, price quoted and self-pay agreed
ABN not required for excluded care; no blanket ABNs; GA, GX, GY, GZ on claimsCMS Claims Processing Manual ch. 30; CGSMandatory ABN only when a covered service may be denied
Self-injected biologics on the self-administered drug list are not Part B drugsNovitas A53127 (2026)Drug plan, its approval form, prior treatments and pharmacy confirmed
Part D: 72 hours standard, 24 hours expedited; exception clock starts with the prescriber's statementCMS Part D coverage determinations pageRequest date logged; prescriber statement sent; follow-up on the due date
MA, Medicaid and CHIP medical requests: 72 hours expedited, 7 days standard; drugs excludedCMS-0057-F; in effect Jan 1, 2026Due date logged; denial reason saved for appeal
PUVA covered for intractable, disabling psoriasis after conventional treatment failsNCD 250.1Prior treatments and dates charted
Example plan: photochemotherapy and excimer need approval; photochemotherapy starts at up to 36 treatments in 16 weeksMass General Brigham Health Plan policy 043 (2025)Sessions used vs approved
Mohs: trunk and limb lesions only for listed indications; if the site was biopsied in the last 60 days, get that report instead of repeating the biopsyNoridian L35702 and A56514Lesion site and referring pathology report on file

Sources: CMS Medicare Coverage Database (Noridian L34233, L35702, A56514, 2025–2026; Novitas A53127, 2026); CMS Claims Processing Manual ch. 30; CGS ABN page (2026); CMS Part D coverage determinations page (2024); CMS-0057-F fact sheet (2024); NCD 250.1; Mass General Brigham Health Plan policy 043 (2025). Always check the member's current plan.

See also our guide to expediting prior authorization for medication.

See what delays and denials cost you

Enter your claim volume and denial rate to estimate what your dermatology practice is losing.

Open the Revenue Calculator

Growing a dermatology practice without breaking privacy rules

Dermatology growth comes from medical and cosmetic demand, and both meet privacy rules when you use patient photos, reviews or website tracking.

Full face photos are HIPAA identifiers under 45 CFR 164.514, and 45 CFR 164.508 requires the patient's authorization to use protected health information for marketing. We post before-and-after photos only with a signed authorization. HHS guidance says tracking on appointment pages can collect protected health information. A 2024 court order vacated part of it; we still keep tracking off booking forms without a vendor BAA.

The FTC's 2024 final rule bans fake reviews and paying for reviews of a particular sentiment. Our review replies never confirm that someone is a patient. For the cosmetic side, see our aesthetic practice growth strategies.

  • Medical KPIs: booked skin checks and new patients by source.
  • Cosmetic KPIs: consults booked and self-pay collected at the visit.

In-house team, billing-only vendor or four-pillar partner?

Stay in-house if you have experienced dermatology coders and time for biologic approvals. Use a billing-only vendor if claims are your only gap. Choose a combined partner when problems start at booking.

Decision table: which model fits a dermatology practice?
JobIn-house teamBilling-only vendorFour-pillar partner (RCM Finder)
Cosmetic or medical, decided at bookingFront desk, if trainedUsually left to the practiceVMA flags it; price quoted first
Modifier 25 and lesion-level codingDepends on one coderFixed on the claim, after the visitChecked against the note before submission
Biologic and phototherapy approvalsStaff between callsUsually out of scopeVMA tracks each request to a decision
Mohs and pathology claimsSurgeon's teamCoded from the charge sheetStages, blocks, repair and 26 or TC checked
Patient growth and reviewsA separate agency, or nobodyNot includedMarketing tied to booked visits
Cost structureSalaries, benefits, turnoverVaries; ask how fees are setQuoted after a free practice audit

How it works

We start with a free audit and change nothing until you see the findings. We build our billing pipeline around how claims actually move through a practice: registration, charge entry, submission, payment and follow-up. For dermatology, we add the checks on this page.

  1. 1

    Free practice audit

    We review recent same-day visits, biopsy, Mohs and pathology claims, cosmetic charges and authorization logs.

  2. 2

    Business Associate Agreement and access

    We put a Business Associate Agreement in place before accessing patient data. Then we work inside your existing EHR (for example PrognoCIS, eClinicalWorks or athenahealth).

  3. 3

    Payer-rule map

    Your contractor's lesion and Mohs documents and your plans' drug and procedure rules become a pre-visit checklist and portal rules.

  4. 4

    Front desk and billing go live

    VMAs sort cosmetic from medical and start approvals. Claims are coded by lesion, scrubbed, submitted and worked through denials and A/R.

  5. 5

    Weekly KPI review

    We review denials by reason, modifier 25 claims, A/R days and new patients by source each week.

Talk to us about your dermatology practice

Tell us your procedure mix, whether you run a Mohs lab and your hardest payer. We will tell you honestly whether we fit.

Call +1 (302) 556-2288

Compliance: what to ask any dermatology billing company

Any billing vendor that handles your patients' data is a HIPAA business associate. Get a Business Associate Agreement before they have any access, and check how they limit and log that access.

HHS guidance names billing, claims processing and practice management as business associate work, and subcontractors need their own agreement. The minimum necessary standard limits use to what each task needs. The Security Rule's technical safeguards require access control, audit controls, integrity controls, person or entity authentication and transmission security.

  1. Will you and your subcontractors sign a Business Associate Agreement before any access?
  2. How do you limit access, and can we see the audit log?
  3. Who codes our claims, and what coding credential and dermatology experience do they hold?
  4. How do you decide when modifier 25 is supported?
  5. Which LCDs, billing articles and drug lists do you track for our contractor?
  6. Can we export our data if we leave?

We use role-based access, audit logging and encrypted (HTTPS) connections, and we put a Business Associate Agreement in place before accessing patient data.

Who this is for, and who it is not for

We would rather tell you now than after you sign. Here is where we fit and where we do not.

A good fit if you are

  • Dermatology groups billing visits and procedures on the same day
  • Mohs surgeons who read their own slides
  • Practices with heavy biologic and phototherapy approval volume
  • Practices that sell cosmetic services and keep them off insurance claims
  • Billing companies serving several dermatology clients from one portal

Probably not a fit if you are

  • Practices that want modifier 25 on every visit by default
  • Practices that want a fixed price before any audit
  • Practices looking for promised collection rates; we report measured KPIs instead
  • Groups that need a credentialing module or in-portal real-time eligibility today (coming next)

Expert recommendations from our operations team

What we would do first if we were running your practice's revenue cycle tomorrow.

  1. 01

    Sort cosmetic from medical at booking

    We ask the reason for every lesion visit when it is booked. Cosmetic work is priced first and stays off the insurance claim.

  2. 02

    Write the separate visit so it stands alone

    OIG has audited dermatology same-day visits. We ask providers to document the separate problem apart from the decision to treat.

  3. 03

    Code by lesion, not by visit

    Each lesion gets its own technique, count, site and diagnosis. We check biopsy order and destruction counts before the claim leaves.

  4. 04

    Get the referring biopsy report before Mohs

    We collect the outside pathology report before the surgery date, so no biopsy is repeated without a documented reason.

  5. 05

    Route biologics to the drug benefit on day one

    We check the drug plan and its approval form before the first dose is planned, not after a Part B denial.

  6. 06

    Model the 2027 same-day proposal now

    If CMS finalizes the 50% same-day reduction, we will model your visit-plus-procedure mix against the final rule.

Frequently asked questions

What do dermatology billing services include?

They cover coding support, claim scrubbing, submission, denial management and A/R follow-up for dermatology visits and procedures: biopsies, destructions, excisions, Mohs surgery, phototherapy and pathology. A good service also separates cosmetic from medically necessary care before the visit and checks that each modifier 25 visit is documented. RCM Finder adds front-desk assistants, patient marketing and a claims portal, so the same rules apply from booking to payment.

Can we bill an office visit and a biopsy on the same day?

Yes, when the visit is significant and separately identifiable from the procedure, reported with modifier 25. The decision to do a minor procedure is already included in the procedure's payment, so it does not justify a visit on its own. Different diagnoses are not required, but the record must support both services. CMS has proposed paying one of the two at 50% starting in 2027, so check the final rule.

How do we code several biopsies done with different techniques?

Report one primary biopsy code and add-on codes for the rest. The American Academy of Dermatology explains the order: incisional first, then punch, then tangential. For example, one incisional, one punch and two tangential biopsies are coded 11106, 11105, 11103 and 11103. A biopsy of a lesion you remove at the same visit is included in the removal code.

Do we need an ABN before a cosmetic procedure for a Medicare patient?

No. CMS says an ABN is not required for care Medicare excludes by law, and cosmetic surgery is one of those exclusions. CMS does encourage a voluntary notice so the patient knows they will pay. On a claim, GY marks a statutorily excluded service and GX marks a voluntary notice. Use the mandatory ABN when a normally covered service may be denied as not medically necessary.

Does Medicare Part B pay for biologics like dupilumab?

Usually not. Novitas, a Medicare contractor, lists dupilumab, secukinumab and similar self-injected biologics on its self-administered drug exclusion list, so Part B does not cover them as office drugs. Coverage runs through the patient's drug plan. Part D plans must decide standard coverage requests within 72 hours and expedited requests within 24 hours. Commercial plans set their own prior authorization rules.

Can a Mohs surgeon bill separate pathology codes for the Mohs specimens?

Not for the margin tissue. The Mohs codes already include the surgeon's own pathology review, and Noridian says billing surgical pathology codes on Mohs margin tissue is inappropriate and denies those Mohs claims. A diagnostic biopsy and frozen section before Mohs can be reported separately with the right modifier, and separate, unrelated tissue may be covered with clear documentation. Repairs, grafts and flaps are billed separately. Other Medicare contractors may differ.

No cost, no commitment

Get your free practice audit

Tell us about your practice. A member of our operations team replies within one business day.

  • A review of your recent claims, denials and A/R aging
  • Where your front desk and prior authorizations slow payment
  • A prioritized fix list you keep, whether or not you hire us

Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.

Tell us about your practice

RCMFinder Master Intake Form
AA

About the author: Awais Afzal

Healthcare Operations & Data Analyst, RCM Finder

Awais has spent more than 16 years in healthcare digital marketing and clinical operations management. He builds data-driven revenue cycle blueprints for high-ticket medical practices and leads product development of the RCM Finder portal. More about our team.

How we write: every figure, code and rule on this page was checked against the primary source listed below and independently fact-checked before publishing. We re-review this page every six months. Last reviewed October 12, 2026; next review April 12, 2027.

Sources

  1. Medicare NCCI Policy Manual, Chapter III: Surgery: Integumentary System (CPT 10000-19999) — CMS (2026 (revision date 1/1/2026))
  2. Medicare Claims Processing Manual, Chapter 12: Physicians/Nonphysician Practitioners — CMS (2026 (chapter rev. 13753, May 7, 2026; §30.6.6 text from 2006))
  3. Modifier 25 fact sheet — First Coast Service Options (Medicare contractor) (2026 (dated March 10, 2026))
  4. Transmittal 13015 (CR 13705): G2211 policy update — CMS (via HHS guidance portal) (2024 (December 23, 2024))
  5. Dermatology Providers Generally Met Medicare Requirements for Evaluation and Management Services Performed on Same Day as Minor Surgical Procedures (A-04-21-04083) — HHS Office of Inspector General (2025 (issued November 18, 2025))
  6. Evaluation and Management Services on Same Day as Minor Surgery With No Modifier 25 (OAS-26-04-028) — HHS Office of Inspector General (Work Plan) (2026 (announced March 16, 2026))
  7. Calendar Year (CY) 2026 Medicare Physician Fee Schedule Final Rule (CMS-1832-F) fact sheet — CMS (2025 (October 31, 2025))
  8. Calendar Year (CY) 2027 Medicare Physician Fee Schedule Proposed Rule fact sheet — CMS (2026 (July 14, 2026))
  9. Cracking the Code (new biopsy codes for 2019) — American Academy of Dermatology, Dermatology World (2018 (November 2018))
  10. Web Announcement 1960: skin biopsy code rate correction — Nevada Medicaid (2019 (August 28, 2019))
  11. LCD L35702: Mohs Micrographic Surgery — CMS Medicare Coverage Database (Noridian) (2025 (revision effective 10/23/2025))
  12. Billing and Coding: Mohs Micrographic Surgery (A56514) — CMS Medicare Coverage Database (Noridian) (2025 (revision effective 10/23/2025))
  13. Transmittal 1165 (CR 5457): HCPCS Codes Subject to and Excluded from CLIA Edits — CMS (2007 (January 26, 2007))
  14. NCD 250.4: Treatment of Actinic Keratosis — CMS Medicare Coverage Database (2001 (revision history through 08/2026))
  15. Coding and Billing Guidelines, DERM-008: Removal of Benign Skin Lesions (archived attachment) — CMS Medicare Coverage Database (WPS) (2009 (archived))
  16. CPT 17000, 17003 and 17004 code summaries — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-09)
  17. LCD L34233: Benign Skin Lesion Removal (Excludes Actinic Keratosis, and Mohs) — CMS Medicare Coverage Database (Noridian) (2025 (revision effective 10/23/2025))
  18. Billing and Coding: Benign Skin Lesion Removal (A57161) — CMS Medicare Coverage Database (Noridian) (2026 (revision effective 10/01/2026))
  19. 42 CFR 411.15: Particular services excluded from coverage — eCFR (current (accessed 2026-10-09))
  20. Medicare Claims Processing Manual, Chapter 30: Financial Liability Protections — CMS (accessed 2026-10-09)
  21. Advance Beneficiary Notices (ABNs) — CGS Medicare (Medicare contractor) (2026 (updated 03.19.2026))
  22. Self-Administered Drug Exclusion List (A53127) — CMS Medicare Coverage Database (Novitas) (2026 (revision effective 08/30/2026))
  23. Coverage Determinations (Part D) — CMS (2024 (last modified 09/10/2024))
  24. CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) fact sheet — CMS (2024 (January 17, 2024))
  25. AMA survey: Prior authorization reform pledge falls short with physicians — American Medical Association (2026 (May 13, 2026))
  26. NCD 250.1: Treatment of Psoriasis — CMS Medicare Coverage Database (longstanding (version 1))
  27. Medical Policy 043: Phototherapy and Photochemotherapy for Dermatologic Conditions — Mass General Brigham Health Plan (2025 (March 2025 update))
  28. CPT 96912 code summary — AAPC (secondary; used for plain-language code meaning only) (accessed 2026-10-09)
  29. Modifier 26 (JF Part B) — Noridian Healthcare Solutions (Medicare contractor) (2025 (last updated May 9, 2025))
  30. MLN Matters SE0587 — CMS (2005)
  31. 45 CFR 164.514: Other requirements relating to uses and disclosures of PHI — eCFR (current (accessed 2026-10-09))
  32. 45 CFR 164.508: Uses and disclosures for which an authorization is required — eCFR (current (accessed 2026-10-09))
  33. Use of Online Tracking Technologies by HIPAA Covered Entities and Business Associates — HHS Office for Civil Rights (2024 (reviewed June 26, 2024))
  34. Federal Trade Commission Announces Final Rule Banning Fake Reviews and Testimonials — Federal Trade Commission (2024 (August 14, 2024))
  35. Business Associates — HHS Office for Civil Rights (2026 (content last reviewed July 30, 2026))
  36. Minimum Necessary Requirement — HHS Office for Civil Rights (2013 (content last reviewed July 26, 2013))
  37. 45 CFR 164.312 Technical safeguards — eCFR (current (accessed 2026-10-09))