
Virtual medical assistants for scheduling

Medical Appointment Scheduling Services Done by Virtual Medical Assistants

Trained remote staff book, confirm and recall patients inside your EHR, and check eligibility and authorization before the visit is on the calendar.
  • Works inside your current EHR
  • US practice time zone, every shift
  • Weekly KPI reporting, or on your schedule
Scheduling dashboard for a medical practice showing booked visits, confirmations, waitlist, recall and open authorizations

Quick answer

Medical appointment scheduling services put trained remote staff in charge of your appointment book. Our virtual medical assistants book, confirm and recall patients inside your EHR, checking eligibility, prior authorization and referral requirements before a visit is final, so fewer slots go empty and fewer visits arrive unpaid.

Disclaimer: This page is general educational information about scheduling and front-desk workflows. It is not legal, compliance, coding or billing advice. Payer rules vary by plan and state, and statistics cited are survey or study results from the years stated. Confirm requirements with your payers and compliance advisor.

Why does front-desk scheduling leak revenue?

An empty slot cannot be billed, and a booked visit with the wrong insurance or a missing authorization may not be paid. Scheduling is where both problems start, and it is usually squeezed between phones, check-ins and checkouts.

No-shows are the visible part. In an MGMA Stat poll published in August 2026, 32% of medical groups reported higher patient no-show rates year to date than in 2025, up 5 percentage points from the same poll a year earlier (190 responses). In MGMA's August 2023 poll, 37% reported an increase over 2022 (380 responses), and the 2022 poll had found 49%.
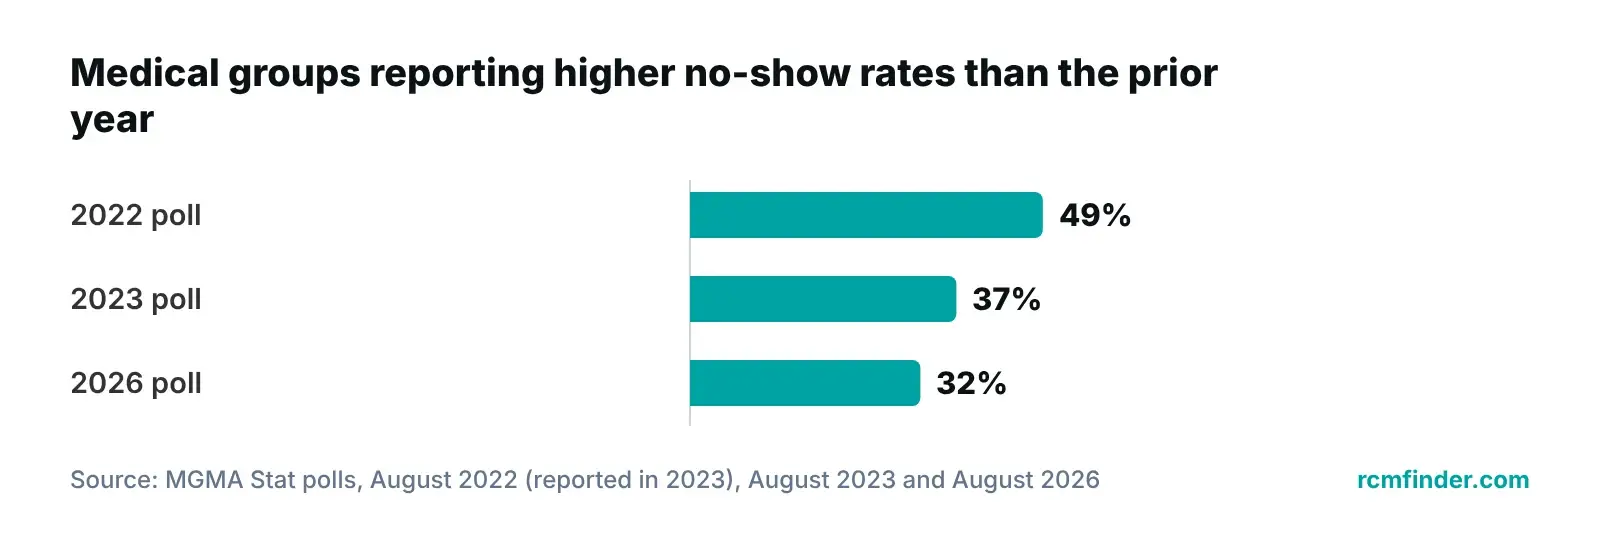
Bar chart of medical groups reporting higher patient no-show rates: 49% in the 2022 poll, 37% in 2023, 32% in 2026
Share of medical groups reporting higher no-show rates than the prior year, from MGMA Stat polls. These are shares of groups, not no-show rates.

Booking choices matter too. A 2024 systematic review in Health Science Reports of no-shows in clinics using open-access scheduling reported, from one included study, no-show rates of 8%, 16% and 22% for lead times of 0-3, 4-6 and 28-30 days. The lead-time figures come from a 2013 before-and-after study. The authors also state that reminders reduce no-shows, but they note that most included studies used before-and-after designs, which are weak evidence of cause, and that some did not evaluate reminders at all.

The other leak is the authorization. The AMA's 2025 survey of 1,000 physicians, released in May 2026, found physicians complete an average of 40 prior authorizations a week, taking about 13 hours of physician and staff time. If nobody checks authorization before the visit is booked, that time is spent after the patient is already on the calendar.

Estimate what an empty slot costs you

Enter your visit volume and average collection into our revenue calculator. It gives you a number to bring to the audit.

Open the Revenue Calculator

What do outsourced medical scheduling services include?

Outsourced medical scheduling means trained remote staff, called virtual medical assistants, run your appointment book for you inside your own EHR. They follow your templates, your rules for each visit type and your escalation steps, and they work on your practice's time zone.

  • Booking and rescheduling: new and returning patients, by phone or from your inbox queue, using your provider templates.
  • Cancellations and waitlist: offering open slots to patients who asked for an earlier date.
  • Confirmations and reminders: contacting patients before the visit, so changes arrive while the slot can still be filled.
  • No-show follow-up and recall: reaching patients who missed a visit or are overdue to return.
  • Intake at booking: demographics, insurance details and reason for visit, captured before the day.
  • Eligibility check: coverage confirmed before the visit. See our patient insurance verification guide.
  • Prior authorization check: flagging visits and procedures that need approval first. See our prior authorization guide.

Assistants do not give clinical advice or triage symptoms. Anything clinical goes to your staff under a script your clinical lead approves. The wider service is described on our virtual medical assistant services page.

A service run by people, not software

This page covers a done-for-you service delivered by named assistants. If you are looking for software that books, reminds and collects intake with little staff involvement, see our automated patient scheduling and intake page. Some practices use both: automation for routine requests, and an assistant for the calls that need judgment.

What does our scheduling workflow check before a visit is booked?

Each booking passes through the same checks, so problems surface while the patient is still on the phone. The table shows the steps and what each one rests on.

Front-desk scheduling workflow, step by step
StepWhat the assistant doesWhat it is based on
Capture intakeRecords demographics, insurance card details and the reason for the visit before the appointmentRCM Finder process
Check eligibilityConfirms active coverage and plan type for the date of serviceRCM Finder process
Check authorizationFlags visits that need prior approval and starts the request before the date is finalAMA 2025 physician survey: 40 authorizations and 13 hours a week on average
Check referralAsks for the referral when the plan requires oneHealthCare.gov and CMS MLN (July 2026): many HMO plans require referrals
Choose the slotApplies your visit type, provider and slot rules, and avoids very long lead times where your calendar allows2024 systematic review: one study found higher no-shows at longer lead times
Confirm and remindContacts the patient before the visit and logs the answer2024 systematic review: authors state reminders reduce no-shows (weak before-after evidence)
Handle no-shows and recallFollows up on misses, offers the waitlist and recalls overdue patientsRCM Finder process

Sources: AMA 2025 Prior Authorization Physician Survey (released May 2026); HealthCare.gov glossary; CMS MLN8659122 (July 2026); Health Science Reports systematic review (2024). Other cells describe RCM Finder's process.

On referrals, HealthCare.gov defines a referral as a written order from your primary care doctor to see a specialist, and notes that in many HMOs, if you do not get one first, the plan may not pay. CMS says patients in HMO-type Medicare Advantage plans also need a referral from their doctor to see a specialist. Plans differ, so we check each one.

Our team keeps one note per visit: what was checked, what is pending and who owns it. Billing sees that note later, which is where the link to front-desk impact on the revenue cycle becomes real.

How medical scheduling differs by specialty

A visit is not the same unit in every specialty. What changes is the length of the slot, the work that must happen before the date and the visits that follow. Slot lengths are set by your clinicians; we follow your templates.

What changes in scheduling by specialty group
SpecialtyWhat changes at bookingWhat we check first
Pain managementProcedure visits such as injections differ from consults, and some need approval before the date.Authorization status before the procedure slot is held
OrthopedicsNew injury visits come with imaging, then pre-operative and post-operative visits tied to a surgery date.Referral, imaging history and the surgery date for follow-ups
CardiologyA consult is often paired with testing, so two bookings must line up.Referral and plan rules for the test, not only the visit
Behavioral healthRecurring sessions, detailed intake and telehealth visits where the clinician's license must cover the patient's state.Patient location and clinician license, per HHS guidance
NeurologyNew patients arrive with records and imaging, and need a longer first slot.Referral, outside records and imaging on file
PediatricsA parent or guardian books, and siblings are often seen together.Guardian contact and consent details
OphthalmologyA single visit can include testing and dilation, so the sequence in one visit matters.Visit type and any testing that needs a separate slot

Sources: HHS Telehealth.HHS.gov licensure pages (2025) for patient-location licensure; HealthCare.gov and CMS MLN (2026) for referral rules. Other rows are operational logic and vary by practice.

Browse the specialties hub for the billing patterns that sit behind each specialty's front desk.

For telehealth, HHS states that a telehealth appointment occurs in the state where the patient is located at that time. HHS's behavioral health guidance advises checking both states' licensing boards. Our assistants ask for patient location at booking and pass it to your team.

In-house, outsourced assistants, automation or an answering service?

The right model depends on call volume, visit complexity and how much judgment a booking needs. The table compares four common choices honestly, including where our own service is not the answer.

Four ways to run medical appointment scheduling
QuestionIn-house front deskOutsourced assistants (VMAs)Scheduling automationAnswering service
Best forSmall practices with calm phonesPractices whose phones and checks outrun staffHigh volume of routine bookingsAfter-hours message taking
Handles judgment callsYesYes, within your scriptsLimitedLimited
Checks eligibility and authorizationIf staff have timeYes, part of the workflowDepends on the buildUsually no
Works in your EHRYesYesDepends on integrationUsually no
Main trade-offStaff time and turnoverNeeds clear scripts and scopeRare cases still need a personMessages, not booked visits

How does our scheduling service work?

It starts with a free practice audit of your schedule, then written scripts, a Business Associate Agreement and a staged go-live. Pricing is quoted after the audit, based on volume and scope.

  1. 1

    Free practice audit

    We review your schedule templates, no-show and cancellation patterns, call handling and how eligibility and authorization are checked today. You get a list of gaps.

  2. 2

    Written scope and scripts

    We document the visit types, rules and escalation steps. Your clinical lead approves anything touching symptoms or urgency.

  3. 3

    Business Associate Agreement and access

    We put a Business Associate Agreement in place before accessing patient data. Each assistant gets an individual login to your EHR, limited to the scheduling queues.

  4. 4

    Training on your templates

    Assistants learn your providers, visit types and payer mix, then shadow your front desk before taking calls alone.

  5. 5

    Staged go-live

    We begin with one queue, such as new-patient booking or recall, and add the next when it runs steadily.

  6. 6

    Weekly review

    Each week you see bookings, reschedules, no-show follow-ups and open authorizations, and we adjust rules with you.
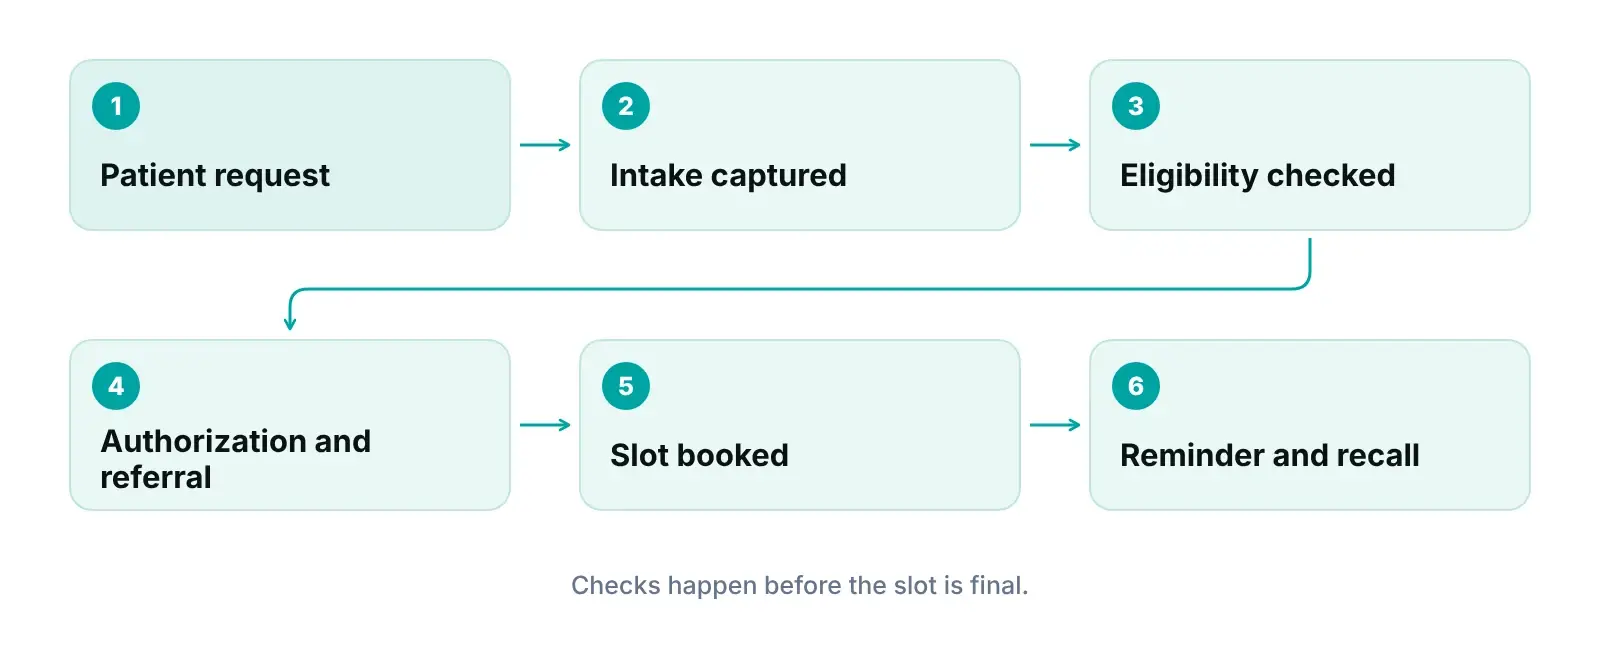
Diagram of medical appointment booking workflow: call, intake, eligibility, authorization check, booked slot, reminder
A booking passes the same checks every time.

Start with a free practice audit

We review your templates, no-show patterns and front-desk checks, then show where bookings are leaking.

Get a Free Practice Audit

What about scheduling inside the RCM Finder portal?

Appointment scheduling with a calendar and day view in our practice management portal is in early access. It is not live for daily use, and we do not promise a release date.

Where scheduling fits in our four pillars

Scheduling connects marketing and billing. It turns a new patient inquiry into a visit that can be billed cleanly.

Pillar 1 · Healthcare Marketing

Healthcare Marketing: answer demand the day it arrives

Campaigns fill the phones. Scheduling decides how many of those calls become booked visits.

  • Patient source recorded at booking
  • Calls turned into appointments
  • Insurance captured up front
Explore Healthcare Marketing
Pillar 2 · Virtual Medical Assistants

Virtual Medical Assistants: this page's service

Scheduling, eligibility checks, prior authorizations and intake, done by named remote staff in your EHR.

  • Your time zone, every shift
  • Scripts approved by your clinical lead
  • Weekly activity reporting
Explore Virtual Medical Assistants
Pillar 3 · End-to-End RCM

End-to-End RCM: visits that arrive claim-ready

Clean intake and authorization notes mean fewer avoidable denials downstream.

  • Eligibility notes passed to billing
  • Authorization status on the visit
  • Denials traced to their source
Explore End-to-End RCM
Pillar 4 · Practice Management System

Practice Management System: scheduling in early access

The portal tracks claims today. Scheduling with a calendar and day view is in early access.

  • Claim pipeline by stage
  • Role-based access and audit log
  • Scheduling: early access
Explore Practice Management System

What should you ask any scheduling vendor about HIPAA and quality?

Ask for a Business Associate Agreement first, then how staff access is limited and how calls are reviewed. Appointment details are protected health information, so a vendor handling them is generally a business associate.

HHS guidance lists billing and practice management among business associate activities, and its examples include a third-party AI chatbot on a provider's patient portal that handles appointment scheduling. It requires satisfactory assurances, in the form of a contract, before protected health information is shared. HHS's minimum necessary guidance asks practices to define who needs access to which information. Be wary of any "HIPAA certified" claim: HHS does not endorse or recognize private Security Rule certifications.

  1. Will you sign a Business Associate Agreement before accessing patient data?
  2. Does every assistant have a unique login to our EHR, limited to scheduling queues?
  3. Who writes and approves the scripts, and what is escalated to our staff?
  4. Are assistants on our time zone, and what are the hours of coverage?
  5. How are calls and bookings reviewed for quality?
  6. What do you report each week, and can we see open items?
  7. What do you not do, such as clinical advice or triage?

At RCM Finder, we put a Business Associate Agreement in place before accessing patient data. Our team works inside your existing EHR, for example PrognoCIS, eClinicalWorks or athenahealth, with role-based access and audit logging. We claim no certifications or EHR partnerships.

Talk through your front desk with our team

Tell us how your phones and schedule run today. We will say what an assistant can take on and what should stay with your staff.

Talk to Our Team

Who this is for, and who it is not for

We would rather tell you now than after you sign. Here is where we fit and where we do not.

A good fit if you are

  • Practices whose phones and bookings outrun the front desk.
  • Specialty practices where visits need authorization or referral checks.
  • Groups that want scheduling, eligibility and intake handled by one team.
  • Practices that need coverage on their own time zone.
  • Owners who want weekly reporting on bookings and no-show follow-up.

Probably not a fit if you are

  • Practices that need a live online booking calendar today; portal scheduling is in early access.
  • Practices wanting software to book with no staff involved; see our automation page.
  • Buyers who expect clinical triage by non-clinical staff.
  • Practices that cannot share templates, scripts and EHR access with an outside team.

Expert recommendations from our operations team

What we would do first if we were running your practice's revenue cycle tomorrow.

  1. 01

    Check authorization before you hold the slot

    If an approval is needed, start it first. We flag those visits at booking so billing does not discover the gap after the visit.

  2. 02

    Write the scripts down and approve them

    Your clinical lead should sign off on what assistants say about symptoms or urgency. We build that into scope.

  3. 03

    Track no-shows by visit type and provider

    One average hides the problem. We report by visit type, provider and booking lead time.

  4. 04

    Keep waitlist and recall lists current

    A waitlist only fills a cancellation if someone calls the right patient quickly. We work the list daily.

  5. 05

    Record patient location for telehealth

    Because a telehealth visit takes place where the patient is, we capture location at booking.

  6. 06

    Start with one queue

    Pick the queue that hurts most, such as new-patient booking or recall, and add the next once it runs steadily.

Frequently asked questions

What are medical appointment scheduling services?

They are services where trained remote staff manage a practice's appointment book: booking, rescheduling, cancellations, reminders, recall and intake. Ours are delivered by virtual medical assistants who work inside your EHR, check eligibility and authorization at booking and follow your scripts. They do not give clinical advice. Pricing is quoted after a free practice audit.

How is this different from your automated patient scheduling?

This is a done-for-you service delivered by people who handle calls, checks and follow-up. Our automated patient scheduling page covers software that books, reminds and collects intake with less staff involvement. Many practices pair them, using automation for routine requests and assistants for judgment calls. We help you choose during the free audit.

Can assistants verify insurance and prior authorization when they book?

Yes, eligibility checks and prior authorization checks are part of our assistant service. They confirm coverage, flag visits that need approval and start the request before the date is final. Payers differ, and authorization decisions stay with the payer. We record what was checked so billing sees it later.

Does this reduce no-shows?

We make no outcome promises. A 2024 systematic review's authors state that reminders reduce no-shows, though most studies it covered were before-and-after designs and some did not evaluate reminders, and one study found no-shows rose with longer lead times. We use reminders, lead-time awareness, waitlists and recall, and report no-shows weekly so you can judge the effect.

Do you offer scheduling inside your practice management portal?

Not yet. Appointment scheduling with a calendar and day view is in early access and is not live for daily use. Today our assistants schedule inside the EHR you already use. You can join the early-access list through the free audit form, and we do not promise release dates.

Which EHRs do your assistants work in?

Our team works inside your existing EHR, for example PrognoCIS, eClinicalWorks or athenahealth, using individual logins limited to scheduling queues. We do not claim an official partnership with any EHR vendor. During the free audit we confirm how your EHR handles templates, reminders and inbox queues, and which of those tasks our assistants take first.

No cost, no commitment

Get your free practice audit

Tell us about your practice. A member of our operations team replies within one business day.

  • A review of your recent claims, denials and A/R aging
  • Where your front desk and prior authorizations slow payment
  • A prioritized fix list you keep, whether or not you hire us

Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.

Tell us about your practice

RCMFinder Master Intake Form
AA

About the author: Awais Afzal

Healthcare Operations & Data Analyst, RCM Finder

Awais has spent more than 16 years in healthcare digital marketing and clinical operations management. He builds data-driven revenue cycle blueprints for high-ticket medical practices and leads product development of the RCM Finder portal. More about our team.

How we write: every figure, code and rule on this page was checked against the primary source listed below and independently fact-checked before publishing. We re-review this page every six months. Last reviewed October 12, 2026; next review April 12, 2027.

Sources

  1. MGMA Stat: patient no-show rates (poll of Aug. 11, 2026) — MGMA (2026)
  2. MGMA Stat: patient no-shows holding steady at medical groups in 2023 — MGMA (2023)
  3. Evaluation of no-show rate in outpatient clinics with open access scheduling system: a systematic review — Health Science Reports (PMC) (2024)
  4. AMA survey: prior authorization reform pledge — American Medical Association (2026)
  5. Referral (glossary) — HealthCare.gov (2026)
  6. Original Medicare vs Medicare Advantage (MLN8659122) — CMS (2026)
  7. Licensure compacts — HHS Telehealth.HHS.gov (2025)
  8. Licensure for behavioral health — HHS Telehealth.HHS.gov (2025)
  9. Business Associates guidance — HHS (2026)
  10. Minimum Necessary Requirement — HHS (2013)
  11. Are we required to certify our organization's compliance with the standards? — HHS (2010)