
Global-period coding, co-surgeon and assistant claims, spine prior authorization, referral marketing and a claims portal for neurosurgery practices, built on CMS rules and your payers' own policies.
By Awais Afzal | Healthcare Operations & Data Analyst
Published October 12, 2026 · Last reviewed October 12, 2026 · Next review April 12, 2027
Quick answer
Neurosurgery billing services code and collect for spine and cranial surgery: 90-day global periods, co-surgeon and assistant claims, multi-level add-on codes, neuromonitoring, and prior authorization from Medicare programs and commercial benefit managers. RCM Finder pairs that billing with front-desk assistants, referral marketing and a claims portal, starting with a free practice audit.
On this page
Neurosurgery billing is different because each case is a package. One spine or cranial surgery can bring a 92-day global period, a second surgeon or an assistant, several add-on codes and prior authorization from more than one program.
CMS's Global Surgery Booklet (December 2025) sets the major-surgery global period at the day before, the day of and 90 days after surgery. The fee covers pre-op visits after the decision to operate, the operation, routine post-op care and complications that do not need a return to the operating room. The decision visit, unrelated visits, diagnostic tests and a return to the OR are billed separately, with the right modifier where one applies.
Spine patients often move between pain management, neurology and surgery, and the same coverage rules follow them. We build our billing pipeline around how claims actually move through a practice: registration, charge entry, submission, payment and follow-up. For neurosurgery, we add the global-period, multi-surgeon and add-on checks on this page. See also our pain management billing services.
CMS's CY 2026 fee schedule final rule (October 31, 2025) set a $33.40 conversion factor for clinicians who are not qualifying APM participants and a -2.5% efficiency adjustment to work RVUs of non-time-based services; E/M and other time-based codes are exempt. The CY 2027 proposed rule (July 14, 2026) would pay a same-day office or outpatient E/M and a 0-, 10- or 90-day global procedure by the same physician or practice at 100% for the most expensive service and 50% for the others. Check the final rule before budgeting.
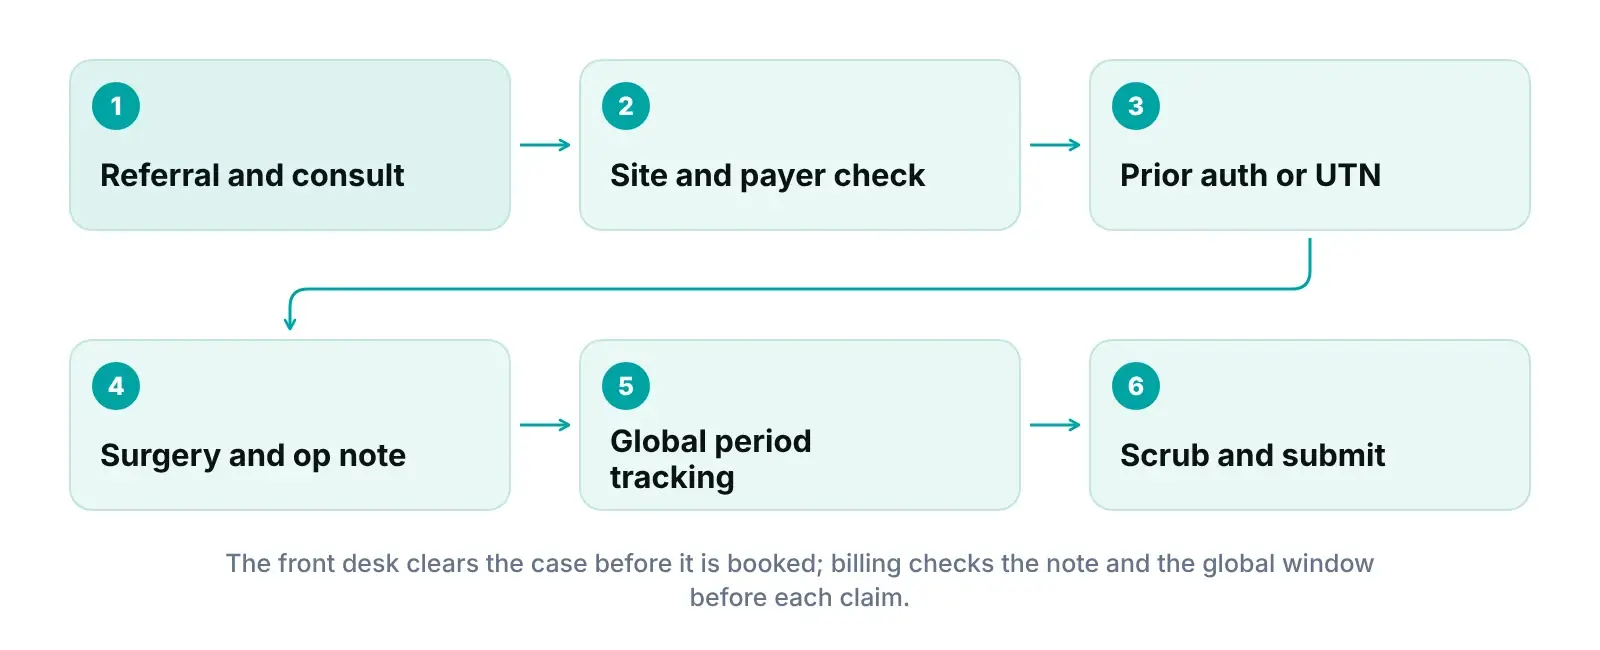
A neurosurgery practice needs steady referrals, a front desk that clears each case before it reaches the OR schedule, billing that codes the whole surgical package, and software that shows every claim. Revenue leaks at the handoffs, so we run all four pillars against one set of payer rules.
Our healthcare digital marketing builds two referral paths: physicians who send spine and cranial cases, and patients who search after a diagnosis. We use local SEO, Google Ads and reputation work.
Our virtual medical assistants run your front desk on your practice's time zone. They verify eligibility, collect imaging and conservative care history, and start prior authorizations with the right program or benefit manager.
Our end-to-end neurosurgery revenue cycle management covers coding support, claim scrubbing, denial management and A/R follow-up, with added checks for global-period modifiers, add-on pairing, and co-surgeon and assistant rules.
Our practice management system tracks every claim by stage, applies specialty-aware billing logic to each claim, checks data completeness before submission and flags payments below the expected amount.
See where your surgical claims stall
We review recent surgical claims, global-period denials and authorization logs, then show what to fix first. Pricing is quoted after the audit.
Most neurosurgery denials trace to a few rules: a missing authorization, an add-on without its primary, decompression billed with a fusion at the same level, a second surgeon on a code that does not allow one, or monitoring billed by the surgeon. Codes are examples in our own words (the AMA owns CPT descriptors); check the current code set and the 2026 NCCI Policy Manual.
| Procedure family | Code examples (our wording) | Billing rule to know | Frequent denial trigger |
|---|---|---|---|
| Anterior cervical fusion | 22551 (fusion with disc removal, first interspace below C2); add-on 22552; 22554 (fusion outside the OPD list) | Hospital OPD cases with 22551 or 22552 need a Medicare affirmation; 22554 is in WISeR | No affirmation: hospital, surgeon and anesthesia claims denied |
| Lumbar fusion | 22630, 22633 (first interspace, by technique); add-ons 22632, 22634 | One primary, then an add-on per added interspace | 63042 or 63047 with 22630 or 22633 at the same interspace |
| Lumbar decompression | 63030 + add-on 63035 (laminotomy); 63047 + add-on 63048 (laminectomy) | Each add-on only with its own primary | Add-on sent alone; laminotomy and laminectomy on one vertebra |
| Instrumentation and bone graft | 22840 to 22847 (instrumentation); 22853, 22854 (interbody devices); 20931, 20937, 20938 (graft) | One instrumentation code per skin incision; built-in device anchoring not billed | Graft codes billed per level, not once per procedure |
| Spinal cord stimulator | 63650 (percutaneous electrodes); 63685 (generator insertion or replacement); 63688 (revision or removal) | 63650 in a hospital OPD needs prior authorization | Replacement billed when the same generator was reinserted |
| Cranial surgery | 61304, 61305 (exploration); 61781 to 61783 (navigation add-ons); 69990 (microscope) | Flap replacement and dural repair are included | Burr hole at the same site; 69990 outside listed ranges |
| Neuromonitoring | 95940 (in the OR, per 15 minutes); G0453 (Medicare remote, one patient, per 15 minutes) | Billed only by a provider other than the surgeon | Surgeon bills it; 95941 sent to a payer that takes only G0453 |
| Two surgeons or an assistant | 62 (co-surgeons); 80, 81, 82 (assisting physician); AS (PA, NP, CNS) | Co-surgeon indicator 1 or 2; both bill the same code with 62 | 62 on one claim only; assistant on a code with indicator 1 |
Sources: CMS OPD prior authorization code list and FAQ (2024); CMS WISeR Operational Guide v7.0 (2026); CMS NCCI Policy Manual 2026, Chapters IV and VIII; CMS remote IONM FAQ (2020); Highmark RP-077 (2026); Noridian (2025); First Coast (2024); AAPC code summaries. Rules vary by MAC and payer.
For diagnosis coding, see our guides to ICD-10 codes for back pain and neck pain ICD-10 coding.
The NCCI musculoskeletal chapter says to report one primary code for contiguous levels and an add-on for each added level. A second primary code may be reported for a noncontiguous region reached through a separate incision. Graft codes 20931, 20937 and 20938 take one unit per operative procedure. CMS's add-on code edits page says add-ons are rarely payable alone and generally carry the ZZZ global, tied to the primary code.
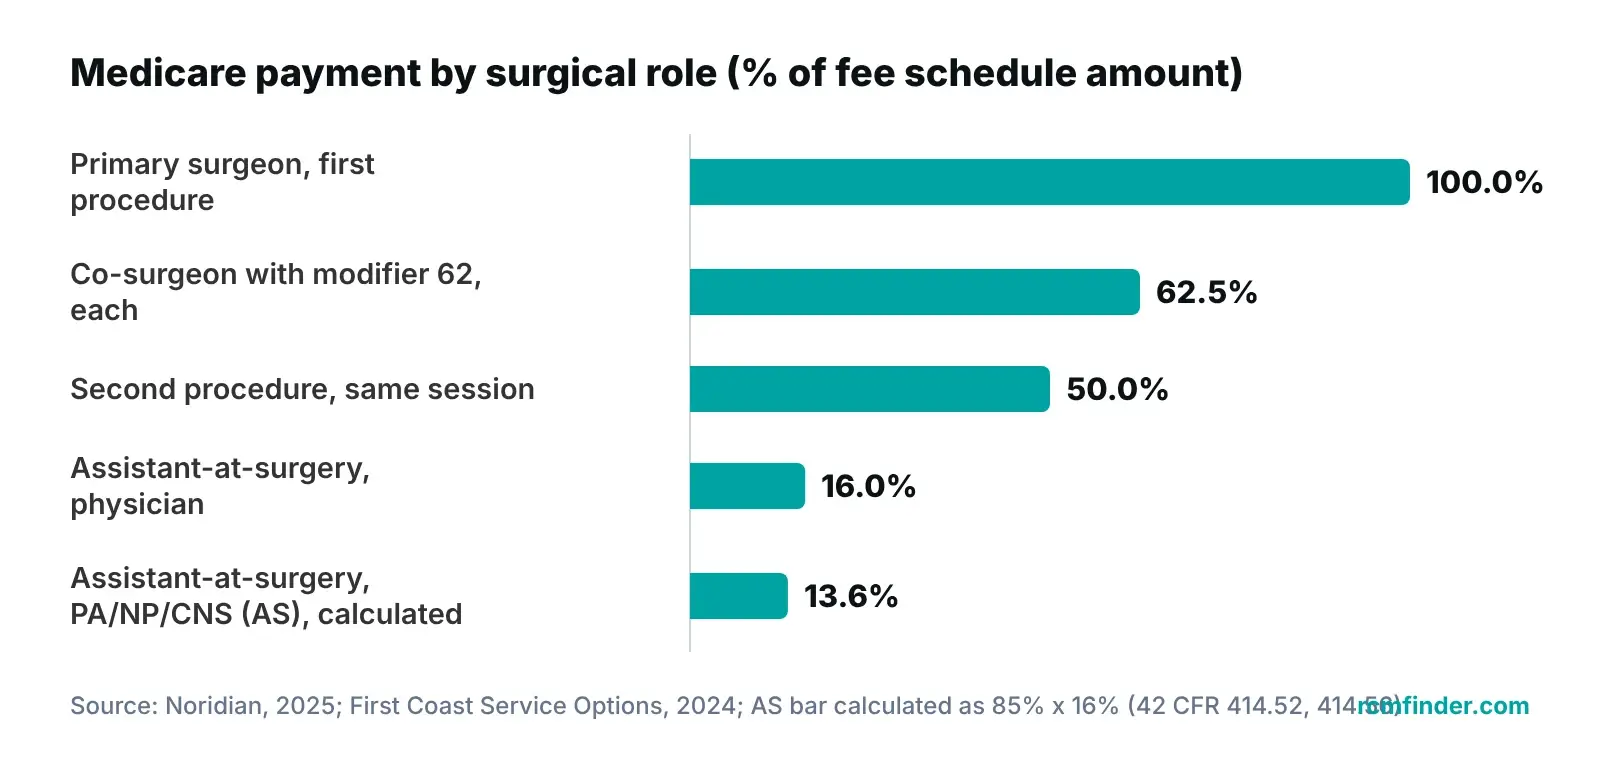
Each code's fee schedule indicators decide who can be paid. Per First Coast, a Medicare contractor, co-surgeon indicator 0 means not permitted, 1 means permitted with documentation and 2 means permitted. Assistant indicator 1 means no payment and 2 means payment is allowed. Noridian pays co-surgeons 62.5% each when both bill the same code with 62, physicians who assist 16%, and PAs, NPs or clinical nurse specialists billing with AS 85% of that. CMS's claims processing manual bars assistant payment where physicians assist in fewer than 5% of cases nationally.
The NCCI nervous system chapter treats 95940, 95941 and G0453 as part of the surgeon's global package, so only a different provider who monitors may bill them. For Medicare, CMS's remote monitoring FAQ (2020) describes G0453 as one patient at a time, in 15-minute units, up to four an hour. Highmark policy RP-077 (2026) does not pay 95941 and asks for G0453.
A neurosurgery global package covers the day before surgery, the surgery and 90 days of routine follow-up. Anything outside routine care needs the right modifier and a note that supports it. CMS's Global Surgery Booklet lists them:
Since January 1, 2025, CMS has applied modifier 54 to every 90-day package when the surgeon expects to furnish only the surgery, even with an informal transfer of care. The CY 2025 final rule also created add-on G0559 for post-op visits by a practitioner who did not operate. See our guides to modifier 79, modifiers 25 vs 59 and co-managed post-op care.
Check the site of service and the patient's state before the code. For Original Medicare, hospital outpatient cervical fusion and spinal neurostimulator electrodes need prior authorization, and six states add more under WISeR. Commercial and Medicare Advantage plans keep their own lists, often run by a benefit manager.
Under CMS's hospital outpatient prior authorization program, cervical fusion with disc removal (22551, 22552) and implanted spinal neurostimulators have needed approval since July 1, 2021; the code list now shows 63650 for that group. The OPD FAQ (November 2024) says unaffirmed claims are denied, along with related physician and anesthesia claims. Physicians may submit for the hospital, an affirmation lasts 120 days, and ASCs and offices are outside the program.
CMS's WISeR model (2026 to 2031) covers Original Medicare in Arizona, New Jersey, Ohio, Oklahoma, Texas and Washington. Its operational guide (version 7.0, July 2026) includes cervical fusion 22554, permanent spinal cord stimulators, initial vagus nerve stimulator implants, trigeminal nerve lesioning and vertebral augmentation; deep brain stimulation is delayed. In hospitals and ASCs, WISeR reviews the facility claim, not the surgeon's.
Every MAC has a cervical fusion LCD, as UnitedHealthcare’s Medicare Advantage spine policy lists. For radiculopathy, CGS L39741 and Novitas L39793 require arm pain of 4 or more for at least 12 weeks despite conservative care, with matching imaging; other MACs may differ. Commercial plans often delegate review: in an April 2024 FAQ, HMSA's benefit manager, Evolent, reviewed non-emergent spine surgery in hospitals and ASCs.
Under CMS-0057-F, Medicare Advantage, Medicaid and CHIP plans must decide standard requests within 7 calendar days and expedited ones within 72 hours. In the AMA’s 2025 survey (released May 2026), physicians averaged 40 prior authorizations and 13 hours of physician and staff time a week. See our prior authorization guide and ASC vs HOPD billing guide.
| Payer rule | Source | What the VMA checks |
|---|---|---|
| OPD cervical fusion (22551, 22552) and spinal neurostimulator electrodes (63650) need a provisional affirmation | CMS OPD program, since July 1, 2021 | Site of service; affirmation and UTN logged; surgery inside the 120-day window |
| OPD decisions: 7 calendar days standard, 2 business days expedited | CMS OPD FAQ (2024) | Request and due dates logged |
| WISeR states: cervical fusion 22554, permanent spinal cord stimulators, initial vagus nerve stimulator implants, trigeminal lesioning | CMS WISeR guide v7.0 (2026) | Patient's state; request sent or pre-payment review chosen; UTN on the claim |
| Cervical radiculopathy fusion: arm pain 4+ for 12+ weeks, failed conservative care, matching imaging | CGS L39741; Novitas L39793; Noridian request checklist | Exam, pain history, daily-living limits, imaging and dated conservative care |
| Benefit managers review spine surgery in hospitals and ASCs; approval windows vary (90 days in one FAQ, 30 days for outpatient cases in another) | Evolent FAQs for HMSA (2024) and BlueChoice (undated), examples | Plan's delegate; most complex procedure as primary; window vs OR date |
| MA, Medicaid and CHIP: 72 hours expedited, 7 days standard, specific denial reason | CMS-0057-F, from January 1, 2026 | Due date tracked; denial reason saved for appeal |
Sources: CMS OPD program page, code list and FAQ (2024); CMS WISeR Operational Guide v7.0 (2026); CMS Medicare Coverage Database (CGS L39741, Novitas L39793); Noridian (2025); Evolent FAQs for HMSA (2024) and BlueChoice (undated); CMS-0057-F fact sheet (2024). Always check the member's current plan.
Estimate what a delayed or denied case costs
Model how denials and slow A/R affect a surgical practice, then bring the numbers to your audit.
Neurosurgery growth usually comes from referring physicians and from patients who search after a diagnosis. Build for both, and keep website tracking within HIPAA.
We build referral pages for pain management, neurology, primary care and physical therapy offices that list what to send: imaging, conservative care history and the reason for referral. Patient pages explain when surgery is considered, so fewer consults fail coverage criteria. HHS tracking guidance says tools on appointment pages can collect protected health information and a cookie banner is not a HIPAA authorization; a June 2024 court order vacated part of it. We keep tracking off forms unless the vendor signs a BAA.
Stay in-house if you have experienced surgical coders and front-desk time for authorizations. Use a billing-only vendor if claims are your only gap. Choose a combined partner when problems start at scheduling and end at the claim.
| Job | In-house team | Billing-only vendor | Four-pillar partner (RCM Finder) |
|---|---|---|---|
| Spine prior authorization | Surgical scheduler, between calls | Usually left to the practice | VMA starts each request and tracks it to a decision |
| Global-period visits and procedures | Depends on one coder | Fixed on the claim, after the fact | Calendar per patient; modifiers checked before submission |
| Co-surgeon and assistant claims | Each office bills its own part | Varies; ask how indicators are checked | Indicators checked at booking; payments compared with expected amounts |
| Add-on and level coding | Coder reads the operative note | Vendor coders and scrubber | RCM coders plus portal completeness checks |
| Referral growth | A separate agency, or nobody | Not included | Marketing pillar tied to booked consults |
| Cost structure | Salaries, benefits, turnover | Varies; ask how fees are set | Quoted after a free practice audit |
We will tell you in the audit if you need only one pillar; each can be contracted separately.
We start with a free audit and change nothing until you see the findings.
We review recent surgical claims, global-period denials and authorization logs, and give you a prioritized fix list.
We put a Business Associate Agreement in place before accessing patient data, then set role-based access in your EHR (for example PrognoCIS, eClinicalWorks or athenahealth).
We map each surgeon's sites, your MACs, any WISeR exposure and your plans' benefit managers into a checklist and portal workflow rules.
VMAs start authorizations on your time zone. The RCM team codes, scrubs, submits and works denials and A/R.
Each week we review denials by reason, A/R days, cases cleared before surgery and underpayments.
Talk through your neurosurgery workflow
Tell us your sites, case mix and hardest payer. We will tell you honestly whether we fit.
Any vendor that handles your claims is a HIPAA business associate. Get a Business Associate Agreement before any access, then check how access is limited and logged.
HHS names billing and claims processing as business associate work, and subcontractors need their own agreement. The minimum necessary standard limits uses to what each task needs. The Security Rule's technical safeguards require access control, audit controls, integrity controls, person or entity authentication and transmission security.
We use role-based access, audit logging and encrypted (HTTPS) connections, and we put a Business Associate Agreement in place before accessing patient data. For your side, use our HIPAA compliance checklist for medical practices.
We would rather tell you now than after you sign. Here is where we fit and where we do not.
A good fit if you are
Probably not a fit if you are
What we would do first if we were running your practice's revenue cycle tomorrow.
Hospital outpatient, ASC and WISeR-state fusions follow different prior authorization paths. We confirm site and state before the code.
LCDs and benefit managers want symptom duration, pain scores, imaging and dated conservative care. We collect it at the first visit.
Each add-on needs its primary code, contiguous levels use one primary, and graft codes carry one unit.
We check co-surgeon and assistant indicators before surgery, so the note explains the need.
We check every visit and procedure in the 92 days and choose 24, 58, 78 or 79 from the operative note.
We confirm who bills neuromonitoring, which code each payer accepts and that recorded times do not overlap.
They cover coding support, claim scrubbing, submission, denial management and A/R follow-up for spine and cranial surgery. A good service also tracks 90-day global periods, applies co-surgeon and assistant rules, pairs add-on codes with their primary codes and confirms prior authorization before the case is scheduled. RCM Finder adds front-desk assistants, referral marketing and a claims portal, so one team owns the process from referral to payment.
For major surgery, Medicare's global period runs 92 days: the day before surgery, the day of surgery and 90 days after. Routine post-op visits and complications that do not need a return to the operating room are included. The visit where you decide to operate (modifier 57), unrelated visits (24), staged procedures (58), returns to the OR (78) and unrelated procedures (79) can be billed with the right modifier and documentation.
Use 62 when two surgeons of different specialties work on the same patient in the same session, each using their own skills, and the code's co-surgeon indicator is 1 or 2. Both bill the same code with 62, and Medicare pays each 62.5%. Use 80, 81 or 82 when a physician assists; Medicare pays 16%. A PA, NP or clinical nurse specialist uses AS and is paid 85% of that amount.
Only in certain settings and states. Since July 1, 2021, hospital outpatient departments have needed a provisional affirmation for cervical fusion with disc removal (22551, 22552) and percutaneous spinal neurostimulator electrodes (63650). In Arizona, New Jersey, Ohio, Oklahoma, Texas and Washington, the WISeR model adds services such as cervical fusion code 22554 and permanent spinal cord stimulator implants. Medicare Advantage and commercial plans set their own rules.
No. CMS's NCCI manual treats neuromonitoring as part of the surgeon's global package, so 95940, 95941 and G0453 can be billed only by a different provider who performs the monitoring. For Medicare, remote monitoring uses G0453, billed per patient in 15-minute units for undivided attention to one patient. Some commercial plans, such as Highmark, do not pay 95941 and ask for G0453 instead.
Yes. Our team works inside your existing EHR, for example PrognoCIS, eClinicalWorks or athenahealth, and we put a Business Associate Agreement in place before accessing patient data. Pricing depends on your case mix, claim volume, sites of service and which of the four pillars you need, so we quote it after a free practice audit rather than publishing a flat rate.
Tell us about your practice. A member of our operations team replies within one business day.
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Tell us about your practice
About the author: Awais Afzal
Healthcare Operations & Data Analyst, RCM Finder
Awais has spent more than 16 years in healthcare digital marketing and clinical operations management. He builds data-driven revenue cycle blueprints for high-ticket medical practices and leads product development of the RCM Finder portal. More about our team.
How we write: every figure, code and rule on this page was checked against the primary source listed below and independently fact-checked before publishing. We re-review this page every six months. Last reviewed October 12, 2026; next review April 12, 2027.
We use cookies to understand how our site is used and to measure our advertising. You can accept or reject non-essential cookies. See our Privacy Policy.