
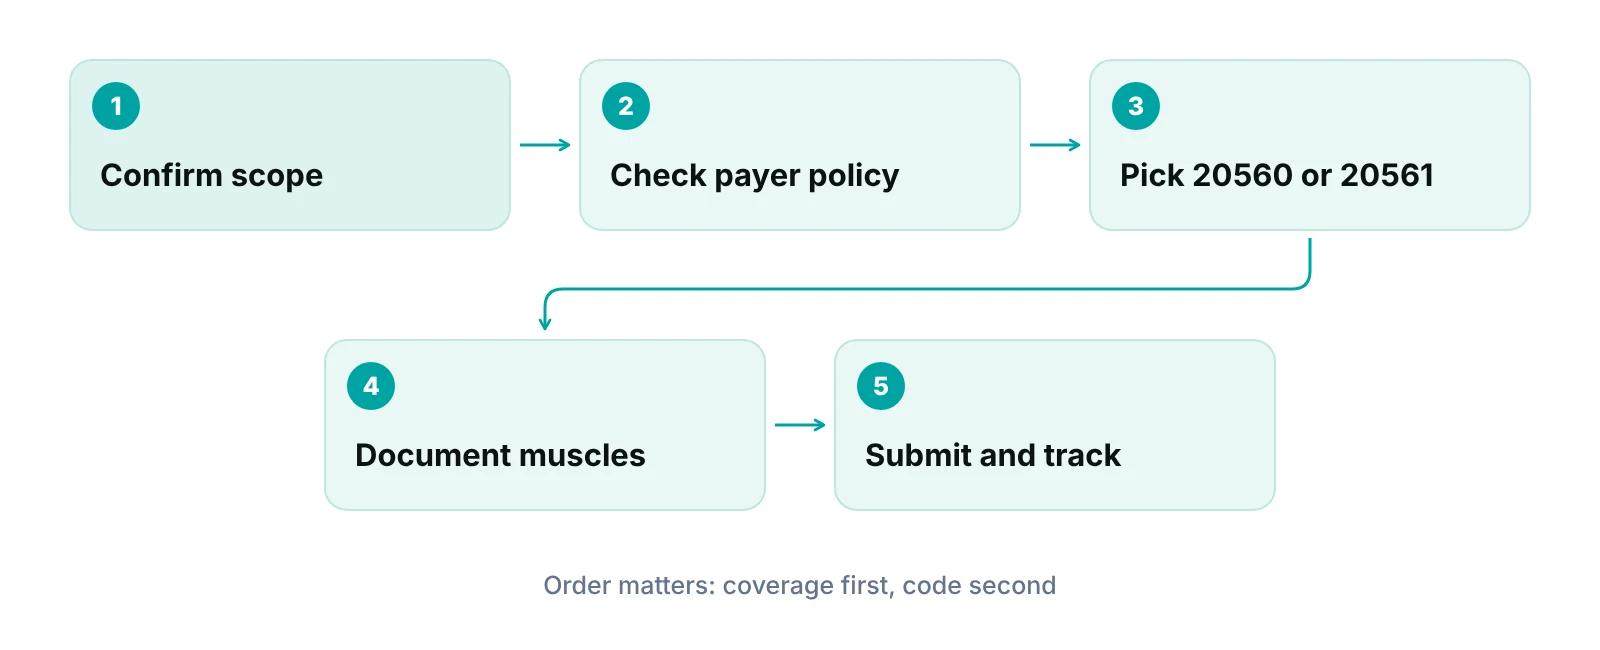
Dry needling billing uses CPT 20560 for one or two muscles and CPT 20561 for three or more. Medicare's national coverage decision excludes dry needling outside chronic low back pain, and commercial payers set their own policies, so confirm each payer's rule before you submit.
Most dry needling denials start before the claim is built: nobody checked the payer’s policy, or the note never said how many muscles were treated. This guide reflects sources we read on October 14, 2026, and it is written for practice owners and billing leads, not for clinical decisions. Our earlier version contained statistics and a cash-discount tip we could not support, so we removed them.
Key takeaways
- CPT 20560 covers one or two muscles and 20561 covers three or more; the muscle count picks the code.
- Medicare NCD 30.3.3 treats dry needling as non-covered for any condition other than chronic low back pain.
- Commercial payers decide by plan; the Medica policy we read calls it investigative and not covered.
- Check the payer policy before billing, not after the denial.
- Do not build a cash-discount policy without advice from your compliance advisor.
What do CPT 20560 and 20561 actually cover?
CPT 20560 is needle insertion without injection into one or two muscles. CPT 20561 is the same service for three or more muscles. The count of muscles treated picks the code. Minutes do not. Both codes were new for 2020, per AAPM&R’s 2020 fee schedule summary and APTA’s February 2020 compliance column.
| Code | What it describes (our wording) | What decides the code | What to document |
|---|---|---|---|
| 20560 | Needle insertion without injection, one or two muscles | Number of muscles treated in the session | Which muscles, and that the count is one or two |
| 20561 | Needle insertion without injection, three or more muscles | Number of muscles treated in the session | Which muscles, and that the count is three or more |
| Neither | Injection of a substance, or acupuncture codes | Not dry needling as these codes define it | Use a different code family and check the payer’s rule for it |
Source: AAPM&R (2019), APTA (2020), CMS MLN Matters MM13288 (2023). Descriptions are paraphrased; CPT is a copyrighted code set.
Pick one code per session, not both. The muscle count should be written in the note by the clinician who did the work, so the biller is never guessing. If your team already bills therapy visits, our physical therapy CPT codes guide shows where these two codes sit next to the usual treatment codes.
Does Medicare pay for dry needling?
For most dry needling, no. CMS’s national coverage determination 30.3.3 states that all types of acupuncture, including dry needling, for any condition other than chronic low back pain are non-covered by Medicare. The rule took effect for services on or after January 21, 2020, per the Medicare Coverage Database entry for NCD 30.3.3.
That corrects a common explanation. Medicare did not leave dry needling uncovered because a coverage decision was missing. It has a national coverage decision that excludes it outside chronic low back pain. CMS also said in the 2020 fee schedule rulemaking that these codes were considered non-covered, while still assigning payment values, per AAPM&R’s summary of the final rule. Private payers could use those values when deciding what to pay.
| Question | What the CMS source says | What it means at the front desk |
|---|---|---|
| Is dry needling covered for most conditions? | NCD 30.3.3: non-covered for any condition other than chronic low back pain | Expect denial for a typical myofascial pain visit |
| Is there a covered exception? | Acupuncture for chronic low back pain is covered under set conditions, including pain of 12 weeks or longer and up to 12 visits in 90 days | Check whether the patient’s diagnosis and visit count fit before assuming either way |
| Who may furnish the covered service? | The NCD lists physicians, PAs, NPs and CNSs, and auxiliary personnel meeting its conditions. It does not list physical therapists | Do not assume a PT can bill Medicare for the chronic low back pain benefit; confirm with your MAC |
| Can dry needling and acupuncture share a date of service? | MLN Matters MM13288: dry needling and acupuncture are disallowed on the same date of service | Do not bill 20560 or 20561 alongside acupuncture codes on one date |
Source: CMS Medicare Coverage Database, NCD 30.3.3 (effective January 21, 2020); CMS MLN Matters MM13288 (effective for dates of service from January 1, 2024).
One gap we could not close
We could not retrieve the current-year Medicare Physician Fee Schedule status for 20560 and 20561 or the current NCCI edit pairs. Check both in the CMS files before you set billing rules for your practice.
Why do commercial payers handle dry needling differently?
Each commercial payer writes its own medical policy, so the answer changes by plan. We read two. Medica’s policy, effective September 1, 2025, calls trigger point dry needling investigative and unproven and says it is not covered, per Medica’s dry needling policy. A Blue Cross Blue Shield of Michigan policy effective June 20, 2026 cites NCD 30.3.3 for the Medicare position and refers to a separate dry needling policy for its own rules, per the BCBSM medical policy.
Two policies do not prove what other payers do. They show why one rule for your whole payer mix fails. Medica’s policy also states that listing a code does not mean coverage or payment. A code that appears in a policy is not a promise to pay.
| Check | Why it matters | Where to find it |
|---|---|---|
| Is the service covered, investigational or excluded? | Medica treats it as not covered; other plans may differ | Payer medical policy library |
| Does the plan cover it for your provider type? | Coverage can depend on who performs it and what state rules allow | Provider manual and contract |
| Which code does the payer expect? | Medica’s policy also lists unlisted code 20999 for information | Payer policy and claim edit rules |
| Is prior authorization required? | Some policies state none applies and review happens after payment | Payer portal or provider services |
| What can the patient be asked to pay? | Contract terms and notice rules limit patient billing | Your contract; for Medicare, CMS notice rules |
Source: Medica Trigger Point Dry Needling policy (effective 09/01/2025); BCBSM medical policy (effective 06/20/2026). Our reading of two policies, not a survey of payers.
What about patient payment and Medicare notices?
If a payer will not cover the service, the question is who owes the charge, and the answer depends on notice and contract terms. We do not suggest discounted cash offers as a workaround. A discount can clash with in-network contracts, and for Medicare patients it can raise separate compliance questions. Ask your compliance advisor or payer before you write a self-pay policy.
For Medicare, notice rules matter. Per the CMS Medicare Claims Processing Manual, chapter 30, section 50, a beneficiary may be held liable only after receiving a proper written notice and agreeing to pay. Without a valid notice when one is required, the provider generally carries the liability and cannot collect from the patient. The same section says a notice is not required for care that is statutorily excluded, and that it may then be issued voluntarily.
What we could not confirm is which category dry needling falls into under NCD 30.3.3. Treat that as a question for your Medicare Administrative Contractor. Our ABN medical billing guide explains how the form works in general.
How does dry needling fit into a therapy visit?
Dry needling is counted by muscles, not minutes, so it does not follow the timed-unit math used for many therapy codes. The two descriptors contain no time period. If the same visit includes timed services, the minutes for those services still need their own record.
Our 8-minute rule billing guide covers how timed units are counted, and the physical therapy billing units guide covers the unit question for the treatment codes around it.
A manual therapy code billed in the same session is where we would look first for a payer edit. We could not confirm a specific bundling pair in the sources we read, so look up the current edits before you decide. If a modifier is ever needed to show a separate service, modifier 59 rules explain what the modifier means, and payer edit rules decide whether it is accepted.
Where do dry needling claims usually break?
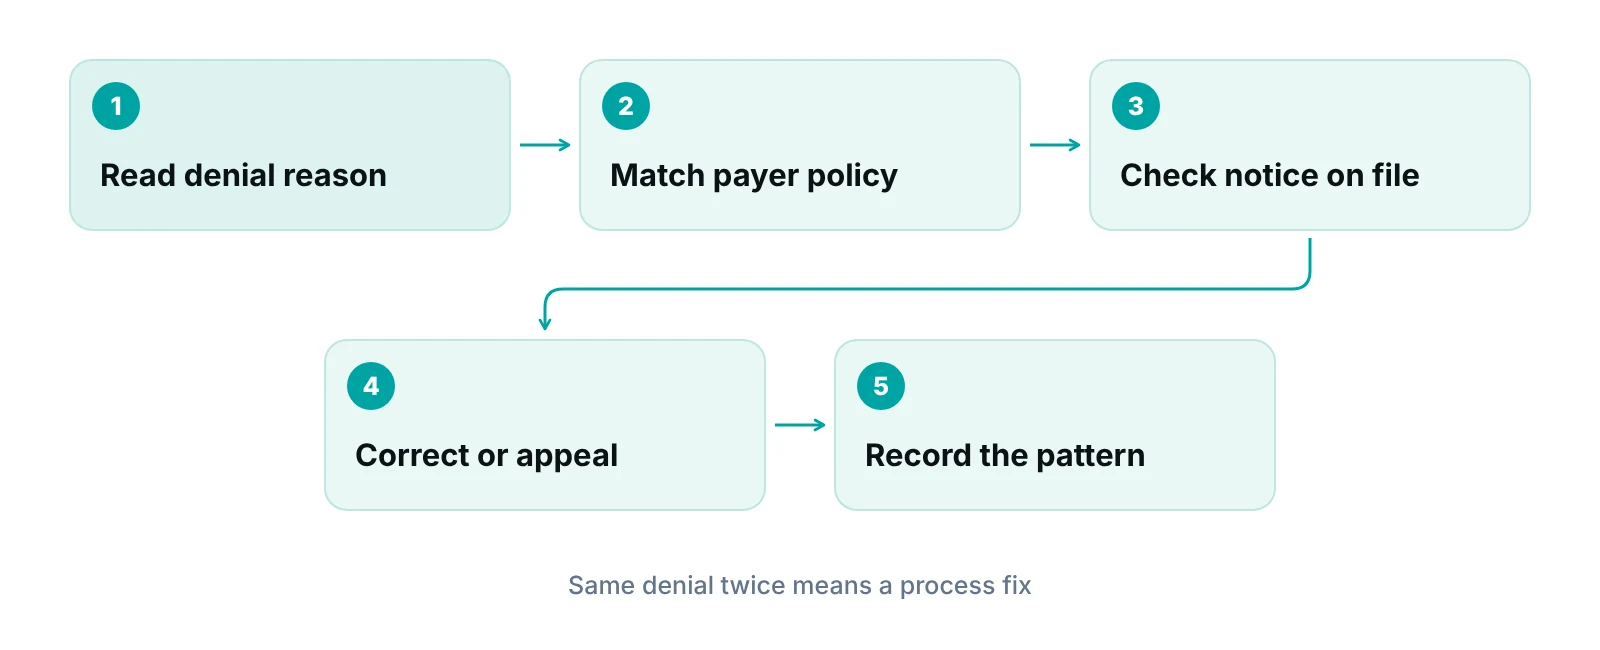
They break at four points: an unconfirmed payer policy, a muscle count that is missing from the note, a code that does not match the note, and a denial that nobody reviews. Each is a process gap, not a coding mystery.
- No policy check: staff bill the code, and the denial arrives weeks later.
- Weak notes: the chart says needling was done but not how many muscles, so 20560 versus 20561 cannot be defended.
- No pattern review: the same payer denies the same code every month and no one notices.
- Unclear owner: the denial sits in a queue with no named person.
Clear notes also make an appeal possible; see our guide to clear documentation in medical billing. For rehabilitation practices, our rehabilitation billing support is built around these visit patterns, and our medical billing and coding support covers charge entry and claim follow-up.
Claims that fail this way are easier to catch when each one has a stage and an owner. That is the idea behind a practice management system that tracks claims by stage, where data-completeness checks run before submission and denial patterns show up in reports. It is a claims tool, not an EHR.
Not sure which payers deny dry needling?
Send us a sample of your denied claims and we will show you the pattern by payer and code in a free practice audit.
Our recommendations
- Build a payer policy sheet. List each payer in your mix and record its dry needling position, the policy date and who checked it. Review it each quarter, since policies change.
- Put the muscle count in the note. Ask clinicians to record the muscles treated. Billing staff should not have to infer the count that decides 20560 or 20561.
- Decide the patient-payment policy in advance. Write it with your compliance advisor before the first denial arrives, and do not improvise at checkout.
- Separate Medicare from commercial rules. NCD 30.3.3 governs Medicare. Commercial payers set their own rules, so one workflow for both will fail.
- Review dry needling denials monthly. Group them by payer and reason. A repeat denial points to a process fix, not a resubmission.
Track dry needling claims by payer and stage in one place.
Our portal tracks each claim by stage with an owner, runs data-completeness checks before submission and reports denial patterns. It is a claims tool, not an EHR.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Dry needling billing is a coverage question first and a coding question second: Medicare’s national coverage decision excludes it outside chronic low back pain, and commercial payers decide plan by plan. Confirm the payer, record the muscle count and review denials by pattern. If your team wants that handled consistently, see our denial management services or ask for a free practice audit.
Frequently asked questions
What is the difference between CPT 20560 and 20561?
CPT 20560 is needle insertion without injection into one or two muscles, and CPT 20561 is the same service for three or more muscles. The number of muscles treated decides the code, not the time spent. Your note should state which muscles were treated so the code can be supported.
Does Medicare cover dry needling?
Mostly no. CMS national coverage determination 30.3.3 says all types of acupuncture, including dry needling, are non-covered for any condition other than chronic low back pain. The covered exception has its own conditions and a list of eligible practitioners that does not include physical therapists. Confirm details with your Medicare Administrative Contractor.
Do commercial insurers pay for dry needling?
It depends on the plan. The two policies we read, Medica’s and a Blue Cross Blue Shield of Michigan policy that cites the Medicare position, point toward non-coverage or separate rules. Check each payer’s current medical policy before you bill, because policies change and differ by plan.
Can I bill 20560 or 20561 with acupuncture codes on the same day?
For Medicare, CMS says dry needling and acupuncture are disallowed on the same date of service in MLN Matters MM13288. Commercial payers set their own rules, so confirm theirs. In either case, the note must support the service you report.
Should I offer cash discounts for dry needling?
We do not recommend building that policy on your own. Discounts can conflict with in-network contract terms, and Medicare patients raise separate notice and liability questions. Ask your compliance advisor and the payer, then write the policy down before you use it.
Does the 8-minute rule apply to dry needling?
The two dry needling codes are described by muscle count, with no time period in the descriptor. The 8-minute rule applies to timed codes, so keep minutes for any timed services in the same visit. Our 8-minute rule guide explains how timed units are counted.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- NCD 30.3.3 Acupuncture for Chronic Low Back Pain — CMS Medicare Coverage Database (2020)
- MLN Matters MM13288 — CMS (2023)
- 2020 Medicare Physician Fee Schedule and CPT Code Changes — AAPM&R (2019)
- CMS Finalizes Physician Payment and Policies for 2020 — AAPM&R (2019)
- Compliance Matters: Physician Fee Schedule coding updates — APTA (2020)
- Biofeedback and Dry Needling Coding Update — APTA Academy of Pelvic Health (2020)
- Trigger Point Dry Needling policy 9672 — Medica (2025)
- Medical policy citing NCD 30.3.3 — Blue Cross Blue Shield of Michigan (2026)
- Medicare Claims Processing Manual, Chapter 30, Section 50 — CMS (2024)
Disclaimer: This article is educational and is not legal, coding, clinical or compliance advice. Payer rules and Medicare policies change and vary by plan and contractor. Confirm current requirements with each payer and your Medicare Administrative Contractor before you bill.
