
In-network vs out-of-network is a difference in contracts. In-network providers have agreed rates with the patient's health plan, so the plan pays an allowed amount and the patient owes a copay, coinsurance or deductible. Out-of-network providers have no such contract, so the plan may pay less and the provider may bill the rest, unless federal protections apply.
This explainer is written for both sides of the desk: patients deciding where to go, and practice staff explaining why a bill looks the way it does. It uses CMS definitions and CMS No Surprises Act guidance, and it flags what is left to plan and state rules.
If you need the billing workflow for non-contracted care, the out-of-network medical billing guide covers it step by step, so this page does not repeat it.
Key takeaways
- The provider’s contract with the patient’s specific plan decides network status.
- Balance billing is the main way out-of-network care costs more, and in-network providers cannot do it for covered services.
- The No Surprises Act protects emergency care and certain facility-based care, but not ground ambulances or doctor’s office visits.
- Signing a notice and consent form is optional and cannot waive protection for emergency or ancillary care.
- Self-pay patients are entitled to a good faith estimate before scheduled care.
What in-network and out-of-network mean
Network status describes whether a provider or facility has a contract with a patient’s health plan. In the plain-language glossary from CMS, in-network providers are those with a contract with your plan to provide services at certain costs. An out-of-network provider is one who does not have a contract with your plan.
That contract is the whole story. It sets the allowed amount, which CMS describes as the most the plan will pay for a covered service (also called the negotiated rate). What the patient owes is worked out from that figure, not from the price on the provider’s own fee list.
One practical point follows from the definition. Network status belongs to the contract between a provider and a particular plan. A clinic can be in network for one plan and out of network for another, so the name of the insurer is not enough to know where a visit stands.
Five terms that decide the patient's share
- Deductible: what the patient pays for covered services in a coverage period (usually a year) before the plan starts paying its share.
- Copayment: a fixed amount, such as $15, paid for a covered service, usually at the visit.
- Coinsurance: the patient’s share of a covered service as a percentage of the allowed amount.
- Out-of-pocket limit: the most a patient could pay in a coverage period for covered services. After it is reached, the plan usually pays 100% of the allowed amount.
- Balance billing: when a provider bills the patient for what remains after the plan pays, which is the billed charge minus the allowed amount.
How the contract changes what a patient pays
In-network care generally costs the patient less, and out-of-network care usually costs more. The reason is the contract, not the quality of care. The table sets the two side by side.
| Feature | In-network | Out-of-network |
|---|---|---|
| Contract with the plan | Yes | No |
| Price basis | Negotiated allowed amount | Provider’s billed charge; the plan still pays from its own allowed amount |
| Patient’s share | Copay, coinsurance or deductible applied to the allowed amount | Usually costs more; read the plan’s out-of-network benefits |
| Balance billing | Not allowed for covered services | Possible, unless a federal or state protection applies |
| Choice of provider | Providers listed by the plan | Any provider, with benefits that depend on the plan |
| Who to ask first | The plan and the provider’s office | The plan and the provider’s office, before the visit |
Source: CMS, Health insurance terms you should know (accessed 2026).
The “balance billing” row is where most of the confusion starts. An in-network provider cannot bill a patient this way for covered services. An out-of-network provider often can, which is why the same service can produce two very different bills.
A worked example with round numbers
The figures below are invented to show the arithmetic. They are not typical prices. Assume the deductible is already met, the provider’s billed charge is $500, and the plan’s allowed amount is $200 in both cases. Assume 20% coinsurance in network and 40% out of network.
| Line | In-network | Out-of-network |
|---|---|---|
| Billed charge | $500 | $500 |
| Plan’s allowed amount | $200 | $200 |
| Coinsurance on the allowed amount | $40 (20%) | $80 (40%) |
| Balance bill (billed minus allowed) | $0 | $300 |
| Patient owes | $40 | $380 |
Illustration only. Figures are hypothetical; balance billing definition from CMS (accessed 2026).
Most of the gap in this example comes from the balance bill, not the higher coinsurance. That is the part federal law now limits in some settings, covered below. Outside those settings, the patient is relying on what the provider and plan have agreed in advance.
Why patients still get surprise bills
A surprise bill happens when a patient expects in-network pricing and receives an out-of-network charge. It is most common when the patient did not choose every clinician involved, such as in an emergency or during a surgery.
The size of the problem before federal protections took effect is documented. A KFF analysis of 2017 claims from large employer plans, published in June 2019, found that 18% of emergency visits had at least one out-of-network charge, as did 16% of in-network hospital stays. Those are pre-2022 figures and do not describe the current rate.
Directories are another source. The CMS overview of the No Surprises Act states that when a consumer relies on incorrect provider directory information, the plan must apply the deductible and out-of-pocket maximum as if the provider were in network. The practical lesson for patients is to screenshot or note the directory listing when booking. The lesson for practices is to keep the plan’s information about the practice accurate. For a closer look at disputing a bill, see our guide to understanding surprise medical bills and how to dispute them.
What the No Surprises Act covers and what it does not
The No Surprises Act limits what patients can be charged in several common surprise-bill situations. Per CMS, the rules for providers and facilities took effect on January 1, 2022, and for health plans on plan or policy years beginning on or after that date (CMS).
Protection depends on both the service and the setting. The table summarizes the main cases.
| Situation | Federal protection | What to know |
|---|---|---|
| Emergency care, including post-stabilization services | Yes, in most cases | Treated as in network with no prior authorization; cost sharing is capped at in-network levels. A valid notice and consent can waive post-stabilization protection. |
| Non-emergency ancillary care (such as anesthesiology or radiology) at an in-network hospital, outpatient department or surgery center | Yes, in all circumstances | A signed form cannot waive protection for these services. |
| Other out-of-network clinicians at those in-network facilities | Yes, unless valid notice and consent | Signing is the patient’s choice. The patient should not be asked to sign if no in-network option was available. |
| Air ambulance | Yes, for covered services | The Act protects against out-of-network air ambulance charges. |
| Ground ambulance | No | CMS says the Act does not cover it. State law may apply. |
| Non-emergency care in a doctor’s office or other setting that is not a hospital, outpatient department, critical access hospital or surgery center | No | This falls outside the federal protection. |
| Coverage only through Medicare, Medicaid, CHIP, Indian Health Service, VA or TRICARE | Not under this Act | These programs have their own rules. |
Source: CMS, No Surprises Act Overview of Key Consumer Protections; CMS, Know your medical bill rights when using insurance (accessed 2026).
How the patient's cost is set
For protected services, the patient’s cost sharing cannot be more than it would be in network. When no state law or all-payer agreement sets the amount, the plan uses the lower of the billed amount or the qualifying payment amount, then applies the in-network deductible, copay or coinsurance (CMS key protections).
Any extra payment the plan owes the provider is a separate matter between them. The plan and provider first have a 30-business-day open negotiation period. If they do not agree, they use the federal independent dispute resolution process. The patient is not part of it.
Notice and consent: when a patient can waive protection
A patient can agree to out-of-network care in limited cases, but the rules are strict. CMS says providers must use the standard CMS notice and consent forms or state versions, cannot create their own, must present them separately from other forms, and must give a good faith estimate first.
- Consent can never waive protection for pre-stabilization emergency care or for ancillary services such as anesthesiology, radiology or assistant surgeon services.
- For post-stabilization care, waiver is allowed only if the patient can safely travel by non-medical transport to an available in-network facility and can give informed consent. If ambulance transport is needed, consent is not valid.
- For scheduled non-emergency care, waiver is allowed only when another in-network provider could provide the service at that facility.
Signing is optional
CMS tells patients that signing the notice and consent form is their choice, and that signing means they agree to get care out of network. Before signing, a patient can call the No Surprises Help Desk at 1-800-985-3059, ask the insurer or provider, or contact a patient advocate (CMS).
Patients paying without insurance
Uninsured and self-pay patients have a related protection. CMS guidance says providers must give a good faith estimate within one business day of scheduling when care is booked at least three business days ahead, and within three business days when it is booked at least ten business days ahead or when the patient asks for cost information. A patient can start dispute resolution if the bill is at least $400 more than the estimate, within 120 calendar days of receiving it. Enrollees in federal programs such as Medicare, Medicaid or TRICARE are not eligible for a good faith estimate.
Questions that settle network status before a visit
Network status is easiest to settle before care starts. These five checks work for most non-emergency visits and apply whether the reader is a patient or the person answering the phone at a practice.
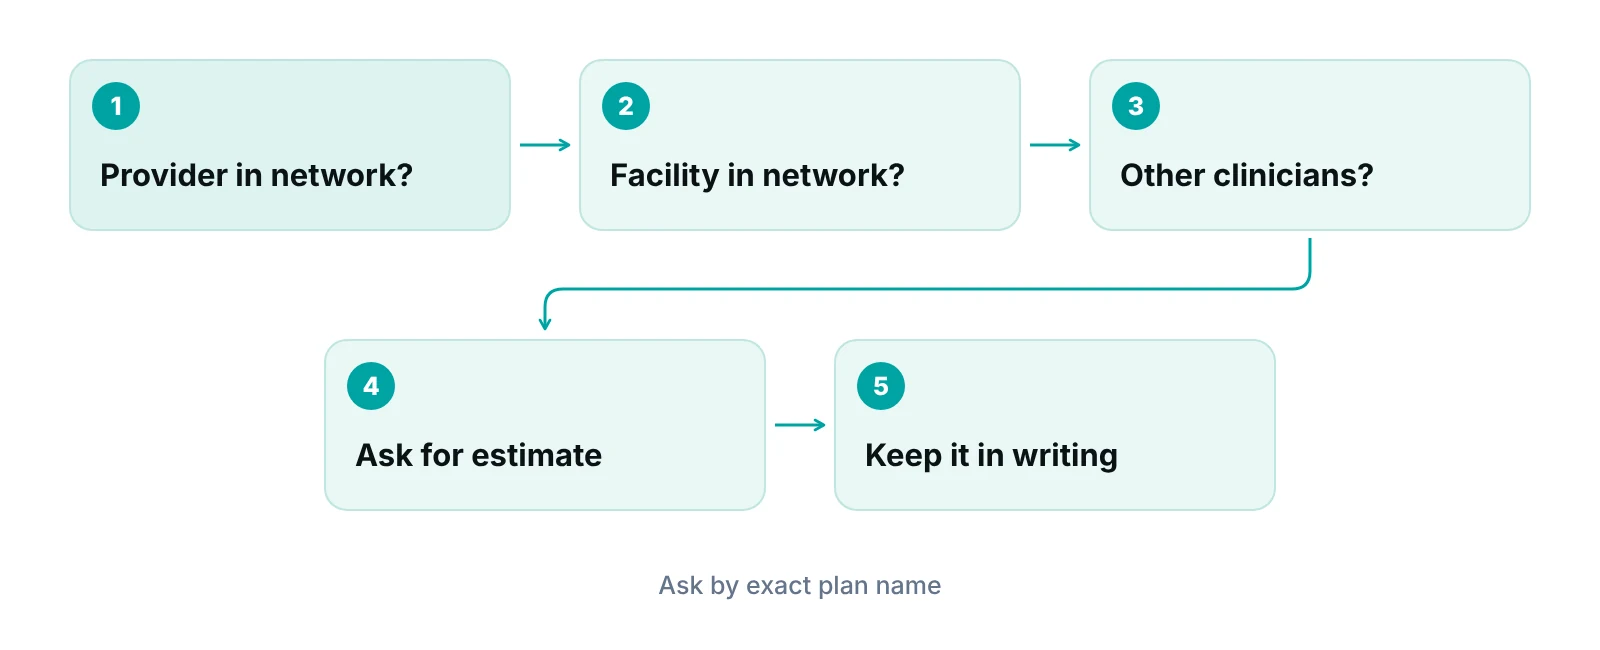
- Ask whether the provider is in network for the patient’s exact plan, not just the insurer.
- Ask the same about the hospital or surgery center, since the facility has its own contract.
- Ask whether anesthesiology, radiology, pathology or assisting surgeons will be involved, and whether they are in network.
- Request a written cost estimate. Uninsured and self-pay patients are entitled to a good faith estimate.
- Keep a record of who answered, what they said and when.
“Network status is decided before the visit, not after the bill, so the cheapest time to check it is at scheduling.”
What the contrast means for a practice
For a practice, network status is a contracting decision first and a billing task second. Being in network means the practice has signed a contract with that plan and accepts its allowed amounts. Enrolling plan by plan is a credentialing and contracting process; our credentialing and payer enrollment services page explains what that work involves,.
The two situations ask different things of the front desk:
- In network: confirm eligibility and plan name, collect the copay, bill the plan, and write off the contractual difference rather than billing the patient for it.
- Out of network: explain expected charges before the visit, check whether a federal protection applies, and avoid balance billing in protected settings.
- Self-pay: issue the good faith estimate on time and keep a copy.
Eligibility checks are the first line of defense, and our patient insurance verification guide covers how to run them. Patients also ask what the plan paid and why, so it helps to know how to read an explanation of benefits.
This article stays at the explainer level. The claim-by-claim workflow for out-of-network care, including superbills, reimbursement and appeals, is in our out-of-network medical billing guide, and the out-of-network claims guide adds claim-level detail. Specialty teams face their own network patterns; see the specialties we support for how billing differs by field.
Need the billing workflow, not just the definitions?
The out-of-network billing guide walks through how claims for non-contracted care are prepared and followed up.
Not sure which of your payers you are in network with?
A free practice audit looks at how your front desk and billing team handle network status and claims today.
How network status flows into the claim
Network status affects every step after scheduling. The same visit moves through the same stages, but the price, the patient’s share and the risk of a dispute differ at each one.
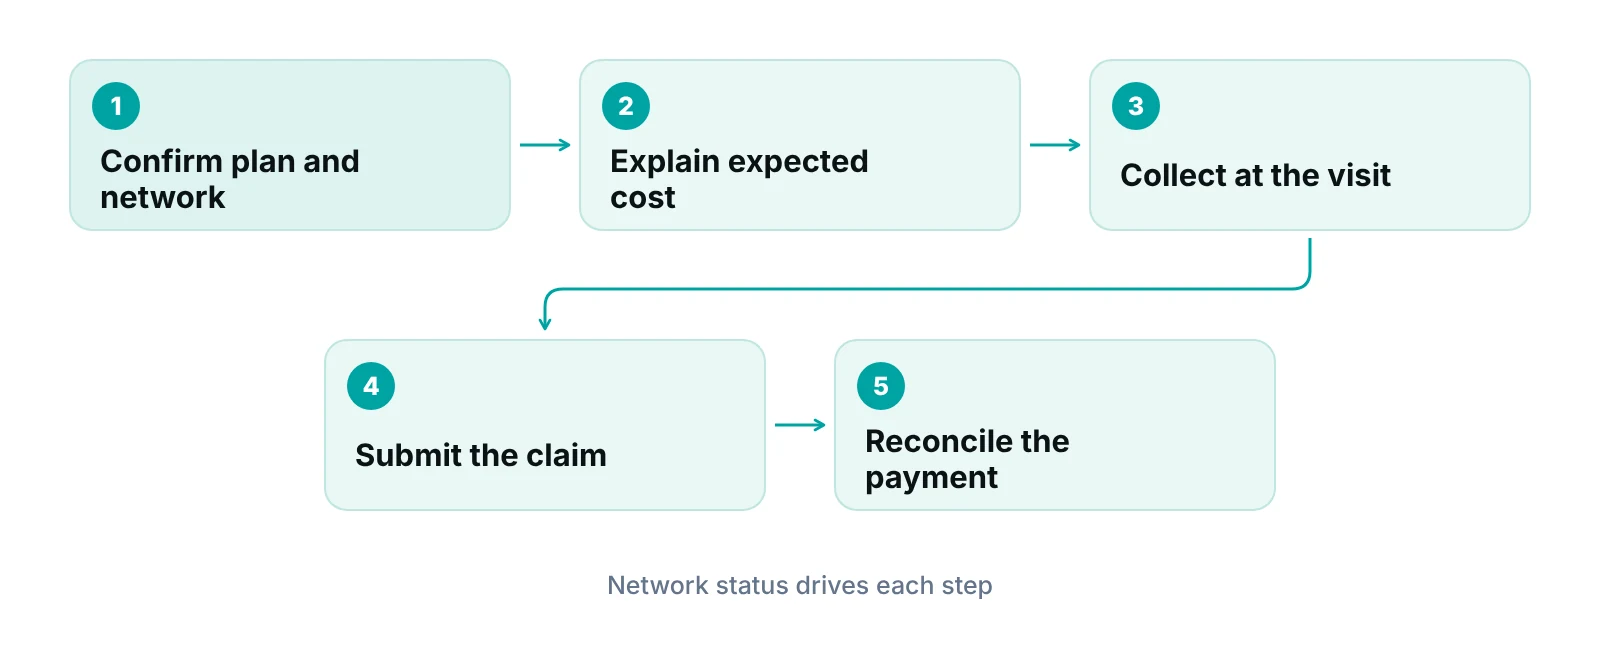
If a claim pays differently than expected, the explanation of benefits usually says why. CMS notes that the plan calculates protected cost sharing, and the patient’s explanation of benefits should show whether the No Surprises Act method was used. A mismatch between what the front desk told the patient and what the explanation shows is the moment to review the claim, not to bill the patient for the difference.
Our recommendations
- Check network status by plan, not by insurer. Record the exact plan name and ID at scheduling. A provider can be in network for one plan and out of network for another.
- Have the cost conversation before non-emergency care. Explain the expected charges and ask the patient to confirm in writing. This is the point where most disputes can be avoided.
- Use only the standard CMS notice and consent forms. Present them separately, with the good faith estimate first, and never ask a patient to sign for emergency or ancillary services.
- Issue good faith estimates on time. For self-pay patients, track the one-business-day and three-business-day deadlines and keep a copy of each estimate.
- Document how network status was checked. Note the date, the source (plan portal, phone call or directory) and who checked. A record helps if a directory error or dispute comes up later.
- Keep the plan's directory listing accurate. Review how your practice appears in each plan’s directory and report corrections, since patients rely on it.
- Send out-of-network claim work to a defined process. Use a written workflow for non-contracted claims instead of handling each case ad hoc. The billing guide linked above is a starting point.
Bottom line
In-network vs out-of-network is a question of who has a contract with whom, and the contract sets the price. Patients should confirm network status for the exact plan before non-emergency care, and practices should make that check part of scheduling. When network status turns into claim work, a medical billing service can take over charge entry, submission and follow-up, and our revenue calculator can help you estimate what slow or missed payments cost. For questions about your own setup, you can also contact the RCM Finder team.
Frequently asked questions
What does in-network mean?
In-network means the provider or facility has a contract with the patient’s health plan to provide services at agreed costs. The plan pays from a negotiated allowed amount, and the patient owes a copay, coinsurance or deductible on it. The contract is with a specific plan, so a provider can be in network for one plan and not another.
Is out-of-network care always more expensive?
Not always, but CMS says care from out-of-network providers usually costs more. Without a contract, the provider may bill more than the plan’s allowed amount, and the plan may cover less. How much more depends on the plan’s out-of-network benefits and whether a federal or state protection applies.
Can an out-of-network provider bill me for the rest of the charge?
Sometimes. That practice is called balance billing. The No Surprises Act limits it for emergency care, for certain services at in-network hospitals and surgery centers, and for air ambulances. It does not cover ground ambulances or care in a doctor’s office outside those settings. State laws may add protection.
Does the No Surprises Act cover Medicare or Medicaid patients?
CMS lists coverage only through Medicare (including Medicare Advantage), Medicaid, CHIP, Indian Health Service, VA or TRICARE as not covered by the Act’s protections. Those programs have their own rules. CMS suggests such patients look for an action plan for their billing issue.
What if the provider directory was wrong?
CMS states that when a consumer relies on incorrect provider directory information, the plan must apply the deductible and out-of-pocket maximum as if the provider were in network. Patients should note the date and source of the listing and contact the plan if they receive a higher bill.
What is a good faith estimate?
A good faith estimate is a written cost estimate that providers must give to uninsured and self-pay patients. It is due within one to three business days of scheduling or a request, depending on timing. If the final bill is at least $400 higher, the patient can start dispute resolution within 120 days.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Health insurance terms you should know — CMS (2026)
- No Surprises Act overview for assisters — CMS (2026)
- No Surprises Act Overview of Key Consumer Protections — CMS (2026)
- Know your medical bill rights when using insurance — CMS (2026)
- Good faith estimate and patient-provider dispute resolution for uninsured or self-pay individuals — CMS (2026)
- An Examination of Surprise Medical Bills and Proposals to Protect Consumers from Them — KFF (2019)
Disclaimer: This article is educational and is not legal, billing, coding or compliance advice. Plan rules, state laws and federal guidance vary and change. Confirm network status and benefits with the health plan and the provider before care, and check current CMS guidance before relying on any rule described here.
