

To credential a provider with insurance, confirm the clinician's identifiers and CAQH profile, apply to each payer (Medicare through PECOS, Medicaid through the state, commercial plans through their own forms), and wait for a confirmed effective date before billing in-network. There is no single official turnaround time, so start early and track every application.
Most practices use “credentialing” to mean the whole journey from a new clinician’s first day to a first paid in-network claim. That journey has separate parts: verification of qualifications, enrollment with each payer, a contract, and ongoing upkeep. This guide separates them, shows the order of work, lists the documented renewal cycles and explains how to avoid stalled applications.
Key takeaways
- Credentialing, enrollment, contracting and privileging are different steps; you need the right ones for each payer.
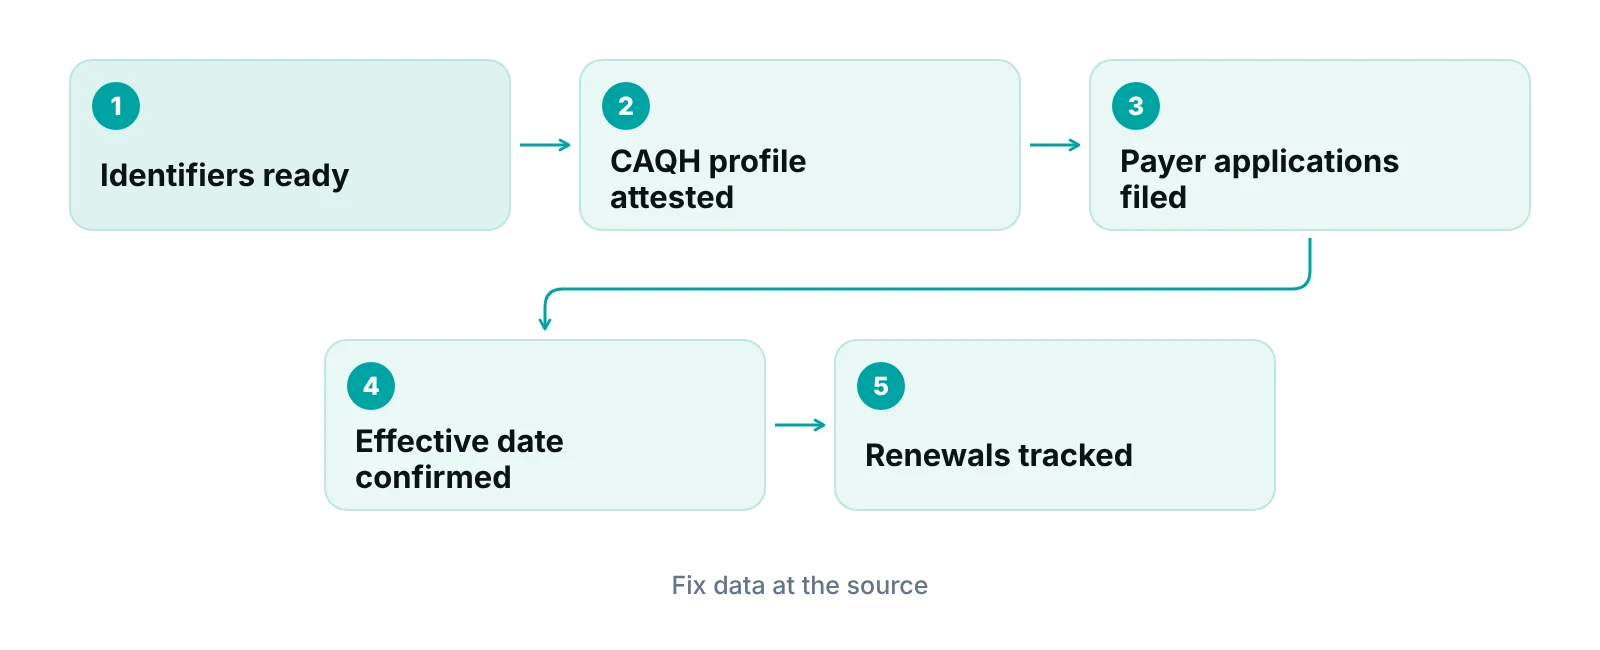
- Work from identifiers to CAQH to each payer, and get the effective date in writing before billing in-network.
- No official source gives one commercial timeline; documented cycles are 120 days (CAQH) and 5 years (Medicare revalidation).
- Late Medicare revalidation deactivates billing and requires a new application.
- Choose in-house, outsourced or hybrid by volume and ownership, not by promised speed.
What it means to credential a provider with insurance
Credentialing is the payer’s check that a clinician is qualified; enrollment and the contract are what let you bill that payer. The Medicaid and CHIP Payment and Access Commission (MACPAC) describes credentialing as the process by which managed care plans verify that a provider is qualified to serve their enrollees, and enrollment as the state Medicaid agency’s decision on whether a provider may serve enrollees and receive payment (MACPAC, 2026). In daily practice the two blur together, which is why a clinician can be “credentialed” and still not be billable.
Hospitals add a fourth step called privileging. In a Medicare-participating hospital, the medical staff examines the credentials of eligible candidates and recommends them, and the governing body makes the appointment, under criteria set out in the medical staff bylaws (42 CFR 482.22). Privileging decides what a clinician may do inside that hospital. It is separate from getting paid by an insurer. See our guide to credentialing, privileging and enrollment.
| Term | What it decides | Who decides | What it unlocks |
|---|---|---|---|
| Credentialing | Whether the clinician’s license, training, work history and record meet the plan’s standards | A health plan, or a verification organization working for it | Eligibility to be considered for the plan’s network |
| Enrollment | Whether the clinician may be paid by the program (Medicare or state Medicaid) | Medicare Administrative Contractor or state Medicaid agency | Billing privileges with that program |
| Contracting | The terms of participation, such as fee schedule and rules | The plan and the practice, by written agreement | In-network status and rates |
| Privileging | Which services the clinician may perform at a hospital | Hospital governing body, on medical staff recommendation | Permission to practice inside that hospital |
Source: MACPAC, Provider Enrollment and Credentialing in Medicaid (2026); 42 CFR 482.22 (Cornell LII).
Why the distinction matters for revenue
A clinician can see patients the day a license is active. Payers, however, pay in-network rates only from the date they confirm in writing. Ask every payer for that date and keep the letter.
The steps, in the order that avoids rework
Work from identifiers outward: get the clinician’s own records right, then the profile plans read, then each payer’s application. Doing it in this order means the same name, license and practice-location data go into every form.
1. Confirm the clinician's individual identifiers
Covered health care providers must obtain a National Provider Identifier (NPI), use it in standard transactions, and report changes to the national provider system within 30 days (45 CFR 162.410). CMS says the web-based NPPES application is the fastest route to an NPI (CMS). Gather the license number and every practice location at the same time.
2. Complete and attest the CAQH ProView profile
CAQH ProView is free to providers, must be re-attested every 120 days (180 days for providers practicing in Illinois), and only the provider can authorize which organizations see the profile (CAQH). If a plan is missing from the authorization list, CAQH says to ask that plan to add the provider to its roster.
3. Apply to Medicare through PECOS
Physicians and non-physician practitioners do not pay a Medicare enrollment application fee. CMS encourages online submission through PECOS because it is faster and easier, and the paper CMS-855I covers individuals, including those who reassign benefits to a group (CMS MLN). CMS states that the reassignment form (CMS-855R) has been merged into the paper CMS-855I, so confirm the current form for your situation. Respond to any information request from the contractor within 30 days, as the same page advises. For the group-level view, read our guide to insurance credentialing for group practices.
4. Apply to the state Medicaid program and its managed care plans
Medicaid is two layers. The state enrolls the provider, and each Medicaid managed care plan credentials the provider for its own network. MACPAC notes that credentialing separately with each plan can discourage providers from joining more than one network, so plan the sequence before you start. State rules differ, so read our Medicaid credentialing guide and your state agency’s current instructions.
5. Apply to commercial plans
Each commercial plan has its own application route and rules. Some read the CAQH profile once you authorize them, and some also want their own forms or roster submissions. Ask each plan, in writing, what it needs and what it counts as a complete request, because an incomplete one may not start the clock. If a plan offers delegated credentialing, read our delegated vs non-delegated credentialing guide first.
6. Confirm the effective date, load the contract, and only then schedule in-network
Get the participation agreement, the effective date and the provider’s plan-specific identifiers in writing. Load them into your billing system and tell the front desk which plans the clinician can see patients for. Claims sent before that date are the kind that end up in denial management later.
What to gather before you start
Collect the documents once, keep them current, and reuse them for every application. CAQH’s quick reference lists the items a provider enters or uploads: identification numbers such as NPI, Medicare and Medicaid numbers, a list of all previous and current practice locations, and scanned copies of the documents below (CAQH).
- Curriculum vitae (CV) with a complete work history
- Medical license
- DEA certificate and, where the state requires it, the controlled dangerous substance (CDS) certificate
- IRS Form W-9
- Malpractice insurance face sheet
- Summary of any pending or settled malpractice cases
Add board certification and hospital affiliations if a plan asks. Make every date and name in the profile match your source records exactly.
How long it takes, and how often it repeats
No government source publishes one timeline for commercial credentialing, so treat any single number you read online as an estimate. What is documented are the response windows, the renewal cycles and a few state and federal benchmarks.
- MACPAC reports that CMS recommends a 60-day timeline for state Medicaid screening and verification, which states may struggle to meet, and that Pennsylvania requires its plans to complete credentialing within 60 calendar days of a completed application (MACPAC, 2026).
- There is no federal timeline for state enrollment decisions, and long processes can cause financial hardship for small practices by delaying billing, according to the same report.
- Federal rules allow a Medicaid plan to sign a network agreement before the state finishes enrollment, but the plan must end it if the state denies the application or 120 days pass without the state executing the provider agreement (MACPAC, 2026).
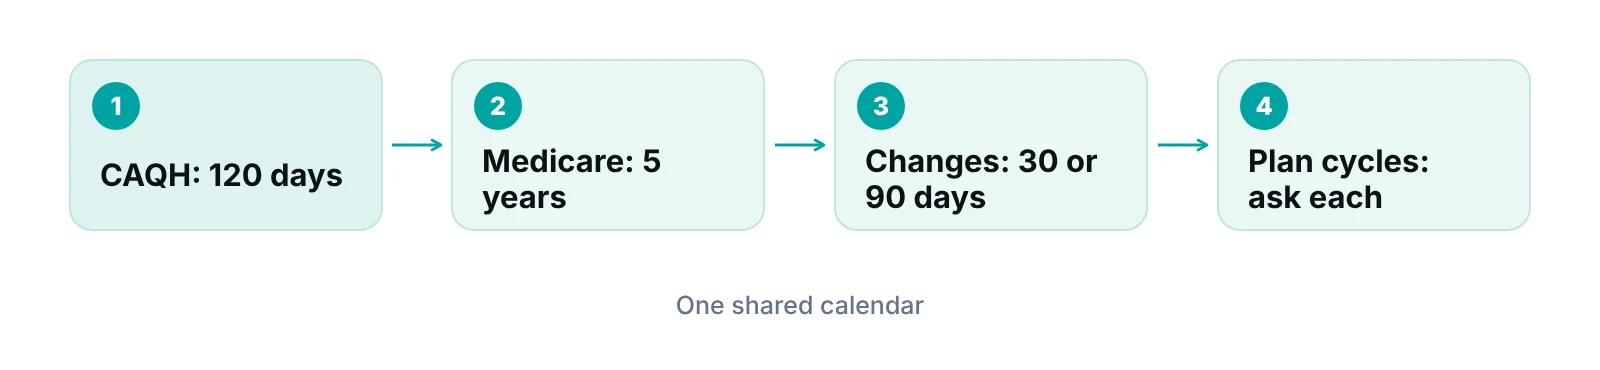
| Item | Interval or deadline | Applies to |
|---|---|---|
| CAQH ProView re-attestation | Every 120 days (180 days in Illinois) | Every provider with a CAQH profile |
| Medicare revalidation | Every 5 years, or when CMS requests it; DMEPOS suppliers every 3 years | Medicare-enrolled providers and suppliers |
| Response to a revalidation notice | Within 60 calendar days of CMS’s notice | Medicare-enrolled providers and suppliers |
| Medicare change reporting | 30 days for ownership or control, practice location and final adverse legal actions; 90 days for other changes | Physicians and non-physician practitioners |
| NPI data changes | Within 30 days of the change | Covered health care providers |
| Hospital NPDB query | At application, then every 2 years | Hospitals, for staff and privileged practitioners |
| Medicaid plan recredentialing | Every 3 years in Ohio, Oregon and Pennsylvania; no federal rule sets one | Medicaid managed care network providers |
Sources: CAQH quick reference; 42 CFR 424.515; CMS MLN Medicare Enrollment for Providers; 45 CFR 162.410; HRSA NPDB; MACPAC (2026).
Missing a revalidation deadline stops billing
CMS’s revalidation FAQs state that a late revalidation leads to deactivation, an interruption in billing, and a full new application to re-establish billing privileges, and that contractors no longer accept extension requests (CMS).
Effective dates and the cost of waiting
For Medicare, the effective date is generally the later of the filing date of an application that is later approved, or the date the provider first began furnishing services at a new location. The rule is in 42 CFR 424.520(d). Retrospective billing of up to 30 days before the effective date is allowed only when circumstances prevented enrolling beforehand and all program requirements, including state licensure, were met (42 CFR 424.521). Do not plan around it. Commercial plans set their own dates, and some will not backdate at all.
Calculate your own cost of delay rather than rely on an industry figure: scheduled in-network visits per week, times average allowed amount per visit, times the weeks the clinician cannot be billed in-network. Visits you can reschedule reduce the loss, so use your own mix. Our revenue calculator is a place to start.
“The cheapest credentialing application is the one filed early, filed complete, and followed up on the day it goes quiet.”
Specialty changes the workload, because each adds different payers, licenses and facility affiliations. Find your type of practice in our specialties overview.
Why applications stall, and how to prevent it
Documented causes of delay include inconsistent data, missed renewals and unreported changes. The list below pairs each with a control.
- Manual data reconciliation. MACPAC identifies difficult database access and manual reconciliation of inconsistent data as causes of screening delays. Keep one master record of each clinician’s details and copy from it.
- Overlapping checks. MACPAC also finds that credentialing checks such as license verification can duplicate federally required screening, so a single clean submission matters.
- Missed renewals. A lapsed Medicare revalidation deactivates billing, and CAQH requires re-attestation every 120 days. Track dates by payer and clinician.
- Unreported changes. A new practice location, ownership change or adverse legal action must be reported to Medicare within 30 days, and other changes within 90 days. NPI data changes are due within 30 days.
- No owner. Applications sitting in a shared inbox go quiet. Give each application a named owner, a next-contact date and a status.
A tracker, whether a spreadsheet or software, works when each application has one row, one owner and one next action. Keep reference numbers and call notes in the same place.
Technology, verification organizations and telemedicine
Technology helps with data entry, reminders and tracking; it does not shorten a payer’s own review. The tools worth using are free or standard: CAQH ProView for the shared profile, PECOS for Medicare, and a tracker for due dates. Some states also use credentials verification organizations (CVOs). MACPAC reports that Ohio contracts with an NCQA-certified CVO for tasks such as sanctions monitoring and primary source verification (MACPAC, 2026).
Telemedicine adds one hospital-specific rule worth knowing. Under 42 CFR 482.22, a hospital’s governing body may allow its medical staff to rely on a distant-site hospital’s or telemedicine entity’s credentialing and privileging decisions, if a written agreement meets conditions. These include that the practitioner holds a license issued or recognized by the state where the patients are, and that the hospital reviews the practitioner’s performance. That applies to hospital privileging. Payer enrollment for telehealth is separate, so see our telehealth billing guide for billing rules.
Be cautious about claims that artificial intelligence or blockchain will transform credentialing. The reliable gains are cleaner data, early filing and diligent follow-up.
In-house, outsourced or hybrid: how to decide
Choose by volume, turnover and who will own the follow-up, not by a promised turnaround. A small office with stable payers and a growing group with frequent hires need different models.
| Model | Works best when | Watch for |
|---|---|---|
| In-house | Few clinicians, few payers, a staff member with protected time | Single point of failure if that person leaves; renewals missed during busy periods |
| Outsourced | Many hires, many payers, or no one has time for weekly follow-up | Unclear ownership of logins; ask who holds the CAQH and PECOS access and how you get them back |
| Hybrid | You want to keep control of the data while delegating forms and follow-up | Two people editing the same record; agree on one master file |
Whoever does the work, ask them to put in writing: who holds each login, how often you receive a status report, how payer reference numbers are logged, and how renewals are tracked. Any vendor that will handle patient or provider data should sign a Business Associate Agreement before access where patient information is involved. Provider-data-only work should still have a confidentiality agreement. If you want help, our credentialing services cover payer enrollment and follow-up, and a free practice audit is a low-pressure place to start.
Not sure where your applications stand?
Ask for a free practice audit and talk through your credentialing workflow with our team.
Our recommendations
- Start before the start date. File as soon as a hire is signed. No source guarantees a timeline, and a Medicare effective date is tied to the filing date, not the day you want to start.
- Keep one master record per clinician. Names, license numbers, locations and tax IDs should be identical across NPPES, PECOS, CAQH and every plan application.
- Name an owner for every application. Record the payer, submission date, reference number, next follow-up and owner. Review the list weekly.
- Put every renewal on a shared calendar. Include CAQH every 120 days, Medicare revalidation every 5 years (60 days to respond once notified), and each plan’s recredentialing date.
- Get the effective date in writing. Do not schedule in-network visits or release claims until the payer confirms the date and the clinician’s identifiers.
- Report changes inside the deadline. A move, ownership change or adverse legal action goes to Medicare within 30 days; other changes within 90 days.
Bottom line
Credentialing a provider with insurance is mostly a matter of order, accurate data and follow-up: identifiers, CAQH, then each payer, then a confirmed effective date, then a renewal calendar. If you would rather hand off the paperwork and tracking, our credentialing services can take it on, and our medical billing services pick up once the first claims are ready to go out. Questions? Contact us.
Frequently asked questions
How long does it take to credential a provider with insurance?
No government source gives one figure for commercial plans. Documented benchmarks include CMS’s recommended 60-day timeline for state Medicaid screening and Pennsylvania’s 60-calendar-day requirement for its plans (MACPAC, 2026). Ask each payer for its current turnaround in writing, start as early as you can, and track each application so a quiet one gets a follow-up.
What is the difference between credentialing and enrollment?
Credentialing is a plan verifying a provider is qualified. Enrollment is the program, such as Medicare or state Medicaid, approving the provider to be paid. A contract with the plan sets the in-network terms. You need the right combination for each payer.
What documents do I need?
CAQH lists identification numbers, practice locations, a CV, medical license, DEA and CDS certificates, a W-9, a malpractice insurance face sheet and a summary of any malpractice cases. Individual plans may ask for more, so check each one before you submit, and keep scanned copies current so every application uses the same documents.
How often does credentialing have to be renewed?
It depends on the payer. CAQH requires re-attestation every 120 days, Medicare revalidates most providers every 5 years, and some state Medicaid plans recredential every 3 years. Hospitals query the NPDB at application and every 2 years.
Can a new provider bill before approval?
Medicare’s effective date is generally the later of the application filing date or the first service date at a new location, with limited 30-day retrospective billing in specific cases. Commercial plans set their own dates. Confirm in writing before scheduling in-network.
Should a small practice outsource credentialing?
It can make sense if no one has protected time for weekly follow-up or you hire often. Decide on volume and ownership, ask who holds the logins, and require a status report schedule. Keep the master data in your own control either way, so a change of vendor does not mean starting over.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Provider Enrollment and Credentialing in Medicaid (Chapter 7) — MACPAC (2026)
- 42 CFR 482.22 Condition of participation: Medical staff — Cornell LII (eCFR text) (2026)
- NPDB: Hospitals — HRSA (2026)
- 42 CFR 424.515 Requirements for reporting changes and revalidation — eCFR (2026)
- 42 CFR 424.520 Effective date of billing privileges — Cornell LII (eCFR text) (2026)
- 42 CFR 424.521 Retrospective billing — eCFR (2026)
- Revalidation Cycle 2 FAQs — CMS
- Medicare Enrollment for Providers and Suppliers (MLN) — CMS
- CAQH ProView Provider Quick Reference — CAQH
- 45 CFR 162.410 Implementation specifications: health care providers — eCFR (2026)
- How to Apply for an NPI — CMS
Disclaimer: This page is general educational information for practice owners and managers. It is not legal, coding, billing-compliance or financial advice. Payer rules, timelines and state requirements vary and change; confirm current requirements with each payer, your state Medicaid agency, your Medicare contractor and a qualified advisor before acting.
