
Patient payment plans let a patient pay a balance in scheduled installments instead of one lump sum. To set one up, choose a plan design, check Truth in Lending and Red Flags rules, put the terms in writing, automate payments with the patient's consent, and track enrollment and defaults.
A payment plan is easy to offer and easy to get wrong. The common failures are no written terms, an offer made only after three unpaid statements, and interest or fees added without a legal check. This guide shows how we would set one up for a medical practice, in the order the work happens. It builds on our posts on patient responsibility in medical billing and improving patient collections, and focuses on the plan itself.
Key takeaways
- Offer a payment plan when the balance is first known, not after repeated unpaid statements.
- Put every plan in writing, with a separate authorization for card or bank charges.
- Start with no interest, no late fees and no credit check, and add them only after legal review.
- Regulation Z and the Red Flags Rule can apply to practices that let patients pay over time; ask a healthcare attorney.
- Track offer, enrollment, on-time and default rates monthly.
What is a patient payment plan, and why do practices need one?
A patient payment plan is a written arrangement in which a patient pays a balance on scheduled dates instead of all at once. It usually covers the patient’s share after insurance: deductible, coinsurance, copay balances or a self-pay fee. Practices need one because the balance often arrives as a single large statement.
The cost pressure is documented. In KFF’s 2025 Employer Health Benefits Survey, covered workers who have a general annual deductible faced an average of $1,886 for single coverage, and workers paid an average of $6,850 toward family premiums. A separate KFF analysis of 2021 federal survey data (published in 2024) found that about 14 million adults, 6% of adults, owed more than $1,000 in medical debt, and that people in the U.S. owe at least $220 billion in total.
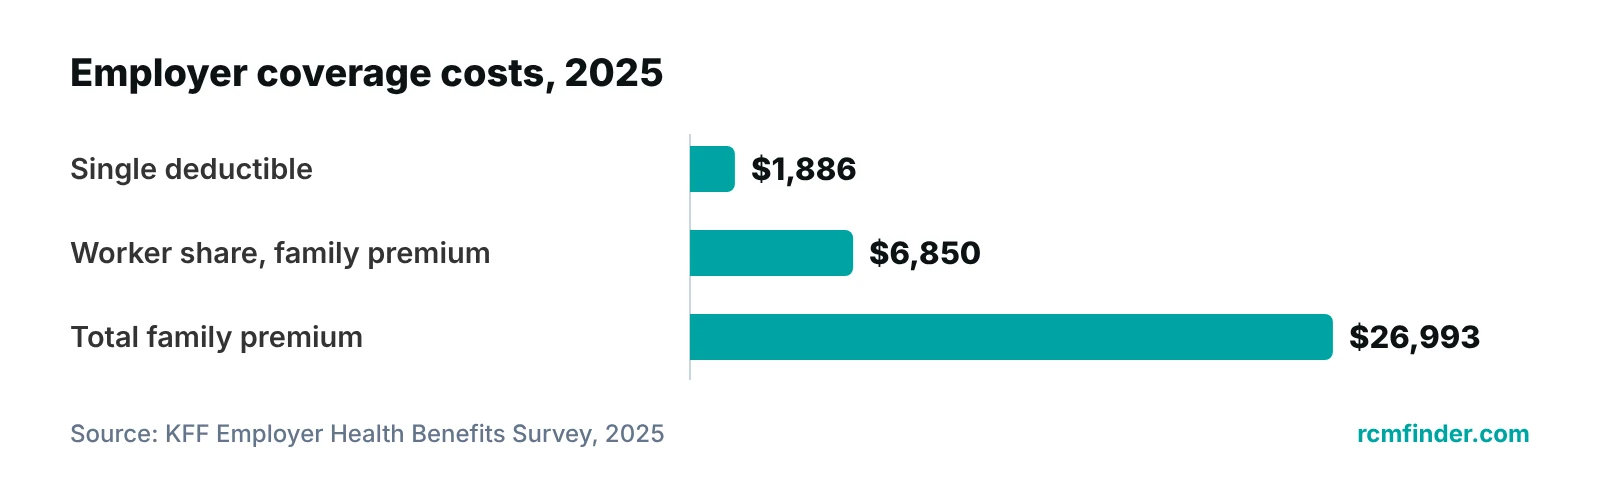
For a practice, the point is simple. A $1,886 deductible is a lot to ask in one payment, and a balance the patient cannot pay in full becomes aged A/R. A plan turns some of that balance into dated, predictable payments. It does not create money that was never collectible, so it works best when offered early.
Which payment plan design should a practice choose?
Choose among three designs: an in-house installment plan, a card-on-file schedule, or third-party financing. They differ in who carries the risk, how much staff time they take and what legal questions they raise. Many practices combine the first two.
| Design | How it works | Best fit | Watch out for |
|---|---|---|---|
| In-house installment plan | Practice and patient sign terms; patient pays the practice on set dates, often with a down payment | Mid-size balances where the practice wants control and no interest | The practice carries the non-payment risk and the tracking work |
| Card-on-file schedule | Patient authorizes recurring charges to a card or bank account for a fixed amount and end date | Any plan, as the collection method inside an in-house plan | Needs written authorization and expiring-card alerts; failed charges need a follow-up routine |
| Third-party financing | A lender pays or credits the practice; the patient owes the lender under its terms | Large planned treatments, when the practice does not want to hold the receivable | Interest and deferred-interest terms belong to the lender; see the legal checks below |
| Deposit plus installments | A deposit before a planned procedure, balance scheduled across the treatment period | Elective or staged care quoted in advance | Estimate must be accurate; insurance changes can move the balance |
Timing matters more than design. Offer the plan when the balance is first known: with the estimate, at check-in, or on the first statement. A practice that quotes treatment in advance, such as a dental practice with treatment plans, can present the plan at the same visit as the quote.
What legal rules should you check before writing the terms?
Check four things first: Truth in Lending (Regulation Z), the FTC Red Flags Rule, the rules around any third-party financing, and your state’s law. Have a healthcare attorney review the final policy. The table below shows what each source says, not a legal opinion.
| Checkpoint | What the source says | What it means for your plan |
|---|---|---|
| Regulation Z: who is a “creditor” | A creditor is a person who regularly extends consumer credit that is subject to a finance charge or is payable by written agreement in more than four installments (not including a down payment), and to whom the obligation is initially payable | A written plan with more than four installments, or any plan with a finance charge, may make the practice a creditor. Counsel should decide how it applies |
| Regulation Z: what counts as credit | Credit is the right to defer payment of debt or to incur debt and defer its payment | Letting a patient pay later is deferred payment in Regulation Z terms |
| FTC Red Flags Rule | Providers that meet the rule’s definition of creditor must maintain a written identity theft prevention program; deferring payment and billing customers are listed as creditor activities, if done regularly and in the ordinary course of business | If you qualify as a creditor, you need a written identity theft prevention program |
| Third-party medical financing | CFPB’s 2023 report found interest was assessed on about 20% of healthcare deferred-interest purchases from 2015 to 2020, and about 34% for borrowers with scores below 619; a footnote says 65% of medical credit cards are signed in providers’ offices | If you offer a lender’s product, present it as the lender’s loan, and offer your own plan or financial assistance review first |
| Medical debt and credit reporting | A federal judge in Texas vacated the CFPB’s medical debt credit-reporting rule in July 2025, according to press coverage; some states have their own laws on reporting medical debt | Do not assume a federal rule decides this. Check your state before reporting plan balances to a credit bureau |
Sources: Cornell LII, 12 CFR 1026.2 (current text); Becker’s Hospital Review on the FTC Red Flags Rule; CFPB, Medical Credit Cards and Financing Plans (May 2023); Checkbook (2025).
Interest, late fees and credit checks change the legal picture
The earlier version of this post listed an interest rate and late-payment penalties as standard plan elements. We now recommend the opposite starting point: no interest, no late fees and no credit check. Add any of them only after legal review. An interest-free plan is also easier for staff to explain and for patients to accept.
The CFPB report also said that many people who sign up for medical financing in a provider’s office may be eligible for financial assistance or charity care. Review that option before you present any financing product. Our post on self-pay patient billing guidelines covers uninsured and self-pay balances in more detail.
How do you set up a patient payment plan, step by step?
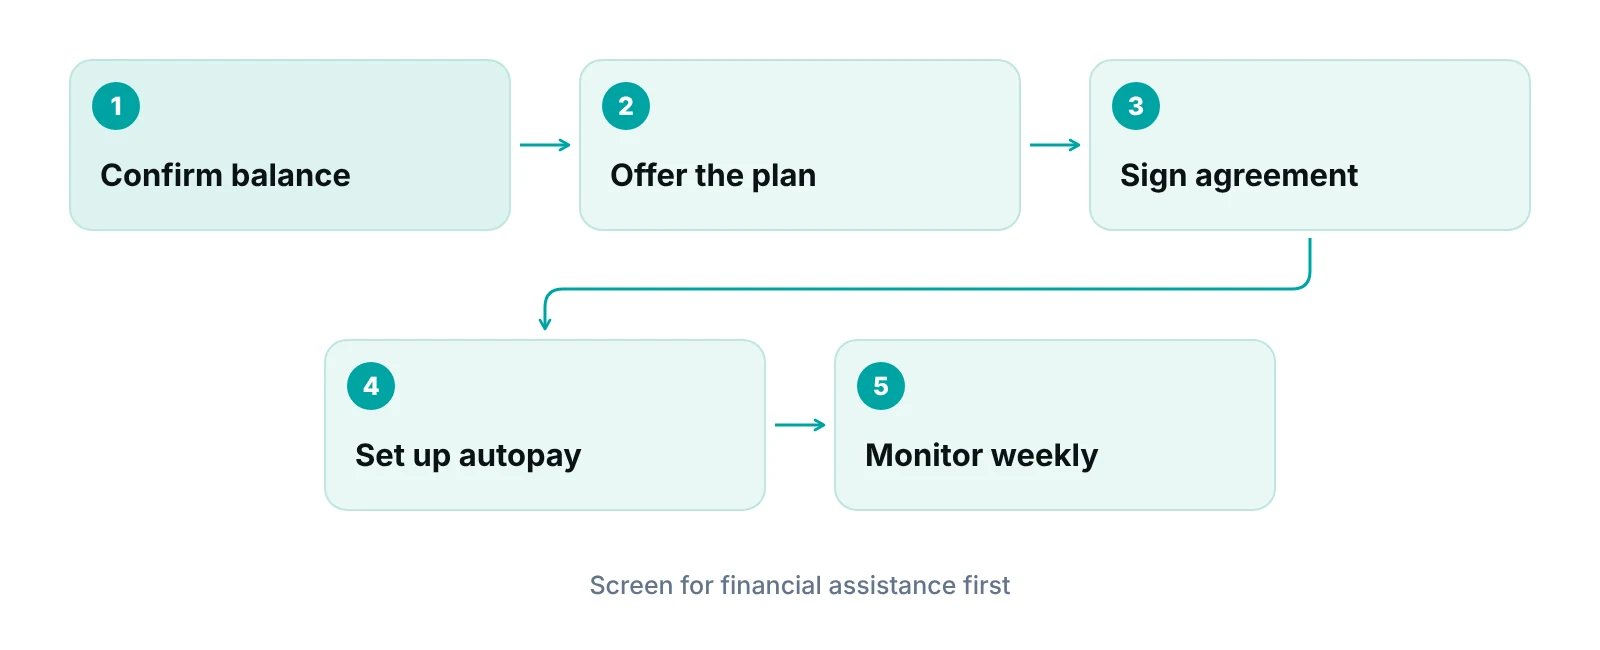
Set the policy once, then follow the same six steps for every patient. A written policy keeps staff from improvising terms at the front desk, which is where inconsistent offers and disputes start.
- Set eligibility. Decide the balance threshold for offering a plan and who may approve exceptions. Screen for financial assistance first.
- Set the terms. Decide the down payment, longest term, minimum installment and due dates. Keep the terms in a table staff can read aloud.
- Confirm the balance. Verify benefits and the patient’s cost share before quoting a total. A wrong estimate becomes a wrong plan. See our insurance verification guide.
- Make the offer. Offer the plan with the estimate, at check-in or on the first statement, not after repeated unpaid statements.
- Sign and authorize. Get the signed agreement and, if you will charge a card or bank account, a separate written authorization.
- Schedule and monitor. Load the schedule into your billing system, set reminders and review plans on a fixed day each week.
What belongs in the written agreement
- Patient and guarantor names, and the total balance the plan covers.
- Down payment, installment amount, due dates and the final payment date.
- A plain statement of any interest or fees. If there are none, say “none”.
- Payment method, the patient’s authorization to charge it, and how to cancel that authorization.
- What happens after a missed payment: grace days, contact steps and when the account moves on.
- How the balance changes if the insurer reprocesses the claim, and how a credit would be refunded or applied.
- A practice contact for questions, the signature date and a copy for the patient.
“A payment plan fails at the first conversation, not the fifth payment. If front-desk staff cannot explain the terms in two sentences, the patient will not sign them.”
— Awais Afzal, Healthcare Operations & Data Analyst
How do you keep a payment plan collecting without chasing patients?
Automate the routine and keep a person for the exceptions. Card-on-file or bank drafts remove the monthly decision from the patient, and a short, fixed missed-payment routine removes guesswork from your staff.
- Autopay with consent. Charge only the amount and dates in the signed authorization, and alert the patient before a card expires.
- Reminders before the due date. Use the patient’s preferred channel and keep the message free of diagnosis or service detail. Ask your compliance lead to approve the message template.
- One routine for a failed payment. Retry once, call the patient, then send a written notice. Review the plan with the patient before it goes to collections.
- Show the plan on the statement. The next due date and remaining balance belong on every statement. See our patient-friendly billing statements guide.
- Post to the right account. Plan payments should post to the patient balance they cover, so aging reports stay accurate.
Are patient balances aging faster than your plans can absorb?
Our free practice audit reviews your patient A/R, statement process and any payment plans in use, and shows where balances stall. Pricing is quoted after the audit.
If your team has no time to run this routine, medical billing services can take statements, payment posting and follow-up while you keep control of the policy and the exceptions.
Which numbers show whether your payment plans are working?
Track six numbers monthly: offer rate, enrollment rate, on-time rate, default rate, days to final payment and aging of plan balances. They show whether the problem is the offer, the terms or the follow-up.
| Metric | Working definition | What it tells you |
|---|---|---|
| Offer rate | Eligible balances offered a plan, divided by all eligible balances | Whether staff make the offer consistently |
| Enrollment rate | Plans signed, divided by plans offered | Whether the terms fit what patients can pay |
| On-time installment rate | Installments paid by the due date, divided by installments due | Whether autopay and reminders work |
| Plan default rate | Plans that miss two scheduled payments in a row, divided by active plans | Whether terms or follow-up need to change |
| Days to final payment | Average days from signing to the last installment | Whether terms are drifting longer |
| Plan balance aging | Open plan balances by days since the last payment | Where follow-up is slipping |
These are our working definitions, not an HFMA or MGMA standard. Set your own targets from your first quarter of data.
Compare your own trend against itself rather than against a published benchmark. To see how patient balances sit within your total revenue, try our revenue calculator.
Our recommendations
- Offer the plan early. We recommend offering a plan with the estimate or at check-in. A plan offered after three unpaid statements competes with every other bill the patient has.
- Write one policy and train from it. Put eligibility, down payment, maximum term and exception approval in a one-page policy. Role-play the two-sentence explanation with front-desk staff.
- Start interest-free. We would start with no interest, no late fees and no credit check, and add any of them only after an attorney has reviewed your state’s rules.
- Keep financing separate from your plan. If you use a lender, label it as the lender’s product. Offer a financial assistance review and your own plan before you present it.
- Use autopay with a signed authorization. Recurring charges remove most missed payments. They need a clear authorization, expiring-card alerts and a set routine for a declined charge.
- Review plans on a fixed day each week. One person checks failed payments, upcoming due dates and balances changed by insurer reprocessing. Weekly review is what stops a small miss from becoming bad debt.
Bottom line
Patient payment plans work when they are offered early, written down, interest-free by default and checked by counsel before launch. Start with a one-page policy, a signed agreement and autopay, and measure enrollment and defaults each month. If patient balances are already aging, A/R management services can help clear the backlog, and you can contact our team with questions about your process.
Frequently asked questions
Does a patient payment plan have to charge interest?
No. Many practices run plans without interest. Adding interest or fees changes the legal analysis, because Regulation Z defines a creditor partly by finance charges and partly by written agreements with more than four installments. Ask a healthcare attorney before you add interest, late fees or credit checks.
How long should a patient payment plan last?
We cannot cite a legal or industry standard for term length. Set a maximum term by balance size in your written policy, start shorter and extend case by case after you review financial assistance. Then watch days to final payment and the default rate to see whether your terms fit.
Should we offer third-party medical financing?
It can suit large planned treatments, but read the terms first. The CFPB’s 2023 report found deferred interest was assessed on about 20% of healthcare deferred-interest purchases from 2015 to 2020. Present any lender product as the lender’s loan, and offer your own plan or financial assistance review first.
Do we need a signed agreement?
We recommend one for every plan. It records the balance, installment amount, dates, any fees and the missed-payment steps, so staff and patient work from the same terms. Add a separate written authorization if you will charge a card or bank account. Have counsel review the form.
Can we charge the patient's card automatically?
Only with the patient’s written authorization that states the amount, the dates and how to cancel. Check your payment processor’s terms and your state’s law as well. Alert patients before a card expires, and keep a standard routine for declined charges.
What if insurance reprocesses a claim after the plan starts?
The patient’s balance can change. Your agreement should say that the plan will be recalculated, and that a credit will be refunded or applied to the remaining installments. Tell the patient in writing when the amount changes.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- 12 CFR 1026.2 Definitions and rules of construction — Cornell Law School Legal Information Institute (current CFR text) (2026)
- FTC releases new guidance for Red Flags Rule — Becker's Hospital Review (2009)
- CFPB report highlights costly credit cards and loans pushed on patients — Consumer Financial Protection Bureau (2023)
- Medical Credit Cards and Financing Plans — Consumer Financial Protection Bureau (2023)
- 2025 Employer Health Benefits Survey, Summary of Findings — KFF (2025)
- The Burden of Medical Debt in the United States — KFF (2024)
- Federal Judge Kills CFPB Rule that Banned Medical Debt in Credit Reports — Checkbook (Washington Consumers' Checkbook) (2025)
Disclaimer: This article is general educational information for medical practice operations. It is not legal, compliance, coding or financial advice. Truth in Lending, identity-theft, credit-reporting and debt-collection rules differ by state and by how a plan is structured. Have a healthcare attorney review your payment plan policy and agreement before use.
