
Gastroenterology billing comes down to one question: was the colonoscopy a screening, or did it turn diagnostic or therapeutic? That answer sets the code, the modifier (PT or KX on Medicare), the patient's cost share and the denial risk. Document the indication and the findings the same day, and most of the rest follows.
Most gastroenterology claims are not hard because the codes are obscure. They are hard because one visit can change category halfway through. A screening colonoscopy that finds a polyp is no longer only a screening. The claim, the patient’s bill and the payer’s edits all change with it. This guide uses Medicare rules from CMS Transmittal 12299, Transmittal 3368 and Noridian’s Part B colorectal screening page as the fixed reference, then shows where commercial plans differ and what to check before a claim leaves your office. If you are comparing in-house billing with an outside team, the last sections explain how to decide. For the specialty overview, see our gastroenterology billing and RCM page.
Key takeaways
- Decide screening or diagnostic from the documentation, then code the claim to match. Do not decide from the schedule.
- On Medicare, a screening colonoscopy that becomes diagnostic or therapeutic takes modifier PT. A colonoscopy after a positive stool test takes KX.
- Medicare pays an incomplete colonoscopy (modifier 53) at one-half the value of the inputs, and has since January 1, 2016.
- Modifier 33 is not recognized by Medicare on colonoscopy or anesthesia codes. Commercial payers set their own rule, so check each payer.
- Most avoidable denials are caught before submission with a short GI-specific checklist.
Screening or diagnostic: the question behind most GI claims
A colonoscopy is billed as screening when it is done for a patient with no symptoms or prior findings, on the screening schedule. It becomes diagnostic or therapeutic when the physician biopsies tissue, removes a lesion, or the visit is for a symptom or a known problem. The same procedure room and the same scope can produce two very different claims.
This matters more than it did a few years ago. The US Preventive Services Task Force recommends colorectal cancer screening for adults 50 to 75 (grade A) and 45 to 49 (grade B), and selective screening for ages 76 to 85 (grade C). More 45-to-49-year-olds on the schedule means more first-time screening patients whose benefits and cost sharing the front desk has to explain correctly.
The practical rule: let the note decide. The order or referral should state the indication. The procedure note should say what was found and what was done. If the two disagree, ask the physician before coding, not after the payer asks.
How Medicare codes each colonoscopy scenario
For Medicare, the scenario picks the code and the modifier. The table below covers the four cases a GI billing team meets daily. It reflects CMS guidance for dates of service on or after January 1, 2023.
| What happened | How it is reported | Modifier | Patient cost share |
|---|---|---|---|
| Screening colonoscopy, nothing found or removed, high-risk patient | G0105 | None | Coinsurance and deductible waived |
| Screening colonoscopy, nothing found or removed, not high-risk patient | G0121 | None | Coinsurance and deductible waived |
| Screening colonoscopy where a biopsy or removal is done | The diagnostic or therapeutic colonoscopy CPT code that matches what was done (for example 45378 for a diagnostic exam) | PT on each CPT code | Deductible waived; coinsurance applies at the scheduled rate (see chart) |
| Colonoscopy after a positive stool test (FOBT, FIT or Cologuard) | G0105 or G0121 | KX | No deductible or coinsurance when it is complete screening with nothing removed |
Source: CMS Transmittal 12299 (2023); CMS Transmittal 3368 (2015); Noridian Medicare Part B colorectal cancer screening page; AGA Medicare coding page.
Two details cause repeat denials. First, KX is a practitioner-applied flag: CMS says the furnishing practitioner must identify the positive-stool-test scenario with KX, and without it Medicare treats the claim under prior policy (CMS). The AGA’s Medicare page adds that without KX, the claim can be returned as unprocessable (AGA). Second, if a polyp is removed or a biopsy taken during that follow-on colonoscopy, the AGA page says to report the matching CPT code with PT rather than KX. Examples of polyp-removal codes it lists include 45380, 45384, 45385 and 45388.
Frequency and coverage limits to check before scheduling
A screening colonoscopy is only payable when the patient is due. Medicare limits how often each screening test is covered, and a claim that ignores the limit is denied at the front end of adjudication, not on appeal.
| Test | Code | Frequency limit | Notes |
|---|---|---|---|
| Screening colonoscopy, high risk | G0105 | Once every 24 months | At least 47 months after a screening flexible sigmoidoscopy |
| Screening colonoscopy, not high risk | G0121 | Once every 10 years | Or 48 months after a screening flexible sigmoidoscopy |
| Flexible sigmoidoscopy | G0104 | Once every 48 months | |
| Fecal occult blood test | 82270 or G0328 | Once every 12 months | Age 45 and older; 82270 or G0328, not both in the same 12 months |
| Multi-target stool DNA (Cologuard) | 81528 | Once every 3 years | Average risk, age 45 to 85 |
| Blood-based biomarker test | G0327 | Once every 3 years | Average risk, age 45 to 85 |
Source: Noridian Medicare Part B colorectal cancer screening page; CMS Transmittal 12299 (2023). Barium enema (G0106, G0120) was removed as a covered screening method effective January 1, 2025.
CMS also counts months strictly. For G0121, coverage is once every 10 years, with at least 119 months after the month of the last covered G0121 (CMS Transmittal 3368). Eligibility tools can show the last paid date. Build the check into scheduling, so the front desk can warn the patient before the appointment, not after the claim denies.
One 2023 change removed a common frequency trap. A screening colonoscopy that follows a positive stool test and carries KX is not denied for frequency limits and does not use up the patient’s next eligible date (CMS).
What the patient owes when screening turns into treatment
When a Medicare screening colonoscopy becomes diagnostic or therapeutic and carries PT, the deductible is waived but coinsurance applies. That coinsurance is being phased out on a published schedule: 15% for calendar years 2023 to 2026, 10% for 2027 to 2029, and none from January 1, 2030 (CMS Transmittal 12299).
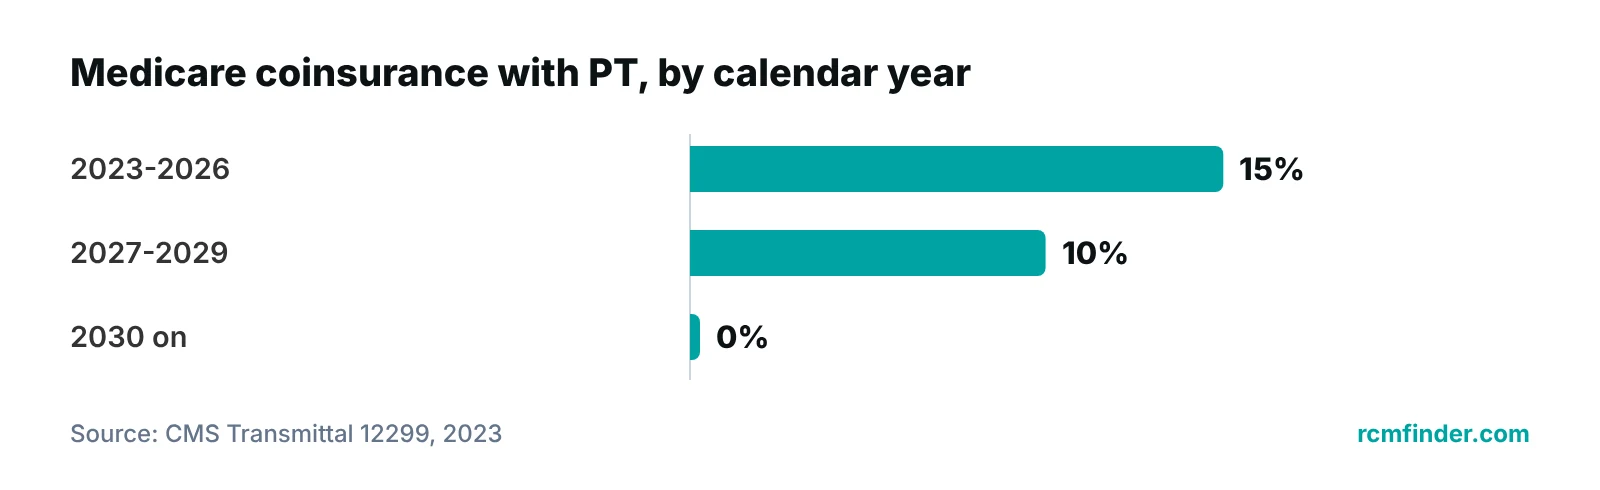
Anesthesia follows a slightly different rule. Anesthesia with a screening colonoscopy (00812) has both coinsurance and deductible waived. Anesthesia with a colonoscopy that became diagnostic (00811 with PT) has only the deductible waived. Moderate sedation reported with G0500 or 99153 and PT also gets only the deductible waiver (Noridian; CMS).
For a practice manager, the takeaway is operational. A patient who expected a free screening can receive a bill after a polyp is removed. Tell patients before the procedure that findings can change the cost share, and have the billing team explain it with the claim in hand.
Incomplete colonoscopies and modifier 53
On Medicare, an interrupted colonoscopy is reported with modifier 53 and paid at one-half the value of the code’s inputs. This rule has applied since January 1, 2016, and covers both diagnostic and screening colonoscopies (CMS Transmittal 3368).
- CMS set specific fee schedule values for 44388-53, 45378-53, G0105-53 and G0121-53.
- Since 2015, CPT defines an incomplete colonoscopy as one that does not evaluate the entire colon, not only one that stops before the splenic flexure.
- Ambulatory surgery centers append modifier 73 or 74 on the facility claim instead of 53.
- If the colonoscopy is later repeated and completed, it is paid under the normal method when coverage conditions are met.
- Keep enough detail in the record to show why the procedure stopped, because the contractor can request it.
Half is the Medicare rule, not a general one. Commercial payers set their own policies for incomplete procedures, so check the payer’s policy before assuming half.
Commercial plans: where the Medicare rules stop
Do not copy Medicare modifiers onto commercial claims without checking. Noridian states that modifier 33 is not recognized for any colonoscopy or anesthesia codes on Medicare (Noridian). Commercial payers set their own modifier rules, so confirm in each payer’s policy whether they expect 33, PT or neither.
What federal rules do say is that cost sharing on integral parts of a preventive screening is restricted. A U.S. Department of Labor FAQ cites earlier guidance that a plan may not impose cost sharing for polyp removal during a preventive screening colonoscopy, and that anesthesia provided with it is covered on the same basis. Plan-specific details depend on the plan type and plan year, so treat this as a reason to dispute a wrong patient bill, not as a coding shortcut.
Verify payer policy in writing
Keep a one-page payer matrix for your top commercial plans: which modifier they want on screening-turned-diagnostic claims, whether prior authorization applies, and how they treat incomplete procedures. Prior authorization rules vary by plan; see our prior authorization guide.
Pre-submission checks that prevent GI denials
Most avoidable denials can be caught by a short, specialty-specific check before the claim goes out. These checks are drawn from the rules above, not from a claim of how often each problem occurs.
| Check | Why it matters | Rule behind it |
|---|---|---|
| Indication matches procedure note | Screening and diagnostic claims are coded differently | Screening vs diagnostic (CMS Transmittal 12299) |
| Biopsy or removal captured | Needs the CPT code plus PT on Medicare, not G0105 or G0121 | CMS Transmittal 3368; AGA |
| KX present on follow-on colonoscopy | Without it the claim follows prior policy or is returned | CMS Transmittal 12299; AGA |
| Frequency and last paid date | Early screenings deny at adjudication | Noridian; CMS Transmittal 3368 |
| Modifier 53 and documentation for stopped exams | Paid at one-half of the inputs on Medicare | CMS Transmittal 3368; MM10937 |
| Anesthesia code and modifier match the colonoscopy | 00812 and 00811 with PT carry different waivers | Noridian; CMS Transmittal 12299 |
Source: CMS Transmittal 12299 (2023); CMS Transmittal 3368 (2015); CMS MLN Matters MM10937 (2018); Noridian; AGA.
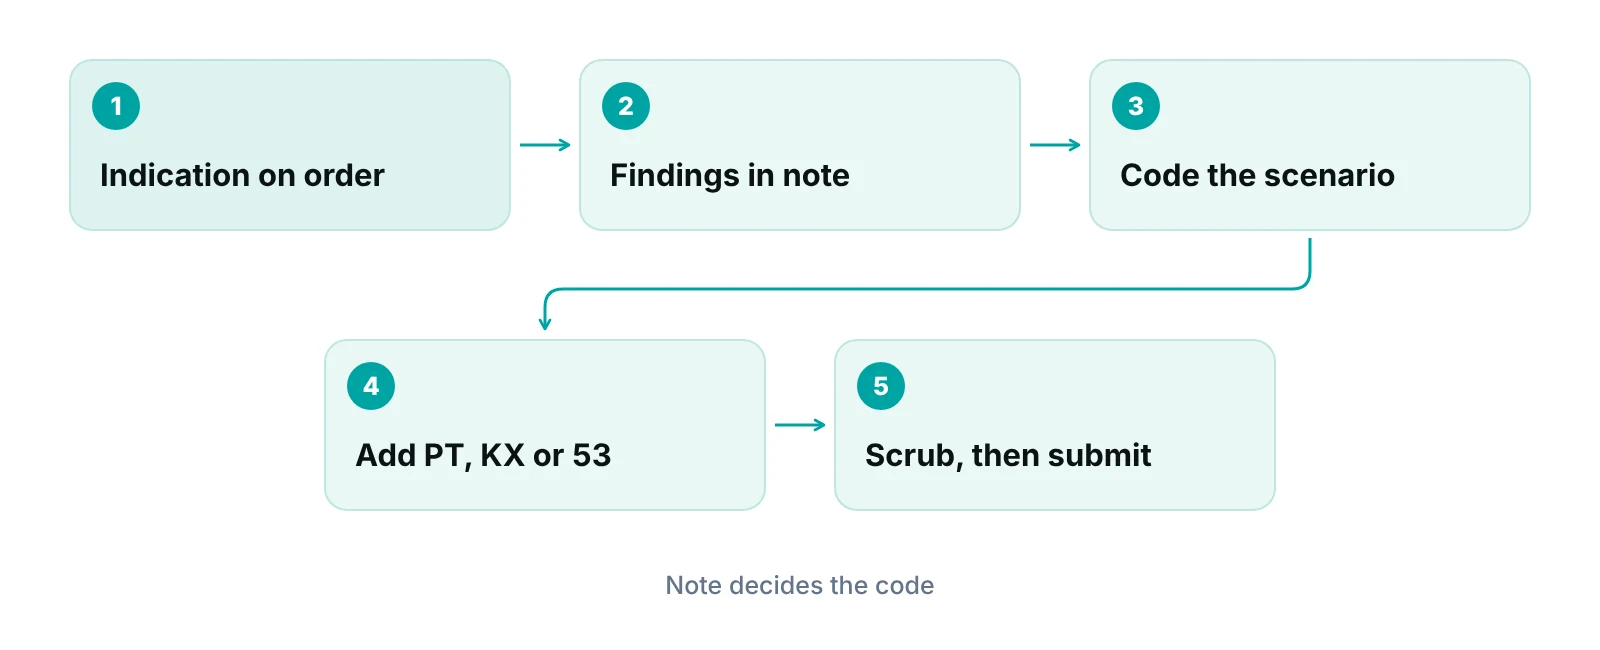
A claim scrubber catches missing modifiers and inconsistent codes before a payer does; see our guides to clean claims and to modifiers 25 and 59. A practice management system that tracks claims by stage with an owner can also hold a claim when required data is missing and flag payments that come in below the expected amount, so underpayments are visible instead of silently written off.
“A modifier is not a patch applied to a finished claim. It is a statement about what happened in the room, and the note has to support it.”
Working GI denials and underpayments
When a GI claim denies, start with the remittance codes, then compare the denial against the note. Group denials by reason, payer and code for a month. Patterns tend to show up quickly: a payer that rejects PT, a frequency edit that nobody checked, or a missing KX.
- Sort denials by cause: eligibility or frequency, coding or modifier, documentation, authorization.
- Fix the front-end cause for each group, not only the individual claim.
- Compare paid amounts to the contract or fee schedule on every remittance to catch underpayments.
- Track the days a claim spends in each stage so no denial sits without an owner.
Our guide to medical billing denial management covers the full appeal workflow. If volume is the issue, outside denial management services handle appeals while your team fixes the front end.
In-house, outsourced or hybrid: how to decide
The right model depends on your volume, your staff’s GI experience and how much control you want over payer follow-up. Be wary of any claim that outsourcing always raises revenue. No honest vendor can promise that outcome.
- In-house fits when you have a coder who knows endoscopy, a written payer matrix and time to work denials weekly.
- Outsourced fits when coding turnover, A/R backlog or denial volume is outrunning your team. A medical billing services partner takes the full cycle.
- Hybrid fits when you want to keep charge entry and patient contact but hand off denials and A/R follow-up.
See where your GI claims are leaking
Ask for a free practice audit and we will review how your screening, diagnostic and incomplete colonoscopy claims are coded and followed up. Pricing, if you want help, is quoted after the audit.
What to ask any billing vendor
Ask every vendor the same questions, in writing. The answers matter more than the sales pitch.
- Will you sign a Business Associate Agreement before accessing patient data? HIPAA requires one for vendors that handle protected health information. See our HIPAA compliance checklist.
- Who codes GI claims, and what credentials and endoscopy experience do they hold?
- How do you handle screening-turned-diagnostic claims, KX and modifier 53?
- What do you report each week, and who owns each stage of a claim?
- How do you detect and dispute underpayments?
- Can you work inside the EHR we already use?
Our recommendations
- Code from the procedure note, not the schedule. Make the findings and any biopsy or removal visible to the coder before the claim is built.
- Build a screening-versus-diagnostic rule into the charge workflow. Require a documented choice, so G0105 or G0121 is never defaulted when tissue was taken.
- Check frequency before the appointment. Look up the last paid screening date when the patient books, and warn them if they are not due.
- Set KX and PT as required fields. Prompt for them when the indication is a positive stool test or when findings change the procedure.
- Warn patients that findings can change their bill. Explain before the procedure that a biopsy or removal can bring coinsurance on Medicare and may change cost sharing on other plans.
- Keep a one-page payer matrix. Record each top payer’s modifier, prior authorization and incomplete-procedure rules, and review it at least twice a year.
- Review denials and underpayments monthly. Group by cause and payer, fix the front-end cause and compare paid amounts to the expected amount.
Track GI claims by stage so screening-turned-diagnostic claims do not stall.
The RCM Finder portal tracks each claim by stage with an owner, checks data completeness before submission and flags payments below the expected amount. It works alongside the EHR you already use.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Gastroenterology billing rewards teams that decide screening versus diagnostic early and document it clearly. Code from the note, apply PT, KX and 53 where Medicare requires them, and verify each commercial payer’s rules instead of assuming. If denials are piling up, our denial management services can trace the pattern, and the revenue calculator shows what unpaid claims may be costing your practice.
Frequently asked questions
What is the difference between screening and diagnostic colonoscopy billing?
A screening colonoscopy is for a patient without symptoms or prior findings, on the screening schedule. It becomes diagnostic or therapeutic if tissue is biopsied or removed. On Medicare, the claim then uses the matching CPT code with modifier PT instead of G0105 or G0121, and coinsurance can apply.
When do I use modifier PT versus KX?
On Medicare, PT goes on the CPT code when a screening colonoscopy converts to diagnostic or therapeutic. KX goes on G0105 or G0121 when a screening colonoscopy follows a positive stool-based test and nothing is removed. If a polyp is removed after a positive stool test, the AGA’s guidance is to use PT, not KX.
How does Medicare pay an incomplete colonoscopy?
Since January 1, 2016, Medicare pays an interrupted colonoscopy, reported with modifier 53, at one-half the value of the code’s inputs. Ambulatory surgery centers use modifier 73 or 74 instead. Commercial payers set their own rules, so check each plan’s policy.
Does modifier 33 apply to colonoscopy claims?
Not on Medicare. Noridian states that modifier 33 is not recognized for any colonoscopy or anesthesia codes. Commercial payers set their own modifier rules, so confirm in the payer’s policy whether 33, PT or no modifier is expected.
How often can Medicare cover a screening colonoscopy?
Once every 24 months for high-risk patients (G0105) and once every 10 years for patients not at high risk (G0121), with month counting rules and shorter waits after a screening sigmoidoscopy. A colonoscopy after a positive stool test billed with KX is not subject to those frequency limits.
Should a GI practice outsource its billing?
It depends on volume, denial rates and in-house coding experience. Compare in-house, outsourced and hybrid models, and ask any vendor for a Business Associate Agreement, GI coding experience and weekly reporting. No vendor can honestly guarantee higher revenue, so ask for a practice audit first.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Colorectal Cancer Screening (Medicare Part B) — Noridian Healthcare Solutions (JF Part B) (2026)
- Transmittal 12299 (CR 13017), Pub. 100-04 Chapter 18 — CMS (2023)
- Transmittal 3368 (CR 9317), Incomplete colonoscopy payment — CMS (2015)
- MLN Matters MM10937, Incomplete colonoscopy — CMS (2018)
- Medicare coding guidance for follow-on colonoscopy — American Gastroenterological Association (2023)
- Colorectal Cancer: Screening (recommendation statement) — US Preventive Services Task Force (2021)
- FAQs about Affordable Care Act Implementation Part 54 — U.S. Department of Labor, EBSA (2022)
Disclaimer: This article is educational and is not legal, coding, clinical or compliance advice. Medicare and payer rules change and vary by contractor and plan. Confirm every code, modifier and frequency rule against current CMS, AMA CPT and payer policy before you bill.
