
Knee pain ICD-10 codes come from category M25.56-: M25.561 for the right knee, M25.562 for the left and M25.569 for an unspecified knee. There is no bilateral code in that family, so report both sides when both are documented. Once the provider confirms a diagnosis that explains the pain, the diagnosis is coded instead.
Older guides on this topic often stop at two codes, mix up left and right, or pair diagnosis codes with the wrong side. This guide sticks to what the official guidelines say and tells you where to check the rest.
It covers the three symptom codes, how the laterality rule works, when a symptom code is the wrong choice and what to check before the claim goes out. For other body regions, see our posts on back pain ICD-10 codes and neck pain ICD-10 coding.
Key takeaways
- M25.561 is right knee pain, M25.562 is left knee pain and M25.569 is unspecified knee pain.
- No bilateral code is listed in M25.56-, so both knees get a code each when both are documented.
- If the side is not in the record, the unspecified code applies, but the guidelines say to query the provider when possible.
- A symptom code fits only when no related definitive diagnosis has been confirmed.
- FY 2027 codes apply to services from October 1, 2026 through September 30, 2027.
Which ICD-10 code reports knee pain?
Knee pain sits under M25.5, pain in joint, and the knee has its own subcategory, M25.56. That subcategory has three codes, one for each side and one for when the side is not known. A CMS-listed value set published through the National Library of Medicine shows exactly these codes (NLM VSAC value set, CMS DRLS Steward).
These are symptom codes. They describe what the patient reports, not why it hurts. That matters because payers and auditors read a symptom code as a placeholder for a diagnosis the provider has not reached yet.
| Code | Meaning | Use when |
|---|---|---|
| M25.561 | Pain in right knee | The record says the right knee hurts and no related diagnosis is confirmed |
| M25.562 | Pain in left knee | The record says the left knee hurts and no related diagnosis is confirmed |
| M25.569 | Pain in unspecified knee | The record does not say which knee. Query the provider first when you can |
| M25.56 | Pain in knee (category) | Not reportable on its own. Choose one of the three codes above |
Source: CMS DRLS Steward, Pain in Joint Disorder ICD10CM value set, via the National Library of Medicine VSAC (accessed 2026). Confirm in the FY 2027 Tabular List.
The code set changes each year. The CDC lists the FY 2027 ICD-10-CM release as applying to services from October 1, 2026 through September 30, 2027 (CDC NCHS ICD-10-CM files). Check your coding tool is on that release before you rely on any code in this guide.
How do you code left, right and bilateral knee pain?
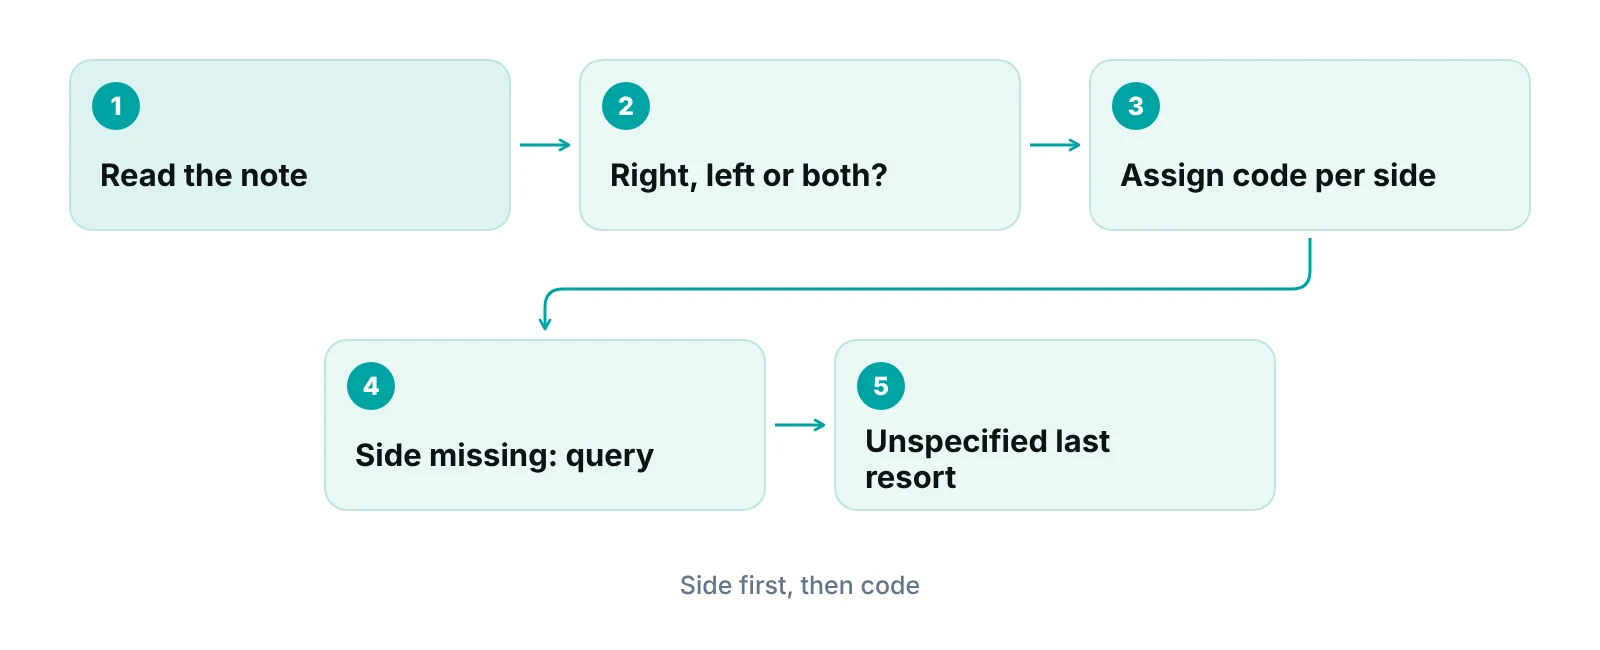
Report the side the provider documents. When both knees hurt and the classification has no bilateral code, assign a separate left and right code. The CDC FY 2027 ICD-10-CM Official Guidelines state this in Section I.B.13.
In practice that gives three cases for knee pain:
- Right only: M25.561.
- Left only: M25.562.
- Both knees: M25.561 and M25.562 on the same claim, since M25.56- has no bilateral code.
Old guides often present bilateral knee pain as a single choice between the two codes. It is not. Reporting only one side understates the visit and can leave the second knee unsupported if you later treat it.
What if the side is not documented?
The guidelines say that if the side is not identified in the medical record, you assign the unspecified-side code. They also say that code should rarely be used and that the provider should be queried when possible. Treat M25.569 as a gap in the note to close, not a normal choice. The guidelines also allow laterality to be taken from other clinicians’ documentation, and conflicting documentation calls for a query.
What about treating one knee at a time?
When each side is treated at a separate encounter, the guidelines say the bilateral reporting applies at the first encounter. At later encounters, after the first side no longer has the condition, you report the code for the side still affected. The guideline is written for conditions with a bilateral code, so for knee pain apply it with care: report what the provider documents for each visit, and confirm the approach with your payer if a split-side plan of care is common in your practice.
When is a knee pain code the wrong choice?
A knee pain code is the wrong choice when the provider has confirmed a diagnosis that explains the pain. Signs and symptoms are reported when a related definitive diagnosis has not been established, and symptoms that routinely come with a disease are not coded separately unless the classification says otherwise (Sections I.B.4 and I.B.5 of the guidelines).
Knee osteoarthritis is the common example. It has its own category, M17, with separate codes for different forms of the disease (NLM VSAC Knee Osteoarthritis value set, Optum Steward). If the provider documents osteoarthritis of the knee as the reason for the pain, the M17 code carries the visit and M25.56- is generally not added for the same pain. Check the Excludes notes in the Tabular List for the exact instruction.
“A symptom code is a holding place. When the diagnosis arrives, the code should move with it.”
The same logic applies to other causes: a meniscus problem, a ligament injury, a fracture, gout or bursitis each has its own diagnosis codes. Older versions of this page listed several of those with incomplete characters or the wrong side, so this guide does not reprint them. Look each one up in the current Tabular List, and note that injury codes in Chapter 19 need a seventh character; the guidelines require any seventh character the Tabular List calls for, with an X placeholder in empty positions (Section I.A.5).
We cover the same symptom-versus-diagnosis decision for another complaint in our guide to chest pain ICD-10 codes, and for a fall that causes injury in ground-level fall ICD-10 codes.
Do not code a suspected cause
If the note says only that pain is present, code the pain. Do not pick a diagnosis code the provider has not documented because the exam or imaging order suggests it. Coders cannot supply a diagnosis. Query the provider.
What does the note need to support the code?
The note needs the side, the complaint in the provider’s words and either a confirmed diagnosis or a clear statement that the cause is not yet determined. Those three items decide which code is correct.
Knee pain is seen across several settings, which is why the same patient can be coded differently on the same day. Primary care, urgent care, physical therapy and orthopedic practices all report these codes, and each may reach a different point in the work-up. Match the code to what that provider documented at that visit.
| Situation | What to report | Guideline section |
|---|---|---|
| Pain in one knee, no confirmed cause | M25.561 or M25.562 for the documented side | I.B.4 (signs and symptoms) |
| Pain in both knees, no bilateral code | Separate right and left codes | I.B.13 (laterality) |
| Side not stated in the record | Unspecified-side code, after trying to query | I.B.13 (laterality) |
| Pain is part of a confirmed disease | Code the disease, not the routine symptom | I.B.5 (integral conditions) |
| Second knee treated at a later visit | Code for the side still affected | I.B.13 (laterality) |
Source: CDC, ICD-10-CM Official Guidelines for Coding and Reporting, FY 2027 (effective October 1, 2026).
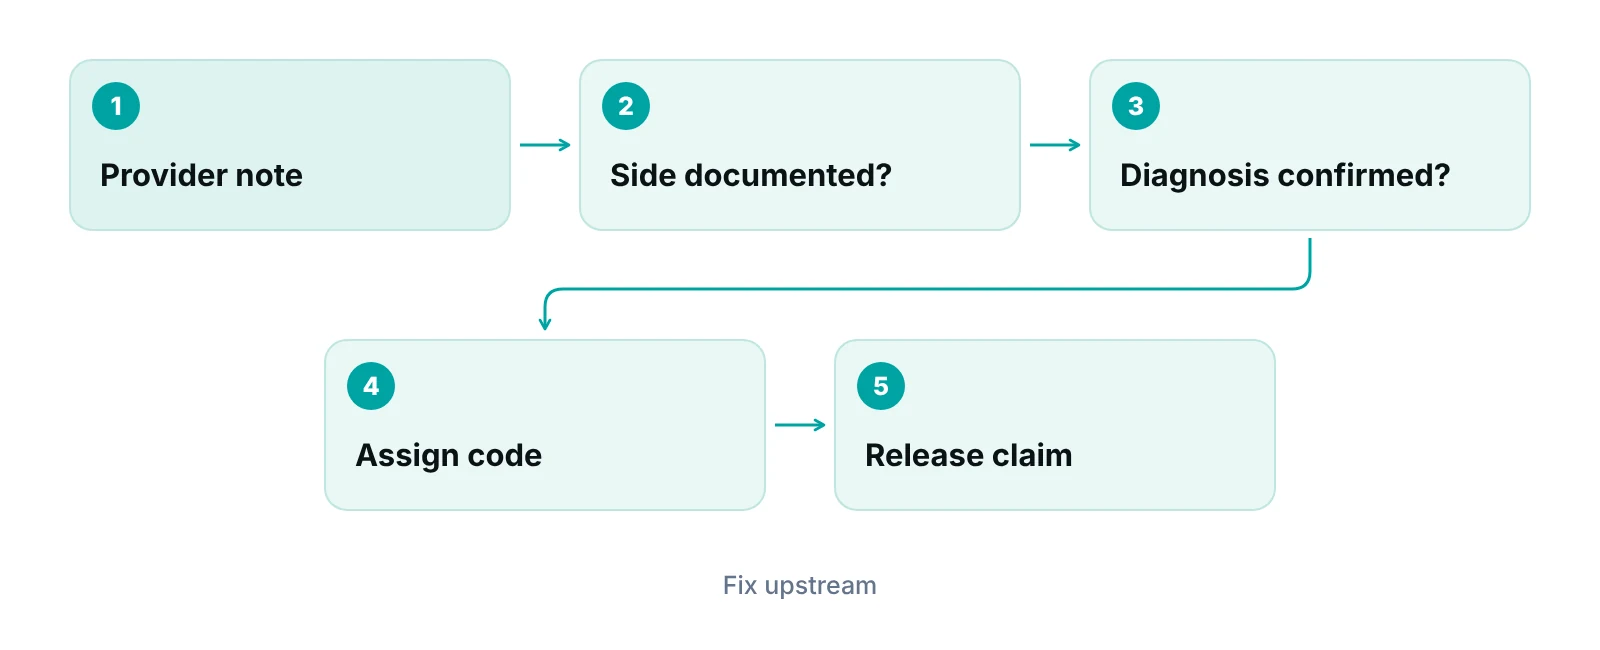
A short template helps: a field for the affected side, a field for whether a diagnosis is established and, if not, a line stating the working impression is symptom only. Templates that default the side to blank prevent a wrong side from being pre-filled.
Also keep the code and the procedure in agreement. If the note documents an injection, therapy session or imaging study on one knee, the diagnosis on that line should name the same knee. A reviewer comparing the claim line with the note will see the mismatch at once, and it is much easier to prevent at charge entry than to explain in an appeal.
How do knee pain coding errors turn into denials?
Knee pain coding errors usually turn into denials through three routes: a symptom code that does not support the procedure billed, a side that conflicts with the procedure or the note, and an unspecified code that a payer edit flags. Edits and policies differ by payer, so the exact rule depends on the plan.
- Symptom code with a diagnostic or therapeutic service: some payer policies expect a more specific diagnosis for imaging, injections or therapy. Check each payer’s policy rather than assuming.
- Side mismatch: a left-knee code on a claim where the note or procedure documents the right knee is a preventable error.
- Unspecified code: M25.569 is accepted as valid, but it signals missing documentation and invites review.
These errors are cheaper to fix before submission. Our guide to clean claims in medical billing explains how front-end edits catch them, and a periodic review of medical coding audits shows whether the same mistake repeats. For joint-related surgery coding, see joint replacement billing and coding.
When denials do arrive, sort them by cause instead of resubmitting blindly. A practice can also use outside medical billing services to review diagnosis coding before claims are sent.
Want a second set of eyes on your diagnosis coding?
A free practice audit looks at how your claims move from the note to payment and where diagnosis and laterality errors start. Pricing, if you decide to go further, is quoted after the audit.
What should you check before a knee claim goes out?
Check four things: the side, whether a diagnosis is confirmed, whether the code set is current and whether the code supports the service billed. A short checklist at the charge-entry step costs less than rework after a denial.
| Check | What to look for | Who fixes it |
|---|---|---|
| Side | Right, left or both is written in the note | Provider (query) or coder |
| Diagnosis status | Confirmed diagnosis present, or note says symptom only | Provider |
| Code release | Code is valid for the date of service under the FY 2027 release | Coder or billing system |
| Service match | Diagnosis supports the procedure or visit per the payer’s policy | Biller |
| Duplicate pain code | M25.56- not added beside a diagnosis that explains the pain | Coder |
Run this check on a sample of knee claims each quarter. If one row fails repeatedly, the cause is usually a template or a missing step, not individual error.
Our recommendations
- Make the side a required field. We recommend a required right, left or both field in every knee visit template, with no default. A blank side is the main source of M25.569 claims.
- Query before using M25.569. The guidelines say the unspecified code should rarely be used and the provider should be queried when possible. Build the query into the coding workflow so it is routine, not an exception.
- Move the code when the diagnosis moves. When a later note confirms the cause, retire the symptom code on that and future claims. Keep a note in the account so the change is traceable.
- Rebuild reference sheets from the current release. Cheat sheets copied from old web pages carry wrong side and wrong character errors. Rebuild each from the Tabular List for the current fiscal year and date them.
- Review knee claims by cause each quarter. Sort denials and corrections by side, symptom-versus-diagnosis and payer. Patterns point to a template or training fix.
Bottom line
Knee pain ICD-10 codes are M25.561, M25.562 and M25.569, and the note decides which applies. Report both knees separately, query before using the unspecified code, and replace the symptom code once a diagnosis is confirmed. If knee claims keep coming back for diagnosis or side errors, our denial management services can sort them by cause, or you can talk to our team or request a free practice audit.
Frequently asked questions
What is the ICD-10 code for left knee pain?
M25.562 is pain in the left knee. Use it when the record says the left knee hurts and no related diagnosis has been confirmed. If the provider has confirmed a cause such as osteoarthritis, code that diagnosis instead and check the Tabular List for the correct side.
What is the ICD-10 code for right knee pain?
M25.561 is pain in the right knee. The same rule applies as for the left: it is a symptom code, so it fits only when no related definitive diagnosis has been established for that knee. If the side is missing from the note, query the provider before choosing between this code and the unspecified one.
Is there a bilateral knee pain ICD-10 code?
Not in M25.56-. The subcategory lists right, left and unspecified codes only. When both knees are documented, the guidelines say to assign separate left and right codes, so report M25.561 and M25.562 together.
When should M25.569 be used?
Only when the side is not identified in the record. The guidelines say unspecified-side codes should rarely be used and that the provider should be queried when possible. A frequent M25.569 is a sign that the visit template is missing a side field.
Can I report knee pain and knee osteoarthritis together?
Generally no for the same pain. Symptoms that routinely accompany a confirmed disease are not coded separately unless the classification says otherwise. Check the Excludes notes in the Tabular List and the payer’s policy, and query the provider if the note is unclear.
Do these codes change every year?
The ICD-10-CM code set is updated each fiscal year. The FY 2027 release applies to services from October 1, 2026 through September 30, 2027. Confirm each code in your coding tool for the date of service rather than relying on a saved list or an old web page. Pages written before the current release may show outdated codes.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- ICD-10-CM Official Guidelines for Coding and Reporting, FY 2027 (October 1, 2026) — CDC National Center for Health Statistics (2026)
- Comprehensive listing of ICD-10-CM files — CDC National Center for Health Statistics (2026)
- 2027 ICD-10-CM files — CMS (2026)
- Pain in Joint Disorder ICD10CM value set (us.nlm.vsac) — CMS DRLS Steward via National Library of Medicine VSAC (2024)
- Knee Osteoarthritis I10 value set — Optum Steward via National Library of Medicine VSAC (2024)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. ICD-10-CM codes, guidelines and payer policies change each year and vary by payer. Verify codes in the current Tabular List and with your payers before you bill.
