
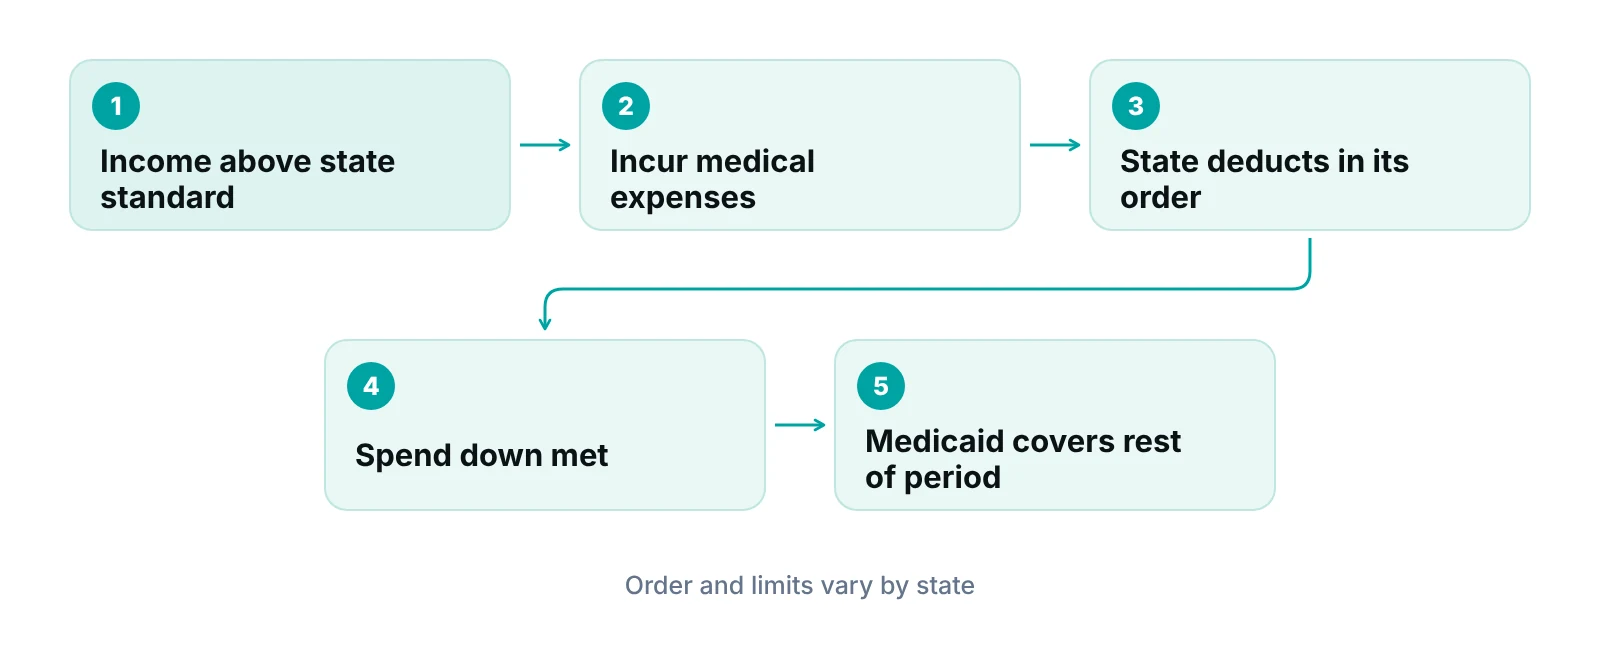
Medicaid spend down lets a person with income above a state's limit qualify by deducting incurred medical bills and health insurance costs from that income. Once the deducted expenses cover the gap, Medicaid pays for care for the rest of the budget period. Which expenses count, and for how long, depends on the state.
This guide is written for practice managers, front desk staff and billers, and for the families they talk to. It follows the federal rule first, then flags what each state decides. An earlier version of this page listed debt payments and funerals as qualifying expenses; those claims could not be verified and have been removed.
Key takeaways
- Spend down subtracts incurred medical and insurance costs from excess income until it reaches the state’s income standard.
- Premiums, deductibles, copays and necessary medical and remedial services are the expenses federal rules require states to count.
- Budget periods run one to six months, and the order bills are applied is a state choice.
- Debt payments, prepaid funerals and gifts are not on the federal list and can create look-back problems.
- Expenses used to meet a spend down are not reimbursable by Medicaid, so practices need to verify coverage by date of service.
What Medicaid spend down is
Spend down is a way to qualify for Medicaid when income is too high. The Medicaid.gov guidance on excess income describes it as reducing countable income by incurred medical and remedial care expenses until it falls to or below the state’s income standard. It is most often tied to the medically needy pathway, which lets states cover people who would otherwise qualify for Medicaid but have income above the usual limit.
It also applies in some states that use stricter rules than the federal SSI program, known as 209(b) states. Those states must let people who are 65 or older, blind or disabled use incurred medical expenses to spend down. Not every state runs a spend down. Each state decides whether to offer the medically needy pathway and how to run it, so the first question for any patient is always which state’s rules apply.
This matters beyond the patient. Spend down is common among older adults and people with disabilities, and KFF reported that in 2021 about 0.9 million dual-eligible enrollees, 23% of all Medicaid enrollees in those pathways, were covered through medically needy pathways. A practice that sees these patients will meet spend down at the front desk, in the billing queue and on the phone.
How the spend down math works
The spend down is the gap between countable income and the state’s income standard, measured over a budget period. Each state sets that period between one and six months. With a one-month period, the person meets the spend down every month. With a longer period, the income standard and the person’s income are both multiplied by the number of months, and the difference is the liability, according to the Medicaid.gov guidance.
The guidance gives a worked example. A person has $600 in monthly countable income and the state’s medically needy income level is $400. Over a one-month budget period the spend down is $200. Over six months it is $1,200, which is $3,600 minus $2,400. The monthly gap is the same, but a longer period lets the person reach the target with bills spread across several months.
| Budget period | Income counted | Standard counted | Spend down |
|---|---|---|---|
| 1 month | $600 | $400 | $200 |
| 3 months (same method) | $1,800 | $1,200 | $600 |
| 6 months | $3,600 | $2,400 | $1,200 |
Source: Medicaid.gov, Handling Excess Income: Spenddown (the 1-month and 6-month rows are from the guidance; the 3-month row applies the same method). Numbers are illustrative, not a state’s actual limits.
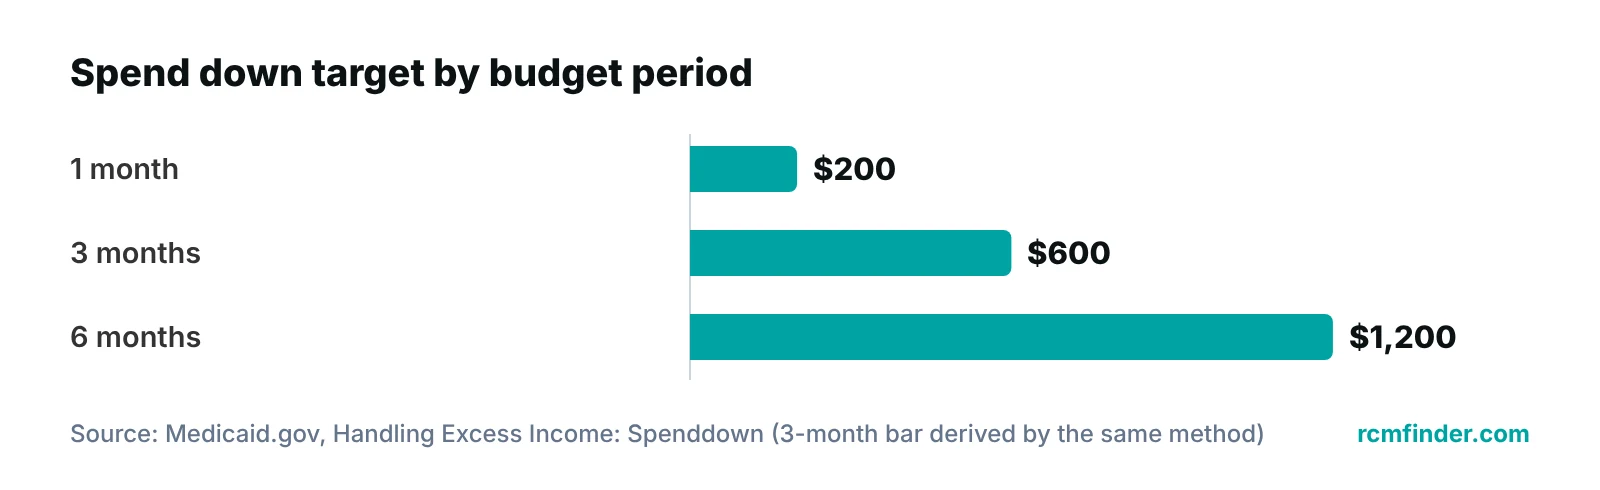
Once the person has incurred enough qualifying expenses, the guidance says Medicaid provides medical assistance for the remainder of the budget period. The start date depends on the state. In partial-month states, eligibility starts the day the deductions bring income down to the standard. In full-month states, it starts on the first day of the month in which the spend down is met.
Which expenses count toward a Medicaid spend down
Federal rules require states to count medical and health insurance costs that the person or family is liable for and that no third party pays. Under 42 CFR 435.831, an expense is incurred on the date liability for it arises. States must deduct three groups of costs, and may add others.
| Type of expense | Treatment | What it covers |
|---|---|---|
| Health insurance costs | Required | Medicare and other health insurance premiums, deductibles, coinsurance, enrollment fees and copayments |
| Necessary services outside the state plan | Required | Necessary medical and remedial services recognized under state law but not covered by the Medicaid plan |
| Necessary services inside the state plan | Required | Necessary covered services, including amounts above the plan’s limits on amount, duration or scope |
| Institutional care and predictable costs | State option | Non-acute institutional expenses and reasonably constant costs such as prescription drugs, projected at the Medicaid rate |
| Bills paid by a third party | Generally not counted | An expense another payer covers is not the person’s liability |
Source: 42 CFR 435.831(d), (e) and (g) via Cornell LII; Medicaid.gov, Handling Excess Income: Spenddown (2021 guidance).
In plain terms, three things almost always count: unpaid or paid bills from doctors, hospitals and other providers for needed care; prescriptions and other needed medical items the state allows; and premiums and cost sharing for Medicare or other health coverage. States may place reasonable limits on some of these categories, but the guidance says a state cannot impose an accumulative dollar limit.
Can old bills count?
Often yes, but it depends on the state. The guidance says 209(b) states may not limit the age of expenses, provided the expense has not already been used and the person is still liable or paid it in the current budget period. Other states may limit the age of expenses, but must allow expenses from the three months before the application. Unpaid expenses can also carry over from earlier budget periods under set conditions.
In what order are bills applied?
The state picks one method and uses it consistently. The rule allows ordering by type of service (insurance cost sharing first, then non-plan services, then plan services), by date of service, or by the date the bill was submitted. Two patients with identical bills can therefore reach their spend down on different dates in different states.
Expenses people assume count (and what to check)
Mortgage or credit card payments, prepaid funerals and home repairs are not on the federal list of required spend down deductions. Many online guides, including an earlier version of this page, listed them as qualifying. Treat any such claim as unverified until the patient’s state Medicaid agency confirms it in writing.
Do not tell a patient these count
The federal rule for income spend down names medical and remedial expenses and health insurance costs. It does not list debt repayment, rent, utilities or groceries. Prepaid funerals and home changes belong to asset planning or to state-specific rules, if they count at all. Send the patient to the state agency or a benefits counselor before any large purchase.
The word remedial is why edge cases exist. The rule counts necessary medical and remedial services recognized under state law, so a state may decide that some non-clinical items, such as certain equipment or transportation to care, qualify. That is a state decision. This page does not list them, because the sources checked here do not confirm which states count which items.
“A spend down counts what a person is liable for in medical bills and health coverage costs. Everything else is a question for the state agency.”
Spend down, share of cost and asset planning are different things
Three terms get mixed up, and mixing them causes costly mistakes. Income spend down reduces countable income with medical bills. Share of cost is California’s version of the same idea. Asset planning is a separate set of rules about resources and gifts.
| Term | What it is | Why it matters |
|---|---|---|
| Income spend down | Medical expenses deducted from excess income over a budget period of one to six months | Once met, Medicaid covers the rest of the period |
| Share of cost (California) | A monthly amount a Medi-Cal member pays toward care before Medi-Cal pays, like a monthly deductible | If no services are received in a month, nothing is owed |
| Pay-in option | A state option letting a person pay the spend down amount to the state | States cannot require anyone to use it |
| Asset transfers and look-back | Medicaid long-term care looks back 60 months for gifts or transfers below fair market value | A transfer can trigger a period of ineligibility for long-term care |
Sources: Medicaid.gov (2021), DHCS All County Welcome Letter I-23-61 (2023), CMS State Medicaid Director letter on the Deficit Reduction Act (2006).
California’s DHCS member insert explains share of cost as a monthly deductible: the member pays for care until the share of cost is met, and Medi-Cal pays covered services after that for the month. Its example starts at $2,000 gross income and ends at a $1,235.10 share of cost after allowed deductions and a $600 maintenance need. Those are 2023 figures, so use them as an illustration only. The insert also says old unpaid medical bills can be applied to the share of cost.
Asset reduction is where families get hurt. For transfers made on or after February 8, 2006, the CMS letter on the Deficit Reduction Act states a 60-month look-back. A transfer for less than fair market value can trigger a period of ineligibility for long-term care, calculated by dividing the transferred value by the state’s average monthly private-pay nursing facility cost. Spending savings on renovations or gifts to relatives is not the same as paying medical bills, so a family should get state or legal advice before moving assets.
What spend down means for a practice's front desk and billing
A spend down patient is on Medicaid only part of the time, so coverage can switch on and off within a budget period. Federal rules also say expenses used to meet a spend down are not reimbursable by Medicaid. The practice may be asked for itemized statements, and some of its charges will be the patient’s responsibility, not a Medicaid claim.
This matters most in practices that serve older adults and people with long-term conditions, such as those covered by a geriatrics billing and RCM page. These patients often have Medicare and Medicaid at once, and the spend down status can change from month to month.
- Verify Medicaid status on the date of service, not only at registration. See our guide to patient insurance verification and the best practices for eligibility and benefits verification.
- Flag the patient account as spend down so billing knows a visit may count toward the patient’s liability rather than a claim.
- Give itemized statements with date of service, service description and amount on request. Patients need them for their caseworker.
- Bill Medicaid only when coverage is active on the date of service. Review Medicare and Medicaid billing tips for payer rules.
- Keep patient balances visible. Our posts on improving patient collections and self-pay patient billing cover the follow-up.
Clean handoffs between registration and billing keep these accounts from stalling. A practice that wants help can look at medical billing services for the claim side. Some practices also use a practice management system that tracks claims by stage so each spend down account has an owner and a visible status.
Want a second pair of eyes on Medicaid accounts?
Our free practice audit looks at how your front desk and billing team handle eligibility changes, patient balances and Medicaid claims.
Our recommendations
- Confirm the state first. Spend down rules, budget periods and allowed expenses are set by each state’s Medicaid agency. Write down the state and the patient’s caseworker contact before advising anything.
- Never promise that an expense counts. Say that the state decides. Point the patient to the caseworker and to the written notice that shows the spend down amount.
- Keep bills and proof of payment together. Itemized statements, receipts, insurance explanations of benefits and premium notices are the evidence a caseworker asks for.
- Re-check coverage on every date of service. A patient can be eligible after the spend down is met and not before. Check the date, not only the card.
- Separate asset questions from medical bills. If a family asks about gifts, renovations or moving property, refer them to the state agency, a benefits counselor or an elder law attorney because of the 60-month look-back.
- Make one person own spend down accounts. Assign an owner and a status so these accounts do not sit in an unbilled queue.
A practice management system can give spend down accounts an owner and a status.
The RCM Finder portal tracks claims by stage with an owner and applies workflow rules, so accounts that need follow-up are flagged for review instead of sitting unbilled.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Medicaid spend down is a state-run way to turn medical bills into Medicaid coverage, and the rules for what counts are narrower than many online lists suggest. Practices that verify coverage by date of service and keep clear patient balances protect both patients and revenue. If you want help with this, see our accounts receivable management services or estimate what unresolved accounts cost with the revenue calculator.
Frequently asked questions
Do mortgage payments, credit card balances or prepaid funerals count toward a Medicaid spend down?
Not under the federal income spend down rule, which names medical and remedial expenses and health insurance costs. Debt repayment is not on that list. Prepaid funerals and home changes fall under asset planning or state-specific rules, if at all. Ask the state Medicaid agency in writing before spending money on any of them.
How long do I have to meet a spend down?
The state sets a budget period between one and six months. With a one-month period, the spend down is met each month. With a longer period, the target is multiplied by the number of months and bills can be spread across it. Ask the caseworker which period applies in your state.
What happens if the spend down is not met?
Medicaid does not start paying for that budget period until the person has incurred enough qualifying expenses. Once the amount is met, Medicaid provides medical assistance for the rest of the period. Some states start coverage the day it is met; others start it on the first day of that month.
How do I calculate a spend down amount?
Subtract the state’s income standard from countable income. For a multi-month budget period, multiply both by the number of months first. For example, $600 income against a $400 standard is a $200 spend down for one month, or $1,200 over six months. Your state’s countable income rules decide what is counted.
Does spend down qualify someone for Medicare Extra Help?
Medicare.gov says people with full-benefit Medicaid, Medicare Savings Program help or SSI get Extra Help automatically. Everyone else can apply, and the 2026 limits are $23,940 income and $18,090 resources for an individual. Whether a person with an unmet spend down counts as having full-benefit Medicaid that month is a question for the state or Social Security.
Does Medicaid pay a provider for the bills used to meet a spend down?
No. Federal rules say expenses used to meet a spend down are not reimbursable by Medicaid, and states must reduce provider charges as needed so the spend down is not passed to Medicaid. A practice should treat those amounts as patient responsibility and ask the state how it handles them.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- 42 CFR 435.831 Income eligibility — Legal Information Institute, Cornell Law School (eCFR text) (2026)
- Handling Excess Income: Spenddown — Medicaid.gov (CMS) (2021)
- Share of Cost insert (All County Welcome Letter I-23-61) — California DHCS (2023)
- Deficit Reduction Act sections 6011 and 6016 (SMD letter enclosure) — CMS / HHS (2006)
- Get Extra Help paying for Medicare drug costs — Medicare.gov (2026)
- Primary Medicaid eligibility pathways for dual-eligible individuals — KFF (2021)
Disclaimer: This article is for education only. It is not legal, financial, coding or compliance advice, and it does not tell any person whether they qualify for Medicaid. Spend down rules, budget periods and income standards differ by state and change over time. Confirm details with the state Medicaid agency.
