

Medicare reimbursement for physician services is set by the Physician Fee Schedule formula, not negotiated, so a practice improves payment by getting every claim coded, documented, filed and paid correctly. The rate is fixed; accuracy is not. CMS finalized higher 2026 conversion factors and has proposed lower 2027 values.
Many articles promise ways to ‘maximize’ Medicare rates. That framing misleads, because the fee schedule amount is the same for every practice in a locality. This guide replaces it with how the formula works, what changed for 2026 and 2027, and which parts of the claim process a practice can control.
It is written for owners and managers deciding whether to fix the process in-house, add software or bring in outside help. See also our Medicare and Medicaid billing tips for day-to-day tactics.
Key takeaways
- Medicare sets physician payment by formula (RVUs x geographic factor x conversion factor); a practice cannot negotiate it.
- The 2026 conversion factor is $33.40 or $33.57; CMS has proposed $32.84 or $33.17 for 2027, not yet final.
- Code to the documentation, not to the highest level; both upcoding and down-coding cost money.
- Claims generally must be filed within one calendar year of the date of service.
- Compare every remittance with the expected amount; that is where payment leaks are found.
How is Medicare reimbursement set?
Medicare sets the payment for most physician services by formula, not by negotiation. A practice cannot bargain the rate up, so the useful questions are whether each claim was built correctly and whether each payment matched the formula. That is where most controllable money sits.
Under the federal rules for the Medicare Physician Fee Schedule (PFS), the amount for a service is the product of three numbers: the relative value units (RVUs) for the service, a geographic adjustment factor for the fee schedule area, and the conversion factor. Those inputs are published by CMS, which means the expected amount for a given code and locality can be worked out before the remittance arrives.
| Item | What the rule says | Why it matters to a practice |
|---|---|---|
| Fee schedule amount (participating) | RVUs x geographic adjustment factor x conversion factor | This is the expected allowed amount to compare against remittances. |
| Nonparticipating supplier | 95 percent of the fee schedule amount | Participation status changes the base amount for the same service. |
| Limiting charge | 115 percent of the fee schedule amount for nonparticipating suppliers | Caps what a nonparticipating provider that does not accept assignment may charge. |
| Filing deadline | Claim filed within 1 calendar year after the date of service | A late claim can be denied no matter how well it was coded. |
Source: eCFR, 42 CFR 414.20, 414.48 and 424.44 (current text, accessed October 2026).
Read the table as a map of what is fixed and what is not. The conversion factor, the RVUs and the limiting charge are set outside the practice. Coding accuracy, documentation, timely filing, payer enrollment status and follow-up on short payments are set inside it.
“A fee schedule rate is a ceiling the practice cannot change. Getting paid correctly means every claim reaches that ceiling and stays there.”
What is happening to Medicare payment rates in 2026 and 2027?
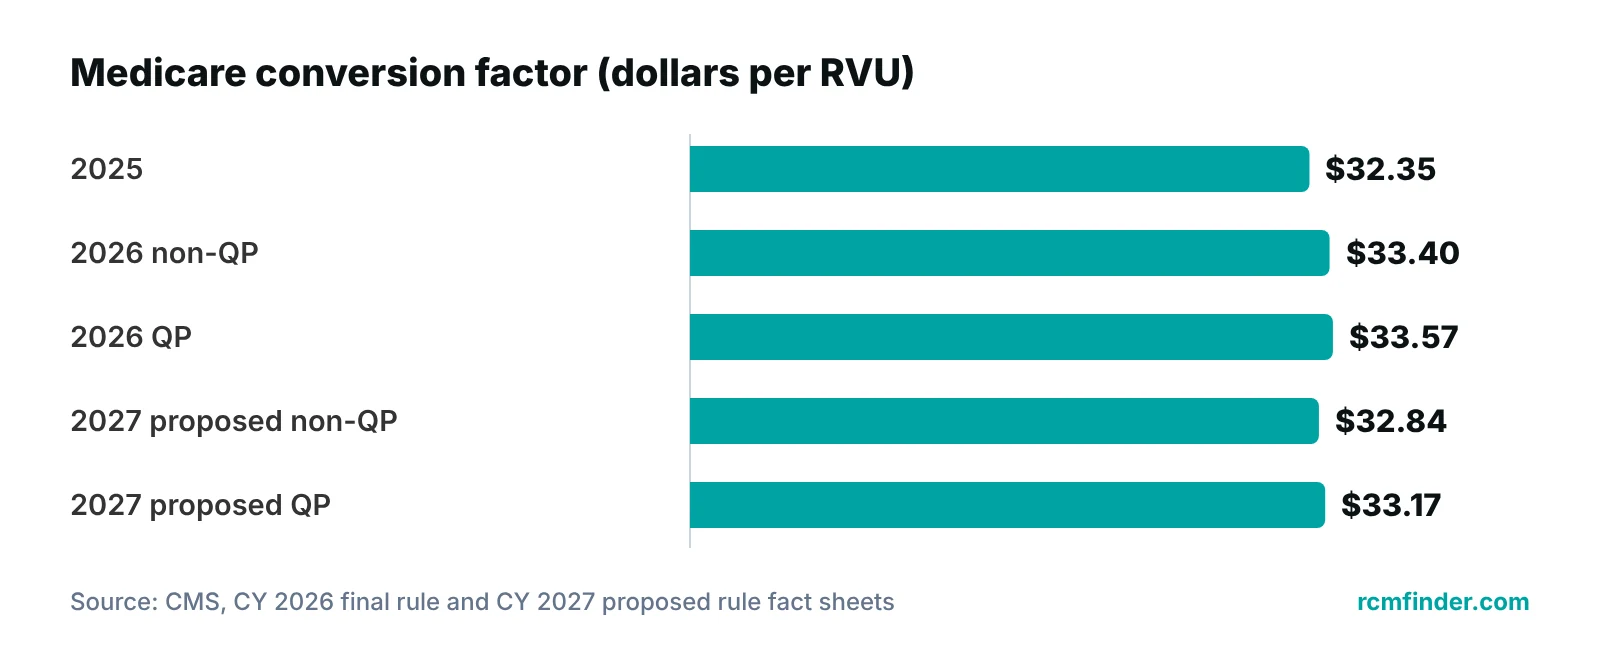
The conversion factor rose for 2026, but a proposed cut for 2027 would reverse much of that. For 2026, CMS finalized two conversion factors: $33.57 for clinicians in qualifying alternative payment models and $33.40 for everyone else, up from $32.35. CMS lists a one-year statutory increase of 2.50 percent as part of that change.
Two cautions apply. First, CMS also finalized a 2.5 percent efficiency adjustment for 2026 that applies to non-time-based services, and excludes office visits (E/M), care management, behavioral health, telehealth-list services and certain maternity codes. A practice’s net effect depends on its service mix, not on the headline number. Second, the CY 2027 proposed rule, released July 14, 2026, would set $33.17 for qualifying APM clinicians and $32.84 for others, and notes that the one-year 2.50 percent increase expires for 2027. The 2027 numbers are proposals until CMS publishes the final rule.
| Year | Qualifying APM | Non-qualifying APM | Status |
|---|---|---|---|
| 2025 baseline | $32.35 | $32.35 | Reference point in CMS’s 2026 fact sheet |
| 2026 | $33.57 (+3.77%) | $33.40 (+3.26%) | Final rule, October 31, 2025 |
| 2027 | $33.17 (-1.19%) | $32.84 (-1.68%) | Proposed rule, July 14, 2026 |
Source: CMS fact sheets for the CY 2026 final rule (CMS-1832-F) and the CY 2027 proposed rule.
For practices that want a longer view of how earlier cuts landed, see our post on the 2025 Medicare payment cuts. The practical use of these numbers is budgeting: if a practice’s Medicare mix is large, model 2027 at the proposed values and treat any final increase as upside.
What can a practice actually control?
A practice controls claim accuracy, not the rate. Five areas decide whether a Medicare claim pays at the full fee schedule amount: coding, documentation, timely filing, enrollment and participation status, and short-payment follow-up. Each has a different owner and a different failure pattern.
| Lever | What it controls | What it does not control |
|---|---|---|
| Coding to the documentation | Whether the billed code matches what the note supports | The RVUs or conversion factor |
| Documentation quality | Whether a claim survives review and appeal | Whether Medicare covers the service |
| Timely filing | Whether the claim is eligible for payment at all | Payer processing time |
| Participation and enrollment | Which base amount applies | Fee schedule values |
| Underpayment review | Catching payments below the expected amount | Policy changes by CMS |
| MIPS reporting | Exposure to a payment adjustment | Annual measure and weight changes |
This reframes the old advice to ‘maximize’ Medicare rates. The rate is fixed. The leakage is in the gap between what the formula allows and what lands in the bank.
Should a practice code to the highest level?
No. A practice should code to what the documentation supports, not to the highest level available. Billing a higher level than the note supports is upcoding and is a compliance risk; billing lower than the note supports gives up payment the practice earned. Both are errors, and an audit finds both.
The practical control is a coding review that compares the note, the diagnosis codes and the modifiers with the billed service. Our guides to upcoding and down-coding explain how each shows up in claims, and medical coding audits describes how to sample charts. Modifier errors are a frequent cause of short or denied payment; modifier 25 and modifier 59 are two common examples.
Services billed by clinicians in a team need the same discipline. Rules for billing under a supervising physician are specific, so check incident-to billing before assuming a visit is billable at the physician rate.
Documentation is the test
Medicare pays for what the record supports. A well-coded claim attached to a thin note can be reduced or recouped later, so train clinicians on the note as well as coders on the code.
How do clean claims and timely filing protect Medicare payment?
A clean claim reaches the right payer, on time, with complete data, so it is paid on the first pass. Under 42 CFR 424.44, a Medicare claim generally must be filed within one calendar year after the date of service. The regulation allows an extension in limited cases, for example when the delay was caused by an error or misrepresentation by a Medicare employee, contractor or agent. Do not plan around exceptions.
The simplest safeguard is a charge lag report: any visit without a submitted claim after a set number of days goes to an owner. Pair it with front-end checks and a scrubbing step before submission. Our clean claims guide lists the edits worth running, and denial management covers what to do once a claim comes back.
A claim-centred practice management system that tracks claims by stage can help here. It gives each claim an owner, checks data completeness before submission and flags payments that land below an expected amount. The tool matters less than the habit: every claim has an owner and a next date.
How does MIPS affect Medicare reimbursement?
MIPS can raise or lower Medicare Part B payments for eligible clinicians, so it is a reporting task to schedule, not a growth strategy to count on. The old claim that clinicians can earn bonuses of up to 9 percent is not a safe planning figure; the adjustment depends on the score and the rules for that year, and the downside is real.
According to HFMA’s summary of the CY 2027 proposed rule, the four MIPS categories are weighted 30 percent quality, 30 percent cost, 15 percent improvement activities and 25 percent promoting interoperability for the 2026 performance year, the performance threshold is 75 points, and adjustments can range from -9 percent to +9 percent. Weights, thresholds and measures change by year, so confirm them on the Quality Payment Program site before choosing measures.
Our MIPS categories and scoring guide walks through the categories in more detail. Assign one person to own MIPS reporting, set an internal deadline well before the submission window closes, and check eligibility early.
What does audit risk mean for Medicare payment?
Payment that is later recouped is not reimbursement. CMS’s fiscal year 2025 improper payment fact sheet put the Medicare fee-for-service estimated improper payment rate at 6.55 percent, or $28.83 billion. That figure covers payments that did not meet requirements, including payments where a reviewer could not tell whether the payment was proper. It is not a denial rate, and it is not a measure of any one practice.
The takeaway is documentation discipline. Older articles quote a figure that CMS denies 10 percent of claims for insufficient documentation; no primary source supports it, and it should not be repeated. For how recovery audits work, see our guide to RAC audits.
Should a practice handle Medicare billing in-house or outsource it?
Keep it in-house if the practice has trained staff, clear owners and the time to review remittances weekly; consider help if claims age without an owner or if denials repeat. Outsourcing does not change the fee schedule, and no vendor can promise a percentage lift in revenue. What it can change is who watches each claim and how quickly problems are found.
Before choosing, ask any billing company how it reports on Medicare claims by stage, how it flags payments below the expected amount, what its coding review process is, how it handles a recoupment request, and whether it will sign a Business Associate Agreement before accessing patient data. Ask for the same reports you would want from an in-house team.
A useful first step is an audit of the current process: sample paid and denied Medicare claims, compare each payment to the expected amount, and sort the gaps by cause. Specialty matters, since coding patterns and documentation expectations differ; our specialty billing pages cover the specialties RCM Finder supports.
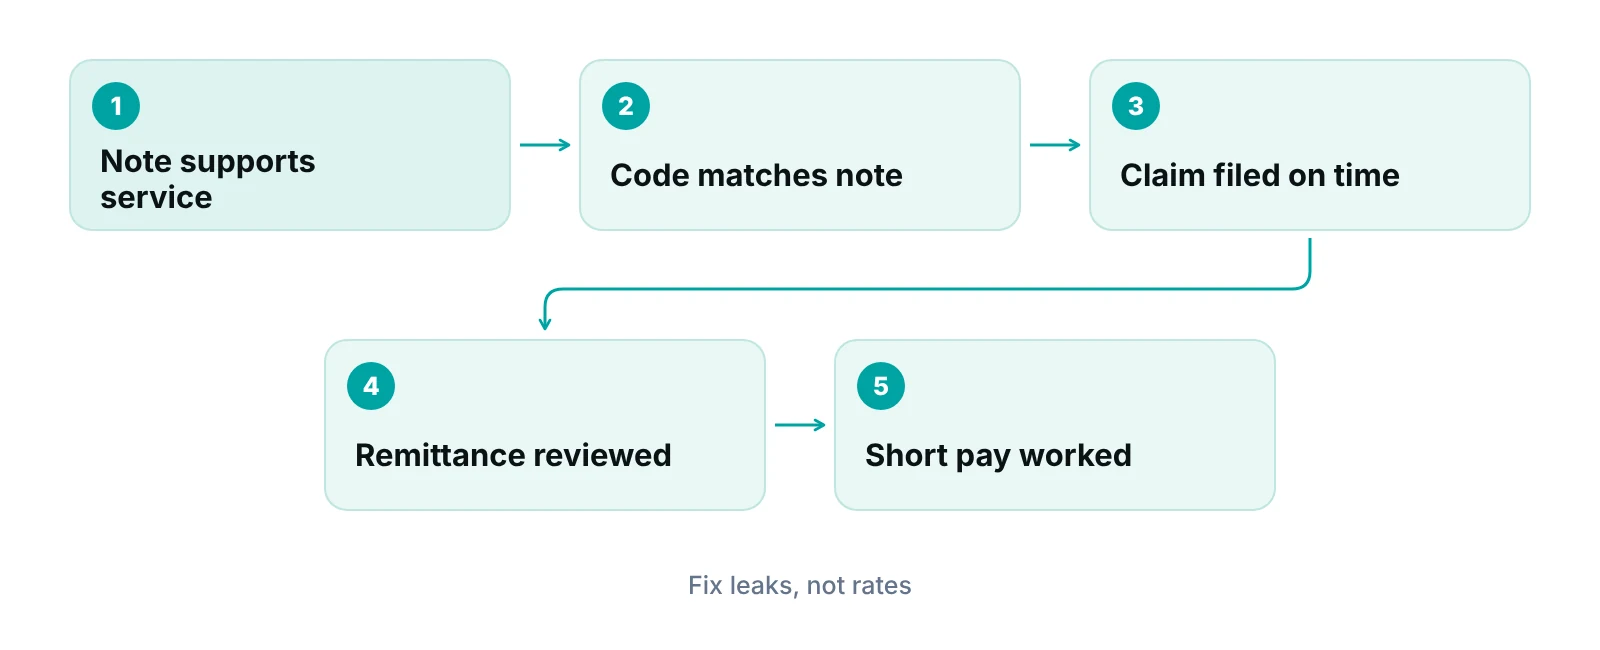
Where are your Medicare claims leaking?
A free practice audit looks at how your claims move from visit to payment and where short payments, denials and filing delays start. Pricing, if you decide to go further, is quoted after the audit.
Our recommendations
- Build a Medicare expected-payment check. We recommend comparing each Medicare remittance with the expected fee schedule amount for the code and locality, and sending any shortfall to a named owner.
- Code to the note, in both directions. We recommend a monthly sample of paid claims reviewed for upcoding and down-coding, with findings fed back to clinicians as well as coders.
- Set a charge lag alert well inside the filing limit. We recommend a weekly list of visits with no submitted claim, escalated long before the one-calendar-year limit in 42 CFR 424.44.
- Budget 2027 at the proposed rates. We recommend modelling Medicare revenue at the proposed 2027 conversion factors until the final rule is published, and updating the plan when it arrives.
- Give MIPS one owner. We recommend one named person for MIPS reporting, with the performance year’s measures and weights checked on the Quality Payment Program site at the start of each year.
- Audit the process before changing vendors. We recommend measuring where Medicare claims leak before deciding to hire, outsource or buy software, so the fix matches the cause.
A claim-centred practice management system gives every Medicare claim a stage and an owner.
It checks data completeness before submission and flags payments that arrive below an expected amount, so short payments are worked rather than written off.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Medicare reimbursement is fixed by formula, so the gains are in accuracy: code to the note, file on time, compare each payment with the expected amount and work the shortfalls. If claims are leaking and nobody owns the follow-up, medical billing services can take over that work, or you can request a free practice audit to see where the gaps are first.
Frequently asked questions
Can a practice negotiate Medicare reimbursement rates?
No. Under the Medicare Physician Fee Schedule, the payment for a service is calculated from relative value units, a geographic adjustment factor and the conversion factor. A practice cannot negotiate those inputs. What it can improve is coding accuracy, documentation, timely filing and follow-up on payments that come in below the expected amount.
What is the Medicare conversion factor for 2026?
For 2026, CMS finalized $33.57 for clinicians in qualifying alternative payment models and $33.40 for others, up from $32.35. The change includes a one-year 2.50 percent statutory increase. For 2027, CMS has proposed $33.17 and $32.84, which are not final until the final rule is published.
Is it a good idea to code to the highest level?
No. Code to what the documentation supports. Billing above the note is upcoding and creates compliance risk. Billing below it loses payment the practice earned. A regular coding review that checks both directions is the safer approach, and it protects the practice in an audit.
How long does a practice have to file a Medicare claim?
Under 42 CFR 424.44, a claim generally must be filed no later than one calendar year after the date of service. Limited extensions exist, such as an error by a Medicare contractor. Most practices set an internal alert far earlier so claims never get close to the limit.
Do MIPS bonuses make up for lower fee schedule rates?
Do not count on it. MIPS adjustments can be positive or negative, depend on scores and annual rules, and the rules change annually. Treat MIPS as a reporting requirement to manage, and check current parameters on the Quality Payment Program site.
Will outsourcing billing raise Medicare payment?
It cannot change the fee schedule, and no vendor can honestly promise a percentage increase. A billing partner can improve who tracks each claim and how fast short payments and denials are found. Compare vendors on reporting, coding review and willingness to sign a Business Associate Agreement.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- CY 2026 Medicare Physician Fee Schedule Final Rule (CMS-1832-F) fact sheet — CMS (2025)
- CY 2027 Medicare Physician Fee Schedule Proposed Rule fact sheet — CMS (2026)
- 42 CFR Part 414, Payment for Part B Medical and Other Health Services — eCFR (2026)
- 42 CFR 424.44, Time limits for filing claims — eCFR (2026)
- Fiscal Year 2025 Improper Payments Fact Sheet — CMS (2026)
- CY 2027 Physician Fee Schedule Proposed Rule Summary, Part III: Quality Payment Program — HFMA (2026)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. CPT codes are owned by the AMA, and payment rates, MIPS parameters and payer rules change and vary by contractor and locality. Verify current requirements with CMS, your Medicare Administrative Contractor and your counsel before you act.
