
Medicare physician fee schedule changes for 2027 are proposed, not final. CMS proposed in July 2026 to lower the conversion factor from $33.40 to $32.84 (-1.68%) for most clinicians, mainly because the one-year 2.5% increase Congress gave for 2026 expires.
This post replaces an earlier article written when a 2025 cut was only proposed. That cut was finalized, 2026 brought a temporary increase, and CMS has now proposed a lower rate for 2027. The figures below come from CMS fact sheets, and the 2027 numbers can still change in the final rule.
Key takeaways
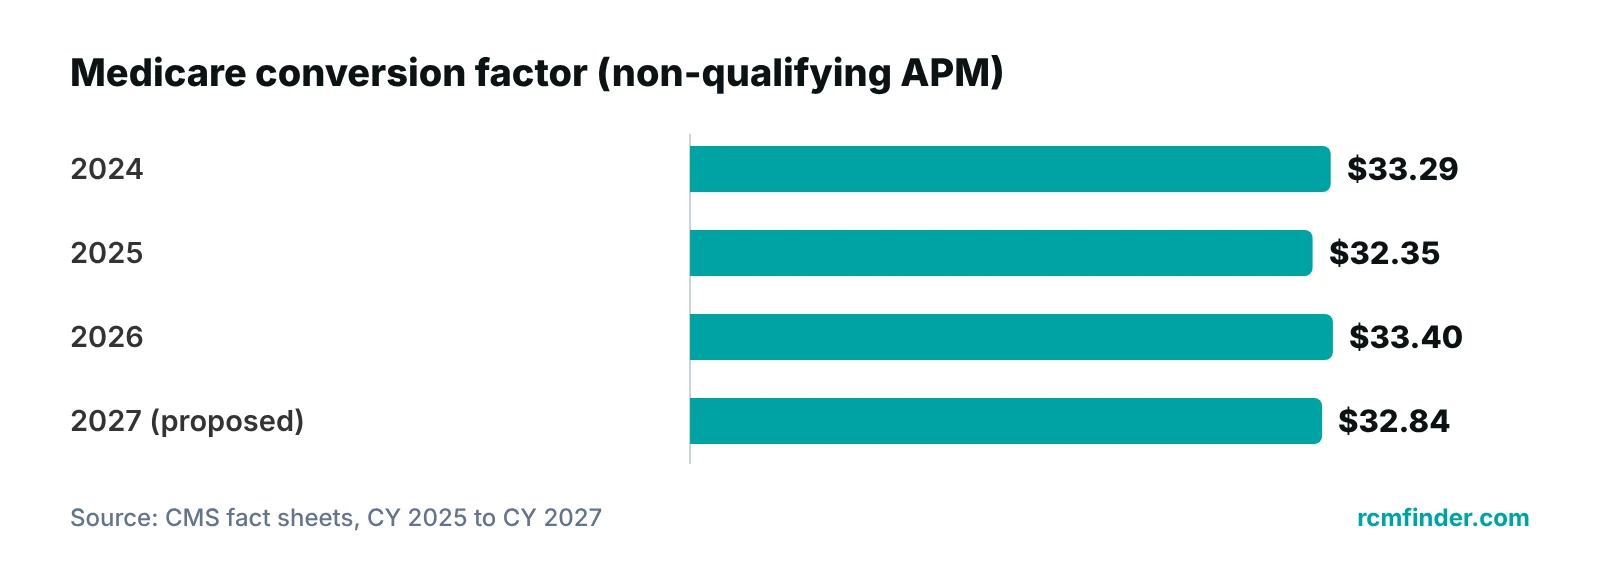
- The CY 2025 conversion factor fell about 2.83%, from $33.29 to $32.35.
- For CY 2026 it rose to $33.40 (non-qualifying APM) or $33.57 (qualifying APM), helped by a one-year 2.50% statutory increase.
- For CY 2027 CMS proposes $32.84 or $33.17, down 1.68% or 1.19%, because that 2.50% increase does not carry over.
- The conversion factor is one input; a code’s payment also depends on its RVUs and your locality.
- Run the numbers on your own top codes and payers before the final rule, not after.
What has changed, and what is only proposed?
Two years of rates are final and one is proposed. The 2025 conversion factor was finalized at about $32.35, down 2.83% from $33.29 in 2024. The 2026 factor is $33.40 for clinicians outside a qualifying advanced alternative payment model (APM) and $33.57 for those in one. The 2027 figures are a proposal published on July 14, 2026.
The conversion factor is the dollar value CMS attaches to each relative value unit (RVU). Medicare publishes a different payment amount for every service, and the factor is the multiplier that turns RVUs into dollars. A small percentage change in it touches every fee-schedule line you bill.
| Year | Status | Conversion factor | Change |
|---|---|---|---|
| 2024 | Final | $33.29 | Starting point |
| 2025 | Final (November 1, 2024) | $32.35 | -2.83% (-$0.94) |
| 2026 | Final (October 31, 2025) | $33.57 qualifying APM / $33.40 non-qualifying | +3.77% / +3.26% vs 2025 |
| 2027 | Proposed (July 14, 2026) | $33.17 qualifying APM / $32.84 non-qualifying | -1.19% / -1.68% vs 2026 |
Source: CMS fact sheets for the CY 2025 final rule, CY 2026 final rule (CMS-1832-F) and CY 2027 proposed rule. The 2027 figures are proposed and may change.
The old 2025 numbers are out of date
The earlier version of this post treated $32.36 as a proposed 2025 rate. CMS finalized the 2025 factor at about $32.35. Any plan built on that proposal, or on a five-year decline, should be rebuilt from the table above.
Why is CMS proposing a lower rate for 2027?
The main driver is a one-year increase that ends. CMS states that a statute gave a 2.50% increase to the conversion factor for 2026 only, and that current law therefore requires a 2.50% reduction in 2027 compared with 2026. Statutory updates of +0.75% (qualifying APM) and +0.25% (non-qualifying) and an estimated +0.53% adjustment for work RVU changes offset part of that, which leaves the net proposed cuts of 1.19% and 1.68%.
Two other changes sit underneath the headline number. They move relative payment between services, so they can matter more to your practice than the conversion factor does.
| Change | Stage | What CMS says |
|---|---|---|
| One-year 2.50% increase | Final for 2026; not in 2027 | Stipulated by statute for 2026 only; current law requires -2.50% against 2026 for 2027. |
| Efficiency adjustment of -2.5% | Final for 2026 | Applied to work RVUs and intraservice time for non-time-based services. Time-based codes such as E/M, care management, behavioral health and telehealth-list services are excluded. |
| Greater indirect cost recognition for office settings | Final for 2026 | Office-based settings get more recognition of indirect practice costs than facility settings. |
| Practice expense stabilizer | Proposed for 2027 | Phases out part of the older specialty-level practice expense data method and replaces it with a stabilizer over several years. |
| Facility vs non-facility payment gap | Proposed for 2027: request for comment only | CMS asks whether the site-of-service payment differential is still appropriate. No rate change is proposed on that point. |
Source: CMS fact sheets for the CY 2026 final rule (CMS-1832-F) and CY 2027 proposed rule.
The practical reading is that two practices with the same conversion factor can see different results. A practice that bills mostly time-based visit codes sits outside the 2026 efficiency adjustment. A practice that bills procedures and diagnostics is more exposed to it. Look at your own code mix, as covered under billing by specialty.
How does a fee-schedule payment get calculated?
A Medicare fee-schedule amount is the sum of three RVU components, each adjusted for locality, multiplied by the conversion factor. CMS publishes the formula for the non-facility amount as: (work RVU x work GPCI) + (non-facility practice expense RVU x PE GPCI) + (malpractice RVU x MP GPCI), all multiplied by the conversion factor. The facility amount uses the facility practice expense RVU instead.
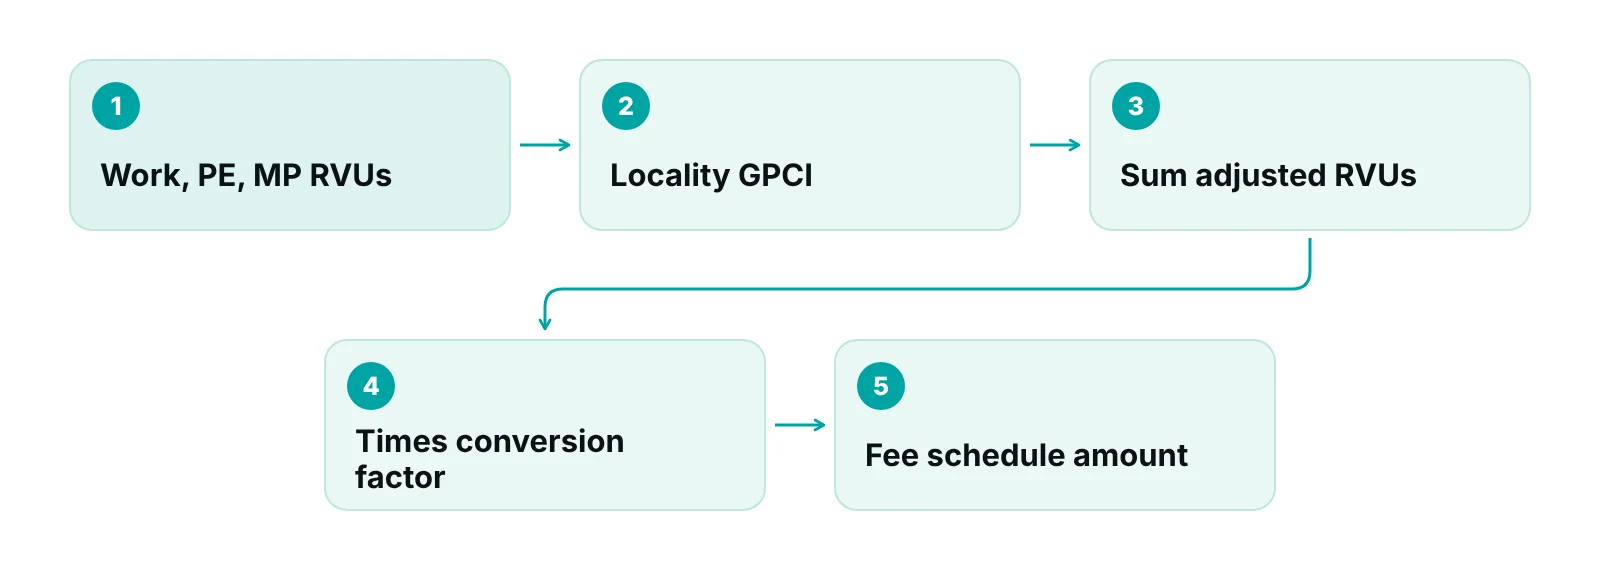
Here is the arithmetic, using a made-up service with 2.00 total locality-adjusted RVUs. At the 2026 non-qualifying factor of $33.40 it pays $66.80. At the proposed 2027 factor of $32.84 it pays $65.68, a difference of $1.12 or 1.68%. This is an illustration of the mechanics, not a real code. Actual payment also depends on RVU changes for that code, the efficiency adjustment, the site of service and any adjustments applied at the claim level.
CMS publishes the facility and non-facility amounts for paid services in its fee schedule files, so you can compare current and proposed amounts for the codes you bill instead of relying on a headline percentage. The rule-based billing mechanics are explained in our guide to billing and coding of Medicare fee-for-service claims.
“A headline percentage is only a starting point. The number that matters is the change on the codes and payers a practice actually bills.”
What does this mean for practice revenue?
The effect depends on your Medicare share and your code mix, and there is no single national answer. A practice with a small Medicare share and mostly time-based visit codes will see a different change from a procedure-heavy practice with a large Medicare population. The way to size it is to apply the proposed rates to last year’s paid Medicare claims.
Fee-for-service Medicare rates also feed other payers. Some commercial contracts and Medicare Advantage agreements are written as a percentage of the Medicare fee schedule, so a change in Medicare rates can flow into them when those contracts reprice. Check the wording of each contract. Whether a payer reprices automatically, on renewal, or not at all is a contract term, and we cannot tell you how any particular one reads.
Keep the scale in view. A 1.68% change on a Medicare line is real money, but it is not the largest leak in most billing operations. Denials, late filing, missed charges and unworked balances often cost more than a one-year rate change. For that reason, we recommend pairing any rate analysis with a look at denial management and the revenue cycle KPIs that show where cash is being lost.
What should a practice do before the final rule?
Start with data you already hold, and do it before the final rule so the result informs budgets rather than explaining a surprise. CMS issued the CY 2025 final rule on November 1, 2024 and the CY 2026 final rule on October 31, 2025, so a CY 2027 final rule around the start of November is a reasonable expectation, but CMS sets its own timing. Public comment on the proposal has closed.
| Step | What to pull | Why it matters |
|---|---|---|
| 1. Rank codes by Medicare revenue | Last 12 months of paid Medicare claims by CPT/HCPCS code | A few codes usually carry most Medicare revenue; those are the ones to model. |
| 2. Apply current and proposed rates | Fee schedule files for your locality, non-facility and facility | Shows the dollar change per code instead of one blended percentage. |
| 3. Flag non-time-based services | Procedures, imaging and diagnostics in the top codes | These sit inside the efficiency adjustment; time-based visit codes do not. |
| 4. Check contract language | Commercial and Medicare Advantage agreements tied to a Medicare percentage | Tells you which payers may reprice, and when. |
| 5. Confirm payment posting | Underpayments against expected allowed amounts | A new rate year is when a wrong fee schedule loaded at a payer or in your own system goes unnoticed. |
Want a second pair of eyes on your Medicare exposure?
Our free practice audit reviews your top codes, payer mix and denial patterns, so you know where Medicare rates sit among the things that move your revenue. Pricing for any service is quoted after the audit.
Which billing steps protect revenue when rates tighten?
Rate pressure makes accuracy more valuable, because the same work has to produce a correct, complete claim. The basics do not change: capture every billable service, code to the note, submit clean claims, work denials and follow up on unpaid balances. The earlier version of this post listed these too, but without telling you how to know they are working.
- Charge capture: compare services documented against services billed, by provider, each month.
- Coding review: check codes and modifiers against the documentation and Medicare policy, including rules such as Medicare incident-to billing where they apply.
- Clean claims: catch missing or mismatched data before submission rather than after a rejection.
- Denials and appeals: track denial reasons by payer and code, and fix the cause upstream.
- Underpayment checks: compare each Medicare payment with the expected allowed amount for that code and locality.
Outsourcing is one option for covering this work, alongside training in-house staff. If you are weighing it, our medical billing services cover claims, charge entry and coding support. It helps to have the claim picture in one place, whichever route you take, such as a practice management system that tracks claims by stage with an owner on each claim.
Do not cut what protects revenue
When margins tighten, front-desk checks and billing follow-up are tempting cuts. They are also where most avoidable revenue loss starts. Cut after you have measured, not before.
Can Congress or CMS still change the 2027 rate?
Yes. The 2027 numbers are proposed, and CMS can change them in the final rule. Congress set the 2026 increase by statute, which shows the rate can also be altered by law. CMS’s own fact sheet says current law requires the 2.50% reduction, so a different outcome would need either CMS to change the policy it has proposed or Congress to act.
Practices can follow these developments through the Federal Register, CMS fact sheets and their specialty society or state medical association. We recommend budgeting on the proposed numbers and holding any upside back until a rule or law makes it final. For wider tactics on payer contracts and coding, see these strategies to maximize Medicare reimbursement and our Medicare billing guide for providers.
Our recommendations
- Budget on the proposed 2027 rate. Use $32.84 for clinicians outside a qualifying APM and $33.17 for those in one, and revisit when the final rule is published.
- Model by code, not by percentage. Apply current and proposed fee schedule amounts to your top Medicare codes for your locality. A blended percentage hides which services move most.
- Separate time-based and non-time-based services. The 2026 efficiency adjustment excludes time-based codes such as E/M and behavioral health. Know how much of your Medicare revenue falls on each side.
- Read your payer contracts. Note which agreements reference a Medicare percentage and when they reprice, so a Medicare change does not reach your cash flow by surprise.
- Verify payments against expected amounts. Check that new-year rates are loaded correctly in your billing system and that payments match the expected allowed amount.
- Measure the leaks first. Review denial rate, days in A/R and unbilled charges. Those are usually larger and more fixable than a one-year rate change.
A practice management system built around claims, not charts.
RCM Finder's portal tracks every claim by stage with an owner and flags underpayments against expected amounts, which helps a practice check payments after a rate change. It is a claims system, not an EHR.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Medicare physician fee schedule changes are a yearly event: a 2.83% cut for 2025, a temporary lift for 2026, and a proposed 1.68% cut for most clinicians in 2027. Model the effect on your own codes, plan on the proposed rate, and keep billing accuracy tight. If you want help with that, see our revenue cycle management services or run your numbers through the revenue calculator.
Frequently asked questions
What is the Medicare conversion factor for 2026?
CMS finalized $33.57 for clinicians in a qualifying advanced APM and $33.40 for everyone else. Compared with 2025’s $32.35, that is an increase of about 3.77% and 3.26%. The rise includes a one-year 2.50% increase set by statute, which does not continue into 2027.
What is the proposed Medicare conversion factor for 2027?
CMS proposed $33.17 for qualifying APM participants and $32.84 for others in its July 14, 2026 proposed rule. Those are decreases of 1.19% and 1.68% from 2026. The numbers are not final until CMS publishes the CY 2027 final rule.
Why are Medicare physician payments proposed to fall in 2027?
CMS says Congress gave a 2.50% conversion factor increase for 2026 only, and current law requires a 2.50% reduction against 2026 for 2027. Small statutory updates and an estimated work RVU adjustment offset part of it, leaving the proposed net cuts.
Does the conversion factor change what I am paid for every code?
It changes the multiplier for every fee-schedule service, but your payment per code also depends on that code’s RVUs, your locality and site of service. The 2026 efficiency adjustment also lowered work RVUs for non-time-based services, so results differ by code.
When will the 2027 final rule come out?
CMS has not announced it in the sources used here. The CY 2025 final rule came out on November 1, 2024 and the CY 2026 final rule on October 31, 2025, so early November is plausible. Watch the CMS newsroom and the Federal Register.
Do Medicare fee schedule cuts affect commercial payers?
Only where a contract ties rates to Medicare. Many commercial and Medicare Advantage agreements reference a percentage of the Medicare fee schedule, but the wording differs. Read each contract for how and when it reprices, and ask the payer if it is unclear.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Calendar Year (CY) 2027 Medicare Physician Fee Schedule Proposed Rule — CMS (2026)
- Calendar Year (CY) 2026 Medicare Physician Fee Schedule Final Rule (CMS-1832-F) — CMS (2025)
- Calendar Year (CY) 2025 Medicare Physician Fee Schedule Final Rule — CMS (2024)
- Physician Fee Schedule Search: Documentation and Files — CMS (2026)
Disclaimer: This article is educational and is not legal, coding, financial or compliance advice. Medicare rules and rates change, proposed rules may be revised before they are final, and payer contracts vary. Confirm current figures with CMS and your Medicare Administrative Contractor before making decisions.
