
What is MIPS in healthcare? It is Medicare's Merit-based Incentive Payment System. Eligible clinicians receive a 0 to 100 final score across four categories, and that score decides whether their Medicare Part B payments rise or fall, with the adjustment capped at 9 percent.
MIPS confuses many practice managers because the rules change every year and older articles blur the performance year with the payment year. This guide explains the categories, the scoring and the payment effect using the federal regulations themselves. It replaces an earlier version of this post that carried a 2024 label and some incorrect score tiers.
Key takeaways
- MIPS has four categories: Quality 30%, Cost 30%, Improvement Activities 15%, Promoting Interoperability 25%.
- The final score is a weighted result from 0 to 100, not a plain sum.
- The performance threshold is 75 points for payment years 2024 through 2030.
- The adjustment limit is 9 percent and lands two years after the performance year.
- Several changes are only proposed; check the final rule before planning.
What is MIPS and who has to take part?
MIPS is the Medicare program that scores eligible clinicians on quality, cost, improvement activities and use of electronic health records, then adjusts their Medicare Part B payments based on the score. It sits inside CMS’s Quality Payment Program, and the rules are written into 42 CFR Part 414, Subpart O.
The idea is simple. Medicare pays a base fee for each covered service. MIPS then moves that payment up or down depending on how a clinician or group scored compared with a performance threshold. Eligibility, not preference, decides whether the adjustment applies to you.
Who counts as a MIPS eligible clinician
For 2024 and later payment years, the eCFR lists physicians, physician assistants, nurse practitioners, clinical nurse specialists, certified registered nurse anesthetists, physical and occupational therapists, speech-language pathologists, audiologists, clinical psychologists, registered dietitians, clinical social workers and certified nurse midwives, plus groups that include them (eCFR). That is far wider than the physician-only group many managers picture.
Who is excluded
- Qualifying APM Participants, and partial QPs who do not elect to take part in MIPS.
- Clinicians below the low-volume threshold. For 2023 and later payment years that means $90,000 or less in allowed charges, 200 or fewer Part B patients, or 200 or fewer covered professional services. Meeting any one of the three puts you below it.
- Clinicians newly enrolled in Medicare during the performance period who have not billed Medicare before.
Small practices (15 or fewer eligible clinicians under one tax ID) are still in MIPS, but the rules treat them as a defined group. Check your own status each year, because eligibility is decided from your Medicare claims, not from your preference.
What are the four MIPS performance categories and their weights?
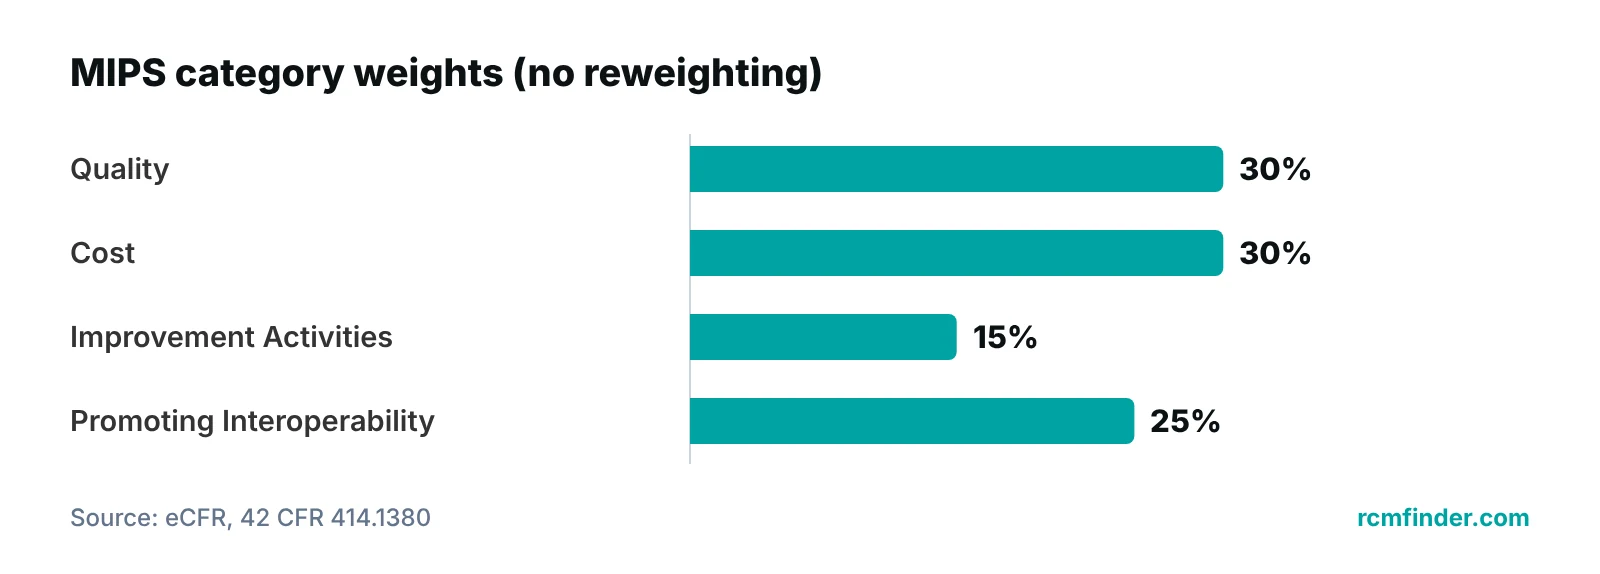
MIPS has four performance categories: Quality 30 percent, Cost 30 percent, Improvement Activities 15 percent and Promoting Interoperability 25 percent. Those weights have applied since the 2024 MIPS payment year and add up to 100.
| Category | Weight | What it measures | What your practice does |
|---|---|---|---|
| Quality | 30% | Clinical quality of care, using measures from the quality measure set | Report the measures CMS requires for your chosen reporting option |
| Cost | 30% | Cost of care, using cost measures CMS selects | CMS scores it; you manage care patterns and referrals |
| Improvement Activities | 15% | Activities from CMS’s improvement activities inventory | Choose and document activities that fit your practice |
| Promoting Interoperability | 25% | Meaningful use of certified EHR technology (CEHRT) | Use CEHRT, attest to required items and report required measures |
Source: eCFR, 42 CFR 414.1380 (weights from the 2024 MIPS payment year onward); 42 CFR 414.1375 (Promoting Interoperability); 42 CFR 414.1367 (improvement activities inventory).
Quality and cost: the two big categories
Together Quality and Cost carry 60 percent of the score. Quality is the category you control most directly, because you choose how to report. Cost is different. CMS selects the cost measures and updates its list over time, so the best lever is care coordination, not paperwork.
Improvement Activities
This category is scored from activities in CMS’s final inventory. The number of activities and their wording change by year, so the old claim of “over 100 activities” is not a safe number to plan around. Look up the current inventory in the QPP Explore Measures tool.
Promoting Interoperability and your EHR
You must use certified EHR technology for the performance period. From the 2021 payment year onward you also attest that you completed a Security Risk Analysis during the performance year. For 2026 onward the SAFER Guides self-assessment needs an affirmative attestation, and you attest that you did not knowingly and willfully limit or restrict how your CEHRT works with other systems (eCFR). Our guide to EHR functions and their effect on the revenue cycle explains why the same EHR set-up affects billing too. The security risk analysis ties into the broader HIPAA Security Rule changes for revenue cycle teams.
How is the MIPS final score calculated?
Each clinician or group gets a final score from 0 to 100. It is a weighted blend of the category scores, not a plain sum, and CMS can shift weight between categories when one does not apply.
The eCFR formula multiplies each category score by its weight, multiplies the result by 100, adds a complex patient bonus, and caps the total at 100. The complex patient bonus cannot exceed 10 points or fall below zero (eCFR).
Worked example (illustrative numbers only)
Say a group earns category scores of 0.80 for Quality, 0.60 for Cost, 1.00 for Improvement Activities and 0.90 for Promoting Interoperability. Weighted, that is 0.24 + 0.18 + 0.15 + 0.225 = 0.795. Multiply by 100 for a final score of 79.5 before any complex patient bonus. These inputs are made up to show the arithmetic, not a benchmark.
Reweighting
If a category does not apply to you, CMS can reassign its weight to the others. The eCFR gives the example of a clinician with no quality measure that is applicable and available. A clinician scored on fewer than two categories receives a final score equal to the performance threshold. Because reweighting changes how much each remaining category counts, never assume the 30/30/15/25 split applies to your group until you see your own scoring.
This also corrects a common shortcut. The final score is not Quality + Cost + Improvement Activities + Promoting Interoperability added together. It is a weighted result.
How do MIPS payment adjustments work?
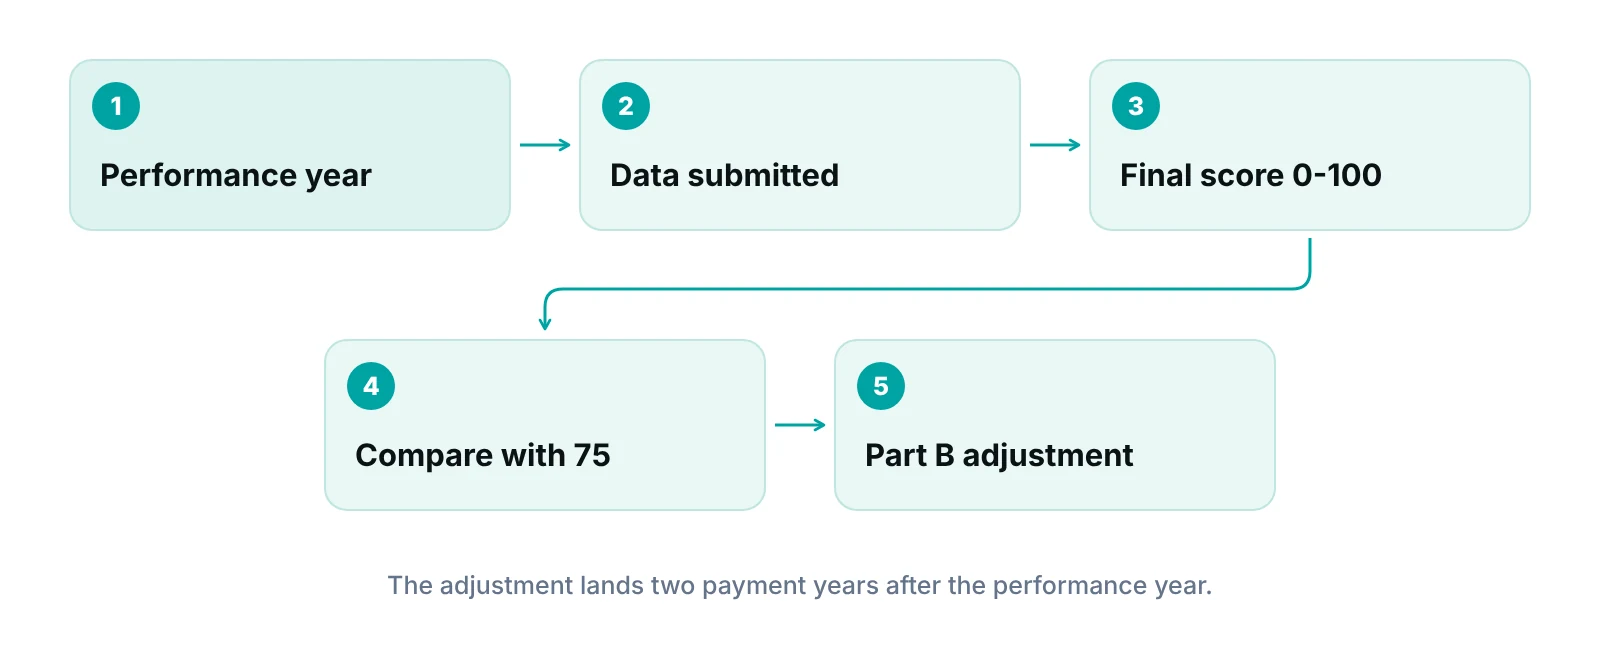
Your final score is compared with the performance threshold, which is 75 points for payment years 2024 through 2030. The payment adjustment limit is 9 percent, and the adjustment applies to your Medicare Part B payments for covered professional services two years after the performance year.
| Performance year | Payment year | Performance threshold | Adjustment limit |
|---|---|---|---|
| 2022 | 2024 | 75 points | 9 percent (plus an extra exceptional-performance adjustment, threshold 89) |
| 2023 | 2025 | 75 points | 9 percent |
| 2024 | 2026 | 75 points | 9 percent |
| 2025 | 2027 | 75 points | 9 percent |
| 2026 | 2028 | 75 points | 9 percent |
Source: eCFR, 42 CFR 414.1405 (thresholds, 9 percent limit, exceptional performance for payment years 2019 through 2024); 42 CFR 414.1380 (performance-period and payment-year pairing); CMS CY 2026 final rule, 90 FR 49266 (2026 performance period/2028 payment year).
What the "2024" in older articles really meant
The year in a MIPS article is easy to misread. Performance year 2024 is the year you deliver and report care. The payment adjustment for that year hits claims in 2026. Many older pages, including our earlier version of this post, blurred the two.
Why the adjustment is not a fixed bonus
Positive adjustments are budget-neutral. The rule lets CMS apply a scaling factor of up to 3.0 to positive adjustments so that the estimated increase in aggregate allowed charges equals the estimated decrease from negative adjustments. So the actual bonus depends on how everyone scores, and the 9 percent figure is a cap on the adjustment, not a promise.
The adjustment is applied by multiplying the Part B amount by 1 plus the adjustment factor divided by 100. A negative 9 percent adjustment turns a $100.00 Part B amount into $91.00 (1 + (-9/100) = 0.91).
Old tiers are not real
Some older guides, including a previous version of this post, showed neat score tiers such as 90 and above, 75 to 89 and 60 to 74 with fixed percentages. The eCFR sets no such tiers. An extra exceptional-performance adjustment existed only for payment years 2019 through 2024.
Which MIPS reporting option fits: Traditional MIPS, an MVP or the APP?
There are three ways to be scored: Traditional MIPS, MIPS Value Pathways (MVPs) and the APM Performance Pathway (APP). Traditional MIPS uses the standard four-category weights. The APP is for clinicians in a MIPS APM, and it weighs the categories differently.
| Option | Who it suits | How the categories are weighted | Cost category |
|---|---|---|---|
| Traditional MIPS | Most clinicians and groups reporting on their own | Quality 30, Cost 30, Improvement Activities 15, Promoting Interoperability 25 | Scored (30 percent) |
| MIPS Value Pathways (MVPs) | Clinicians who want a smaller set of measures and activities tied to a specialty or condition | Defined through rulemaking for each pathway; check the QPP page for yours | Check the pathway |
| APM Performance Pathway (APP) | Clinicians on the Participation List or Affiliated Practitioner List of an APM Entity in a MIPS APM | Quality 50, Cost 0, Improvement Activities 20, Promoting Interoperability 30 | Weighted at zero |
Source: eCFR, 42 CFR 414.1367 (APP weights and eligibility) and 42 CFR 414.1305 (MVP definition: a subset of measures and activities established through rulemaking).
One correction to older guides: the APP is not limited to quality and cost. Under the eCFR it scores Quality, Improvement Activities and Promoting Interoperability, and the cost category weight is zero. Specialty can matter here, since MVPs are built around specialties and conditions. See our specialty billing pages for how coding and workflows differ by specialty.
What is changing in MIPS now?
The rules move every year, so treat any MIPS article, ours included, as a snapshot. Two federal documents matter most right now.
- CY 2026 final rule (published November 5, 2025, effective January 1, 2026): includes the MIPS payment adjustment section covering the performance threshold for the CY 2026 through CY 2028 performance periods (Federal Register). The eCFR lists the threshold at 75 points through payment year 2030.
- CY 2027 proposed rule (published July 16, 2026, comments closed September 14, 2026): proposals include designating MIPS Core Measures with an exemption for small practices, removing the Security Risk Analysis measure from Promoting Interoperability starting with the 2027 performance period, and making the electronic prior authorization measure optional (Federal Register).
Proposals are not rules. Until CMS publishes a final rule, plan around what is in effect today and recheck after the final rule appears.
What does MIPS mean for billing, cash flow and operations?
MIPS changes how much Medicare pays for the same service two years later, so it is a revenue topic as well as a quality topic. The people who own billing, the EHR and clinical reporting need to agree who owns MIPS.
- Cash-flow planning: a negative adjustment lowers every Part B payment for the year it applies. Model it as a percentage of your Medicare Part B volume. Our revenue calculator can help size the exposure.
- Claim integrity: clean claims and accurate coding come first, because MIPS adjusts payment on top of what you bill. See our guide to billing and coding Medicare fee-for-service claims.
- Risk coding: if you also hold value-based contracts, HCC coding runs alongside MIPS and uses different rules.
- Compliance record: keep evidence for the Security Risk Analysis and improvement activities. Our medical billing compliance guide covers documentation habits.
It also helps to see MIPS in context. It is one of the ways Medicare ties payment to results, covered in fee-for-service versus value-based care. And the KPIs that show claim problems early are in our revenue cycle KPI guide.
Where we help: our team works with the EHR you already use to keep Medicare claims accurate and follow up on underpayments, and a practice management system that tracks claims by stage shows you where each claim sits. It does not report MIPS measures or calculate your MIPS score. That stays with your EHR, registry or reporting vendor.
See where Medicare claims stall in your practice
A free practice audit looks at your claim flow, denials and Part B payments so MIPS planning starts from real numbers.
Our recommendations
- Confirm your eligibility status each year. We would start with the eCFR criteria above: clinician type, the low-volume threshold and any APM status. Do it before the performance year starts, not after.
- Name one owner for MIPS. Quality data lives in the EHR, billing lives in the revenue cycle, and attestations need a compliance signature. Split ownership is how deadlines get missed.
- Pick your reporting option on purpose. Compare Traditional MIPS, an MVP that fits your specialty and, if you qualify, the APP. Each weights the categories differently.
- Document the Security Risk Analysis and improvement activities as you go. Evidence gathered in the moment is easier than evidence rebuilt at year end.
- Model the downside in dollars. Take your Medicare Part B volume and apply the 9 percent cap as a worst case. Seeing the dollar figure usually settles how much effort MIPS deserves.
- Recheck the rules after every final rule. Weights, measures and thresholds are set through rulemaking. Calendar a review when CMS publishes the annual final rule.
See where every Medicare claim sits while your MIPS results settle.
Our portal tracks each claim by stage with an owner, flags underpayments against expected amounts and shows reporting dashboards. It does not report quality measures or calculate MIPS scores; those stay with your EHR, registry or reporting vendor.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
MIPS is a scoring system with a payment consequence, and the rules change every year. Know your eligibility, your reporting option and the 75-point threshold, then model the 9 percent cap against your own Medicare volume. If you want a second pair of eyes on how Medicare claims move through your practice, our end-to-end revenue cycle management team can start with a free audit.
Frequently asked questions
What is MIPS in healthcare in simple terms?
MIPS is Medicare’s pay-for-performance program for clinicians. You are scored from 0 to 100 on quality, cost, improvement activities and use of certified EHR technology. The score is compared with a performance threshold, and your Medicare Part B payments are adjusted up or down about two years later.
What are the four MIPS categories and their weights?
Quality is 30 percent, Cost is 30 percent, Improvement Activities is 15 percent and Promoting Interoperability is 25 percent, under the eCFR weights for the 2024 payment year onward. CMS can reweight categories that do not apply to a clinician, so your own weights can differ.
What is the MIPS performance threshold?
The eCFR sets the performance threshold at 75 points for payment years 2024 through 2030. The payment year is two years after the performance year, so the 2026 performance year is the 2028 payment year. Rules can change through annual rulemaking, so confirm the current figure on the QPP site.
How big can a MIPS payment adjustment be?
The adjustment limit is 9 percent for payment year 2022 and every later payment year. Positive adjustments can be scaled, up to a factor of 3.0, to keep the program budget-neutral. The extra exceptional-performance adjustment applied only to payment years 2019 through 2024.
Do small practices have to report to MIPS?
Not necessarily. Clinicians at or below the low-volume threshold are excluded: $90,000 or less in allowed charges, 200 or fewer Part B patients, or 200 or fewer covered professional services. Meeting any one of the three puts you below it. Check your status each year with CMS.
Is the MIPS score just the four category scores added up?
No. Each category score is multiplied by its weight, the total is multiplied by 100, a complex patient bonus of up to 10 points may be added, and the result is capped at 100. Reweighting can also change how much each category counts.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- 42 CFR 414.1380 Scoring — eCFR (2026)
- 42 CFR 414.1405 Payment — eCFR (2026)
- 42 CFR 414.1367 APM performance pathway — eCFR (2026)
- 42 CFR 414.1375 Promoting Interoperability — eCFR (2026)
- 42 CFR Part 414 Subpart O (MIPS and APM incentive) — eCFR (2026)
- CY 2026 Physician Fee Schedule final rule (CMS-1832-F), 90 FR 49266 — Federal Register (2025)
- CY 2027 Physician Fee Schedule proposed rule (CMS-1848-P), 91 FR 43842 — Federal Register (2026)
Disclaimer: This article is general education on MIPS, not billing, coding, legal or compliance advice. Medicare rules, thresholds and weights change through annual rulemaking and individual scoring can differ. Verify current requirements on the CMS Quality Payment Program site and the eCFR, and consult a qualified professional before deciding for your practice.
