

The best medical billing and coding tips are habits that stop errors early: verify coverage before the visit, code only from a signed note, use the current code set, scrub claims before submission, and audit a small sample each month. Follow-up habits then catch denials and underpayments.
Most practices do not lose revenue in one big failure. They lose it in small, repeatable gaps: a registration error, a vague note, an outdated code, a missed deadline. Each is easy to fix once you can see it.
This guide is for owners and managers. It covers ten habits, the sources behind the rules, and the order we would fix them in.
Key takeaways
- Fix the front of the claim path first; registration and coverage errors travel with the claim.
- Code from a signed note, and query the provider instead of guessing.
- ICD-10-CM updates by fiscal year (FY 2027 set effective October 1, 2026); CPT is updated yearly and NCCI edit files quarterly.
- Medicare claims must be filed within 1 calendar year after the date of service, with limited exceptions.
- Audit a small sample monthly and log the cause of each mismatch.
Which medical billing and coding tips matter most?
The tips that matter most are the ones that stop a claim from going wrong before it reaches the payer: correct registration, a note that supports the code, a current code set, and a check before you submit. Follow-up habits then catch what slips through. Tools help, but the habits come first.
We group the ten habits below by where they sit on the claim path. That makes it easier to see who owns each one and where your own process leaks. If a habit is already in place, move on to the next.
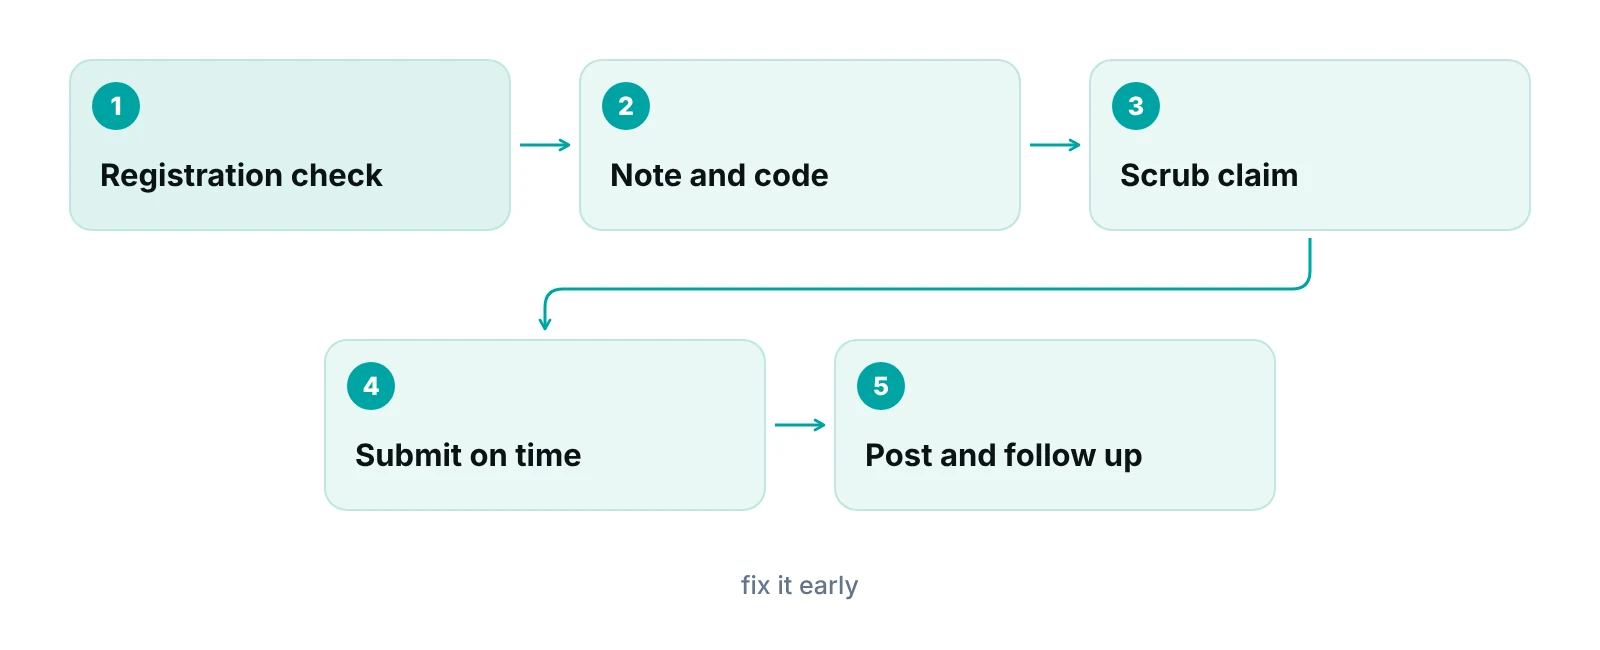
This post covers habits, not benchmarks. For targets such as denial rate and days in A/R, see our guide to revenue cycle KPIs and our essential accounts receivable metrics guide, so you get one set of definitions. Where a number or rule appears below, it comes from a primary source we link.
Which habits come before the visit and the note?
Registration and coverage checks come first, because errors made here travel with the claim. A wrong subscriber ID or a name that does not match the insurance card can be rejected before anyone looks at the codes.
1. Verify coverage and registration before the patient arrives
- Confirm that coverage is active for the date of service, who the subscriber is, and whether there is a secondary plan.
- Match the name, date of birth and member ID to the card, and scan both sides of the card each visit.
- Check whether the service needs prior authorization or a referral under that plan.
- Write down the date and the method of each check, so a denial can be traced to a record.
Our patient insurance verification guide walks through the checks in more detail.
2. Document first, then code from the note
A code should describe what the medical record says, not what the practice hopes to bill. The HHS Office of Inspector General (OIG) lists claims that are upcoded, or not supported by the patient’s medical record, as examples of potentially false claims in its General Compliance Program Guidance (2023). The safest routine is simple: the provider completes the note, the coder reads it, and any gap goes back to the provider as a question.
Give coders a quick, written way to query the provider, and keep the answer with the note.
A coding query is not a leading question
Ask what the provider meant, such as which side, which stage or how long. Do not suggest the answer that pays better. Queries should be neutral, because the note must stand on its own if a payer reviews it.
Which coding habits protect the claim?
Code from a current code set, choose the most specific code the note supports, and treat modifiers as documentation decisions. These three habits cover most avoidable coding errors.
3. Use the code set that matches the date of service
Code sets are not static. According to CMS, new ICD-10-CM diagnosis codes for fiscal year 2027 take effect on October 1, 2026, and CMS lists that set for use through September 30, 2027. CMS also notes on its HCPCS page that the American Medical Association (AMA) republishes and updates CPT codes every year, and that CMS maintains HCPCS Level II codes. Load each update into your billing system before it takes effect.
| Item | Who maintains it | How often it changes | What your practice should do |
|---|---|---|---|
| ICD-10-CM diagnosis codes | CDC announces the codes; CMS lists them | Annually, by federal fiscal year (FY 2027 set effective October 1, 2026) | Load the update before October 1 and retrain on changed codes |
| CPT codes | AMA | Republished and updated every year | Update the code table and the charge master each year |
| HCPCS Level II codes | CMS | Additions, revisions and deletions decided by CMS | Check the release notes for the supplies and drugs you bill |
| NCCI procedure-to-procedure (PTP) and MUE edit files | CMS | Quarterly | Refresh your claim-scrubbing rules each quarter |
| NCCI Policy Manual for Medicare | CMS | Once a year | Review the changes affecting your common code pairs |
| Medicare claim filing limit | Set in 42 CFR 424.44 | Rule, not a calendar update | File within 1 calendar year after the date of service |
Source: CMS ICD-10 codes page; CMS HCPCS page; CMS NCCI page; 42 CFR 424.44 (eCFR). Pages read October 14, 2026.
4. Code to the most specific level the note supports
A vague diagnosis code can fail a payer’s medical-necessity checks or hide the severity of a case. Choose the most specific code the note supports. If the note is vague, query the provider rather than guessing. If the note is specific, do not fall back to an unspecified code out of habit.
5. Use modifiers and edit pairs on purpose
CMS describes the National Correct Coding Initiative (NCCI) as a program that promotes correct coding of Medicare Part B claims, and says its procedure-to-procedure edits are meant to prevent improper payment when incorrect code combinations are reported. Payers may run their own edits, and your scrubber should check for them. Treat a modifier as a statement about the note: if the record does not show a separate service, the modifier does not belong on the claim.
Rules and common edit pairs differ by specialty. Our specialty billing pages show how we group them, and a short coding cheat sheet for your top 20 services is worth building and reviewing each year.
Which habits protect the claim at submission?
Scrub the claim, enter charges promptly and watch the filing clock. A claim that is complete and on time avoids the rework that costs the most staff hours.
6. Scrub every claim before it leaves
A scrubber, whether a clearinghouse tool or a rule set in your billing system, should check required fields, code pairs, diagnosis pointers, modifiers and payer-specific rules. Define what counts as a clean claim in writing, because sources define it differently. Our clean claims guide gives the working definition we use and the reports that show where claims fail.
7. Enter charges promptly and file inside every deadline
Set an internal charge-entry limit that your practice can meet, such as the same business day or the next one, and report on the late ones. For Medicare, the rule at 42 CFR 424.44 says a claim must be filed no later than the close of the period ending 1 calendar year after the date of service, with limited exceptions. Commercial and Medicaid limits are set by each contract or program and can be much shorter, so record them per payer.
Habits 6 and 7 are easier when claims are visible. A practice management system that tracks claims by stage lets you see which claims are waiting on a charge, a note or a correction, and who owns each one. RCM Finder’s portal does this today, and it also checks claim data for completeness before submission.
Want to see where your claims leak?
Our free practice audit looks at your registration, coding and scrub steps against this list. Pricing for any service is quoted after the audit.
Which habits keep money from slipping after submission?
After submission, post every payment line by line, compare it with what you expected, and work each denial back to its cause. These habits turn the payer’s response into information.
8. Post payments line by line and compare them with the expected amount
Payment posting is where short payments become visible. Compare each remittance line with the allowed amount in your contract, and flag lines that pay less. A claim can show as paid and still be short. A weekly review of flagged lines by payer shows patterns that one-off calls will not.
9. Work denials by root cause, then fix the front end
Each denial has a reason code and a cause. The reason code tells you what the payer said, while the cause tells you where the process failed: registration, authorization, documentation, coding or timing. Count denials by cause, not only by payer, then change the step that produced them. Fix the cause upstream, and the appeal queue shrinks.
10. Send clear patient statements and set expectations early
Patients can pay only what they understand. A statement should show the date of service, what the insurer paid or adjusted, what the patient owes and why, the due date, how to pay and who to call. Tell patients about copays and deductibles at scheduling and check-in, so the statement is not the first they hear of it.
“Most billing problems are decided before the claim exists. A tidy front desk and a clear note beat a clever appeal.”
— Awais Afzal, Healthcare Operations & Data Analyst
How often should you audit your own claims?
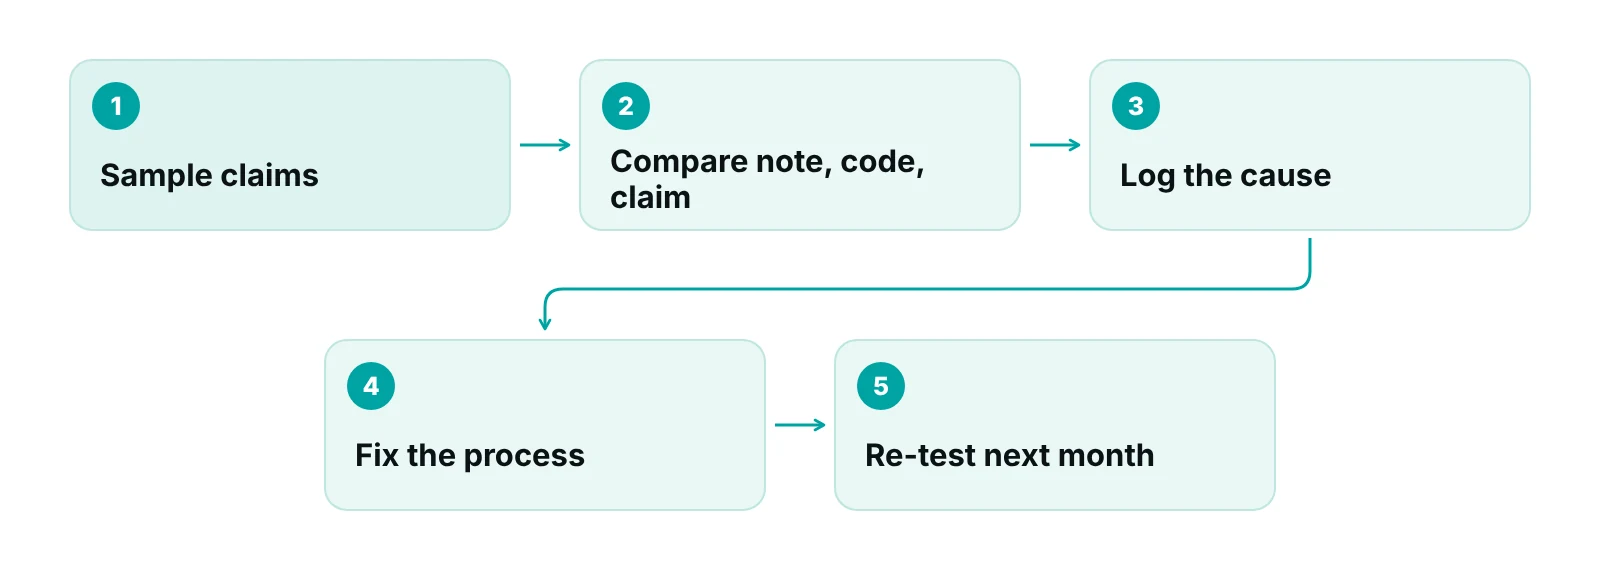
Review a small sample every month and look for causes, not just errors. The OIG’s 2023 guidance says compliance work should include regular reviews to keep billing and coding practices up to date, and that regular internal billing and coding audits are recommended. The guidance is voluntary and not binding, but it is a useful standard for a practice of any size.
- Pull a small random sample of paid and denied claims for each provider.
- Compare three things for each claim: the signed note, the codes billed and the payer’s response.
- Log the cause of every mismatch, such as missing documentation, wrong code, wrong modifier or registration error.
- Retrain on the top cause and re-test the next month.
Our guide to medical coding audits explains the audit types and when each fits. Audits also bring a legal duty. The OIG guidance says an entity that finds an overpayment, even from an innocent billing mistake, must report and return it by the later of 60 days after identification or the due date of any corresponding cost report.
Which habit should you fix first?
Start with the symptom you see most often. Match it to the habit that most likely causes it, then read the linked guide.
| What you see | Habit to check first | Why | Read next |
|---|---|---|---|
| Rejections for name, ID or coverage errors | 1. Verify coverage and registration | The error starts at scheduling or check-in | Insurance verification guide |
| Denials for missing or unsupported documentation | 2. Document first, then code | The note does not support the code billed | Medical coding audits guide |
| Claims bounce on code pairs or modifiers | 5. Use modifiers and edit pairs on purpose | The edit or the modifier logic is wrong | Specialty billing pages |
| Claims reach the payer with missing fields | 6. Scrub every claim | No check runs before submission | Clean claims guide |
| Payments look right but revenue is short | 8. Compare payments with the expected amount | Underpayments are not flagged | Accounts receivable metrics guide |
| The same denial reason keeps returning | 9. Work denials by root cause | The cause is not being fixed | Denial management guide |
Which numbers show whether the habits are working?
Track a few ratios on a fixed schedule, using one written definition for each. Do not copy a benchmark from a blog post, including this one. Benchmarks vary by specialty, payer mix and how a metric is defined.
For definitions and formulas, use our revenue cycle KPI guide for the full set, and our accounts receivable metrics guide for days in A/R and aging. If you want to estimate what unpaid or delayed claims cost your practice, the revenue calculator is a quick starting point.
Who should own these habits: staff, software or an outside team?
A practice can own all ten habits in-house if it has the staff time, a scrubber and someone who reads remittances. Consider outside help when claims age faster than staff can work them, when coders turn over often, or when payer rules outrun your training.
| Option | Works best when | What it does not cover | What to ask or check |
|---|---|---|---|
| In-house team | Volume is steady and one person owns each habit | Coverage during absences and turnover | Who owns each checkpoint and who backs them up |
| Software | You need visibility: claim stages, completeness checks, flags | Reading the note and choosing the code | Which checks run before submission and who acts on the flags |
| Hybrid | Staff own the front end and an outside team works claims and follow-up | Unclear ownership if roles are not written down | A one-page split of tasks and a weekly shared report |
| Outside team | You need coverage, specialty depth or cleanup | Registration and note quality at your front desk | A signed business associate agreement, written coding and audit routines, and readable reports |
If you want help, see our medical billing services. We work inside your existing EHR, for example PrognoCIS, eClinicalWorks or athenahealth. We start with a free audit, and pricing is quoted after it.
Our recommendations
- Write the claim path on one page. List the five checkpoints, the owner of each and the report that shows it is working. Share it with every new hire.
- Fix the front desk first. We start with registration and coverage checks, because those errors travel the farthest. Measure them before touching anything else.
- Query the provider, never guess. Give coders a written, neutral query process, and keep the answer with the note.
- Put the code-set calendar on the wall. Set reminders for the October ICD-10-CM update, the January CPT update and the quarterly NCCI edit files.
- Count denials by cause. We sort denials by where the process failed, not only by payer. That points to the habit that needs fixing.
- Audit a small sample every month. Compare the note, the code and the payer response. Log the cause, fix it and re-test the next month.
A practice management system built around claims, not charts.
RCM Finder's portal tracks each claim by stage with an owner, checks claim data for completeness before submission and flags payments below expected amounts. It is a claims system, not an EHR.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Good billing and coding is a set of small checks done in the same order every time. Start at registration, make the note support the code, scrub before you submit, and learn from every denial. If a part of the path needs help, see our denial management service or talk to us. A free practice audit is the easiest way to begin.
Frequently asked questions
What are the most important medical billing and coding tips for a small practice?
Start with accurate registration and coverage checks, code only from a signed note, use the code set that matches the date of service, scrub claims before submission and compare payments with expected amounts. Then audit a small sample monthly. These habits catch most avoidable errors before they become denials or write-offs.
How often do medical codes change?
ICD-10-CM codes change by federal fiscal year, and CMS lists the fiscal year 2027 set as effective October 1, 2026. The AMA republishes and updates CPT codes every year, and CMS maintains HCPCS Level II codes. NCCI edit files update quarterly. Check each source’s release notes for the exact changes.
What is the deadline to file a Medicare claim?
Under 42 CFR 424.44, a Medicare claim must generally be filed no later than the close of the period ending 1 calendar year after the date of service. The rule lists limited exceptions, such as certain errors by a Medicare contractor. Commercial and Medicaid limits vary, so check each contract or program.
Should billing staff or providers choose the codes?
The provider documents the service and is responsible for the note. Many practices let trained coders or billers assign codes from that note, then query the provider when something is missing or unclear. The signed record must support the code. Follow your payer contracts and your compliance policy.
How do I know whether my coding is accurate?
Audit it. Pull a small sample of claims each month, compare the signed note, the codes billed and the payer’s response, and log the cause of every mismatch. The OIG’s voluntary 2023 guidance recommends regular internal billing and coding audits. Repeat errors point to a training or process fix.
What should I do if I find I was overpaid?
Do not ignore it. The OIG’s 2023 guidance says an entity that identifies an overpayment must report and return it by the later of 60 days after identification or the due date of any corresponding cost report, if applicable. Involve your compliance contact or healthcare counsel to follow the right process for your payer.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- ICD-10 Codes — CMS (2026)
- Healthcare Common Procedure Coding System (HCPCS) — CMS (2026)
- National Correct Coding Initiative (NCCI) Edits — CMS (2026)
- 42 CFR 424.44 Time limits for filing claims — eCFR (2026)
- General Compliance Program Guidance — HHS OIG (2023)
- General Compliance Program Guidance (PDF) — HHS OIG (2023)
Disclaimer: This post is general educational information about revenue cycle operations. It is not legal, coding, compliance or financial advice. Code sets, payer rules and deadlines change and vary by payer, contract and state. Confirm requirements with each payer, current code-set publications and qualified advisors before acting.
