
RVUs in medical billing are the points Medicare assigns to each service: one for physician work, one for practice expense and one for malpractice cost. Medicare adjusts each for your locality, adds them up and multiplies by a dollar conversion factor. That product is the fee schedule amount.
Most explanations stop at the three components and skip the last step, the conversion factor. Without it, RVUs never become dollars. This guide covers the whole chain with CMS and eCFR sources, using values current as of October 2026.
It also corrects a common mix-up. You do not bill RVUs. You report a code and your charge, and the payer’s fee schedule turns that code into an amount. The numbers below help you check that the amount you receive is the amount you should.
Key takeaways
- An RVU has three parts: work, practice expense and malpractice. Each is set per service.
- Medicare payment = (work RVU x work GPCI + PE RVU x PE GPCI + MP RVU x MP GPCI) x conversion factor.
- The CY2026 non-qualifying APM conversion factor is $33.40, and CMS proposed $32.84 for CY2027.
- The same code can pay differently by locality, by setting (facility or office) and by participation status.
- Check your top codes against the CMS fee schedule each January before you trust an expected-payment number.
What is an RVU in medical billing?
A relative value unit (RVU) is a point value that ranks one physician service against others. Under Medicare, 42 CFR Part 414, Subpart B says CMS sets RVUs for three things: physician work, practice expense and malpractice insurance. Each CPT or HCPCS code gets its own set of values.
RVUs are relative, not dollars. A service with a work RVU of 2.0 is rated at about twice the physician work of a service rated 1.0. The dollar figure only appears once a conversion factor is applied.
| Component | What it measures | Where it varies |
|---|---|---|
| Work RVU | The physician work of the service, rated against other physician services | By code |
| Practice expense (PE) RVU | Practice costs such as staff, supplies and equipment, computed for each service or class of service | By code and by setting (facility or non-facility) |
| Malpractice (MP) RVU | Malpractice insurance costs, computed for each service or class of services | By code |
Source: eCFR, 42 CFR 414.22 (current as fetched October 2026). Descriptions paraphrased.
The work component is the one most people mean when they say wRVU. It is only one of three inputs to the Medicare payment.
How do RVUs become a Medicare payment?
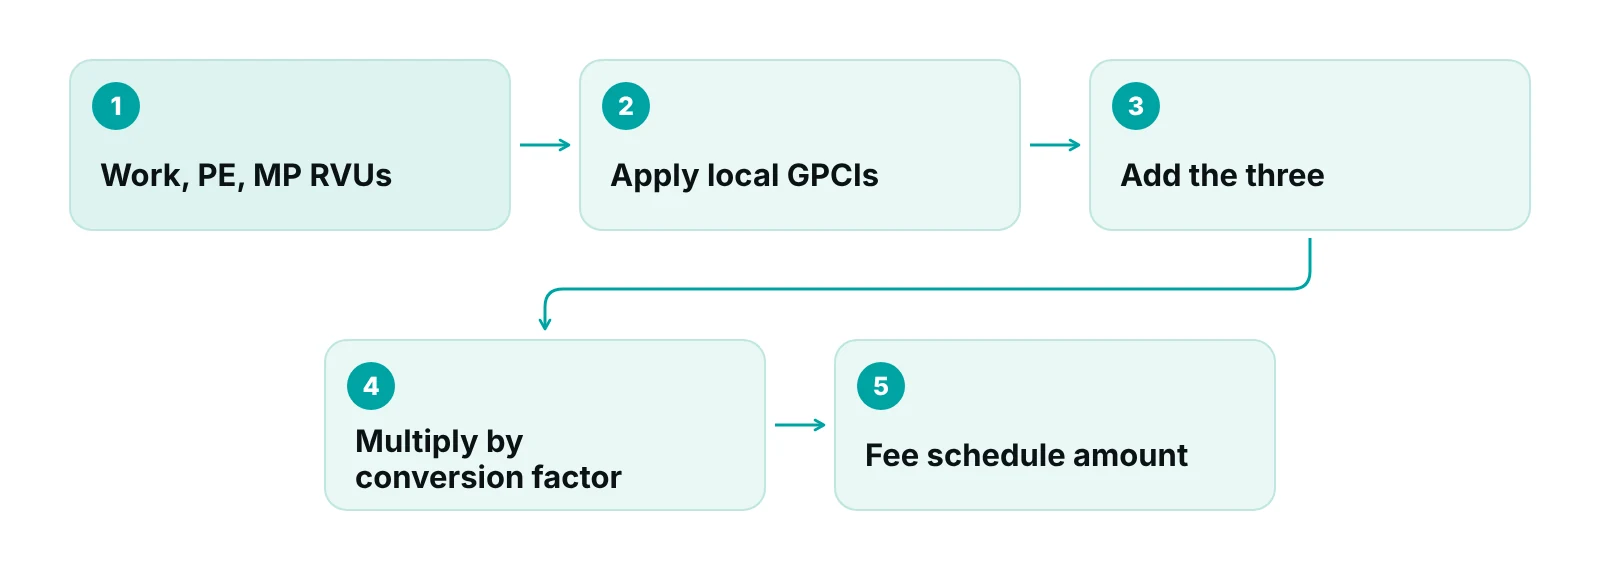
Medicare multiplies each RVU component by a geographic index, adds the three results and multiplies the total by the conversion factor. The CMS fee schedule documentation page gives the non-facility formula as (work RVU x work GPCI) + (non-facility PE RVU x PE GPCI) + (MP RVU x MP GPCI), then x conversion factor.
What is a GPCI?
A geographic practice cost index (GPCI) adjusts an RVU for local costs. CMS publishes GPCIs for each payment locality and for each of the three components, so a locality has a work GPCI, a PE GPCI and an MP GPCI. Two practices billing the same code in different localities can receive different amounts for that reason alone.
Facility and non-facility payment
The practice expense RVU depends on where the service is performed. CMS lists the same formula for facility settings but uses the facility PE RVU. In the CY2026 final rule, CMS also finalized greater indirect practice expense costs for office-based practitioners than for facility-based ones, so the setting matters more than it did.
A worked example with illustrative numbers
The values below are invented to show the arithmetic. They do not belong to any real CPT code. Look up your own codes in the CMS PFS look-up tool or the annual RVU file. The conversion factor used is the CY2026 non-qualifying APM figure of about $33.40.
| Component | RVU | GPCI | RVU x GPCI |
|---|---|---|---|
| Work | 2.00 | 1.02 | 2.040 |
| Practice expense (non-facility) | 1.50 | 0.95 | 1.425 |
| Malpractice | 0.20 | 0.90 | 0.180 |
| Total adjusted RVUs | 3.645 | ||
| Total x $33.40 conversion factor | about $121.74 |
Source: Formula from CMS, Physician Fee Schedule documentation; conversion factor from CMS CY2026 PFS final rule fact sheet (2025). RVU and GPCI values are illustrative only.
If the same service were done in a facility, and the facility PE RVU were 0.60 instead of 1.50, the PE line would be 0.570. The total would be 2.790 adjusted RVUs, or about $93.19. Same code, same locality, a different payment. That gap is why the place of service on the claim has to be right.
The fee schedule amount is not always the amount you collect
The result is the Medicare fee schedule amount for that code and locality. Patient cost sharing, participation status and other payer rules decide what is collected. Other payers set their own rates, so read each contract to see whether it uses Medicare as a base.
What changed in the conversion factor for 2026 and 2027?
For CY2026, CMS set two conversion factors (the 2025 Medicare payment cuts post covers the year before). The CMS CY2026 final rule fact sheet lists $33.57 for qualifying APM participants and $33.40 for everyone else, up from $32.35. It describes a one-year increase of 2.50 percent for 2026 that is set by statute.
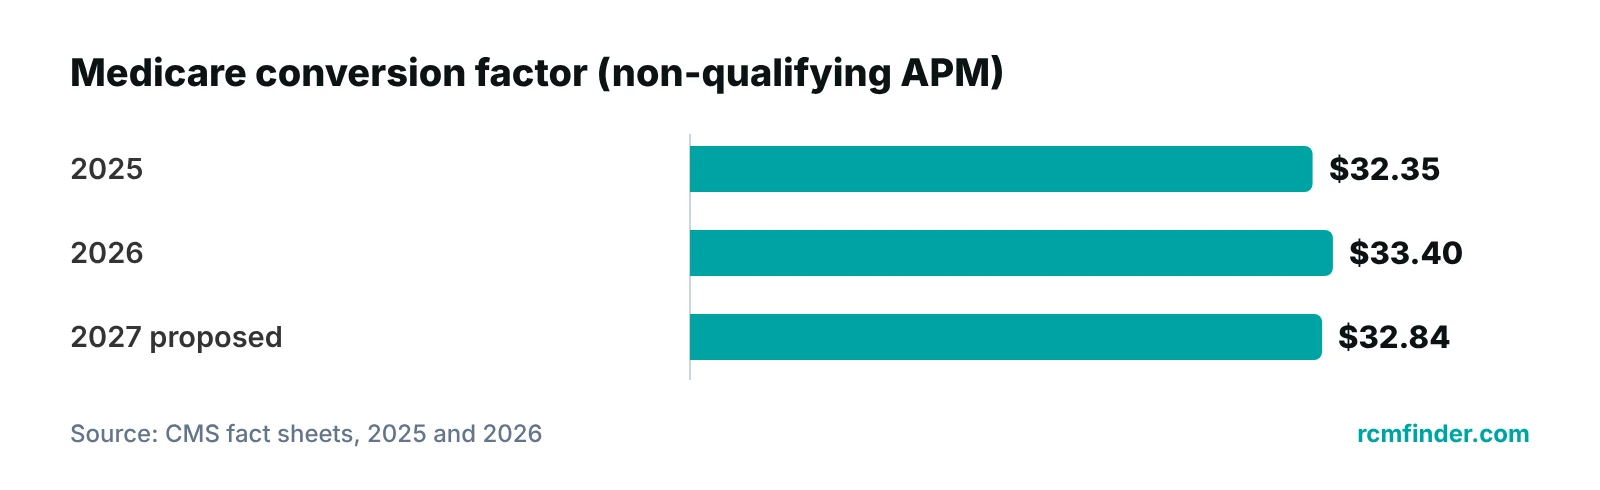
For CY2027, the CMS CY2027 proposed rule fact sheet proposes $33.17 for qualifying APM participants and $32.84 for others. CMS attributes the decrease mainly to the expiry of the one-year 2.50 percent increase. This is a proposal, not a final rule. Final figures can change.
The 2026 efficiency adjustment
CMS also finalized a minus 2.5 percent efficiency adjustment for CY2026. It applies to work RVUs and the intraservice part of physician time for non-time-based services. Time-based codes are excluded, including E/M, care management, behavioral health, telehealth-list services and certain maternity codes. A procedure-heavy code mix is therefore more exposed than an E/M-heavy one.
Do not reuse last year's expected amounts
A fee schedule amount copied from a 2025 spreadsheet can be wrong for 2026. The conversion factor, the RVUs and the practice expense method all changed. Reload the current RVU file and GPCIs each year and rebuild your expected-payment list for your top billed codes.
Why can the same code pay differently?
Medicare payment for one code varies with locality, setting, year and participation status. Knowing which of these applies to a claim is the fastest way to explain a payment that looks off.
| Factor | What changes | What to check |
|---|---|---|
| Locality | GPCIs are set per payment locality for work, PE and MP | That each claim uses the locality of the service |
| Setting | Facility and non-facility claims use different PE RVUs | The place of service on the claim |
| Year | RVU files and conversion factors are issued per year; CY2026 differs from CY2025 | That your expected amounts use the current year’s file |
| Participation status | Non-participating suppliers are paid 95 percent of the fee schedule amount; the limiting charge is 115 percent of that payment | Your participation status with Medicare |
| Code-level adjustments | The 2026 efficiency adjustment lowers work RVUs on many non-time-based codes | Your top procedure codes against the current file |
Source: eCFR 42 CFR 414.20 (current as fetched October 2026); CMS PFS documentation page; CMS CY2026 PFS final rule fact sheet (2025).
For a non-participating supplier, 42 CFR 414.20 sets payment at 95 percent of the fee schedule amount. CMS notes the limiting charge is 115 percent of that payment, which works out to the fee schedule amount multiplied by 1.0925.
Most of this is invisible on the remittance. The adjustment between your charge and the allowed amount usually appears as a contractual adjustment, so understanding the CO-45 adjustment code helps you read where a charge reduction comes from.
RVU, charge, fee schedule amount: what is the difference?
These terms get mixed up on the billing floor. Keeping them apart makes underpayments easier to find, because each one sits at a different step between the visit and the deposit.
- RVU: a relative point value for a code. It is not money.
- Fee schedule amount: the dollar result of the Medicare formula for a code, locality and setting.
- Charge: the price your practice sets and bills. It can be higher or lower than the fee schedule amount.
- Allowed amount: the amount a payer accepts for the service under its schedule or contract.
- Contractual adjustment: the difference between your charge and the allowed amount, written off under the contract.
Five mistakes that distort expected payments
- Using the work RVU alone as if it were the whole payment, when the formula adds practice expense and malpractice.
- Leaving out the conversion factor, so the RVU total never becomes a dollar figure.
- Skipping the GPCIs, or using the wrong locality for the service.
- Mixing facility and non-facility practice expense RVUs for the same claim.
- Reusing a prior-year RVU file or conversion factor after the new year starts.
Each mistake is easy to catch when expected amounts live in one maintained list with a version date. They are hard to catch when the numbers live in several personal spreadsheets.
How should a practice use RVUs?
Use RVUs to build expected payments and spot underpayments, not as a number to put on claims. Price your charge entry list with the fee schedule in view, then compare what posts against what the schedule says should post.
Some practices and employers also use work RVUs to measure or pay for productivity. If yours does, that is a private compensation plan set by its own contract. It is separate from the Medicare formula above, which does not depend on how any one physician is paid.
Specialty changes the picture. Procedure-heavy, imaging and primary care practices rely on different codes, so the 2026 changes land differently. Our specialty billing pages show how billing patterns differ by specialty, and the Medicare fee-for-service billing guide covers the claim side.
“An expected-payment list built once and never refreshed is a guess. Rebuild it every year, starting with the codes that bring in the most revenue.”
A practice management system that tracks claims by stage can hold an expected amount per code and payer and flag a claim that is paid below it. Whatever tool you use, the habit matters more than the software: set the expected amount, compare it to the payment, and send the gap to a person who owns it. To see how small per-claim gaps add up, try our revenue calculator.
Want your fee schedule checked against what payers actually paid?
Our free practice audit looks at how your top codes are billed and paid, and flags where payments land below the expected amount.
Our recommendations
- Know which formula your payer uses. This guide covers Medicare. Read each commercial and Medicaid contract to see how its rates are set and which year’s schedule it follows. Our guide to healthcare reimbursement types explains the common payment models.
- Rebuild expected amounts every January. Download the current RVU file and GPCIs, then refresh your expected payment for each of your top 25 codes by revenue.
- Check the place of service. A facility versus office error changes the PE RVU and so the payment. Review it on a sample of claims each month.
- Compare the payment to the fee schedule amount. When a Medicare payment lands below what the formula gives, check locality, setting and participation status first, then escalate.
- Track the 2027 final rule. The CY2027 conversion factor is proposed, not final. Plan budgets with a range and update when CMS publishes the final rule.
- Keep compensation and billing separate. If you pay physicians on work RVUs, document that plan on its own. Do not assume it matches what any payer pays.
A practice management system can hold the expected amount for a code and flag claims paid below it.
RCM Finder's portal tracks claims by stage with an owner and flags underpayments against expected amounts, so a gap between the fee schedule and the payment goes to a named person.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
RVUs explain how Medicare prices a code, but only the conversion factor, the locality and the setting turn them into a payment. Check your top codes against the current schedule each year and chase any gap. If you want help reviewing how your claims are billed and paid, see our medical billing services or contact us to start with a free practice audit.
Frequently asked questions
What does RVU mean in medical billing?
RVU stands for relative value unit. It is a point value CMS assigns to each service for physician work, practice expense and malpractice cost. The points rank services against each other and are not dollars. Medicare converts them into dollars by adjusting each for locality and multiplying the total by a conversion factor.
What is a work RVU?
A work RVU rates the physician work of a service against other physician services. It is one of the three Medicare RVU components. Some employers also use work RVUs in compensation plans, but that is a separate private arrangement from Medicare payment.
How do you calculate Medicare payment from RVUs?
Multiply each RVU by its GPCI, add the three results, then multiply by the conversion factor. For office-based services, use the non-facility PE RVU. For services in a facility, use the facility PE RVU. The result is the Medicare fee schedule amount for that code and locality, before any patient cost sharing.
What is the 2026 Medicare conversion factor?
CMS set two for CY2026: $33.57 for qualifying APM participants and $33.40 for everyone else. For CY2027, CMS proposed $33.17 and $32.84. The 2027 figures are a proposal until the final rule is published.
Do claims include RVUs?
No. You report CPT or HCPCS codes, modifiers, units and your charge. The payer applies its own fee schedule to the code to find the allowed amount. Use RVUs on your side as a check, to see what a Medicare payment for that code and locality should be.
Do Medicaid and commercial payers use Medicare RVUs?
It depends on the payer and the contract. This guide covers Medicare only. Read each state Medicaid fee schedule and each commercial contract to see how its rates are set, whether they follow Medicare at all, and which year’s values apply to your claims.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- 42 CFR Part 414 Subpart B (sections 414.20, 414.22, 414.26) — eCFR (2026)
- Physician Fee Schedule documentation and files — CMS (2026)
- CY 2026 Medicare Physician Fee Schedule Final Rule fact sheet — CMS (2025)
- CY 2027 Medicare Physician Fee Schedule Proposed Rule fact sheet — CMS (2026)
Disclaimer: This article is educational. It is not legal, coding or compliance advice. Medicare values change each year and payer rules vary, so confirm figures against the current CMS files and your contracts.
