
Self-pay patient billing starts with a written good faith estimate before the service, sent within 1 to 3 business days of scheduling. Then publish one price list, offer a few clear payment options, send itemized bills that match the estimate and keep a written policy. Dispute rights begin at $400 above the estimate.
Many practices bill uninsured and cash-pay patients with an informal price and a verbal quote. Since 2022 that is not enough. A federal rule sets a written estimate, a clock and a dispute process, and the details are easy to get wrong.
This guide replaces an earlier version of this post. It corrects the estimate rule, removes numbers we could not trace to a primary source and adds practical pricing and policy steps for the front desk and billing team.
Key takeaways
- A self-pay patient is uninsured, or insured but choosing not to use coverage for the service.
- The estimate is due within 1 or 3 business days of scheduling, depending on how far ahead the visit is; there is no dollar minimum.
- The $400 figure is the dispute threshold, not the trigger for giving an estimate.
- Keep the final bill tied to the estimate and send an updated estimate if the plan of care changes.
- One published price list, applied consistently, avoids most disputes.
Who counts as a self-pay patient?
Under the federal No Surprises Act rules, a self-pay patient is someone with no coverage for the service, or someone who has coverage but does not want a claim sent to it. The definition is in 45 CFR 149.610. Your front desk has to ask the question, because the patient may not volunteer it.
That second group matters. A patient with a high-deductible plan who lets you bill the plan is not self-pay for this purpose, even if they will owe the full allowed amount until the deductible is met. Their balance is patient responsibility under the payer contract. A patient with the same plan who says “I will pay cash instead” is self-pay.
The group is large enough to plan for. In its 2025 employer survey, KFF found that 33% of covered workers were enrolled in a high-deductible plan with a savings option, and that 88% of workers with single coverage had a general annual deductible, averaging $1,886 among those who had one. Those are insured patients, but a large deductible is often what pushes someone to ask for a cash price.
- Uninsured: no coverage for the service. A good faith estimate is required.
- Insured but paying cash: coverage exists, but the patient chooses not to have a claim submitted. Treated as self-pay under the same definition.
- Insured and using coverage: not self-pay. Verify benefits and collect the patient share instead. See our guide to patient insurance verification.
- Out of network, insured: a different situation with its own rules. Our out-of-network billing guide covers it.
Medicare and Medicaid patients need a second look
The federal definition counts a person who has benefits under a federal program but does not want a claim submitted. Separately, CMS’s dispute-process page states that enrollees in federal health care programs are not eligible for a good faith estimate. We could not reconcile the two statements from the pages we reviewed, so check your Medicare and Medicaid cash-pay policy with a healthcare attorney or your MAC before applying it.
When must you give a good faith estimate?
Before the service, and on a clock that depends on how far ahead the visit is scheduled. There is no dollar minimum for the estimate itself. The old advice that an estimate is only needed above $400 is wrong; $400 relates to a different step, the dispute process, covered below.
The convening provider, meaning the provider or facility that schedules the primary service or receives the request, issues the estimate. Other providers who will furnish related services, such as anesthesia, send their expected charges to the convening provider rather than to the patient. The timing is set in 45 CFR 149.610.
| Situation | Deadline for the estimate | Practical note |
|---|---|---|
| Service scheduled at least 3 business days ahead | Within 1 business day of scheduling | Start the estimate at the moment of booking, not at check-in. |
| Service scheduled at least 10 business days ahead | Within 3 business days of scheduling | Gives time to collect co-provider information. |
| Patient asks what the service will cost | Within 3 business days of the request | Applies even if no visit is booked yet. |
| Scope changes (new items, providers, frequency or charges) | Updated estimate no later than 1 business day before the service | Tell the patient in writing, not only at the desk. |
| Co-providers asked for their information | Convening provider asks within 1 business day of scheduling; co-provider replies within 1 business day | Build a standing contact for each co-provider. |
Source: 45 CFR 149.610, eCFR (current version, reviewed 2026-10-14)
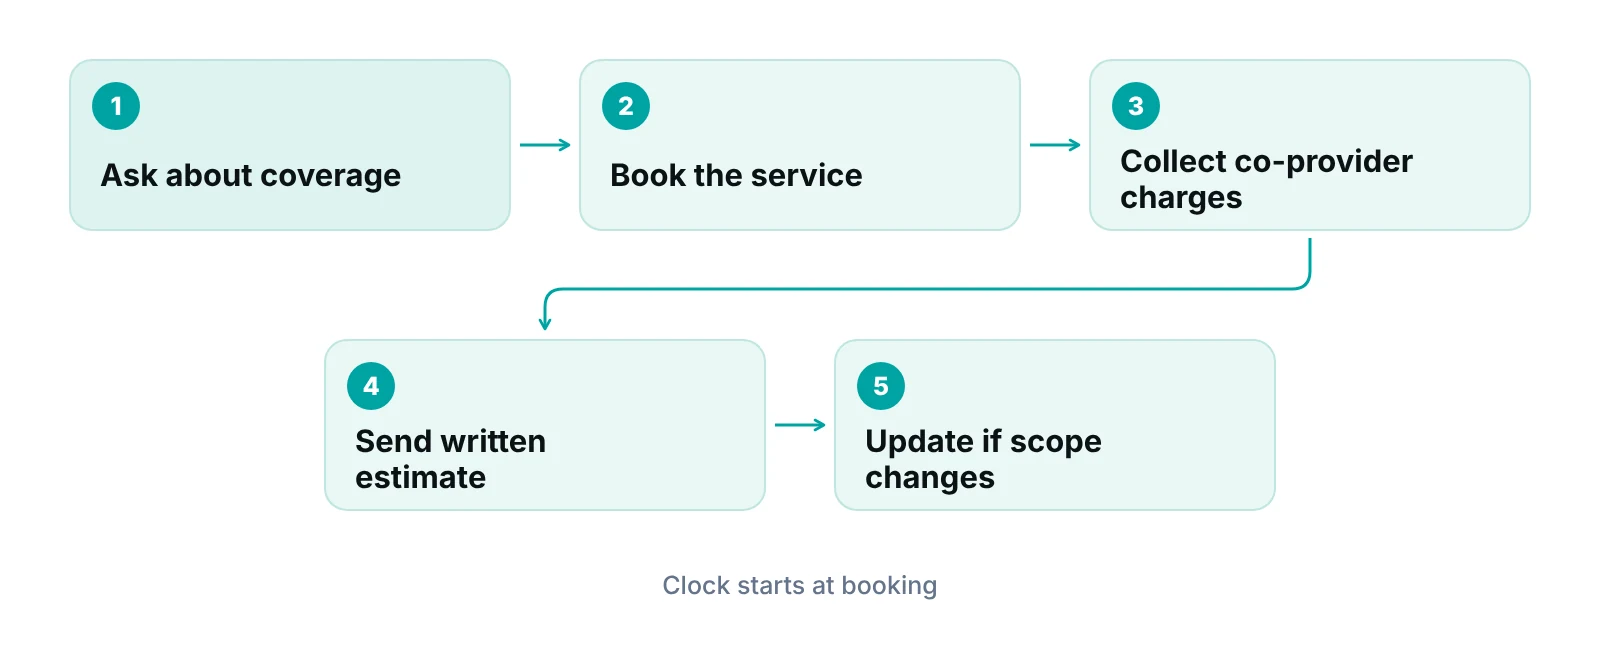
Two details help in an audit. The estimate becomes part of the patient’s medical record, and the convening provider must give a copy of any estimate issued in the past 6 years on request. A recurring-service estimate may cover no more than 12 months; after that, a new one must explain what changed. Both points are in the same eCFR text.
What does a good faith estimate have to include?
It must be in writing, in plain language, and itemized by provider or facility. Electronic copies must be savable and printable. You may answer a phone or in-person request orally, but a written estimate must still follow.
| Element | What to include |
|---|---|
| Patient details | Name and date of birth. |
| Primary service | Description of the primary item or service and the scheduled date, if there is one. |
| Itemized list | Expected items and services for the period of care, grouped by provider or facility. |
| Codes and charges | Diagnosis codes, service codes and the expected charge for each item. |
| Provider identifiers | Name, NPI and TIN of each provider or facility, with the state and location of service. |
| Separately scheduled items | A list of items that need separate scheduling, plus the required disclaimer and how to get those estimates. |
| Disclaimers | The estimate is not a final bill and charges may differ; it is not a contract; the patient may start the dispute process if billed charges are substantially higher than the estimate. |
Source: 45 CFR 149.610, eCFR (current version, reviewed 2026-10-14)
Separate from the estimate, CMS says information about good faith estimates must be posted on your website and in the office or on-site where services are scheduled. If a patient asks about cost, you must tell them, orally or in writing, that they can request an estimate. That is from CMS. Many practices miss this posting step.
Honest mistakes are treated differently
The regulation says a good-faith error or omission is not a violation if it is corrected as soon as practicable, and it protects reasonable reliance on another entity’s information. That is not a reason to skip the process. It is a reason to keep a documented correction step.
What if the final bill is higher than the estimate?
A self-pay patient can start a patient-provider dispute process if the bill is at least $400 more than the expected charges for that provider or facility. CMS describes the process on its dispute-resolution page. This is where the $400 figure belongs.
- Threshold: $400 above the total expected charges, assessed separately for each provider or facility on the estimate. Charges for items not on the estimate count toward the billed total.
- Deadline: the patient must start the process within 120 calendar days of receiving the initial bill. CMS notes the sample disclaimer counts from the date on the original bill, so wording differs by source.
- Fee: $25 administrative fee, which CMS says may change in future years.
- Settlement: if the parties settle, the provider must apply a reduction of at least $12.50, half the fee.
The practical lesson is to keep the final bill tied to the estimate. If the plan changes, issue an updated estimate before the service. A charge that was never on an estimate is the easiest way to end up in this process. Our guide on surprise medical bills and how to dispute them explains the patient’s side of it.
How should you set self-pay prices?
Pick one published fee approach, apply it to every self-pay patient, and write it down. There is no federal rule that fixes the discount level. The old claim that discounts should stay under 30% of usual fees has no basis in anything we could verify, so we removed it.
The three common structures are easy to compare. None is required, and the right one depends on your specialty and how many cash patients you see.
- Single flat fee per visit or service: easy for patients and staff to understand, but may not reflect the cost of complex visits.
- Fee schedule: a price list built from your costs and local market rates. Flexible and transparent, but it needs clear communication before the visit.
- Bundled or package price: one price for a defined episode, such as a procedure and its follow-up. Predictable and easy to turn into an estimate, but you must be precise about what is included.
- Sliding fee scale: tiers based on ability to pay. It serves lower-income patients, but needs documented criteria applied the same way every time.
“A self-pay price only works when the patient hears it before the visit, sees it in writing and gets a bill that matches.”
Whatever you choose, build the price list from your actual costs and the going local rate, review it at least once a year and apply it consistently. Inconsistent discounts are the part that causes trouble, both with patients and with regulators.
Be careful with Medicare and Medicaid copays
Discounting a self-pay price is a different thing from waiving the copay or deductible of a Medicare or Medicaid patient. The HHS Office of Inspector General’s bulletin on gifts and other inducements says routine waivers of those amounts are not protected. The statutory exception covers only non-routine, unadvertised waivers based on individualized determinations of financial need or exhaustion of reasonable collection efforts. The bulletin does not address discounts for uninsured or self-pay patients. If you are unsure whether a discount touches a federal program patient, ask counsel.
Which payment options should you offer?
Offer two or three options and make them easy to choose at scheduling: pay in full, a short instalment plan, or a longer plan for larger balances. Fewer, clearer choices get used more than a long menu. Our post on patient payment plans goes deeper on plan design.
| Option | Best for | Main benefit | Main risk |
|---|---|---|---|
| Pay in full at scheduling or check-in | Low-cost services and predictable visits | Nothing to chase afterwards | Some patients delay care if the sum is large |
| Prepaid discount for early payment | Practices that want cash earlier | Faster cash and fewer statements | Must be offered to all self-pay patients on the same terms |
| Short instalment plan, no interest | Mid-sized balances | Lower default risk than an open balance | Needs a written agreement and tracking of due dates |
| Longer plan with scheduled payments | Large procedures | Makes care affordable | Higher chance of missed payments; review plan terms with counsel |
Put the payment plan terms in writing: the amount, the due dates, what happens after a missed payment and who the patient contacts. Check the rules in your state, and with counsel, before adding interest or fees to any plan.
What belongs in a written self-pay policy?
A one-page policy that the patient sees before the visit and signs or acknowledges. It should say when payment is due, which methods you accept, how to get an itemized bill, how estimates work and what happens if an account falls behind.
- Payment timing: in full at the time of service, or by an agreed date.
- Accepted methods: cash, card, check or a plan.
- Itemized bills: list each service, its code if you use one, and the charge, so the total ties back to the estimate.
- Financial assistance: state clearly whether you offer it and how a patient applies.
- Past-due steps: a reminder schedule, a final notice and a named person to contact.
The front desk carries most of this work. A script that asks about coverage at booking, offers the estimate and explains payment options removes most disputes before they begin. Our article on how front desk staff affect the revenue cycle covers that, and improving patient collections covers follow-up.
Primary care and other high-volume practices see the widest mix of insured, uninsured and cash-pay patients, so the setup matters most there. Our family practice billing support page lists the billing support we offer for primary care.
If a patient stops paying
Contact the patient in writing first and offer a plan. If you consider ending the relationship, the AMA Code of Medical Ethics, Opinion 1.1.5 says to give notice long enough in advance for the patient to secure another physician, and to help facilitate transfer of care when appropriate. Many states add their own rules and your payer contracts may too, so a healthcare attorney should review your dismissal letter before you send it. The opinion does not address payment disputes or state law.
Check your self-pay workflow
Our free practice audit looks at how you handle estimates, payment options and patient balances, and shows where to tighten the process. Pricing for any service is quoted after the audit.
When does outside help make sense?
Consider it when patient balances age faster than your team can work them, or when estimates are late because no one owns the process. Estimates and payment plans are front-end tasks. Statements and follow-up are back-end tasks. Both are manageable in-house in a small practice, and both can be handed off in parts.
If you want help, look for support that fits your setup: charge entry and billing from medical billing services, or a team to run patient balance follow-up. Ask any vendor how it protects patient data, whether it will sign a Business Associate Agreement and how you can see the work it does.
Our recommendations
- Ask about coverage at booking. Make the coverage question a required field in scheduling. It is the trigger for the estimate.
- Start the estimate clock at scheduling. Set a task for the next business day for near-term visits. Missing the deadline is easier to prevent than to fix.
- Keep one price list. Publish it, date it and apply it to every self-pay patient. Do not discount ad hoc.
- Tie the final bill to the estimate. If the plan of care changes, send an updated estimate before the service. Compare each bill with the estimate before it goes out.
- Post the notice. Put the good faith estimate information on your website and at the scheduling desk. Check it every quarter.
- Keep federal-program patients separate. Write a short rule for Medicare and Medicaid patients and get it reviewed by counsel.
- Get legal review on dismissals and plan terms. Have a healthcare attorney check your dismissal letter and any plan with interest or fees.
Bottom line
Self-pay billing works when the price, the estimate and the bill all match. Ask about coverage at booking, send the estimate on time and keep a written policy. If patient balances are where your team falls behind, our accounts receivable management services and revenue cycle management support can take on the follow-up, and our revenue calculator can show what unpaid balances cost you.
Frequently asked questions
Do I have to give every self-pay patient a good faith estimate?
Yes, for scheduled services, if the patient is uninsured or has coverage but chooses not to use it. There is no dollar minimum for the estimate. It is also required when a patient asks what a service will cost. Check your Medicare and Medicaid policy with counsel, because the sources we reviewed differ for federal program enrollees.
What is the $400 figure in the good faith estimate rules?
It is the dispute threshold. A self-pay patient can start the patient-provider dispute process if the bill is at least $400 more than the expected charges for that provider or facility. It does not set a minimum for when you must give an estimate.
How soon must the estimate be sent?
Within 1 business day of scheduling if the service is at least 3 business days away, and within 3 business days if it is at least 10 business days away. A patient request for cost information also has a 3-business-day deadline. Updated estimates are due no later than 1 business day before the service.
Can I give a self-pay patient a discount?
Usually yes for true self-pay patients, if you apply it consistently, but we could not verify any percentage cap. Waiving the copay or deductible of a Medicare or Medicaid patient is different, because routine waivers are not protected under the OIG’s analysis. Ask counsel about edge cases.
Is a patient with a high-deductible plan a self-pay patient?
Not if you bill the plan. If the patient uses coverage, they owe the allowed amount until the deductible is met, and you collect the patient share. They become self-pay for this purpose only if they decline to have a claim submitted.
Can I dismiss a patient who does not pay?
Sometimes, but do it carefully. The AMA’s ethics guidance says to give enough notice for the patient to find another physician and to help with transfer of care. State rules and payer contracts may add requirements, so have an attorney review the process.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- 45 CFR 149.610 Requirements for provision of good faith estimates for uninsured (or self-pay) individuals — eCFR (2026)
- Good faith estimate and patient-provider dispute resolution process for uninsured or self-pay individuals — CMS (n.d.)
- 2025 Employer Health Benefits Survey: Summary of Findings — KFF (2025)
- Special Advisory Bulletin: Offering Gifts and Other Inducements to Beneficiaries — HHS Office of Inspector General (n.d.)
- Opinion 1.1.5 Terminating a Patient-Physician Relationship — American Medical Association (n.d.)
Disclaimer: This article is general educational information for medical practice owners and managers. It is not legal, compliance, coding or billing advice. Federal rules, state law and payer contracts vary and change. Confirm requirements with a healthcare attorney and each payer before acting.
