
Outsourcing DME billing makes sense when your orders, delivery records and notes are dependable and the real limit is billing capacity or DME know-how. A billing partner can only bill what your files support, and you stay responsible for every claim. Compare in-house, outsourced and hybrid models first.
Durable medical equipment (DME) billing is not general medical billing with different codes. Claims depend on orders, delivery proof, prior authorization for listed items and, for rented equipment, month-by-month payment rules. This guide helps a DME supplier decide whether to hand billing to a partner and how to do it safely.
It does not repeat code lists. For those, see our HME vs DME billing guide and guide to DME billing modifiers.
Key takeaways
- Outsource when your orders and delivery records are reliable; a partner cannot fix missing paperwork.
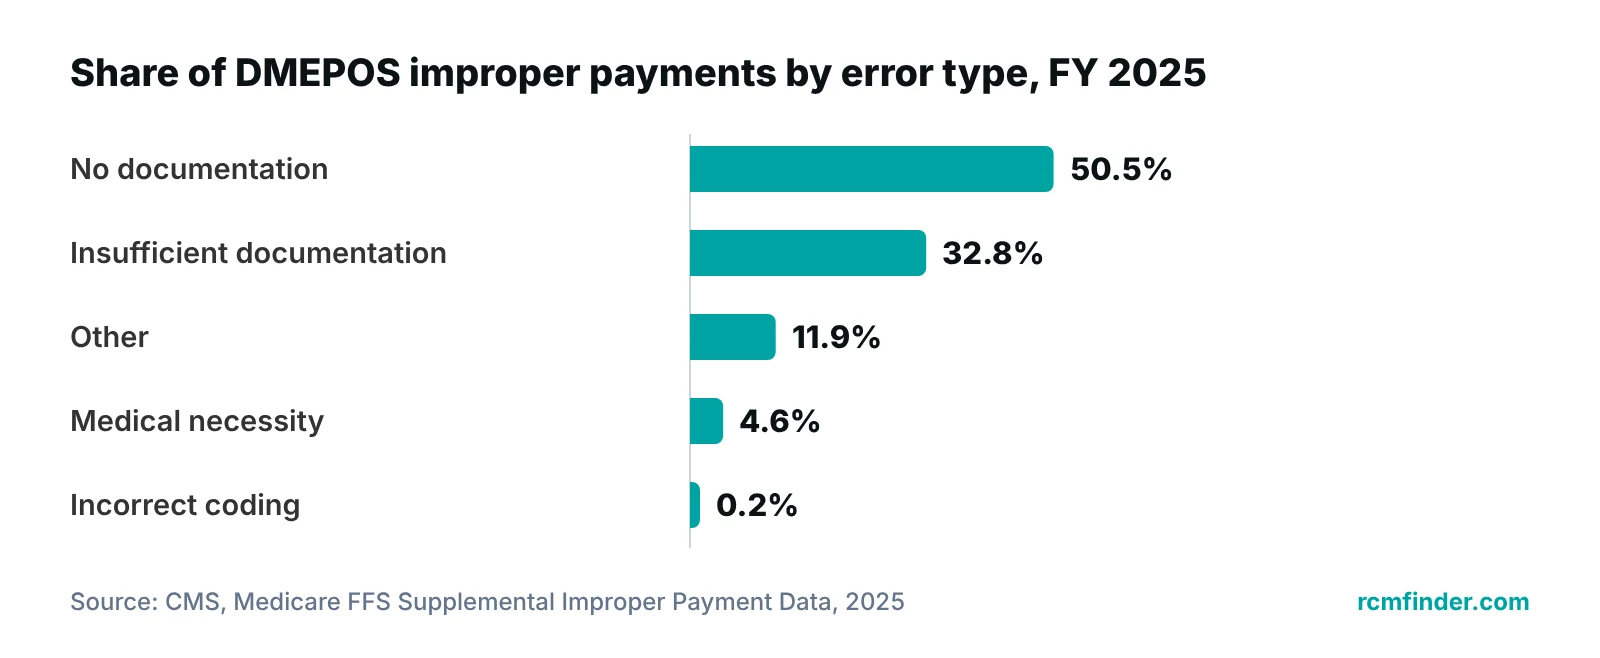
- In FY 2025, CMS tied most DMEPOS improper payments to missing or insufficient documentation, not coding.
- You stay the Medicare supplier: the supplier number, accreditation and bond remain yours.
- A hybrid model, with intake and delivery records in-house, suits many suppliers.
- Ask six DME-specific questions on orders, prior authorization, rentals, proof of delivery and payments.
Should a DME supplier outsource its billing?
Outsource when the paperwork behind your claims is reliable and the bottleneck is people, time or DME-specific knowledge. Do not outsource to escape a weak intake process. A billing partner works from the records you give it, so missing orders or delivery proof become denials no matter who submits the claim.
CMS data points the same way. In its fiscal year 2025 improper payment report, the Medicare fee-for-service improper payment rate for DMEPOS was 24.1%, measured on claims submitted from July 1, 2023 to June 30, 2024. Of the improper payments, 50.5% were no documentation and 32.8% were insufficient documentation. Incorrect coding was 0.2%. An improper payment is not the same as fraud: it means a claim did not meet a rule. For DME, the weak spot is more often the file than the code.
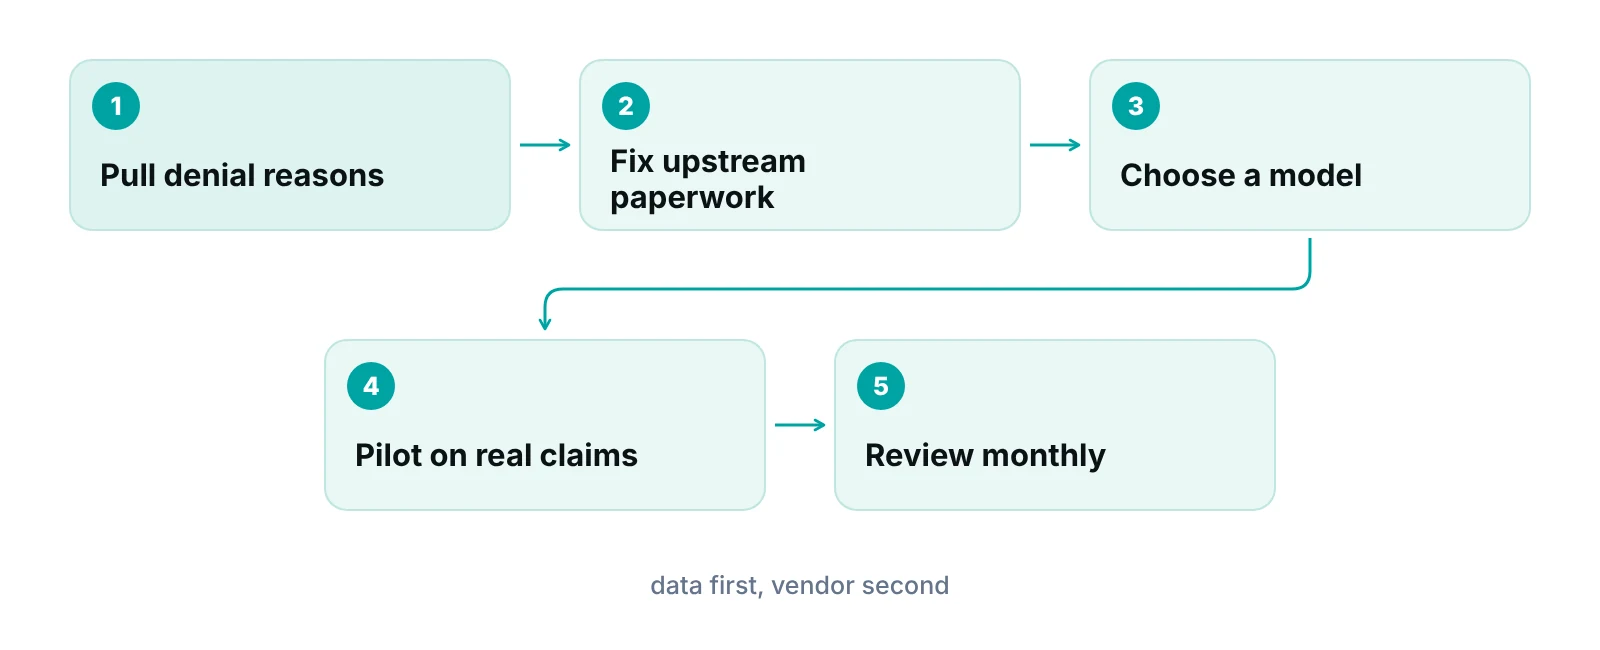
So the first question is not which vendor to pick. It is where your own claims fail today. Pull twelve months of denials and group them by reason: missing order, missing delivery record, no prior authorization, medical necessity, rental month errors, coding. If most sit upstream of billing, fix intake first or choose a hybrid model.
How is DME billing different from general medical billing?
The main difference is that a DME claim is built around an item and its paperwork trail, not around a visit. For Medicare, the supplier must be able to show an order, proof of delivery and, for some items, prior authorization before payment is safe. The table below covers Medicare fee-for-service; commercial payers set their own rules.
| Area | General medical billing | DME supplier billing (Medicare) |
|---|---|---|
| What starts the claim | A documented patient visit or procedure | An item furnished to the patient. The supplier must be responsible for delivery and keep proof of delivery |
| Order | Charge comes from the encounter note | A standard written order from the treating practitioner: patient name or MBI, general item description, quantity if applicable, order date, practitioner name or NPI, and signature |
| Extra pre-delivery steps | Referral or authorization only when a payer asks | Some items on CMS’s Master List need a face-to-face encounter and a written order before delivery |
| Prior authorization | Set payer by payer | CMS keeps a Required Prior Authorization List. A claim for a listed item is denied if it has no provisional affirmation |
| Payment pattern | One claim per service | Capped rental items are paid monthly for up to 13 continuous months, then the supplier transfers title to the patient |
| Enrollment | Practitioner enrolls and bills | The supplier must be separately accredited and submit a surety bond of $50,000, or more if the contractor requires it |
Source: 42 CFR 424.57 (2026 eCFR); CMS Program Integrity Manual ch. 5, sec. 5.2.2; Federal Register, Aug. 10, 2022; 42 CFR 414.234; 42 CFR 414.229. Wording is paraphrased.
Many orders reach a supplier from other specialties, such as orthopedics or pulmonology, so your referral sources shape your documentation risk. Our specialty billing pages show how we think about each one. Our Medicare DMEPOS competitive bidding guide covers that separate program. For the daily controls that keep claims clean, see DME billing best practices.
Prior authorization is narrower than the old post implied. Only items on the Required Prior Authorization List need it. CMS has added groups over time, including certain lower limb and lumbar-sacral orthoses, pressure reducing support surfaces, power mobility devices, lower limb prosthetics and pneumatic compression devices. Since January 1, 2025, a standard request gets a decision within 7 calendar days and an expedited request within 2 business days, according to CMS. The list changes, so a partner must check the current version each time.
In-house, outsourced or hybrid: how do they compare?
There is no single winner. In-house fits a steady operation with an experienced biller. Full outsourcing fits a supplier with no billing staff. A hybrid, where you keep intake, orders and delivery records and a partner runs claims and A/R, fits many suppliers because most DME failures start before the claim.
| Model | Fits when | Main advantages | Main risks |
|---|---|---|---|
| In-house | Steady volume and a biller who knows your DME MAC and item categories | Direct control; staff know your referral sources and patients | Depends on one or two people; rule changes are on you; weak cover for absence |
| Fully outsourced | No billing staff, or volume has outgrown the team | Dedicated capacity and wider DME exposure; coverage for absence | Less day-to-day visibility; claims are only as good as the records sent over; transition and exit terms matter |
| Hybrid: partner bills, you keep intake | Billing is the bottleneck but your orders and delivery records are solid | You control orders and proof of delivery; partner handles claims, rentals and follow-up | Needs clear handoff rules and a shared view of each claim |
| Hybrid: partner on denials and A/R only | Current billing works but a backlog of unpaid claims has built up | Narrow scope, quick to test | Does not fix root causes upstream |
What outsourcing can genuinely give you
- Coverage when a biller leaves or is out, so claims do not stall.
- Broader exposure to DME item categories and payer rules than one person usually has.
- Capacity to scale up without hiring and training.
- More of your own time for referral sources, delivery and patients.
What it can take away
- Visibility. You need a regular report by claim stage and denial reason, or you will not know what is stuck.
- Control. Someone outside your building now decides how to work a denial.
- Data exposure. Patient information moves to a vendor, so a business associate agreement is required.
- Time to switch. Open rentals, pending authorizations and unpaid claims must be handed over cleanly.
- Incentives. How the partner is paid can pull against your interests.
Want to see where your DME claims stall first?
Our free practice audit reviews a sample of your claims, denials and A/R aging, so you decide with your own numbers.
What risks does outsourcing add for a DME supplier?
The biggest risk is assuming the liability moves with the work. It does not. OIG’s 1998 compliance guidance for third-party billing companies warned that a billing company’s weak compliance program may expose its provider clients to liability, and it recommends that both sides divide compliance duties and write them into the contract.
You remain the Medicare supplier
Your supplier number, accreditation and surety bond stay yours. Medicare’s supplier standards say a supplier must not convey or reassign a supplier number (42 CFR 424.57(c)(18)), and it must keep proof of delivery. A billing partner works for you; it does not replace you.
Where the money goes
Medicare’s billing-agent exception, in 42 CFR 424.80(b)(5) and 424.73(b)(3), allows payment to an agent only under conditions. Among them: the agent’s pay must not be related in any way to the dollar amounts billed or collected, it must not depend on actual collection, and payment is made in the supplier’s name. This is a legal point, so ask your attorney how any fee model fits. The simple protection is to keep payer deposits going into your own bank account.
OIG’s same guidance flagged percentage-based arrangements as a possible anti-kickback concern and a factor that can increase upcoding. Ask any partner to explain how it is paid and why that does not reward aggressive coding.
Rentals and handoffs
Capped rental items are paid monthly for up to 13 continuous months, and the supplier must transfer title after the 13th month under 42 CFR 414.229. A switch mid-rental is where months get lost or double-counted. Ask for a per-patient rental schedule on day one.
Privacy and records
A billing partner handling patient data is a business associate. HHS says the written contract must set permitted uses, require safeguards, require reporting of improper uses and breaches, require subcontractors to agree to the same limits, and let you end the contract for a violation (see HHS guidance). You also need access to your own claim files. Medicare expects the supplier to keep the written order and supporting documentation and produce it on request (Program Integrity Manual, ch. 5). When you compare providers, including our own medical billing services, ask for the BAA before any patient data moves.
What should you ask a DME billing partner?
Start with the general vendor checklist in our ten questions to ask a medical billing company, then add these six that only matter in DME. Ask for each answer in writing.
| Question | A good answer includes | Why it matters |
|---|---|---|
| Which item categories and DME MAC regions do you bill now? | Names your top items and shows how they handle them | Documentation lists and payer rules differ by item |
| How do you check an order before billing? | Checks the six standard written order elements and returns gaps to you with a reason | Missing or incomplete orders cause documentation denials |
| Who owns prior authorization for listed items? | A named person, a check against the current CMS list, and saved decision records | A listed item without a provisional affirmation is denied |
| How do you track rentals? | A per-patient month count to 13, a flag for title transfer, and a plan for supplier changes | Rental months drive payment and ownership |
| Where is proof of delivery stored? | Kept in your files, copy shared, and missing proof flagged before the claim goes out | The supplier must maintain it |
| Whose account gets payer payments, and what does the BAA say? | Your account, plus a BAA with safeguards, breach reporting and subcontractor limits | Billing-agent rule and HIPAA |
Source: CMS Program Integrity Manual ch. 5; 42 CFR 414.234; 42 CFR 414.229; 42 CFR 424.57; 42 CFR 424.73; HHS OCR (business associate contracts).
Whoever bills, both sides need one shared view of each claim: its stage, its owner and what is blocking it. A practice management system that tracks claims by stage can do that, with data-completeness checks before submission and flags for payments below expected amounts. Denials should then be worked by cause, which is how a dedicated denial management service is meant to operate.
How do you test the decision before you sign?
Run a small, time-boxed pilot on real claims. Agree what you will measure before it starts, and what happens to your data and open claims if you leave. Do not accept a promised result as proof; ask to see how the partner works your claims.
- Denials by reason, not just a total.
- Days in A/R and the oldest unpaid claims.
- Claims held for missing orders or delivery proof, and how long they waited.
- Rental schedule accuracy: does the partner’s month count match yours?
- Prior authorization requests and their outcomes.
“If a vendor cannot show me how a claim moves from order to payment, I would not hand over my files, however good the pitch.”
— Awais Afzal, Healthcare Operations & Data Analyst
Curious what stalled A/R could be costing you?
Use our revenue calculator to put a rough figure on open claims before you compare models.
Our recommendations
- Fix intake before you outsource. We would check that every order is complete, signed and dated before it reaches billing. A vendor cannot repair a missing order after delivery.
- Keep orders and proof of delivery in your own files. Share copies with the partner, but the supplier must maintain them. Ask for read access to everything they hold about your claims.
- Keep payer payments in your own account. Use your bank account and your supplier number, and have counsel review any fee model against the billing-agent rule.
- Start narrow and write the exit. Pilot on a defined set of items or payers. Agree in writing how you get your data and open claims back.
- Hand over rentals with a schedule. Give the partner a per-patient rental month count at the start, and reconcile it every month.
- Review by denial reason every month. Totals hide problems. Ask for denials by reason and by item category, and decide who fixes each cause.
A practice management system built around claims, not charts.
RCM Finder's portal tracks each claim by stage with an owner, checks claim data for completeness before submission and flags payments below expected amounts. It is a claims system, not an EHR.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
For most DME suppliers the sound choice is a hybrid: keep intake, orders and delivery records close, and give claims, rental tracking and A/R follow-up to a partner who can show the work. If you want a second view before choosing, our end-to-end revenue cycle management is one option to compare, and the contact page is the quickest way to ask us a question. Start with a free practice audit so you compare vendors against your own numbers.
Frequently asked questions
How much does outsourcing DME billing cost?
Fees vary by scope, volume and model, and we do not publish prices. We quote after a free practice audit. When comparing quotes, ask exactly what is included, how the fee is calculated, and have your attorney check the fee structure against Medicare’s billing-agent rule.
Can a billing company use my Medicare supplier number?
A billing partner can submit claims on your behalf, but the number stays yours. Medicare’s supplier standards say a supplier must not convey or reassign a supplier number. Under the billing-agent rule, payment to an agent is made in the supplier’s name.
Is DME billing harder than regular medical billing?
It is different. Claims rest on a written order, proof of delivery, prior authorization for listed items and, for rentals, a monthly payment cycle. A practice with strong visit documentation can still struggle if its delivery and order files are loose.
What happens to open rentals if I switch billers?
They need a clean handoff. Give the new partner a per-patient schedule showing months already billed, and check it against the old biller’s records. Capped rental items are paid for up to 13 continuous months, so a miscount affects both payment and title transfer.
Does every DME item need prior authorization?
No. Medicare requires it only for items on CMS’s Required Prior Authorization List, which CMS updates. A claim for a listed item without a provisional affirmation is denied. Your billing partner should check the current list each time rather than rely on memory.
Will outsourcing reduce my denials?
Not by itself, and no honest vendor can promise a number. CMS data shows missing or thin documentation drives most DMEPOS improper payments. Outsourcing helps when it adds capacity and DME knowledge on top of dependable orders and delivery records.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Medicare Fee-for-Service Supplemental Improper Payment Data (Nov. 2025) — CMS (2025)
- Prior Authorization Process for Certain DMEPOS Items — CMS (2026)
- 42 CFR 424.57 DMEPOS supplier standards — eCFR (2026)
- 42 CFR 414.229 Capped rental items — eCFR (2026)
- 42 CFR 414.234 Prior authorization of DMEPOS items — Cornell LII (eCFR text) (2026)
- 42 CFR 424.73 Prohibition of assignment of claims by providers — Cornell LII (eCFR text) (2026)
- 42 CFR 424.80 Prohibition of reassignment of claims by suppliers — Cornell LII (eCFR text) (2026)
- Medicare Program Integrity Manual, Chapter 5 — CMS (n/d)
- Federal Register notice CMS-6087-N (Aug. 10, 2022) — Federal Register (2022)
- OIG Compliance Program Guidance for Third-Party Medical Billing Companies — HHS OIG / Federal Register (1998)
- Business Associate Contracts — HHS OCR (n/d)
Disclaimer: This article is general educational information for DME suppliers and practices. It is not legal, compliance, coding or billing advice. Medicare rules, CMS lists and payer policies change and vary by item and contractor. Confirm requirements with qualified counsel, your DME MAC and your payers before acting.
