
Legacy accounts receivable is money owed to your practice that has sat unpaid long past normal follow-up, or that came over from an old billing system or company. No regulation defines the term, so set your own cutoff in writing. Recover it by re-aging every balance from the date of service, checking filing and appeal deadlines, then working the balances you can still win first.
If your aging report has a long tail of balances older than 120 days, you are not alone, and you do not need a new strategy for every payer. You need a count, a cutoff, a deadline check and an owner for each balance.
This guide is for practice owners and billing managers. It covers what the term means, what the Medicare rules say about old claims, how to sort a backlog and when to stop chasing a balance. For A/R basics, start with our accounts receivable guide.
Key takeaways
- No regulation defines legacy A/R: set a written cutoff and use it for every payer.
- Re-age by date of service, then check filing, appeal and reopening limits before anyone calls.
- Sort balances into buckets with one next action and one owner each.
- Credit balances found during cleanup may be overpayments you must return.
- Write off under a written policy, and fix the cause so the balance does not return.
What does legacy accounts receivable mean?
Legacy A/R is a working label, not a regulatory term. Billing teams use it for two different piles of money, and the right plan depends on which pile you have. Write down which one you mean before you assign anyone to it.
| Type | Where it comes from | What it usually looks like | First check |
|---|---|---|---|
| Aged balances | Claims and statements that missed normal follow-up | Old unpaid claims, stalled appeals, small patient balances nobody owns | Is the claim still inside a filing, appeal or reopening window? |
| Inherited balances | A prior billing company, an old practice management system or an acquired practice | Open items with thin notes, missing remits, unclear payer status | Can you match each open item to a claim, a remit and a contract? |
| Credit and overpaid balances | Duplicate payments, payer takebacks, posting errors | Negative balances hidden inside aging buckets | Does any balance need to be refunded rather than collected? |
| Patient-responsibility tail | Copays, deductibles and coinsurance left after insurance paid | Many small balances across many accounts | Was the patient billed correctly and told the amount in time? |
Source: RCM Finder working definitions, not a regulatory classification.
A sensible cutoff is a business decision. Many teams treat anything past 120 days from the date of service as the point where a balance leaves the daily work queue and enters a recovery project. Pick your own number, apply it to every payer, and review it twice a year. Our guide to accounts receivable in medical billing explains how aging buckets and days in A/R are calculated.
Why does legacy A/R build up?
Legacy A/R builds up when no one owns a balance after the first follow-up fails. Each cause below is a process gap, and each one can be closed.
- Claims sit in a status nobody checks. A claim that is neither paid nor denied can age quietly for months.
- Denials are worked once, then dropped. A first appeal is sent, no one diarizes the response date, and the file goes cold. See our medical billing denial management guide for a working routine.
- Staff turnover or a system change. Notes and queues do not always move with the data. A migration can leave open items without owners.
- Patient balances are billed late or unclearly. Statements that are hard to read, or sent weeks after the visit, get paid less often.
- No written write-off rule. Without one, balances are either kept forever or cleared inconsistently.
Most legacy A/R is the sum of small, repeatable gaps, so a cleanup that skips the root causes refills.
Which deadlines decide whether an old balance is still collectible?
Deadlines decide whether a balance is a collection task or a write-off decision. Check them before you spend staff time. The Medicare rules below are federal and public. Commercial and Medicare Advantage rules sit in each contract, provider manual or plan notice, so pull those separately.
| Rule | What it says | Why it matters for old balances |
|---|---|---|
| Timely filing, 42 CFR 424.44 | A Medicare claim generally must be filed within one calendar year after the date of service, with limited exceptions such as contractor error or retroactive entitlement | A claim you never billed, or billed incorrectly and need to refile, may be past the limit |
| Redetermination (first appeal), 42 CFR 405.942 | File within 120 calendar days of receiving the initial determination notice; receipt is presumed 5 calendar days after the notice date; late filing needs good cause | A denial older than that is no longer an easy appeal |
| Reopening, 42 CFR 405.980 | A party can ask to reopen an initial determination within 1 year for any reason, or within 4 years for good cause | A reopening request can recover an older payment error where an appeal can’t |
| Overpayment return, 42 CFR 401.305 | Report and return a Medicare overpayment within 60 days of identifying it, for overpayments received within the prior 6 years | Cleanup often turns up credits and duplicate payments you must return, not collect |
Source: eCFR, 42 CFR 424.44, 405.942, 405.980 and 401.305 (current text, fetched October 2026).
The timely filing rule lists the exceptions and the extension periods that go with each. Treat them as narrow. If you plan to rely on one, keep the correspondence that proves it. The redetermination rule and the reopening rule are separate tools: the first is for appealing a decision on time, the second for asking a contractor to correct one after that window.
Do not assume commercial limits match Medicare
Commercial payers set their own filing and appeal windows by contract, and they differ by payer and by plan. Build a one-page table of the limits from your actual contracts and keep it where the A/R team works. If you cannot find a limit, ask the payer in writing.
How do you triage a legacy A/R backlog?
Triage means sorting every balance into a bucket with one next action, so the team stops re-reading the same files. Do this before anyone makes a call.
| Bucket | What to look for | Next action | Stop and check |
|---|---|---|---|
| Billable now | Charges never billed, or rejected before payer acceptance | Correct and submit, with proof of original submission if you have it | Is the filing limit still open? |
| Appealable | Denied claims with a live appeal or reopening window | Appeal with the missing document or correct code | Is the denial reason one you can fix with facts? |
| Follow-up | Claims accepted, no payment or denial | Call or check the payer portal, record the reference number and next date | Does the payer show a different status than your system? |
| Patient balance | Verified patient responsibility after insurance | Statement, reminder, payment plan offer | Was the amount calculated from the processed remit? |
| Refund or credit | Negative balances, duplicate payments | Review, then refund or reallocate | Does the overpayment rule or a payer contract set a deadline? |
| Write-off candidate | Past all limits, no appeal route, or cost to pursue exceeds likely recovery | Approve under your written write-off policy | Who signs off, and is the reason coded? |
Source: RCM Finder recommended workflow; it is an operating method, not a regulatory requirement.
Work the buckets in this order: billable now, appealable, then follow-up. They are the balances most likely to turn into payments, and they are the ones with deadlines. Our A/R recovery tips for small practices cover the day-to-day habits that keep those buckets from refilling.
“The first week of a cleanup is spent reading, not calling. The practices that skip that step make the same calls twice.”
What is a step-by-step recovery workflow?
A recovery workflow is a short, repeatable sequence that every balance goes through once. Keep it the same for every payer so it can be audited.
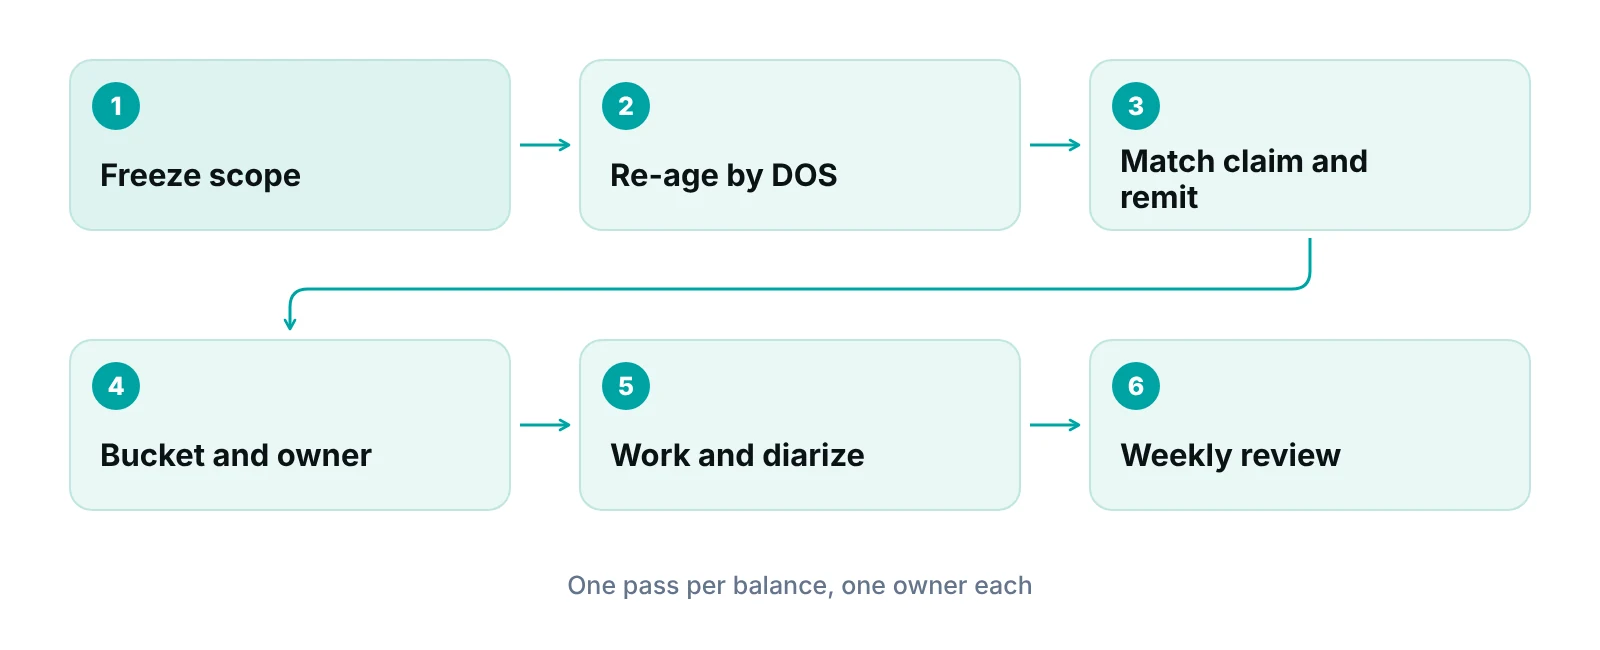
- Freeze the scope. Pick a cutoff date and export every open item as of that day. New work stays in the normal queue so the project does not move under you.
- Re-age from the date of service. Many systems age from the billing date or the last action date. Re-age from the date of service so filing limits are measured correctly.
- Match each item to a claim and a remit. Look for the claim, the payer response and the remittance. Items you cannot match go to a research list, not the call list.
- Assign a bucket and an owner. Use the triage buckets above. Every balance needs a named person and a next-action date.
- Work, document, diarize. Record the payer, the reference number, what was promised and when to check again. A note without a date is not follow-up.
- Review weekly and close the loop. Report what moved between buckets. Write off under policy, refund credits and send the root causes to whoever can fix them.
If the backlog is large, a system that shows claims by stage with an owner makes this easier to run. A practice management system that tracks claims by stage can hold the bucket, the owner and the next-action date in one place instead of a spreadsheet. Whatever you use, the rule is the same: no balance without an owner and a date.
What if the A/R came from an old system or billing company?
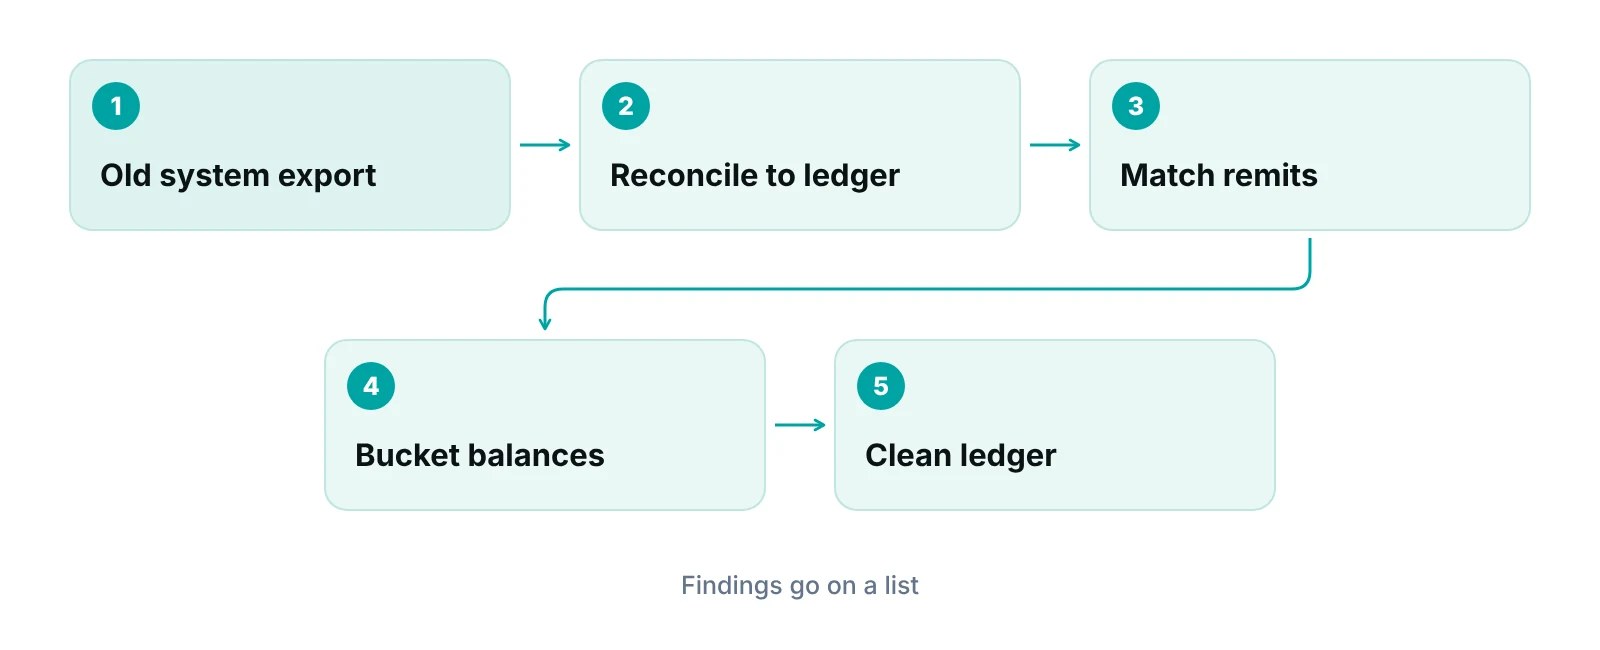
Inherited A/R needs a reconciliation first, because you cannot recover what you cannot match. Treat the handoff as an audit, not a data import.
- Ask the prior company or vendor for a full A/R export, payment posting history and open denial list, in a format you can read.
- Reconcile the export total to the ledger and bank deposits for the same period. Differences are findings, not noise.
- Check that payer remits and claim submission proof moved over. Without them an appeal is much harder.
Plan for how the data will be protected during the move. Any outside party that handles patient information for you should sign a Business Associate Agreement before it sees a record, and you should share only what the work requires. Our HIPAA compliance checklist is a useful starting point for that review.
How should you handle old patient balances?
Old patient balances recover best when the amount is confirmed, the statement is clear and a payment option is offered early. Collection effort does not make up for a wrong balance.
- Confirm the amount first. Recalculate from the processed remittance. A patient balance built on a wrong estimate is the one most likely to be disputed.
- Send a clear statement. Say what the visit was, what insurance paid and what is owed now, and give a phone number that gets answered.
- Offer a payment plan. Smaller scheduled payments often work better than a single large demand. See our guide to patient payment plans for policy options.
- Keep contact respectful and documented. Log each statement, call and result.
If an outside agency or in-house team makes collection calls, find out whether federal debt collection rules apply to them. The CFPB’s Regulation F, for example, sets a presumption on call frequency for debt collectors: more than seven calls to a person about a particular debt within seven consecutive days, or a call within seven days after a telephone conversation about that debt, creates a presumption of a violation (see 12 CFR 1006.14). Whether a particular practice or agency counts as a debt collector is a legal question, so ask your attorney. State laws can add more limits.
For a longer treatment, see our post on improving patient collections.
When should you write off old A/R?
Write off a balance when it is past every deadline you can use, has no valid route to payment, or costs more to pursue than it can return, and only under a written policy. The goal is an honest ledger, not a good-looking aging report.
- Write the policy down: who can approve, what dollar limits apply and which reason codes are allowed.
- Separate contractual adjustments, bad debt and administrative write-offs in your reports. They answer different questions.
- Do not write off a balance that is a billing or coding error you can still correct.
- Ask your accountant how write-offs flow into your books and taxes, and your attorney before any blanket waiver of patient responsibility.
If the same payer or denial reason keeps showing up in write-offs, the fix is upstream. Our essential A/R metrics post shows which reports to watch.
Should you recover legacy A/R in-house, with software or with a partner?
The right choice depends on volume, staff time and whether the data needs a reconciliation first. A small backlog with clean data suits an in-house sprint. A large or messy one often needs dedicated hours.
- In-house sprint. Best for a small backlog and a stable team. The risk is that daily work pushes the project aside.
- Software plus your staff. Best when the main gap is visibility: stage, owner, next date. It does not replace payer calls and appeals.
- Outside A/R partner. Best for large backlogs or inherited data. Ask who works the claims, how notes are shared with you and how the work is reported. Our accounts receivable management services are one option, and a free practice audit shows what your backlog looks like before you commit.
See what is in your aging report
Send us your A/R aging summary and we will tell you which balances look recoverable, which look stuck and what to fix first. Pricing is quoted after the audit.
Whichever route you choose, ask any outside party for a Business Associate Agreement before sharing patient data, role-based access, an audit trail of who touched which account, and a clear statement of who is allowed to contact patients. Specialties bill and appeal differently, so ask how they handle yours; our specialty billing pages show how we group them.
Estimate what slow collections cost
Use the revenue calculator with your own numbers to see the cash effect of aged balances.
Our recommendations
- Define legacy A/R in writing. Pick the cutoff, the meaning (aged, inherited or both) and the owner of the project. Without it, people argue about numbers instead of working them.
- Re-age from the date of service. This is the date that filing limits are measured from. Aging from billing or last-touch dates hides risk.
- Check deadlines before you call. We would rather lose a day reading contracts than lose a week on balances that are already out of time.
- Fix one root cause per month. Each cleanup should end with a prevention task: a denial reason removed, a status check automated or a statement redesigned.
- Review credit balances early. Cleanup surfaces negative balances. Decide who reviews them and how refunds are approved before you find the first one.
- Report weekly. Show how many balances moved buckets, what was written off and why.
Track every legacy balance by stage with an owner.
RCM Finder's portal tracks claims through each stage with an assigned owner, applies workflow rules to flag or hold items for review, and shows reporting dashboards, so a cleanup list does not live in a spreadsheet.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Legacy A/R is a process problem with a calendar attached. Count it, check the deadlines, sort it, work the winnable balances and write off the rest under a written policy. If appeals are the bottleneck, our denial management services and A/R follow-up work from the same bucket-and-owner method, and the free audit is the place to start.
Frequently asked questions
What is legacy accounts receivable?
Legacy accounts receivable is money owed to a practice that has stayed unpaid well past normal follow-up, or that was inherited from a former billing system or company. No law or standard defines the term, so practices set their own cutoff. Many treat balances past 120 days from the date of service as legacy, but that number is a choice.
How old is too old to collect?
It depends on the payer. For Medicare, a claim generally must be filed within one calendar year after the date of service, and first appeals are due within 120 days of the notice. Commercial limits come from your contract. Check the limit for each payer before you invest time in the balance.
Can you still appeal an old denial?
Sometimes. A Medicare redetermination is due within 120 calendar days of receiving the notice, with a possible extension for good cause. A reopening request can be made within 1 year for any reason, or within 4 years for good cause. Commercial appeal windows are contract-specific.
What do you do with credit balances found during cleanup?
Review them before treating them as income. Some are duplicate payments or payer overpayments that must be returned. Under Medicare’s rule, an identified overpayment is generally due back within 60 days, with a six-year lookback. Check other payers’ contracts and your state’s rules for their refund deadlines.
Should we hire an outside company for old A/R?
It helps when the backlog is large, the data is messy or your staff cannot spare the time. Ask who will work your claims, how you will see their notes and how patient data is protected, including a Business Associate Agreement. Keep ownership of payer relationships and write-off decisions.
How do we stop legacy A/R from coming back?
Give every claim a stage, an owner and a next-action date. Work denials to a deadline, send clear patient statements promptly and review aging weekly. Track the cause of each write-off so the process changes, not only the balance.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- 42 CFR 424.44 – Time limits for filing claims — eCFR (2026)
- 42 CFR 405.942 – Time for filing a request for a redetermination — eCFR (2026)
- 42 CFR 405.980 – Reopening and revision of initial determinations and decisions — eCFR (2026)
- 42 CFR 401.305 – Requirements for reporting and returning of overpayments — eCFR (2026)
- 12 CFR 1006.14 – Harassing, oppressive, or abusive conduct — eCFR (CFPB Regulation F) (2026)
Disclaimer: This post is general educational information about revenue cycle operations. It is not legal, accounting, coding or compliance advice. Deadlines vary by payer, contract and state, and regulations change. Confirm requirements with each payer and your qualified advisors before acting.
