
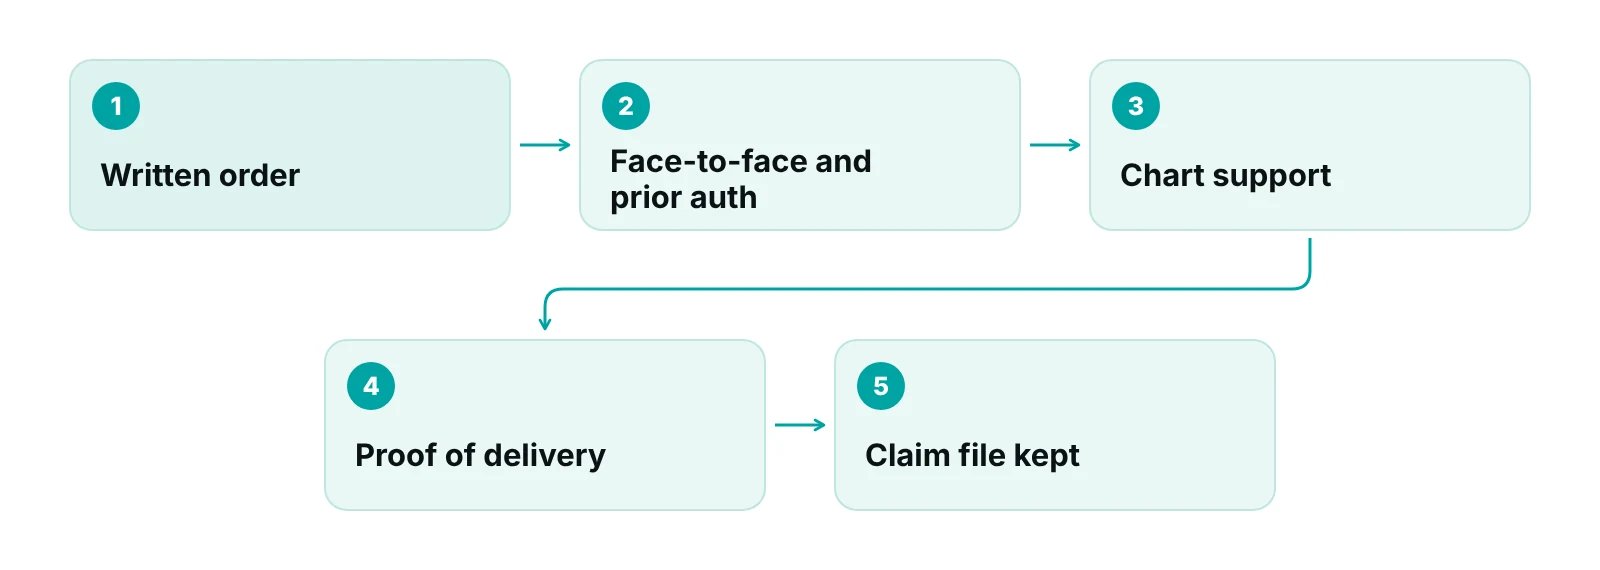
<strong>DME billing compliance</strong> means every Medicare DME claim is backed by records proving the item was ordered, medically necessary, delivered and billed by an enrolled supplier. The core records are a standard written order, chart support, proof of delivery and, for listed items, a face-to-face visit and prior authorization.
This guide replaces generic billing tips with the specific documents Medicare reviewers ask for. It is written for DME suppliers, billing managers and practices that order equipment. For the coding side, see our DME coding with HCPCS codes, modifiers and ICD-10 and DME billing modifiers guide.
Key takeaways
- Most DMEPOS improper payment dollars in FY 2025 traced to no or insufficient documentation, not to coding errors.
- A standard written order has six required elements and must be in place before the claim, or before delivery for listed items.
- The medical record, not the order or a supplier statement, proves medical necessity.
- Proof of delivery depends on the delivery method, and records must be kept for seven years from the date of service.
- CMNs are no longer submitted for dates of service on or after January 1, 2023, but supplier standards and enrollment rules still apply.
What DME billing compliance means in practice
DME billing compliance means that every Medicare claim line you submit is backed by records that prove the item was ordered, medically necessary, delivered and billed by a supplier that meets enrollment rules. Medicare pays on the paper trail. If a reviewer cannot find the order, the delivery proof or the clinical support, the payment is treated as improper, even when the patient really got the equipment.
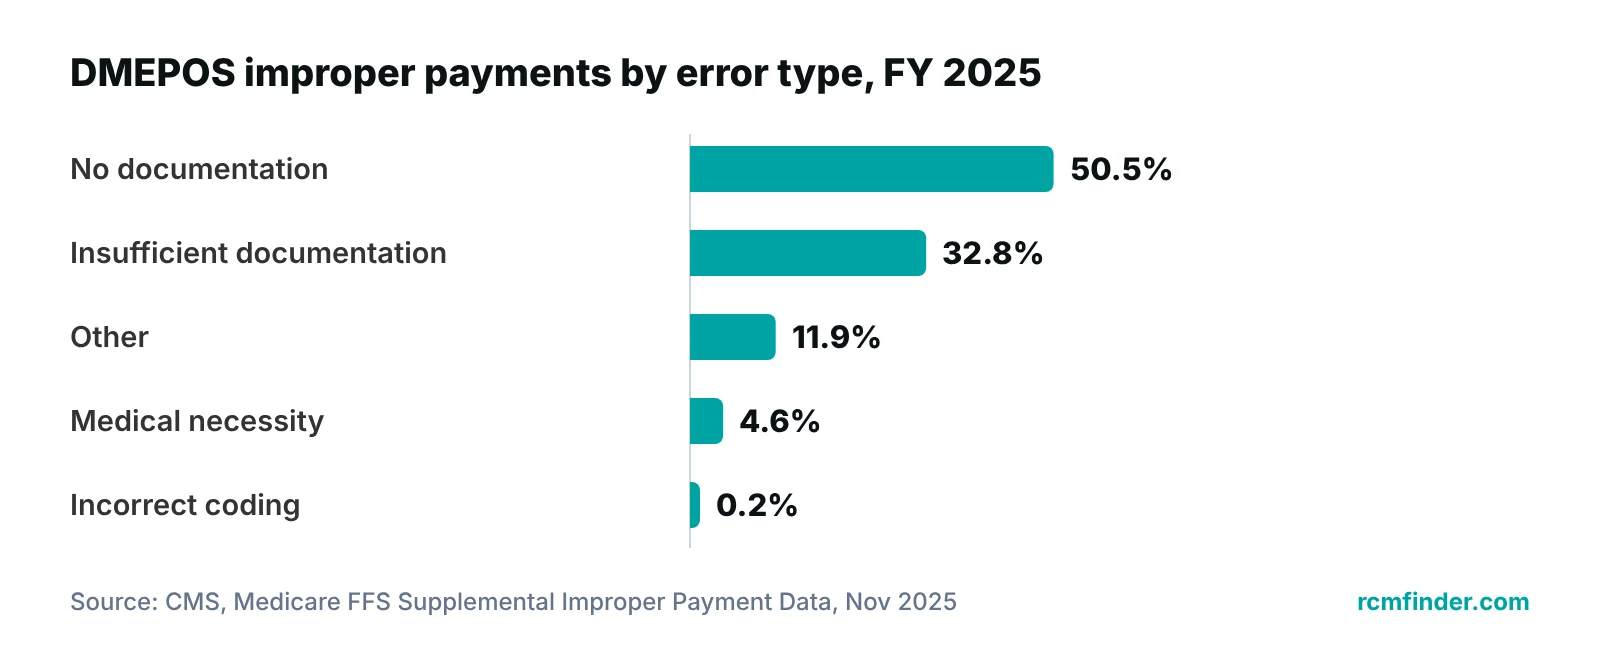
The scale of the problem is visible in federal data. In its FY 2025 report, CMS put the Medicare fee-for-service improper payment rate for DMEPOS at 24.1%, about $2.3 billion of $9.4 billion in DMEPOS payments. The sample covered claims submitted between July 1, 2023 and June 30, 2024 (CMS supplemental improper payment data, November 2025). It is a payment-accuracy measure, not a count of fraud.
What matters for a supplier is the reason. Of the DMEPOS improper dollars, 50.5% were classed as no documentation and 32.8% as insufficient documentation. Incorrect coding was 0.2%. Most of the money at risk is lost to missing or thin records, not to a wrong code.
Medicare rules first, then your payer
This guide follows Medicare fee-for-service and DME MAC guidance. Medicaid plans, Medicare Advantage plans and commercial payers can ask for different documents or timing. Check each payer’s DME policy before you copy a Medicare pattern.
The standard written order: what it must contain
Every Medicare DMEPOS claim needs a written order from the treating practitioner as a condition of payment. CMS calls the order a standard written order (SWO), and the required elements are set out in the CMS Program Integrity Manual, Chapter 5, which points to 42 CFR 410.38(d)(1).
- Beneficiary name or Medicare Beneficiary Identifier (MBI)
- A general description of the item
- Quantity to be dispensed, if applicable
- Order date
- Treating practitioner name or National Provider Identifier (NPI)
- Treating practitioner signature
Elements such as length of need or frequency of use are not required for payment, but they can help support medical necessity (MLN Matters MM11599). Stamped signatures are generally not accepted, with a narrow exception for practitioners with a documented physical disability (CGS supplier manual, Chapter 3).
Timing, new orders and refills
For most items, the SWO must reach the supplier before you submit the claim. For items on CMS’s Required Face-to-Face Encounter and Written Order Prior to Delivery list, it must reach you before delivery, and the order date must be on or before the delivery date (or the ship date, when shipping sets the date of service).
You need a new order for a purchase or initial rental, when the order changes (a different quantity, for example), when an item is replaced, and when you take over a patient and cannot get a valid order from the previous supplier. A routine renewal is required only when the medical policy for that item says so.
Refills have their own rule. Contact the beneficiary before each refill, do not ship automatically on a set schedule, and deliver no sooner than 10 calendar days before the current supply ends (Program Integrity Manual, sections 5.2.5 and 5.2.6).
“An order is a starting point, not a defence. If the chart does not back it up, the signature will not save the claim.”
— Awais Afzal, Healthcare Operations & Data Analyst
Face-to-face visits, written orders before delivery and prior authorization
Some items need more than an SWO. Items on CMS’s Required Face-to-Face Encounter and Written Order Prior to Delivery (F2F/WOPD) list require a face-to-face encounter between the treating practitioner and the patient within the 6 months before the written order, plus an order communicated to the supplier before delivery. Power mobility devices are on the list by statute. A January 2023 CMS rule added 10 orthosis codes to it, effective April 17, 2023 (Federal Register, January 17, 2023).
The encounter can be in person or by telehealth when the telehealth rules are met, and the record must show subjective and objective information about the condition the item treats (MM11599). For specified items the order has to be completed within 6 months after the encounter (Noridian F2F and written order letter). Because the list changes, pull the current version from CMS or your DME MAC.
Required prior authorization
CMS also runs a prior authorization program for selected DMEPOS items. As CMS described it in its 2015 fact sheet, the Required Prior Authorization List is a subset of a larger Master List, and a claim submitted with a non-affirmation or with no decision is denied (CMS fact sheet, December 29, 2015). Which items are on the list changes over time, so check CMS’s current list before you deliver. Our prior authorization guide covers how prior authorization works across payers.
Certificates of medical necessity are no longer submitted
Older guides, including earlier versions of this post, tell suppliers to collect a certificate of medical necessity (CMN). For dates of service on or after January 1, 2023, CMS no longer requires CMNs or device information forms (DIFs) to be submitted with claims (Program Integrity Manual, section 5.5; CGS Chapter 3). For earlier dates of service, such as an audit that reaches back, the forms still matter.
Medical necessity lives in the patient's chart, not in your file
Medicare decides medical necessity from the patient’s medical record. The record must support the type, quantity and frequency of what was ordered. According to the Program Integrity Manual (section 5.9), an order, a CMN, a supplier statement or a physician attestation alone is not enough.
Noridian’s DME MAC guidance adds two limits. Supplier-produced records are not treated as part of the medical record, even when the prescriber signed them, and records from a party with a financial interest in the claim are not enough on their own (Noridian article A55426, archived 2017 version). Because that version is archived, confirm the wording in the active article.
If the record does not support the item, the supplier is liable for the amount unless a properly executed Advance Beneficiary Notice (ABN) is on file (Noridian supplier documentation page). So ask referral sources for visit notes, test results and functional findings, not only a signature.
The need is clearest where coverage turns on clinical findings, for example oxygen and positive airway pressure (PAP) devices ordered by pulmonology practices. Read the Local Coverage Determination and Policy Article for each item you bill. They list the findings the chart must show, and we do not summarize them here because they differ by item.
Your coding must tell the same story as the chart. Our DME coding with HCPCS codes, modifiers and ICD-10 article covers matching HCPCS codes and diagnoses, and our DME billing modifiers guide covers the KX modifier, which says the item’s policy requirements are met. Treat KX as a statement you must be able to prove.
Proof of delivery: the record auditors ask for first
Proof of delivery (POD) is the supplier’s record that the patient actually received the item. Under supplier standard 42 CFR 424.57(c)(12), the supplier is responsible for delivery and must keep proof of it (eCFR). Where POD is a condition of payment, missing POD leads to denial and recoupment.
| Delivery method | What the record must show | Date of service |
|---|---|---|
| Direct delivery | Beneficiary name, delivery address, item description, quantity, delivery date, and a signature from the beneficiary or designee | Date the beneficiary received the item |
| Shipped or delivery service | A tracking record that links your invoice to the carrier’s record, with beneficiary name, address, item description, quantity, delivery date and evidence of delivery | Ship date |
| Nursing facility | Proof of delivery to the facility, plus the facility’s record that the beneficiary received or used the item, in quantities that justify what you billed | Per DME MAC guidance |
Source: Noridian Healthcare Solutions, article A55426 (archived 2017 version) and CGS Administrators, DMEPOS Supplier Manual Chapter 3 (current edition); confirm against the active DME MAC article.
A designee may sign for the beneficiary, and the relationship should be noted. Suppliers, their employees and anyone with a financial interest in the delivery may not sign as designee (CGS Chapter 3). Keep POD with the claim file for seven years from the date of service. For rentals, standard documentation, including POD, applies at the initial rental date of service.
Supplier standards: compliance starts at enrollment
Even perfect claim files do not help if the business itself falls out of compliance. Medicare DMEPOS suppliers must meet 30 supplier standards listed in 42 CFR 424.57(c) and certify on their enrollment application that they continue to meet them (eCFR 424.57).
| Standard | What it requires | Reference |
|---|---|---|
| Accreditation | Each location must be accredited for the products and services it supplies, and re-accredited at least every 12 months. | 42 CFR 424.57 (c)(22), (c)(24) |
| Surety bond | A $50,000 base bond, with higher amounts for certain adverse legal actions. A lapse leads to revocation, and Medicare does not pay for items furnished during the gap. | 42 CFR 424.57 (d) |
| Insurance | At least $300,000 in comprehensive liability coverage. | 42 CFR 424.57 (c)(10) |
| Location and hours | An accessible, staffed practice location of at least 200 square feet, open at least 30 hours a week, with exceptions for certain physicians, therapists and custom orthotic and prosthetic suppliers. | 42 CFR 424.57 (c)(7), (c)(30) |
| Complaints | A written complaint protocol, with each complaint recorded and its follow-up documented. | 42 CFR 424.57 (c)(19), (c)(20) |
| Calls to patients | No unsolicited calls about covered items unless the patient gave written permission, the call coordinates delivery of an item already furnished, or you supplied a covered item within the prior 15 months. | 42 CFR 424.57 (c)(11) |
| Rent-or-buy notice and standards disclosure | Tell beneficiaries their options and give each one a copy of the supplier standards. | 42 CFR 424.57 (c)(5), (c)(16) |
Source: eCFR, 42 CFR 424.57 (supplier standards). Check the current regulation; this table covers selected standards, not all 30.
Report changes to your enrollment application to CMS within 30 days ((c)(2)). If competitive bidding affects the products you supply, see our Medicare DMEPOS competitive bidding guide.
What auditors check and how long you must keep records
Your claims can be reviewed by DME MACs, the CERT contractor, the Supplemental Medical Review Contractor (SMRC), Recovery Audit Contractors (RACs) and Unified Program Integrity Contractors (UPICs). You must give them enough information to show that the coverage criteria were met, and keep a description of the item delivered, which can be a narrative, a HCPCS code, a long descriptor, or a brand and model number (Noridian). Keep all supplier documentation for seven years from the date of service.
The April 2026 OIG audit of Medicare PAP device payments shows how reviews play out. OIG reviewed 110 sampled claims and found that 97 complied and 13 did not, because the documentation needed to support the billed services was missing. Some suppliers did not respond to OIG’s requests at all. OIG estimated that Medicare paid about $15.2 million for PAP claims in the audit period that did not meet billing requirements (OIG report A-05-21-00036). OIG’s overall finding was that CMS generally ensured payments complied, so the lesson is not that PAP billing is broken. The failures traced to records.
Build one claim file per delivery and check it before you bill. A records request that finds a missing order is a recoupment risk. A pre-bill check that finds it is a phone call to the referral source.
A pre-bill compliance check for every DME claim
A pre-bill check confirms the documents exist and agree with each other before the claim goes out. Run these six steps on every claim line.
- Confirm the order. All six SWO elements are present, the signature is genuine, and the date is on or before delivery when the item is on the F2F/WOPD list.
- Check the item against the lists. Look up the code on the current F2F/WOPD list and the Required Prior Authorization List, and record the prior authorization decision when one applies.
- Match the chart. The visit notes support the item, quantity and frequency, and the diagnosis code agrees with them.
- Check the proof of delivery. It names the right patient, address, item and quantity, carries a valid signature or tracking record, and gives a date that matches the claim.
- Check codes and modifiers. The HCPCS code, rental or purchase modifier and KX status follow the policy for that item.
- File and retain. Store the full set under one claim reference and keep it for seven years from the date of service.
Many suppliers run this check in spreadsheets, which works until volume grows. With a practice management system that tracks claims by stage, each claim has an owner and data-completeness checks run before submission, so missing fields are caught before the payer sees them. The portal is a claims system, not an EHR, and it does not replace your own record keeping for orders and delivery proof.
Handle it in-house, outsource it or split the work
You can run DME compliance in-house, hand billing to an outside team, or split the work. The right choice depends on who can reliably chase missing orders and delivery proof, because that is where claims fail. Our pros and cons of outsourcing DME billing article gives the longer comparison.
| Question | In-house | Outsourced billing | Hybrid |
|---|---|---|---|
| Who chases missing orders and chart notes? | Your staff, alongside other duties | The billing team, working from what you share | Your intake staff collect; the billing team verifies |
| Who holds proof of delivery? | You | You, unless the contract says otherwise | You, with a shared checklist |
| Who answers a records request? | You | You, with billing support | You, with billing support |
| Main risk | Rules change faster than training | Gaps between your records and their billing | Unclear handoffs |
| Fits best when | Volume is low and a trained coder is on staff | Staff is stretched and backlogs are growing | You want control of delivery but help with claims |
Whichever model you choose, you remain the supplier of record, and the enrollment and documentation duties above stay yours. If you want help with claims and follow-up, our medical billing and claims support works inside your existing systems. Ask any billing partner how it checks orders, delivery proof and chart support before a claim is submitted.
Want your DME claim files checked against this list?
Our free practice audit reviews a sample of your DME claims for missing orders, delivery proof gaps and documentation mismatches, and shows where to fix the process. Pricing for any service is quoted after the audit.
Our recommendations
- Make the written order a gate, not a follow-up. Do not schedule delivery until a complete order is on file. For F2F/WOPD items, also confirm the visit date and order date.
- Ask referral sources for the chart note, not only the signature. Give prescribers a short list of what the LCD requires for each item and ask for the visit note with every order.
- Treat proof of delivery as part of the delivery job. Capture signature, date, address and item details at the door, and link tracking numbers to the invoice the same day.
- Run a quarterly mock audit. Pull a small sample of paid claims and rebuild each file. If you cannot produce the order, chart note and POD quickly, a reviewer will not wait either.
- Keep a dated list of the rules you rely on. Record when you last checked the F2F/WOPD list, the prior authorization list and each LCD. Rules change, and a dated check shows diligence.
- Review your supplier standards every year. Check accreditation dates, surety bond terms, insurance and complaint logs against the current standards in 42 CFR 424.57 before the renewal date, not after.
A practice management system built around claims, not charts.
RCM Finder's portal tracks every claim by stage with an owner and runs data-completeness checks before submission. It is a claims system, not an EHR.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
DME claims are paid on proof. Get a complete order, a chart that backs it up and a delivery record that matches the claim, and keep the supplier standards current. If denials already pile up, our denial management service can work them while you fix the cause, and you can talk to us or start with a free practice audit.
Frequently asked questions
What is a standard written order for DME?
It is the treating practitioner’s order for a DMEPOS item. It must show the beneficiary’s name or MBI, a general item description, the quantity if applicable, the order date, the practitioner’s name or NPI, and the practitioner’s signature. For most items it must reach the supplier before the claim is submitted. For listed items it must reach the supplier before delivery.
Do I still need a certificate of medical necessity?
For dates of service on or after January 1, 2023, CMS no longer requires CMNs or DIFs to be submitted with claims. The medical record must still support medical necessity. For earlier dates of service, such as a look-back audit, the old CMN rules still apply.
What counts as proof of delivery?
For direct delivery, a signed and dated record with the beneficiary’s name, delivery address, item description, quantity and delivery date. For shipments, a tracking record that links your invoice to the carrier’s record. Suppliers and their employees cannot sign as the beneficiary’s designee.
How long must I keep DME records?
DME MAC guidance requires supplier documentation to be kept for seven years from the date of service. Keep the order, delivery proof and any other claim support together. Some states or payers set longer periods, so check your own contracts.
Which DME items need a face-to-face visit or prior authorization?
CMS publishes a Required Face-to-Face Encounter and Written Order Prior to Delivery list, and a separate Required Prior Authorization List. Both change over time, so check the current versions on CMS.gov or your DME MAC’s site before you deliver a covered item.
Does a clean claim mean a compliant claim?
No. A claim can pass payer edits and still lack the order, chart support or delivery proof that a later review requires. Compliance is judged on the supporting records, so check them before you bill, not only the claim data.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Medicare FFS Supplemental Improper Payment Data (Nov 2025) — CMS (2025)
- Program Integrity Manual, Chapter 5 (Items and Services Having Special DME Review Considerations) — CMS (current)
- MLN Matters MM11599: Revising Chapters 3 and 5 of Pub. 100-08 (CMS-1713-F) — CMS (2020)
- Medicare Program; Updates to Face-to-Face Encounter and Written Order Prior to Delivery List — Federal Register / CMS (2023)
- F2F and Written Order Requirements for Certain Types of DME — Noridian Healthcare Solutions (DME MAC) (2018)
- Supplier Documentation – JD DME — Noridian Healthcare Solutions (DME MAC) (2025)
- Standard Documentation Requirements for All Claims Submitted to DME MACs (A55426, archived) — Noridian Healthcare Solutions (DME MAC) (2017)
- DMEPOS Supplier Manual, Chapter 3 Supplier Documentation — CGS Administrators (DME MAC) (2026)
- 42 CFR 424.57 Special payment rules for items furnished by DMEPOS suppliers — eCFR / HHS (current)
- CMS Finalizes Rule Creating Prior Authorization Process for Certain DME (fact sheet) — CMS (2015)
- Medicare Payments for PAP Devices Used for Obstructive Sleep Apnea (A-05-21-00036) — HHS Office of Inspector General (2026)
Disclaimer: This post is general educational information about Medicare DME billing. It is not legal, coding or compliance advice. Requirements vary by DME MAC, payer, item and date of service, and change over time. Confirm them in current CMS, DME MAC and payer sources before you bill.
