
Medical billing services for small practices make sense when claims depend on one or two people and denials or A/R follow-up keep slipping. Decide by scope, who receives your payer payments, how the vendor is paid, the written privacy terms and the reports you will get. Compare cost on one yardstick, not a headline rate.
A small practice rarely has a billing department. It has a biller, a front desk and a provider who also does paperwork. That is why the decision is different from the one a hospital faces: one absence, one missed deadline or one weak handoff shows up in cash flow quickly. This guide helps you decide whether to outsource, what the service should cover, and what to put in writing. It does not repeat our vendor checklist; when you reach the shortlist stage, use the ten questions to ask before hiring a medical billing company.
Key takeaways
- Decide scope first: list what stays at your front desk and what a vendor handles.
- Compare in-house, outsourced and hybrid on one yardstick, such as HFMA’s Cost to Collect.
- A signed BAA comes before any patient data access; payments should go to an account in your name.
- Agree named metrics with written definitions, not a promise of a good rate.
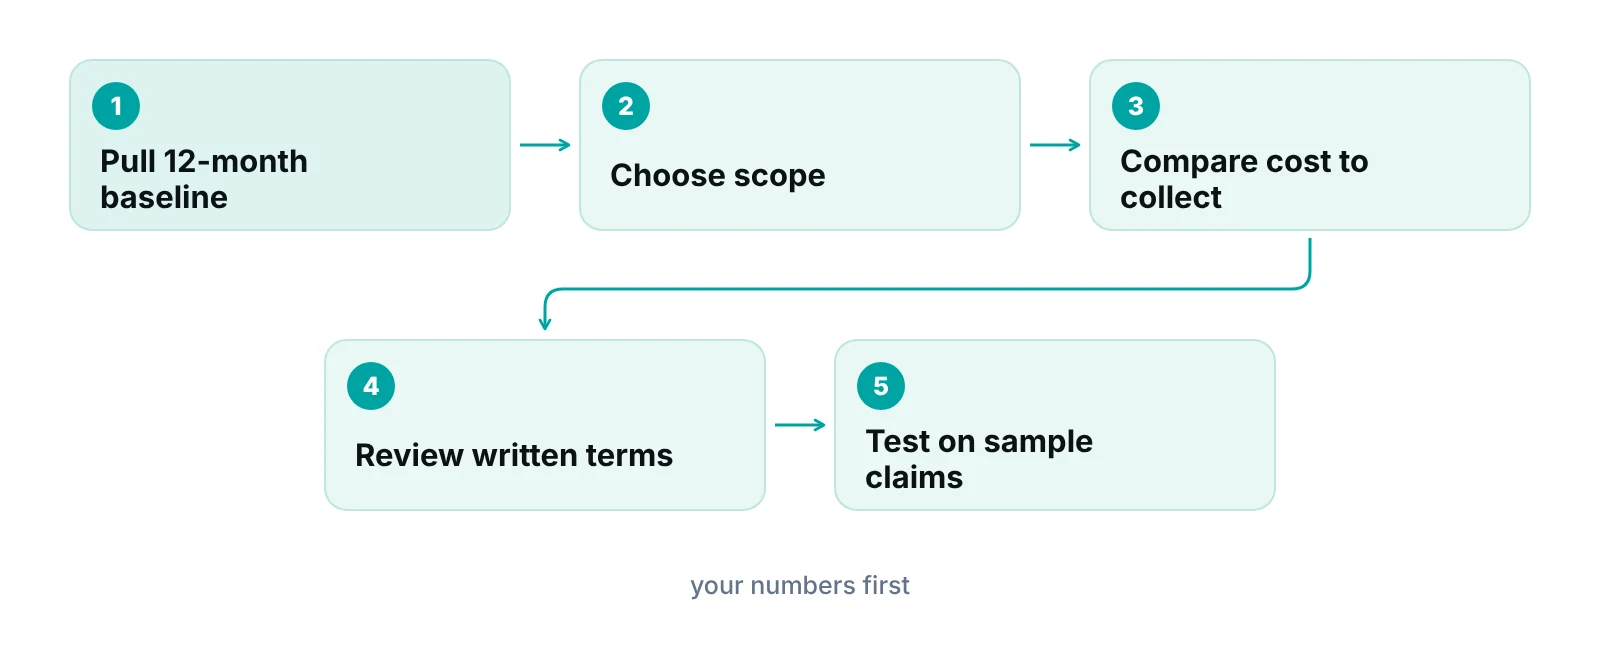
- Test the vendor on a sample of your own claims before volume moves.
What do medical billing services for small practices actually cover?
A billing service takes over some or all of the work between a finished visit and a posted payment, and the scope varies by vendor. Our medical billing services page lists what we handle; use the same split below to ask any vendor what is in and what is out.
| Task | Billing service usually | Practice usually keeps |
|---|---|---|
| Registration and insurance details | Optional add-on: eligibility checks on request | Collect accurate demographics and the insurance card at scheduling and check-in |
| Documentation and code selection | Coding support or coder review, if in scope | The provider documents the visit; clinical documentation stays the provider’s responsibility |
| Charge entry and claim submission | Included in most scopes | Send encounter data on an agreed schedule |
| Payment posting | Included in most scopes | Compare reports with bank deposits |
| Denial follow-up and appeals | Often included; confirm how far appeals go | Supply records a payer asks for |
| A/R follow-up on unpaid claims | Often included | Set write-off and adjustment policy |
| Patient statements and balance questions | Sometimes included | Handle conversations at check-out |
Source: HHS OIG compliance guidance for third-party billing companies (Federal Register, 1998) on documentation responsibility; the other rows describe common scopes, not a regulatory list.
Notice the gap in most small-practice setups: front-end errors such as a wrong member ID or missing authorization are created at the desk, but a billing service finds them later. Agree up front who fixes them and how fast.
Should a small practice outsource billing, keep it in-house, or split it?
Outsource when billing rests on one person or denials are not being worked; keep it in-house when you have a trained biller, a backup and steady reporting; split it when you want the front desk to keep control of registration.
| Option | Works best when | Watch for |
|---|---|---|
| In-house | You have a trained biller, a cross-trained backup and enough claim volume to keep that role busy | A single point of failure: one absence stalls claims, and know-how leaves with the person |
| Fully outsourced | Billing is a bottleneck, nobody follows up on denials, or the provider is doing billing after hours | Less day-to-day visibility unless reports are specific, and payments must still land in your account |
| Hybrid | The front desk keeps registration and check-out collection while a vendor handles claims, denials and A/R | Handoff gaps: who fixes missing insurance data and who talks to the patient |
Compare the cost of each option on one measure. HFMA defines Cost to Collect (FM-6) as total revenue cycle cost divided by patient service cash collected for the month, net of refunds, and its definition counts outsourced arrangements and software maintenance among the costs. Add your biller’s pay and benefits, software, clearinghouse fees and the provider and manager time you spend on billing, then do the same for a vendor quote. A lower fee that leaves you doing more of the work is not cheaper.
“For a small practice, the real risk is not the fee. It is a billing process that only one person understands and nobody else can check.”
— Awais Afzal, Healthcare Operations & Data Analyst
Want to know what your open claims are tying up?
Use the revenue calculator for a rough view of stalled A/R before you compare options.
How should you compare fees, and who should hold the money?
Compare fee models by what each one rewards, and keep payer payments going to an account in your practice’s name. We do not publish prices; our fees are quoted after a free audit, because scope and claim volume change the answer.
- Percentage of collections: ties the vendor’s income to your collections. Ask which payments count, how reversals are handled and what review guards against upcoding.
- Flat monthly fee: predictable. Ask what volume and tasks it covers and what counts as extra.
- Per-claim fee: easy to compare. Ask whether resubmitted claims and appeals are charged again.
- Hourly or dedicated staff: suits a defined workload. Ask who supervises the work and how hours are reported.
Two rules sit behind the questions. The HHS OIG, in its compliance guidance for third-party billing companies, has long been concerned that percentage billing may increase the risk of upcoding, and it says compensation should not give a financial incentive to improperly upcode (Federal Register, 1998). Separately, for Medicare, 42 CFR 424.73 says payment to a billing agent is always made in the provider’s name, and lists conditions for an agent that receives payment, including that its pay is not tied to the amounts billed or collected and that the provider can change or revoke the payment instructions. Have a healthcare attorney review how those rules apply to your contract.
What must be in writing before a billing company touches patient data?
A signed business associate agreement (BAA) comes first. HHS lists billing among the activities that can make a vendor a business associate, and a covered entity may disclose protected health information (PHI) to one only after getting satisfactory assurances in a contract or other written arrangement.
| Item | What the rule or guidance says | Ask for |
|---|---|---|
| BAA before access | A covered entity may share PHI with a business associate only with written satisfactory assurances (HHS) | A signed BAA before any login or data transfer |
| Subcontractors | A business associate needs its own BAA with any subcontractor that handles PHI (HHS) | A list of subcontractors and confirmation of flow-down terms |
| Breach notice | A business associate must notify the covered entity without unreasonable delay and no later than 60 calendar days after discovery (45 CFR 164.410) | A contractual window that is shorter than the outer limit |
| Where payments go | Payment to a billing agent is made in the provider’s name (42 CFR 424.73) | Deposits into an account in your practice’s name |
| Claim review | OIG recommends review of claims before and after submission, with at least a valid statistical sample each year by a qualified coding expert (1998 guidance) | Who reviews, how often, and how you see results |
| Exclusion screening | OIG guidance says billing companies should avoid employing or contracting with sanctioned individuals and should screen against the sanction lists | Written confirmation of how staff are screened |
Sources: HHS business associate guidance; 45 CFR 164.410 (eCFR); 42 CFR 424.73; HHS OIG compliance guidance for third-party billing companies (Federal Register, 1998).
A BAA does not hand off your responsibility. HHS says a business associate is directly liable for failures such as not meeting Security Rule requirements, not notifying of a breach and not limiting PHI to the minimum necessary (HHS fact sheet), yet the OIG also notes that providers who rely on a billing company’s assurances can face liability if its program is ineffective. Ask about exit terms too: HHS says a BAA should direct the vendor to return or destroy PHI at the end of the agreement where feasible (HHS FAQ 2082). For the wider picture, see our guide to HIPAA compliance in medical billing.
At RCM Finder, we put a Business Associate Agreement in place before accessing patient data. Our portal uses role-based access, audit logging and encrypted (HTTPS) connections. Ask every vendor, including us, to show these in writing.
Which small-practice risks should a billing service cover?
Four risks hit small practices hardest: filing deadlines, unworked denials, specialty coding gaps and coverage when someone is out. Ask how the vendor handles each one.
Filing deadlines
For Medicare, 42 CFR 424.44 generally requires a claim to be filed no later than one calendar year after the date of service for services on or after January 1, 2010, with narrow exceptions. Commercial payers set their own limits in their contracts, so ask the vendor how it tracks the deadline for each payer you bill.
Denials and clean claims
A claim that is rejected or denied needs a named owner and a due date. Our guides to clean claims and medical billing denial management show what a working process looks like. Ask whether the vendor checks data completeness before submission and what happens to a denial after the first appeal.
Your specialty
Coding and payer rules differ by specialty. Ask the vendor to walk through your most common procedures and modifiers, and to work a sample of your own claims. You can see the specialties we support. Our team works inside your existing EHR (for example PrognoCIS, eClinicalWorks or athenahealth), so you do not have to change systems to start.
Coverage
Ask who covers your account during absences and how a staffing change on the vendor side is communicated to you.
How will you know a billing service is working?
Agree on a short list of named metrics with written definitions, then review them on a set schedule. A vendor’s own definition of a “clean claim” or “days in A/R” may differ from yours, which makes comparisons useless. The HFMA MAP Keys (2023 edition) give standard wording to borrow.
- Net Days in A/R (FM-1): net A/R divided by average daily net patient service revenue, using the most recent three months.
- Remittance Denial Rate (AR-5): claims denied divided by claims remitted, counting only actionable denials, at claim level.
- Clean Claim Rate (CL-1): claims that pass edits with no manual intervention divided by claims accepted into the claims processing tool.
- Cost to Collect (FM-6): total revenue cycle cost divided by patient service cash collected, net of refunds.
We do not set targets here because the right level depends on specialty, payer mix and starting point. Capture your own baseline first. Our guide to revenue cycle KPIs explains each measure in more depth.
What should the first weeks with a billing service look like?
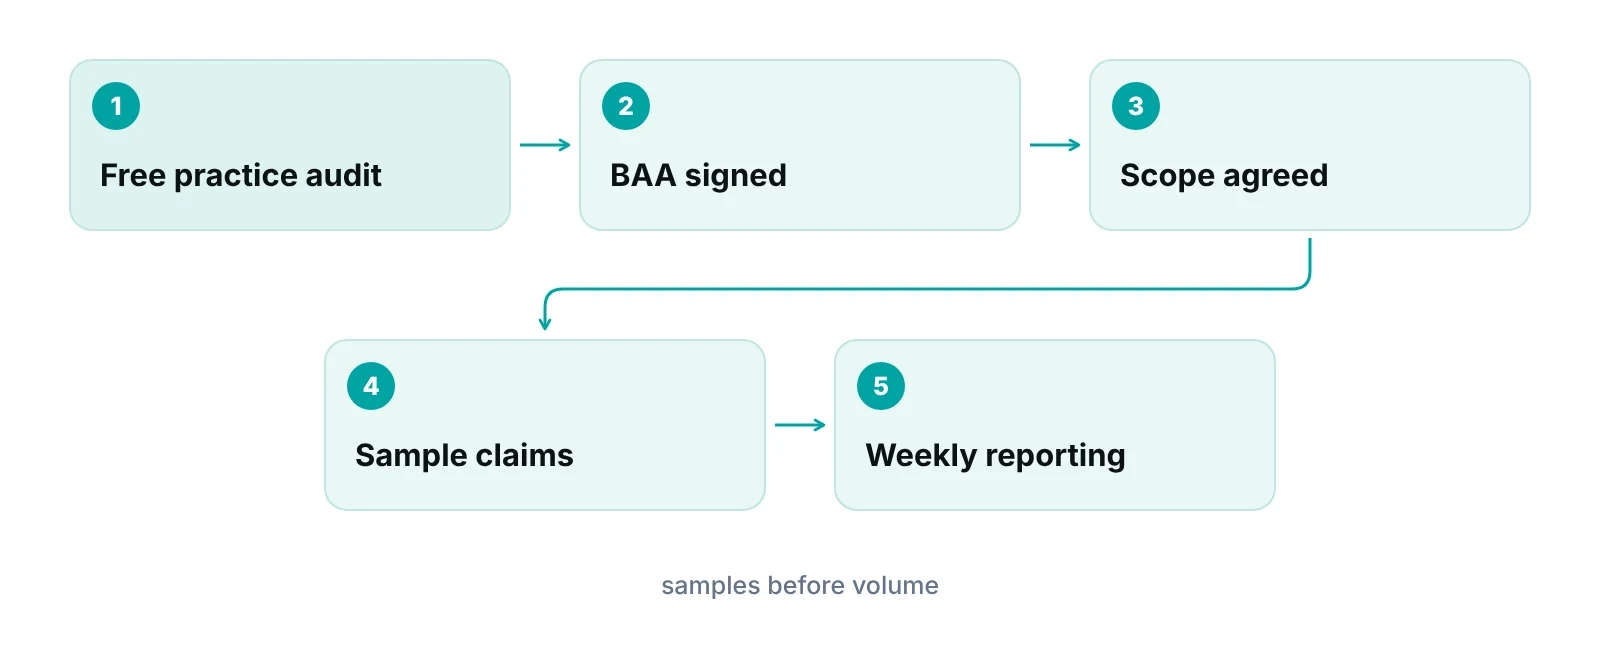
A careful start is slower than a rushed one and cheaper than a bad handoff. This is the sequence we follow, and a fair test for any vendor:
- Baseline review. We start with a free practice audit of your claims, denials and A/R aging.
- BAA and access. The agreement is signed before anyone sees patient data, and staff get role-based permissions.
- Scope and handoffs in writing. Who enters charges, who fixes missing insurance data, who calls patients.
- Sample claims. A set of your own claims is worked and reviewed by you before volume moves.
- Go-live with reporting. You see claim status by stage and the metrics you agreed.
- Scheduled review. Scope, results and exceptions are reviewed at an agreed interval.
Our portal supports this with a claim tracking pipeline by stage, data-completeness checks before submission, underpayment detection against expected amounts, an audit log and a client portal, so you can check progress yourself.
Start with your own numbers
Our free practice audit gives you a baseline to hold any billing company to, including us. Pricing is quoted after the audit.
Who should outsource billing, and who should not?
Outsourcing fits practices where billing is fragile; it does not fit practices that want to hand off everything and stop looking.
- A good fit: billing depends on one person, denials sit unworked, a provider or manager is doing billing at night, or you are adding providers and payers.
- A fit with a hybrid scope: your front desk is strong and you want help only with claims, denials and A/R.
- Probably not yet: you have a trained biller with backup, reports you trust and a baseline you are happy with.
- Not a fit: you want a guarantee of results or no involvement. No honest vendor can promise collections, and you remain responsible for documentation.
Be careful with guarantees
Treat any promise of a specific collection increase or denial rate as a reason to ask for the written definition and the data behind it.
Our recommendations
- Pull your last 12 months before any call. We would not talk to a vendor, including ourselves, before pulling denial reasons, A/R aging and payer mix. Every answer you hear is then testable.
- Decide scope before price. Write down what stays at your front desk and what moves. A quote is only comparable when two vendors price the same scope.
- Keep deposits in your own name. Ask for payer payments to land in an account you control, and read the contract clause on payment instructions.
- Sign the BAA first. No logins, no data exports and no screenshots of patient records before the agreement is signed.
- Test on your own claims. Have the vendor work a sample of your real claims and review the result yourself before volume moves.
- Agree metric definitions in writing. Use named measures such as Net Days in A/R and Remittance Denial Rate, with the formula in the contract, and review them on a fixed schedule.
Small practices often outsource and then lose sight of their claims.
The portal gives you a client view of claim status by stage and owner, so you can check where things stand without calling your biller.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
The right choice for a small practice is the one that fits your scope, keeps payments in your name, puts privacy terms in writing and gives you reports you can check. If you are weighing a fuller outsourced model, read how our end-to-end revenue cycle management service works, start with a free practice audit, or reach us through the contact page.
Frequently asked questions
What are medical billing services for small practices?
They are outside teams that handle some or all of the work from charge entry to payment posting, denial follow-up and A/R. Scope varies. Some only submit claims; others also check eligibility, support coding and appeal denials. Get the scope listed in writing.
Is it better to outsource billing or hire a biller?
It depends on backup and visibility. A trained biller with a cross-trained backup can work well. If billing rests on one person or denials go unworked, outsourcing or a hybrid split may be safer. Compare both using Cost to Collect, not just a fee or salary.
How much do medical billing services cost?
It depends on the fee model, claim volume, payer mix and scope, so we do not quote a number here. Common models are a percentage of collections, a flat fee, a per-claim fee or hourly staff. We quote after a free audit.
Do I need a business associate agreement with a billing company?
Yes, if the company handles protected health information for you. HHS lists billing among business associate activities, and a covered entity may disclose PHI only after getting satisfactory written assurances, usually a BAA. Get it signed before any data access.
Should payments go to the practice or the billing company?
Ask for payments to go to an account in your practice’s name. For Medicare, 42 CFR 424.73 says payment to a billing agent is made in the provider’s name and sets conditions for agents. Have an attorney review your contract.
How long does it take to switch billing companies?
We do not promise a timeline because it depends on your EHR, open A/R and payer enrollment. A careful switch includes a baseline review, a signed BAA, a sample of your claims and an agreed reporting schedule before full volume moves.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Business Associates (HIPAA guidance) — HHS Office for Civil Rights (current)
- Direct Liability of Business Associates fact sheet — HHS Office for Civil Rights (current)
- HIPAA FAQ 2082: return or destruction of ePHI — HHS (current)
- 45 CFR 164.410 Notification by a business associate — eCFR (current)
- 42 CFR 424.73 Prohibition of assignment of claims by suppliers — Cornell LII (eCFR text) (current)
- 42 CFR 424.44 Time limits for filing claims — eCFR (current)
- Compliance Program Guidance for Third-Party Medical Billing Companies — HHS OIG, Federal Register (1998)
- MAP Keys, 2023 edition — HFMA (2023)
Disclaimer: This article is general educational information for medical practices. It is not legal, HIPAA-compliance, coding or billing advice. Fee arrangements, payer rules and contract terms vary, and the rules cited here can change. Confirm requirements with qualified counsel and your payers before acting.
