
Screening and diagnostic colonoscopy claims, anesthesia and pathology coordination, prior authorization, patient marketing and a claims portal for GI practices, built on CMS rules and your payers' own policies.
By Awais Afzal | Healthcare Operations & Data Analyst
Published October 12, 2026 · Last reviewed October 12, 2026 · Next review April 12, 2027
Quick answer
Gastroenterology billing services manage the claims a GI practice creates: screening colonoscopies that turn diagnostic (modifiers PT, 33 and KX), anesthesia and pathology that bill separately, ASC and hospital place of service, and prior authorization for items such as capsule endoscopy. RCM Finder pairs that billing with front-desk assistants, patient marketing and a claims portal.
On this page
In gastroenterology, one colonoscopy can be a screening, a diagnostic procedure or both. What the doctor finds changes the codes, the modifiers and what the patient owes. Anesthesia and pathology usually bill on their own claims, so all three must agree.
Medicare uses its own screening codes: G0121 for patients who are not high risk and G0105 for high-risk patients, as Noridian's colorectal screening page lists. 42 CFR 410.37 defines high risk and sets the clock: a G0121 screening needs at least 119 months after the month of the last screening colonoscopy, and a G0105 screening needs 23.
Place of service matters too. Under the Medicare Claims Processing Manual, the physician gets the facility rate in an ASC (POS 24) or hospital outpatient department (POS 19 or 22) and the non-facility rate in the office (POS 11). Noridian article A57342 adds that office colonoscopy claims without validated equipment information do not meet coverage requirements. See our guides to ASC vs HOPD billing and ASC and hospital billing services.
CMS's CY 2026 Physician Fee Schedule final rule fact sheet (October 31, 2025) set the conversion factor at $33.40 for clinicians who are not qualifying APM participants, up from $32.35. It applied a -2.5% efficiency adjustment to the work RVUs of non-time-based services (time-based codes such as E/M are exempt), and it now recognizes greater indirect costs for office-based work than for facility-based work. For 2027, the proposed rule fact sheet (July 14, 2026) projects $32.84. Check the final rule before budgeting.
For Medicare, a screening colonoscopy has no deductible or coinsurance. If the doctor removes a polyp or takes a biopsy, the claim carries modifier PT, the deductible stays waived and the patient pays reduced coinsurance: 15% through 2026, 10% from 2027 to 2029 and nothing from 2030.
The phase-down comes from section 122 of the Consolidated Appropriations Act, 2021. CMS's CY 2022 Physician Fee Schedule final rule fact sheet (November 2, 2021) set the schedule: 20% in 2022, 15% for 2023 through 2026, 10% for 2027 through 2029 and zero from 2030. CMS Transmittal 11772 applies it when PT is on a line with a procedure code from 10000 to 69999, anesthesia code 00811, G0500 or 99153. Pathology codes are not on that list.

Since January 1, 2023, a colonoscopy after a positive Medicare-covered stool-based test counts as screening. Per CMS MLN Matters MM13017, you add modifier KX to the screening code, frequency limits do not apply and the patient has no cost sharing. The CY 2025 PFS fact sheet extends this to a positive blood-based biomarker test. If polyps are removed, the AGA coding guide notes that Medicare treats the procedure as diagnostic and coinsurance applies.
Commercial claims use modifier 33, which marks a preventive service with a USPSTF A or B rating (per Palmetto GBA). The AGA guide adds 33 to each polypectomy code and to a colonoscopy after a positive stool test. Federal ACA FAQs Part 51 (January 10, 2022) treat polyp removal, anesthesia and pathology on a polyp biopsy as part of a screening colonoscopy, so non-grandfathered plans cannot charge cost sharing for them. From plan years starting on or after May 31, 2022, that covers a follow-up colonoscopy after a positive stool-based test too.
A GI practice needs referrals coming in, procedures classified before the scope, consistent claims across three billers and software that shows every claim.
Revenue leaks at the handoffs: a diagnostic colonoscopy booked as screening, an anesthesia claim without PT, a capsule study booked before the EGD report arrives. We run all four pillars on one set of payer rules.
Our healthcare digital marketing builds demand for screening and specialty care through local SEO, Google Ads, reputation work and a simple referral path for primary care offices.
Our virtual medical assistants for GI practices work on your practice's time zone. They verify eligibility, set the visit type from patient history, collect prior stool-test and scope reports, and start prior authorizations.
Our end-to-end gastroenterology revenue cycle management covers coding support, claim scrubbing, denial management and A/R follow-up, with extra GI checks: PT, 33 and KX, G0105 or G0121, modifier 53 and place of service.
Our practice management system tracks every claim by stage. It applies specialty-aware billing logic to each claim, checks that data is complete before submission and flags payments below the expected amount.
Find where your scope claims leak
We review recent colonoscopy, EGD, anesthesia and pathology claims, then show where screening status, modifiers or place of service cost you. Pricing is quoted after the audit.
Each GI service family has its own coding rule and common errors. Codes are described in our own words (the AMA owns CPT descriptors); check current code sets and your Medicare contractor's articles before billing.
| Service family | Code examples (our wording) | Billing nuance | Typical denial or billing error |
|---|---|---|---|
| Medicare screening colonoscopy | G0121 (not high risk); G0105 (high risk) | No cost sharing; 119 months between G0121 screenings, 23 for G0105 | Billed too early; G0105 without a documented high-risk condition |
| Screening that turns diagnostic or therapeutic | 45380 (biopsy) or 45385 (snare removal) with PT (Medicare) or 33 (commercial) | Medicare: deductible waived; coinsurance 15% in 2026, 10% from 2027 | PT or 33 missing, so the patient is billed as diagnostic |
| Follow-on colonoscopy after a positive stool or blood test | G0105 or G0121 with KX (Medicare); 33 (commercial) | Part of screening; no frequency limit; no cost sharing | Billed as diagnostic, so cost sharing is applied |
| Incomplete colonoscopy | 45378 (diagnostic), G0105 or G0121 with modifier 53 | Paid at one-half the value of the code's inputs (Noridian) | Billed as complete; report missing the maximum depth reached |
| Anesthesia for colonoscopy | 00812 (screening); 00811 with PT (turned diagnostic); 00813 (upper and lower together) | Medicare: no cost sharing on 00812; 00811 with PT has no deductible and reduced coinsurance | Plan criteria for monitored anesthesia not documented |
| Surgical pathology from endoscopy | 88300 to 88309 series, e.g. 88305 (level IV tissue exam); 88342 (immunostain) | One unit per specimen; several biopsies of one polyp are usually one specimen | Extra units for tissue not sent for separate examination |
| Capsule endoscopy | 91110 (esophagus through ileum); 91111 (esophagus) | Covered for listed indications, e.g. obscure bleeding after upper and lower endoscopy (Novitas) | Upper and lower endoscopy not done first; used for colorectal screening |
Sources: CMS Transmittal 11772 (2022); CMS MLN Matters MM13017 (2023) and MM10181 (2018); 42 CFR 410.37; Noridian colorectal screening page (2025) and article A57342 (2025); NCCI Policy Manual ch. X (2026); Novitas LCD L35089; Anthem CG-MED-34 (2026); AGA coding guide; Palmetto GBA; AAPC code summaries. Rules vary by contractor and payer.
For Medicare, MLN Matters MM10181 uses 00812 for anesthesia with a screening colonoscopy, with deductible and coinsurance waived, and 00811 with PT when the screening becomes diagnostic. Commercial plans may set criteria for monitored anesthesia; Anthem guideline CG-MED-34 lists situations such as ASA class III or higher, sleep apnea and age over 70. Our anesthesia billing guide explains time and base units.
Pathology is billed per specimen. The NCCI Policy Manual (2026) says several biopsies of the same polyp are usually one specimen, while two polyps at different sites may be separate when knowing which is malignant matters. Immunostains count per antibody per specimen. Our pathology CPT code guide covers code levels.
Clear the visit type and any authorization before the scope is scheduled: screening status, the last procedure date and each plan's rules for EGD, colonoscopy, capsule endoscopy and anesthesia.
Plan rules move. UnitedHealthcare announced on September 1, 2026 that from October 1 it would stop requesting advance notification for EGD, capsule endoscopy and diagnostic and surveillance colonoscopy for commercial and Oxford New York and Connecticut members, and end GI site-of-service reviews. The AGA notes that ERCP and certain small-bowel services are not named and member-specific rules still apply.
Capsule endoscopy has its own rules. Novitas LCD L35089 covers it for listed indications, such as obscure bleeding after upper endoscopy and colonoscopy fail to find the source, and not for colorectal screening. Medicare Recovery Auditors have an approved review of capsule claims (topic 0227, March 2026). Washington's Health Care Authority uses a capsule authorization form that asks for the last EGD and colonoscopy findings.
Since January 1, 2026, the CMS-0057-F rule has required Medicare Advantage, Medicaid and CHIP plans to decide expedited requests within 72 hours and standard requests within seven calendar days, with a specific denial reason. In the AMA's 2025 survey of 1,000 physicians (released May 2026), physicians averaged 40 prior authorizations and 13 hours of staff and physician time per week.
| Rule | Source | What the VMA checks |
|---|---|---|
| High risk: close relative with colorectal cancer or adenomatous polyp, hereditary syndromes, or personal history of adenomatous polyps, colorectal cancer or IBD | 42 CFR 410.37(a)(3) | Family and personal history recorded; G0105 or G0121 flagged |
| Screening colonoscopy: 119 months (not high risk), 23 months (high risk), or 47 months after a screening sigmoidoscopy | 42 CFR 410.37(g) | Date and type of the last colonoscopy or sigmoidoscopy |
| Follow-on colonoscopy after a positive stool or blood-based test is screening, with no cost sharing | 42 CFR 410.37(k); MLN MM13017; ACA FAQs Part 51 | Positive result on file; booked as follow-on screening |
| Medicare coinsurance if screening turns therapeutic: 15% in 2026, 10% from January 1, 2027 | CMS Transmittal 11772 | Patient told before the procedure what they may owe |
| Monitored anesthesia may need documented risk factors | Anthem CG-MED-34 (example) | ASA class, sleep apnea and sedation history noted |
| Capsule study after upper and lower endoscopy; not for colorectal screening | Novitas L35089; Washington HCA form 13-0144 | Prior EGD and colonoscopy reports attached to the request |
| MA, Medicaid and CHIP decide in 72 hours (expedited) or 7 days (standard) | CMS-0057-F; in effect Jan 1, 2026 | Request and due dates logged; follow-up on the due date |
| Commercial lists change; UnitedHealthcare ended GI advance notification Oct 1, 2026 | UnitedHealthcare notice (2026) | Current plan rules checked at each booking |
Sources: eCFR 42 CFR 410.37; CMS MLN Matters MM13017 (2023); DOL ACA FAQs Part 51 (2022); CMS Transmittal 11772 (2022); Anthem CG-MED-34 (2026); Novitas LCD L35089; Washington HCA form 13-0144 (rev. 12/24); CMS-0057-F fact sheet (2024); UnitedHealthcare (2026). Always check the member's current plan.
For the general workflow, read our prior authorization guide for providers.
See what misclassified scopes cost you
Enter your claim volume and denial rate to estimate what denials and slow A/R cost your GI practice.
GI growth comes from screening demand, referring physicians and local search, and the tracking behind it must respect HIPAA.
We build location pages, procedure pages and plain-language screening pages that compare stool tests and colonoscopy. Primary care offices get a simple referral path. We ask real patients for reviews, and our replies never confirm someone is a patient.
HHS guidance on online tracking says tracking tools on patient portals generally have access to protected health information, and tools on scheduling pages may collect it too. A cookie banner is not a HIPAA authorization. A June 20, 2024 court order vacated part of that guidance. Even so, we keep tracking off scheduling and referral forms unless the vendor signs a BAA.
Stay in-house if experienced GI coders and your front desk already handle screening history well. Use a billing-only vendor if claims are your only gap. Choose a combined partner when errors start at scheduling and end in patient bills.
| Job | In-house team | Billing-only vendor | Four-pillar partner (RCM Finder) |
|---|---|---|---|
| Visit type set at booking | Front desk, if trained | Left to the practice | VMA asks history questions; coder confirms |
| PT, 33 and KX on scope claims | Depends on one coder | Fixed after a denial or complaint | Checked before submission on every scoped claim |
| Anesthesia and pathology in step | Separate billers, little contact | Scope claim only | Screening status shared with each biller |
| Capsule and plan authorizations | Front desk, between calls | Left to the practice | VMA tracks each request to a decision |
| Screening and referral growth | A separate agency, or nobody | Not included | Marketing pillar tied to booked procedures |
| Cost structure | Salaries, benefits, turnover | Varies; ask how fees are set | Quoted after a free practice audit |
We will tell you in the audit if you need only one pillar. For general in-house tips, see our gastroenterology billing guide.
We start with a free audit and change nothing until you see the findings. We build our billing pipeline around how claims actually move through a practice: registration, charge entry, submission, payment and follow-up. For GI, we add the screening, modifier and specimen checks on this page.
We review recent scope, anesthesia and pathology claims, denials and billing complaints, and map each procedure to its place of service.
We put a Business Associate Agreement in place before accessing patient data. Then we work inside your existing EHR (for example PrognoCIS, eClinicalWorks or athenahealth).
Your Medicare contractor's articles and main plans' rules become a pre-procedure checklist and portal workflow rules.
VMAs set visit types and start authorizations on your time zone. Claims are scrubbed, submitted and worked through denials and A/R.
Each week we review denials by reason, A/R days, screenings turned diagnostic and referrals. Add Own Practice Management System for more depth.
Talk to us about your GI practice
Tell us your sites, procedure mix and hardest payer. We will tell you honestly whether we fit.
Any billing vendor that handles your patients' data is a HIPAA business associate. Get a Business Associate Agreement before any access, and check how access is limited and logged.
HHS guidance names billing, claims processing and practice management as business associate work; subcontractors need their own agreement. The minimum necessary standard limits uses and disclosures to what each task needs. The Security Rule's technical safeguards are access control, audit controls, integrity, person or entity authentication and transmission security.
We use role-based access, audit logging and encrypted (HTTPS) connections, and we put a Business Associate Agreement in place before accessing patient data. For your own side, use our HIPAA compliance checklist for medical practices.
We would rather tell you now than after you sign. Here is where we fit and where we do not.
A good fit if you are
Probably not a fit if you are
What we would do first if we were running your practice's revenue cycle tomorrow.
We set screening, surveillance or diagnostic from the patient's history before the scope is scheduled. The coder then confirms it against the findings.
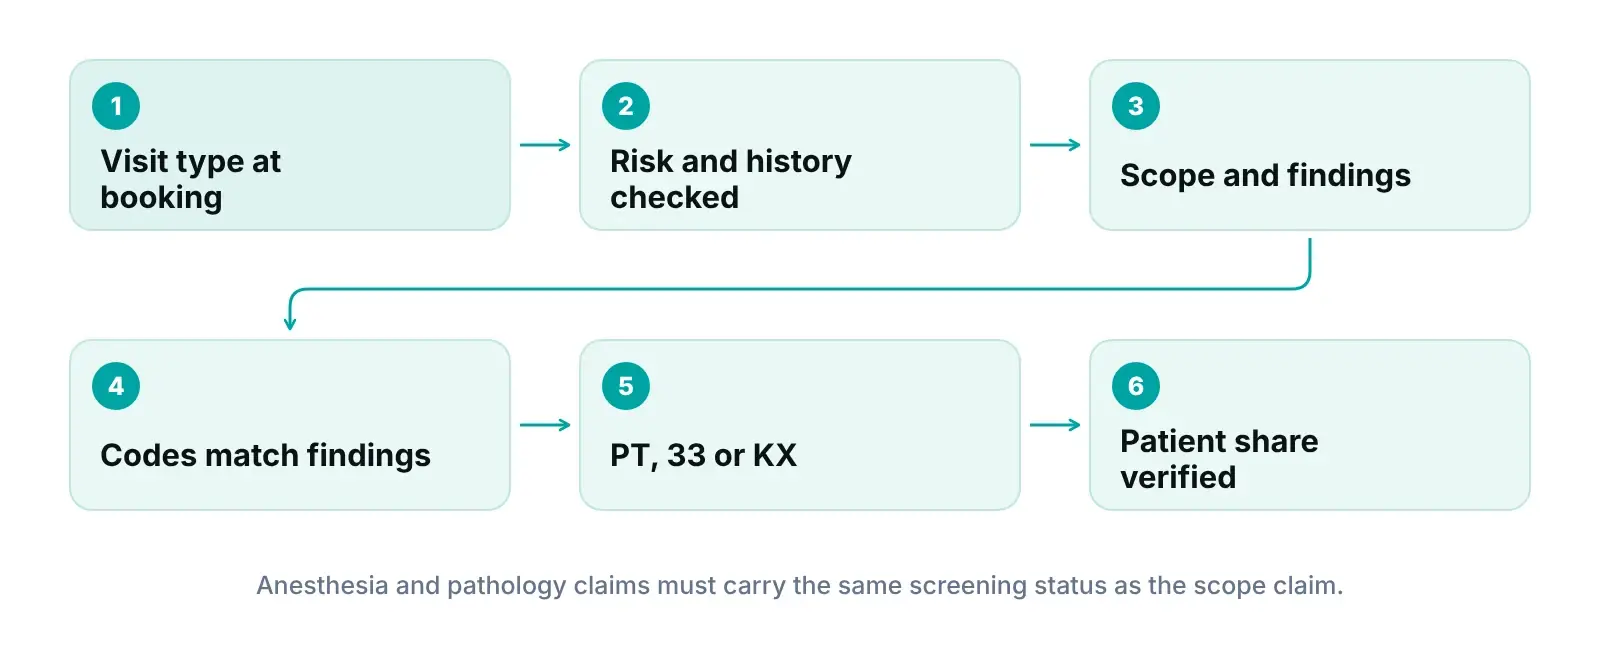
Every scoped claim gets three questions: did it start as a screening, was tissue removed, and was there a positive stool or blood test first? Each answer maps to a modifier.
Medicare coinsurance on a screening that turns therapeutic drops from 15% to 10% for dates of service from January 1, 2027. We update cost estimates and scripts before then.
We share the screening status with your anesthesia and pathology billers so all three claims match.
We attach the last EGD and colonoscopy reports to the request. The LCD we reviewed also expects the full image set to be kept.
GI endoscopy rules changed in 2026. We recheck the main plans' lists and your contractor's articles each quarter.
They cover coding support, claim scrubbing, submission, denial management and A/R follow-up for GI visits and procedures such as colonoscopy, EGD and capsule endoscopy. A good partner also sorts screening from diagnostic work before the scope, adds the right modifier (PT, 33 or KX), keeps anesthesia and pathology claims consistent, and handles prior authorization. RCM Finder adds front-desk assistants, patient marketing and a claims portal, so one team owns the process from referral to payment.
When the doctor does more than look, such as taking a biopsy or removing a polyp, the claim uses the code for what was done. For Medicare, add modifier PT to that code; for commercial plans, add modifier 33. The visit still began as a screening, so the patient keeps screening protections: no Medicare deductible, reduced Medicare coinsurance, and no cost sharing for polyp removal under non-grandfathered ACA plans.
The deductible is waived. Coinsurance is reduced under section 122 of the Consolidated Appropriations Act, 2021: 15% for 2023 through 2026, 10% for 2027 through 2029, and zero from 2030. So a procedure in 2026 carries 15% coinsurance, and dates of service from January 1, 2027 carry 10%. The claim must include modifier PT. A screening colonoscopy with no tissue removed has no cost sharing.
For Medicare, bill the screening colonoscopy code (G0105 or G0121) with modifier KX. Since 2023 this follow-on colonoscopy counts as part of screening, frequency limits do not apply, and the patient has no cost sharing. Since 2025 the same applies after a positive blood-based biomarker test. If polyps are removed, coinsurance applies. Non-grandfathered commercial plans must cover the follow-up colonoscopy without cost sharing for plan years starting on or after May 31, 2022.
It depends on the payer. For Medicare, contractors set coverage rules: Novitas, for example, covers capsule studies for listed indications, such as obscure bleeding that upper endoscopy and colonoscopy did not explain, and not for colorectal screening, and Recovery Auditors review capsule claims. Some state programs use authorization forms. UnitedHealthcare stopped advance notification for capsule endoscopy for commercial members on October 1, 2026. Check each plan before scheduling.
It can be, if the vendor is treated as a business associate. HHS lists billing and claims processing as business associate work, so you need a Business Associate Agreement before the vendor receives patient data, and the agreement must require safeguards. The Security Rule's technical safeguards include access control and audit controls. We put a Business Associate Agreement in place before accessing patient data, and we use role-based access, audit logging and encrypted (HTTPS) connections.
Tell us about your practice. A member of our operations team replies within one business day.
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Tell us about your practice
About the author: Awais Afzal
Healthcare Operations & Data Analyst, RCM Finder
Awais has spent more than 16 years in healthcare digital marketing and clinical operations management. He builds data-driven revenue cycle blueprints for high-ticket medical practices and leads product development of the RCM Finder portal. More about our team.
How we write: every figure, code and rule on this page was checked against the primary source listed below and independently fact-checked before publishing. We re-review this page every six months. Last reviewed October 12, 2026; next review April 12, 2027.
We use cookies to understand how our site is used and to measure our advertising. You can accept or reject non-essential cookies. See our Privacy Policy.