
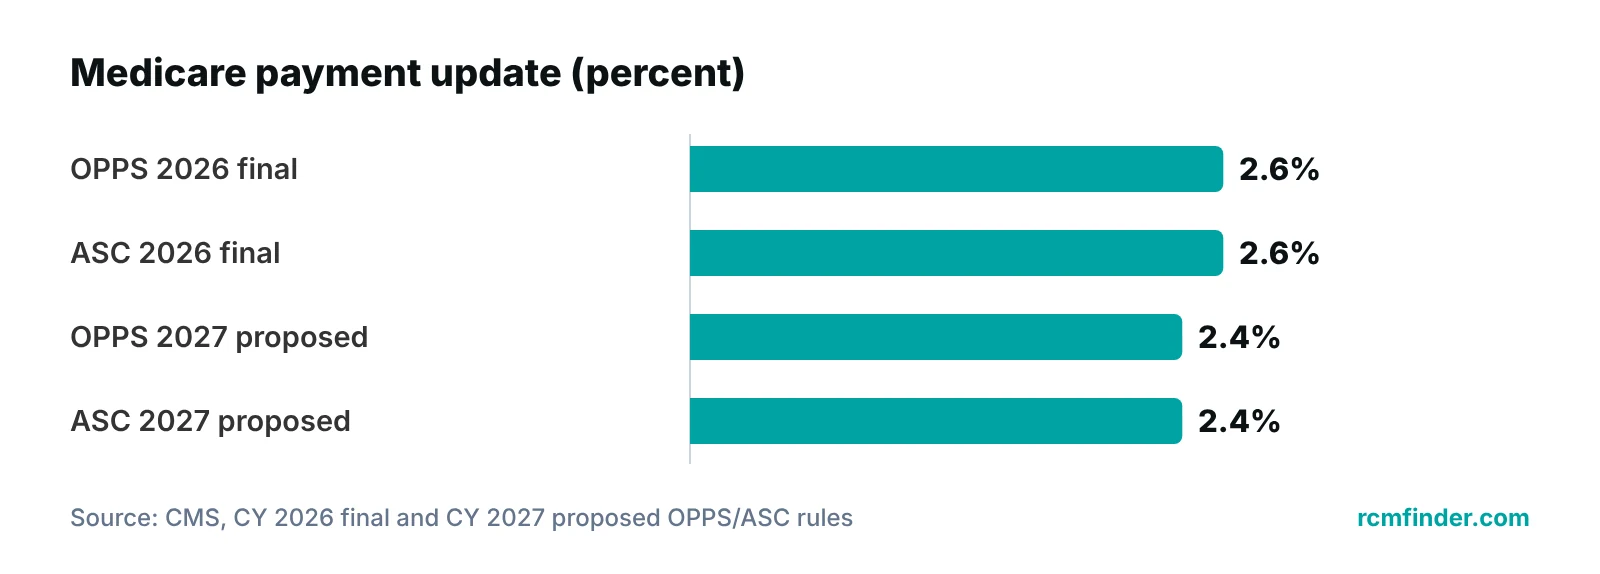
ASC vs HOPD billing differs mainly in who bills the facility fee and which Medicare payment system sets it. An ASC bills under the ASC payment system for procedures on the ASC list. A hospital outpatient department is paid under OPPS. Both got a 2.6% update in CY 2026 (CMS).
If you manage a surgery center, a physician-owned practice that uses one, or a billing team that handles both settings, the same procedure can follow two different billing paths. The rules change every year, and several popular articles on this topic still quote cost gaps and denial rates that cannot be traced to a source.
This guide sticks to what CMS publishes. It explains the billing mechanics, the current-year payment facts (calendar year 2026, final) and the 2027 changes that are still only proposed. For the general explainer, see our ASC vs hospital billing overview.
Key takeaways
- ASCs and HOPDs are paid under two separate Medicare systems: the ASC payment system and OPPS.
- Medicare pays an ASC a facility rate only for covered surgical procedures on the ASC list, and routine items are packaged into that payment.
- CMS finalized a 2.6% update for both OPPS and ASC payments in CY 2026; CMS proposed 2.4% for both in CY 2027, but that is not final.
- Site-neutral policy is expanding inside hospital outpatient departments, so the HOPD side of a comparison is moving.
- Do not rely on blanket claims that one setting is cheaper or denies less; test your own payer mix.
What is the core difference between ASC and HOPD billing?
The core difference is the payment system behind the facility fee. Medicare pays hospital outpatient departments under the Outpatient Prospective Payment System (OPPS) and pays ambulatory surgery centers under the ASC payment system. Each system has its own covered-service list, its own annual update and its own quality-reporting rules (CMS, CY 2026).
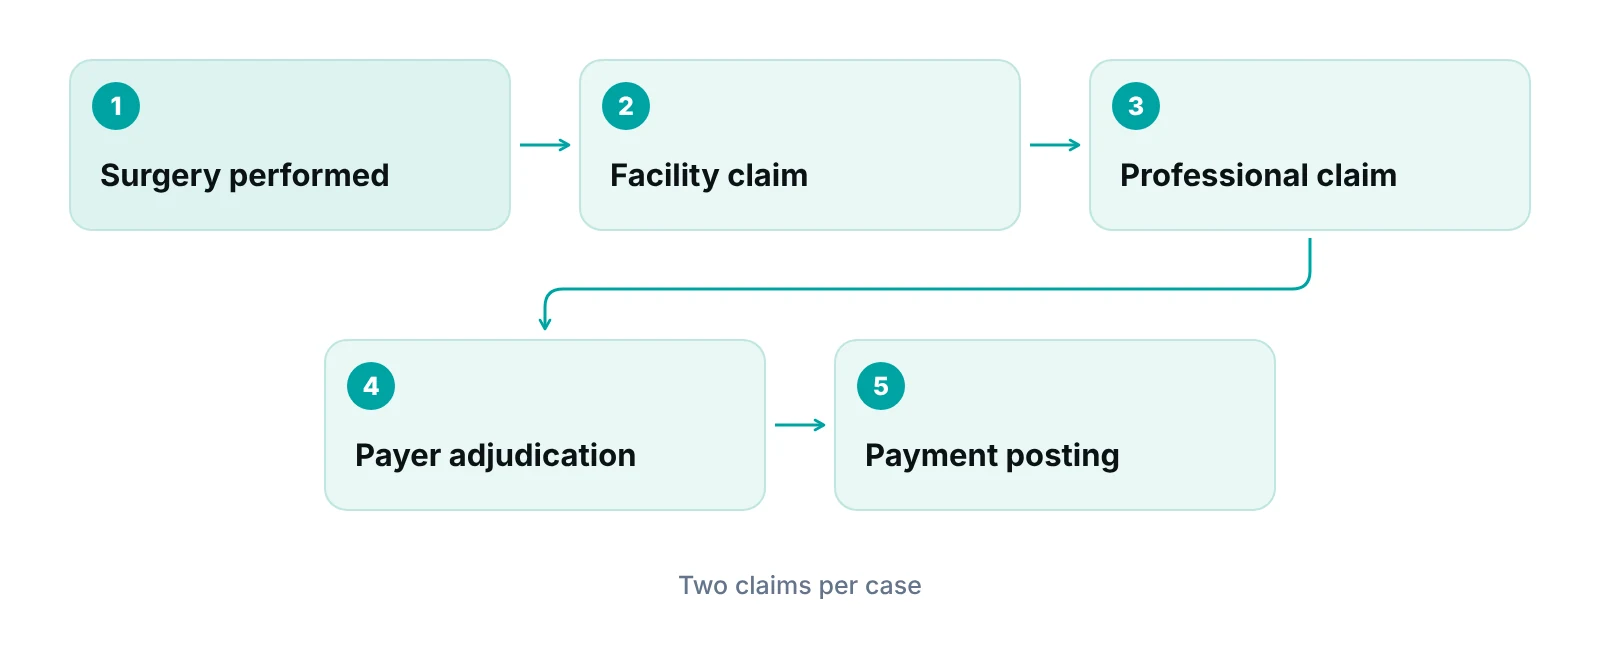
Everything else follows from that. The facility that owns the building, staff and supplies bills a facility fee. The surgeon and anesthesia clinicians usually bill their own professional fees separately. Mixing up the two claim types is one of the most common sources of rework when a practice starts using an ASC. Our guide to hospital vs professional billing explains that split.
Why the setting matters to your revenue cycle
- Different list of payable procedures. An ASC is paid only for covered surgical procedures on the ASC list. A hospital department is paid under OPPS rules instead.
- Different annual rule cycle. CMS issues one combined OPPS and ASC rule each year, but each system gets its own payment update and policies.
- Different billing workflow. The claim format, place of service and modifiers you need are different, and an error in one often produces a denial rather than a visible underpayment.
How do ASC and HOPD billing compare side by side?
On the Medicare side, the verified differences are the payment system, the claim format and what is packaged. The table below lists only items we could confirm from CMS documents. Commercial payers set their own terms, so treat it as the Medicare baseline.
| Item | Ambulatory surgery center (ASC) | Hospital outpatient department (HOPD) |
|---|---|---|
| Medicare payment system | ASC payment system | Outpatient Prospective Payment System (OPPS) |
| What is paid | A facility rate for covered surgical procedures on the ASC list; nursing, facility use, supplies and anesthesia materials are packaged into it | Services paid under OPPS; see your hospital’s billing office for how its packaging and status rules apply |
| Claim format used by the facility | ASC X12 837 professional format, or rarely Form CMS-1500; place of service 24 | Set by the hospital’s own institutional billing process; confirm with the hospital billing office or your MAC |
| SG modifier | No longer required on ASC facility claims since January 1, 2008 | Not applicable |
| CY 2026 payment update (final) | 2.6% for ASCs that meet quality reporting | 2.6% for hospitals that meet quality reporting |
| Quality reporting penalty | A non-reporting ASC takes a 2-percentage point reduction to its annual update | Hospitals must meet quality reporting requirements to get the full update |
Source: CMS Transmittal 3031, Medicare Claims Processing Manual Ch. 14 (2014 revision; confirm against the current manual); CMS CY 2026 OPPS/ASC final rule fact sheet (November 21, 2025).
Two details from that table cause real billing problems. First, the SG modifier is a leftover habit. CMS Transmittal 3031 (Claims Processing Manual, Chapter 14) states that since January 1, 2008 ASCs are no longer required to include SG on Medicare facility claims, yet many templates still add it. Second, the same transmittal says items such as nursing, facility use, supplies and anesthesia materials are packaged into the ASC procedure payment, so facilities should not bill those as separate lines.
For form-level detail, see our guides to the CMS-1500 claim form and the UB-04 claim form.
What billing mechanics trip up ASC claims?
ASC claims fail on a short list of mechanics: the wrong place of service, a missing technical-component modifier, a device-credit modifier left off, and packaged items billed as separate lines. Each is cheap to prevent before submission and slow to fix after a denial.
Place of service and the TC modifier
Per the Medicare Claims Processing Manual language in CMS Transmittal 3031 (Claims Processing Manual, Chapter 14), place of service code 24 applies to procedures performed in an ASC, and modifier TC is required unless the code describes the technical component only. First Coast Service Options (a Medicare Administrative Contractor) describes the same idea in its December 2024 modifier article: ASCs bill TC to show the technical (facility) component.
Device credit modifiers FB and FC
Some procedures involve implanted devices. First Coast Service Options states that an ASC must put FB on the procedure when a specified device is furnished at no cost or with full credit, and FC when it receives a partial credit of 50 percent or more of the device cost. One procedure code should not carry both. Your device purchasing log has to reach the billing team, or these modifiers get missed.
Check the current manual before you build edits
The SG and place-of-service language above comes from a 2014 transmittal that updated Chapter 14 of the Medicare Claims Processing Manual. Compare it with the current manual and your MAC’s ASC page before you hard-code any claim edit.
Facility fee and professional fee on separate claims
A surgeon who operates in an ASC bills a professional claim for the surgeon’s own work. The ASC bills a facility claim. If your practice both owns the ASC and employs the surgeon, keep two clean workflows so a charge posted to one never silently drops from the other. A practice with orthopedic cases will feel this most, which is why orthopedic billing support usually starts with a facility-versus-professional charge audit.
What changed for ASCs and HOPDs in 2026?
For calendar year 2026, CMS finalized a 2.6% payment update for both OPPS and ASC payments, using a 3.3% market basket increase less a 0.7 percentage point productivity adjustment. It also expanded site-neutral payment inside hospital departments and added 289 procedures to the ASC list (CMS fact sheet on the CY 2026 OPPS/ASC final rule, issued November 21, 2025).
| Policy | What CMS finalized for CY 2026 | Billing effect |
|---|---|---|
| Payment update | 2.6% for OPPS and for ASCs that meet quality reporting (3.3% market basket less 0.7 point productivity) | Update your fee schedule loads and expected-payment tables |
| ASC Covered Procedures List | 289 procedures added; 271 codes removed from the Inpatient Only list | More procedures can now be considered for the ASC setting; verify each code against the list |
| Drug administration at off-campus hospital departments | Paid at the Physician Fee Schedule equivalent rate at excepted off-campus provider-based departments | Lower expected payment for those hospital-department drug administration services |
| 340B offset | Existing 0.5% reduction for non-drug items and services kept; the proposed 2% was not finalized | Applies to affected hospitals’ OPPS rates, not to ASC claims |
| ASC quality reporting | 2-percentage point cut for non-reporting ASCs; four measures removed | Missing quality data reduces the annual update |
Source: CMS, CY 2026 OPPS/ASC final rule fact sheet (CMS-1834-FC), November 21, 2025.
The cost-comparison argument is shifting as well. CMS estimated that its 2026 site-neutral drug administration policy would save $290 million in OPPS spending, of which $220 million is Medicare’s share and $70 million is beneficiary coinsurance (CMS, CY 2026). For those services, hospital departments are paid at the physician fee schedule equivalent rate, so older comparisons that assume a fixed hospital premium may no longer hold.
What is proposed for 2027, and is any of it final?
None of the 2027 policies below are final as of October 14, 2026. CMS proposed a 2.4% update for both OPPS and ASC payments, based on a projected 3.2% market basket increase less a 0.8 percentage point productivity adjustment (CMS fact sheet on the CY 2027 OPPS/ASC proposed rule, July 2026).
- Proposed update: 2.4% for hospitals and ASCs that meet quality reporting.
- Proposed site-neutral extension: CMS proposes to apply its volume control method to imaging without contrast services at excepted off-campus provider-based departments, paying the Physician Fee Schedule equivalent rate. Rural sole community hospitals would be exempt. CMS estimates a reduction of about $260 million in Part B spending in the first year.
- Proposed ASC quality change: removal of the Appropriate Follow-Up Interval for Normal Colonoscopy in Average Risk Patients measure from the ASC Quality Reporting Program, starting with the CY 2027 reporting period.
Plan against the 2026 numbers, model 2027 as a range, and re-check once CMS publishes the final rule. A final rule normally differs from the proposal in places, so do not load proposed rates into your system.
What should you not assume about ASC vs HOPD billing?
Do not assume that one setting is always cheaper, always paid more, or always denied less. Many popular articles state a fixed dollar gap or a denial-rate range between the two. We could not trace those figures to any CMS or other primary source, and the answer depends on payer contracts, procedure mix and how clean your claims are.
- Medicare is only one payer. Commercial plans and Medicare Advantage plans set their own rates and rules, and those contracts often decide the real difference.
- Procedure mix drives the comparison. A list of covered ASC procedures grew by 289 in 2026, but whether a specific case belongs in an ASC is a clinical and payer decision, not a billing one.
- Denial rates belong to your own data. Pull denials by payer, procedure and setting from your own claims before comparing settings.
“The honest comparison is your own claims data by payer and procedure, not an industry average. I would rather see a practice measure two quarters of denials than quote a statistic it cannot source.”
— Awais Afzal, Healthcare Operations & Data Analyst
If you want a first estimate of revenue leakage across settings, our revenue calculator gives a rough starting point you can refine with your own numbers. For the Medicare rules behind the facility fee, see our guide to Medicare fee-for-service billing and coding.
What should you ask a billing partner who handles both settings?
Ask how they separate facility and professional claims, how they apply setting-specific modifiers, and how they track the annual rule cycle. A billing partner that cannot answer these in specifics is likely to treat both settings the same way, which is where denials start.
| Question | Why it matters | What a solid answer includes |
|---|---|---|
| How do you separate facility and professional claims for one case? | Charges can fall through the gap between the two | A charge-matching step that compares both claims per case |
| How do you handle ASC-specific edits such as place of service, TC, FB and FC? | These cause avoidable denials on ASC claims | Pre-submission checks tied to the device log and the claim format |
| How do you load the annual OPPS and ASC rule changes? | Rates and covered-procedure lists change each year | A dated process that separates final rules from proposals |
| What do you report weekly? | You need to see denials and A/R by setting | Denials by payer and procedure, A/R aging and a claim status view |
| What do you do with a denial? | Appeals need the right evidence and deadline | A named owner, payer-specific appeal steps and root-cause feedback to the front end |
Compare your ASC and hospital-side billing with a free audit
We review a sample of your claims by setting, flag the edits that are missing, and show you where denials start. Pricing is quoted after the audit.
Our recommendations
- Separate facility and professional workflows. We keep two charge lists per case and compare them before submission, so a surgery never ends up with only one of the two claims.
- Remove stale ASC claim edits. We check templates for legacy habits, such as adding SG to Medicare ASC facility claims, against the current Claims Processing Manual and your MAC’s ASC page.
- Tie the device log to modifiers. We ask the ASC to share its device invoices and credits so FB and FC can be applied on the right procedure lines.
- Load annual rules on a calendar. We update rates and covered-procedure lists once the final rule is out, and keep proposed rules in a separate watch list.
- Measure denials by setting from your own data. We report denials by payer, procedure and place of service, so any ASC or HOPD decision rests on your claims, not an industry average.
Bottom line
ASC and HOPD billing run on different Medicare payment systems, different claim mechanics and different annual updates, and the hospital side keeps moving toward site-neutral rates. Build your billing around verified rules and your own data. If you want a second pair of eyes on a mixed-setting workflow, our medical billing services and denial management services can start with a free audit, or you can talk to our team.
Frequently asked questions
What is the main difference between ASC and HOPD billing?
The payment system. Medicare pays ASCs under the ASC payment system for covered surgical procedures on the ASC list, and pays hospital outpatient departments under OPPS. Claim mechanics differ too. ASCs bill Medicare on the 837 professional format, or rarely the CMS-1500, with place of service 24, while hospitals use their own institutional billing process.
Which claim form does an ASC use for Medicare?
According to CMS Transmittal 3031 to Chapter 14 of the Medicare Claims Processing Manual, ASCs bill the Medicare contractor using the ASC X12 837 professional claim format or, in rare cases, Form CMS-1500. Place of service 24 applies. Confirm against the current manual and your Medicare Administrative Contractor, because commercial payers may add their own instructions.
Do ASCs still need the SG modifier?
Not for Medicare facility claims. CMS Transmittal 3031 says that starting January 1, 2008, ASCs are no longer required to include the SG modifier on Medicare facility claims. Some billing templates still add it, so review your claim edits. Commercial and Medicaid payers can have different modifier rules, so check each payer’s policy.
What did CMS finalize for ASC and hospital outpatient payment in 2026?
CMS finalized a 2.6% update for both OPPS and ASC payments in CY 2026, for facilities that meet quality reporting. It added 289 procedures to the ASC Covered Procedures List, and set drug administration at excepted off-campus hospital departments to the Physician Fee Schedule equivalent rate. The rule was issued November 21, 2025.
Is the 2027 OPPS and ASC update final?
No. As of October 14, 2026, the 2027 figures are proposals. CMS proposed a 2.4% update for both OPPS and ASC payments, plus a site-neutral extension for imaging without contrast at excepted off-campus hospital departments. Do not load proposed rates into your billing system. Check CMS for the final rule before you change any payment table.
Which setting has lower denial rates?
There is no reliable published figure we could verify, so we do not quote one. Denials depend on the payer, the procedure and how clean the claim is before submission. Compare denial rates by setting from your own claims data, grouped by payer and procedure, over at least a couple of quarters before you draw a conclusion.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Calendar Year 2026 OPPS/ASC final rule fact sheet (CMS-1834-FC) — CMS (2025)
- Calendar Year 2027 OPPS/ASC proposed rule fact sheet — CMS (2026)
- Transmittal 3031, Medicare Claims Processing Manual Pub. 100-04, Chapter 14 (Ambulatory Surgical Centers) — CMS (2014)
- Modifiers applicable to ambulatory surgical centers (ASCs) — First Coast Service Options (Medicare Administrative Contractor) (2024)
Disclaimer: This article is general educational information about Medicare billing operations. It is not legal, coding, billing-compliance or financial advice. Medicare rules, payer contracts and annual CMS rules change, proposed rules may not be finalized, and commercial and Medicare Advantage plans set their own terms. Confirm requirements with CMS, your Medicare Administrative Contractor, your payer contracts and qualified advisors before acting.
