
Ambulance billing codes are HCPCS Level II codes, not CPT. Medicare pays a base-rate code for the service level, from A0426 to A0434, plus a separate mileage line, A0425, for loaded miles only. Each claim also needs documented medical necessity and the correct origin and destination modifier.
This guide covers Medicare ground and air ambulance billing: what each code means, how to count mileage, and what the record must show. Every rule below is tied to a CMS document or the federal regulation, and we date the figures. Rules and payer contracts vary, so treat this as a reference, not coding advice.
Key takeaways
- Ambulance A-codes are HCPCS Level II, not CPT.
- A ground claim needs a base-rate code plus a separate loaded-mileage line (A0425).
- Bill the level the patient needed and the crew delivered, using the definitions in 42 CFR 414.605.
- CMS reported in 2024 that documentation problems caused 63.5 percent of ambulance improper payments.
- A certification form or a diagnosis code alone does not prove medical necessity.
What are ambulance billing codes?
Ambulance billing codes are HCPCS Level II codes that start with the letter A. They are not CPT codes. The old habit of calling A0425 a “CPT code” is wrong, and it matters because coders look in different books for each set. Medicare publishes the ambulance code list and the claim rules in Chapter 15 of its Claims Processing Manual.
A ground transport is paid in two parts: a base-rate code for the level of service, and a separate mileage code. The manual states that payment “includes a base rate payment plus a separate payment for mileage” (CMS). So a typical ground claim has at least two service lines. Missing either one is a billing error.
| Code | What it reports | Notes for the biller |
|---|---|---|
| A0426 | ALS, non-emergency transport, level 1 | Ground. ALS1 requires an ALS assessment or at least one ALS intervention |
| A0427 | ALS, emergency transport, level 1 | Ground. Emergency means an immediate response to a 911 call or its equivalent |
| A0428 | BLS, non-emergency transport | Ground. Crew is staffed by an EMT-Basic |
| A0429 | BLS, emergency transport | Ground. Same emergency-response test as A0427 |
| A0433 | ALS, level 2 (ALS2) | Ground. Needs three or more IV-push or infusion medications, or a listed procedure |
| A0434 | Specialty care transport (SCT) | Interfacility only, for a critically ill or injured patient who needs care beyond paramedic scope |
| A0430 / A0431 | Air transport, fixed wing / rotary wing | One way. Reported with air mileage codes A0435 / A0436 |
| A0432 | Paramedic ALS intercept (PI) | Rural transport furnished by a volunteer ambulance company |
| A0425 | Ground mileage, per statute mile | Loaded miles only. Billed as a separate line with the base-rate code |
Source: CMS, Medicare Claims Processing Manual, Chapter 15, Section 30 (code list); 42 CFR 414.605 (definitions). Descriptions are paraphrased.
When does Medicare cover an ambulance transport?
Medicare covers an ambulance transport when the patient’s condition makes every other way of travelling unsafe, and when the trip goes to a covered destination. The rule text says the “medical condition is such that other means of transportation are contraindicated” (42 CFR 410.40). The condition must support both the trip and the level billed.
Bed confinement is only one factor
A patient counts as bed-confined only if they cannot get out of bed without help, cannot walk, and cannot sit in a chair or wheelchair. A non-emergency transport can be medically necessary if the patient is bed-confined and other transport is contraindicated, or if the condition requires an ambulance regardless of bed confinement (CMS Medicare Learning Network).
Covered origins and destinations
Under the regulation, transport from any origin is covered to the nearest hospital, critical access hospital, rural emergency hospital or skilled nursing facility that can give the required level and type of care. Trips home from those facilities are covered. So are some other routes, such as a skilled nursing facility to the nearest provider of a service it cannot offer, and a home to dialysis trip for a patient with end-stage renal disease (42 CFR 410.40). Read the full rule before billing a route that is not on that list.
| Transport type | What to have on file | Timing rule |
|---|---|---|
| Emergency | Run record showing the patient’s condition and why other transport was contraindicated | Part of the record for the claim |
| Scheduled, repetitive, non-emergency | Physician certification statement plus supporting records | Certification dated no earlier than 60 days before the service |
| Unscheduled or non-repetitive, non-emergency, facility resident under a physician’s care | Physician certification statement | Due within 48 hours after the transport |
| Unscheduled or non-repetitive, non-emergency, patient not under direct physician care | No physician certification required; the run record still has to show necessity | Not applicable |
Source: 42 CFR 410.40(e); CMS Medicare Learning Network, Ambulance Services compliance tips.
A signed form is not proof of necessity
CMS states that the physician’s certification statement alone does not show that the transport was medically necessary (CMS). The crew’s patient care report has to describe the patient’s condition. If you cannot get any signature within 21 days, document your attempts before you bill.
CMS defines a repetitive transport as three or more round trips in a 10-day period, or at least one round trip a week for three weeks. It says prior authorization applies to repetitive scheduled non-emergent transport under the RSNAT model (CMS). Ask your Medicare Administrative Contractor (MAC) whether your service area is covered by that model.
How do you choose between BLS, ALS1, ALS2 and SCT?
You bill the level the patient needed and the crew delivered, not the level of the vehicle that showed up. The regulation defines each level by what was done on the call (42 CFR 414.605).
- BLS: ground transport with the needed supplies and services, staffed by an EMT-Basic who is qualified under state and local law.
- ALS1: the same transport, plus either an ALS assessment by ALS personnel or at least one ALS intervention.
- ALS2: transport plus either at least three medications given by IV push or bolus or by continuous infusion (standard crystalloid fluids do not count), or at least one of seven listed procedures, such as manual defibrillation, endotracheal intubation or a surgical airway.
- SCT: interfacility transport of a critically ill or injured patient who needs ongoing care from health professionals beyond the paramedic’s scope.
An ALS assessment does not make the trip ALS
The definitions say an ALS assessment is one done by an ALS crew as part of an emergency response. An ALS assessment alone does not mean the patient needed an ALS level of service (42 CFR 414.605). If a paramedic crew responded and only basic care was needed, the documentation should support a BLS-level claim, and the emergency or non-emergency code should follow how the call came in.
A line like “ALS intervention performed” does not support A0427. The record should name the intervention, who performed it and why the patient needed it.
How is ambulance mileage billed?
Bill loaded miles only. Loaded mileage is the number of miles the patient is carried in the ambulance. The manual says charges for mileage must be based on loaded mileage only (CMS Chapter 15). Miles driven to the pickup and miles driven back empty are not billable.
- Report fractions: for trips of up to 100 miles, round the total up to the nearest tenth of a mile. For 100 miles or more, round up to a whole number. A trip under one mile gets a leading zero, such as 0.9.
- Do not leave units blank: if the mileage units are missing, contractors default to 0.1. That pays almost nothing for a real trip.
- Use one mileage line: for ground transport, report all medically necessary mileage on a single line, using A0425.
- Air is separate: air mileage is reported in fractional loaded statute miles flown, with A0435 for fixed wing and A0436 for rotary wing.
A simple example: a crew drives 4.0 miles to the scene, loads the patient and drives 6.3 miles to the hospital. The claim reports 6.3 units of A0425. The 4.0 response miles are not billed.
If more than one patient rides in the vehicle, use modifier GM on each service line. The record must show how many patients were transported at the same time and each patient’s Medicare number (CMS).
How do you build a clean Medicare ambulance claim?
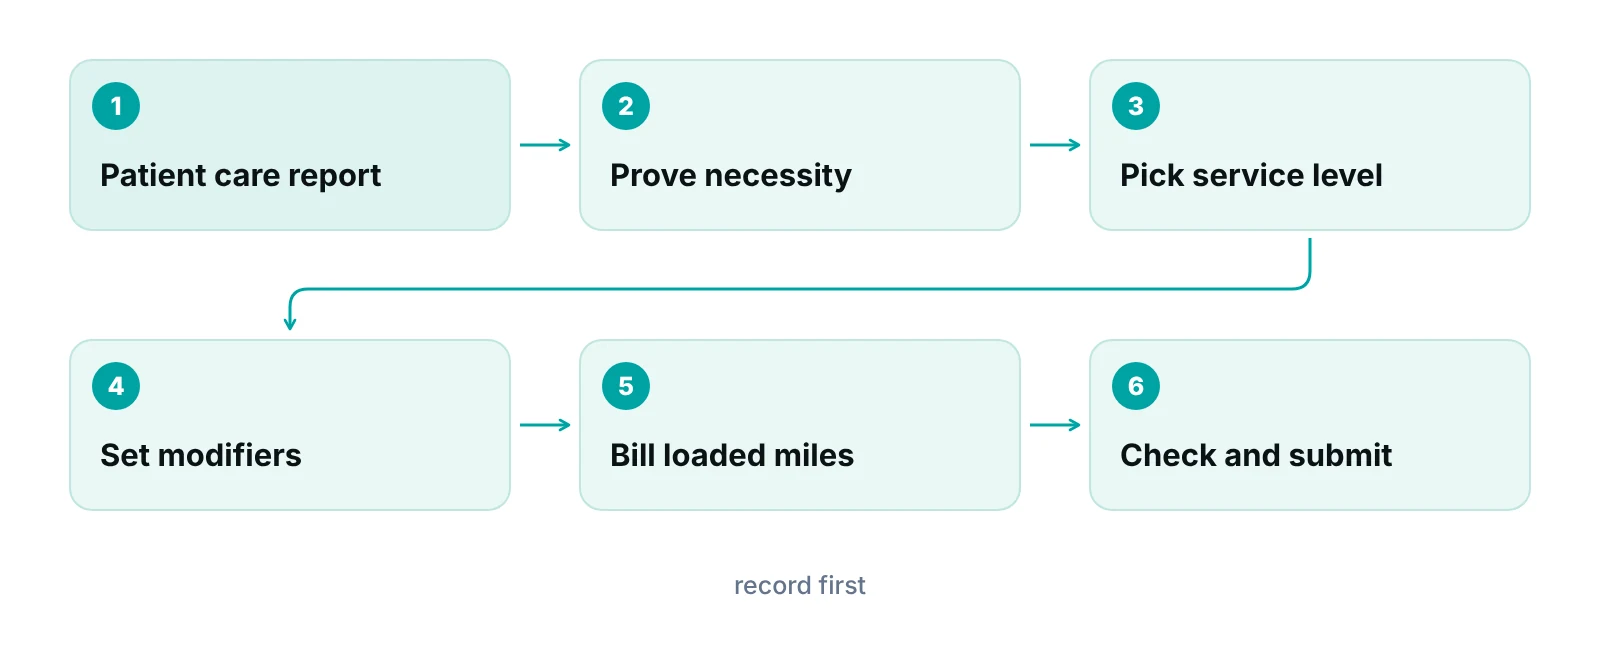
A clean claim carries the right form, the right base-rate and mileage lines, an origin and destination modifier on each line, and a record that supports all of it. Independent suppliers bill on the ASC X12 837 professional transaction or the CMS-1500 form. Institutional providers use the 837 institutional or the CMS-1450 (CMS Chapter 15). The old CMS-1491 form has not been valid since April 2, 2007.
Origin and destination modifiers
Each service line carries a two-character origin and destination modifier. The first character is where the patient was picked up and the second is where the patient was taken. Chapter 15 defines the permitted single-letter values in Section 30 (CMS). Pick them from the record, not from a default.
Hospital-based services use QM when the service is provided under arrangement by a provider of services, and QN when the provider furnishes it directly (CMS).
Diagnosis codes
The 837 professional format requires a diagnosis code on the claim. The manual also says a diagnosis code on an ambulance claim is not required as a condition of the Medicare payment policy (CMS). Enter an accurate code, and let the patient care report carry the proof.
Related reading: clean claims and claim scrubbing explain the general data checks that catch gaps before a payer does.
What does Medicare pay for ambulance services?
Medicare pays from a national fee schedule: a base rate plus a mileage payment, with Part B deductible and coinsurance applying. The common “Medicare pays 80%” shortcut leaves out the fee schedule, the deductible and the add-ons. The manual states that Part B coinsurance and deductible requirements apply to payments under the ambulance fee schedule (CMS).
The base rate is built from a conversion factor and a relative value for each service level, with BLS set at 1.00. A geographic index is applied to 70 percent of the base rate. The mileage rate is not adjusted by that index (CMS). The MACs keep the official files used to pay claims.
Temporary add-ons also apply. On its CY 2026 fee schedule page, CMS lists a 2 percent increase for ground services starting in urban areas, 3 percent for rural areas, and a 22.6 percent increase to the base rate for ground transports starting in the lowest quarter of rural areas by population density. The page says these add-ons run through December 31, 2027, and would expire on January 1, 2028 without new legislation (CMS Ambulance Fee Schedule). The add-ons follow the pickup ZIP code, so the origin address on the record affects the payment.
Why do ambulance claims fail review?
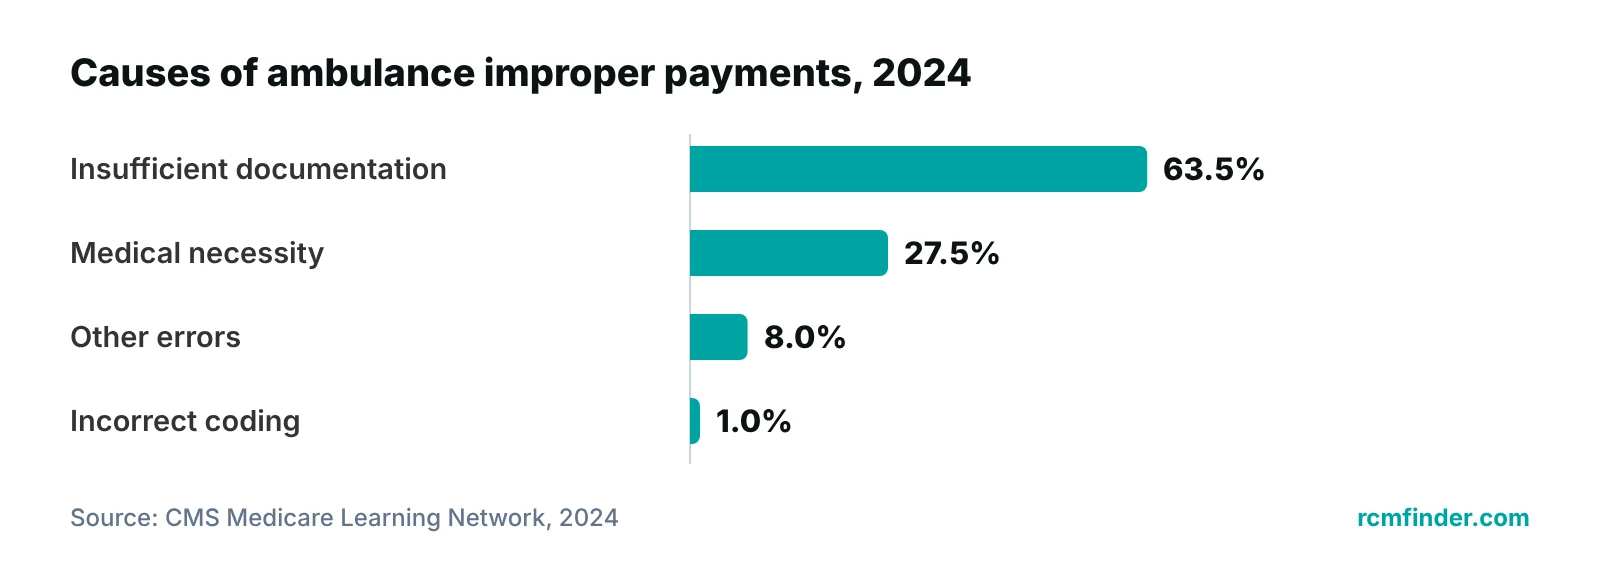
Most failures are paperwork failures. CMS reported a 13.2 percent improper payment rate for ambulance services in 2024, about $595.1 million in improper payments. Of those improper payments, 63.5 percent came from insufficient documentation and 27.5 percent from medical necessity problems (CMS). Incorrect coding was 1 percent.
Code lookup is the easy part. Three documentation problems follow directly from the CMS rules above:
- Thin run records: the report does not say why the patient could not travel any other way, or does not name the ALS intervention behind the level billed.
- Missing or late certification: a scheduled repetitive transport with no physician statement dated within 60 days of the service.
- Signature gaps: claims need a signature from the patient or an authorized representative. If the patient cannot sign, certain people, such as a legal guardian, may sign. When a representative signs, keep that documentation for at least four years from the date of service (CMS).
“I think the code is rarely the problem. The record behind the code is. If a reviewer cannot see why the patient needed an ambulance, the right A-code will not save the claim.”
— Awais Afzal, Healthcare Operations & Data Analyst
When a claim does get denied, work it with a defined process. Our denial management guide covers root-cause tracking, and our prior authorization guide explains how authorization works for services that need it. For the wider picture, see our posts on ambulance billing workflow tips and how ambulance billing services work. This post stays on Medicare codes, mileage and documentation.
Should you bill in-house, outsource or split the work?
Choose by volume, staff skill and how much your documentation varies from crew to crew. Be wary of any vendor that promises a fixed revenue uplift. Compare the models on the work you actually need done.
| Model | Works best when | Watch out for |
|---|---|---|
| In-house | Steady call volume, a trained biller and a crew that writes strong reports | Single-person risk if the biller leaves |
| Outsourced | Low volume, no billing expertise, or a backlog of unworked claims | You still own the patient care report quality; ask who handles appeals |
| Hybrid | Your team keeps charge capture and report review; a partner handles claim follow-up and denials | Unclear handoffs; agree on who owns each claim stage in writing |
Source: RCM Finder editorial comparison. No outcome data is implied.
If your ambulance service sits inside a hospital or a multi-service group, the billing may overlap with other departments. Our specialty billing pages show how we organize billing work by service line, and our emergency services billing guide covers the hospital side of emergency care. For hands-on help with claims, charge entry and follow-up, see our medical billing services.
Before you hire anyone, ask how they handle loaded mileage, origin and destination modifiers, certification statements and your patient care reports. Ask for a Business Associate Agreement before they see any patient data.
Not sure where your ambulance claims are losing money?
Our free practice audit reviews how your claims move from the patient care report to payment and shows where the gaps are. Pricing is quoted after the audit.
Our recommendations
- Audit ten recent claims against the run record. We recommend pulling ten paid and ten denied claims and checking each one: does the record show why other transport was unsafe, and does it support the level billed?
- Make mileage a required field. Do not allow a claim to leave without loaded miles in tenths. A blank unit field defaults to 0.1 and underpays the trip.
- Track certification dates for scheduled trips. For repetitive non-emergency transport, keep a calendar of the 60-day certification window for each patient. Do not wait for a denial to find an expired statement.
- Check your add-on eligibility by pickup ZIP. The urban, rural and super-rural add-ons follow the pickup ZIP code. Confirm that your system codes the origin correctly and that your MAC applies the add-on.
Bottom line
Ambulance billing is a two-part claim backed by a record that proves the patient needed the ride. Get the level, the loaded miles and the modifiers right, and make the patient care report do the proving. If your team needs help with claim follow-up, our medical billing services and denial management team can take part of that work. Start with a free practice audit, or talk to us.
Frequently asked questions
Is A0425 a CPT code?
No. A0425 is a HCPCS Level II code for ground mileage, per statute mile. CPT codes are owned by the AMA and cover physician and similar services. Ambulance A-codes are maintained as HCPCS Level II codes, and Medicare’s Chapter 15 lists them with the claim rules.
What is the difference between A0426 and A0428?
A0426 is a non-emergency ALS level 1 transport. A0428 is a non-emergency BLS transport. The difference is what the patient needed and what the crew did: ALS1 needs an ALS assessment by ALS personnel or at least one ALS intervention. BLS is ground transport by an EMT-Basic crew.
Can I bill mileage for the drive to the patient?
No. Medicare pays loaded mileage only, meaning the miles the patient is carried in the ambulance. The drive to the scene and the empty return trip are not billed. The base-rate code covers the response.
Does Medicare require a physician certification for every non-emergency transport?
No. A statement is required for scheduled, repetitive non-emergency transports, dated no earlier than 60 days before the service. For unscheduled trips of a facility resident under a physician’s care, it is due within 48 hours. Patients not under direct physician care do not need one.
Does a diagnosis code prove medical necessity?
No. The 837 professional claim format requires a diagnosis code, but Medicare’s manual says its presence is not a condition of ambulance payment policy. Necessity is judged from the patient care report and supporting records, so the record must describe the patient’s condition.
Which claim form do ambulance suppliers use?
Independent suppliers bill on the ASC X12 837 professional transaction or the CMS-1500. Institutional providers use the 837 institutional or the CMS-1450. Medicare no longer accepts the old CMS-1491 form. Confirm the format your MAC and your other payers require.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- 42 CFR 414.605 Ambulance definitions — CMS (current)
- 42 CFR 410.40 Coverage of ambulance services — eCFR (current)
- Ambulance Services (Medicare provider compliance tips) — CMS Medicare Learning Network (2024-2025)
- Medicare Claims Processing Manual, Chapter 15: Ambulance — CMS (current)
- Ambulance Fee Schedule Public Use Files — CMS (2026)
Disclaimer: This post is general educational information about revenue cycle operations. It is not legal, coding, billing-compliance or financial advice. Medicare rules, fee schedule amounts and add-on payments change, and other payers have their own policies. Confirm requirements with your Medicare Administrative Contractor, the payer and qualified advisors before acting.
