
Acute bronchitis ICD-10 coding starts at category J20, and J20.9 (acute bronchitis, unspecified) is the right code when the provider documents acute bronchitis without naming an organism. If the note says only "bronchitis", the code is J40. If the patient also has COPD, J44.0 is involved.
Most bronchitis coding errors are small. A provider writes “bronchitis” instead of “acute bronchitis”, a COPD flare gets a J20 code on its own, or a named virus is left on the chart but the claim carries J20.9. Each one can change the code, and the code is what the payer reads.
This guide reflects the FY2027 ICD-10-CM code set, which CDC lists as effective October 1, 2026 through September 30, 2027, and which CMS describes the same way. We could not open the FY2027 tabular file itself, so the code titles and notes below were checked against two public copies of the tabular list. The sources section says exactly what that means. It is general education for billing teams, not clinical advice.
Key takeaways
- J20 is a category with ten codes. J20.9 is the one for acute bronchitis with no organism documented.
- “Bronchitis” with no acute or chronic wording goes to J40, and J20 and J40 have Excludes1 notes against each other.
- Acute bronchitis in a patient with COPD points to J44.0, which carries a “code also” instruction for the infection.
- Allergic bronchitis NOS (J45.909) and bronchitis from chemicals or fumes (J68.0) are not J20 codes.
- The code follows the provider’s words. A coder who is unsure should send a query, not pick the closest code.
What does acute bronchitis ICD-10 category J20 cover?
J20 covers acute bronchitis, and it is a category, not a billable code. Ten subcodes sit under it, J20.0 through J20.9, and the choice between them depends on whether the provider names an organism. This is the same pattern as many ICD-10-CM categories: the category holds the concept and the last digit holds the detail.
The tabular list also gives J20 inclusion terms, so you do not need a separate code for these presentations: acute and subacute bronchitis with bronchospasm, with tracheitis, or with acute tracheobronchitis, and the fibrinous, membranous, purulent and septic forms. If a note says “acute tracheobronchitis” or “acute bronchitis with wheeze”, it is still J20.
On the clinical side, CDC’s chest cold page says a virus usually causes acute bronchitis and that symptoms last less than three weeks. For a coder that matters in one way only: the diagnosis comes from what the provider documents. A cough that lasts longer is a clinical question for the provider, not something to re-code from the billing side.
Each subcode names an organism. J20.9 is the code for when none is named. The next table lists all ten.
| Code | Title (organism) | Use it when the provider documents |
|---|---|---|
| J20.0 | Acute bronchitis due to Mycoplasma pneumoniae | Mycoplasma pneumoniae as the cause |
| J20.1 | Acute bronchitis due to Hemophilus influenzae | Hemophilus influenzae as the cause |
| J20.2 | Acute bronchitis due to streptococcus | Streptococcus as the cause |
| J20.3 | Acute bronchitis due to coxsackievirus | Coxsackievirus as the cause |
| J20.4 | Acute bronchitis due to parainfluenza virus | Parainfluenza virus as the cause |
| J20.5 | Acute bronchitis due to respiratory syncytial virus | RSV as the cause |
| J20.6 | Acute bronchitis due to rhinovirus | Rhinovirus as the cause |
| J20.7 | Acute bronchitis due to echovirus | Echovirus as the cause |
| J20.8 | Acute bronchitis due to other specified organisms | A specific organism that has no J20.0-J20.7 code |
| J20.9 | Acute bronchitis, unspecified | Acute bronchitis with no organism named |
Source: AAPC code lookup for J20 and RapidClaims codebook for J20, both mirrors of the ICD-10-CM tabular list (checked October 14, 2026). Code set: FY2027, effective October 1, 2026.
When is J20.9 the right choice?
J20.9 is right when the chart says acute bronchitis and does not name the cause. Typical wording is “acute bronchitis”, “acute bronchitis, viral”, or “acute bronchitis with cough”. “Viral” alone does not name a specific virus, so it does not unlock an organism code.
Do not move to an organism code because a test result or a visit reason hints at one. A positive test in the lab section, or “flu season” in the history, is not the provider linking that organism to the bronchitis. Code the organism only when the provider’s assessment ties it to the bronchitis. When the link is unclear, send a short query.
A short, neutral query works better than a leading one. For example: “Visit note says acute bronchitis and the lab shows a positive RSV result. Is the bronchitis due to RSV? Yes / No / Unable to determine.” The provider answers, the answer is saved with the chart, and the code follows the answer.
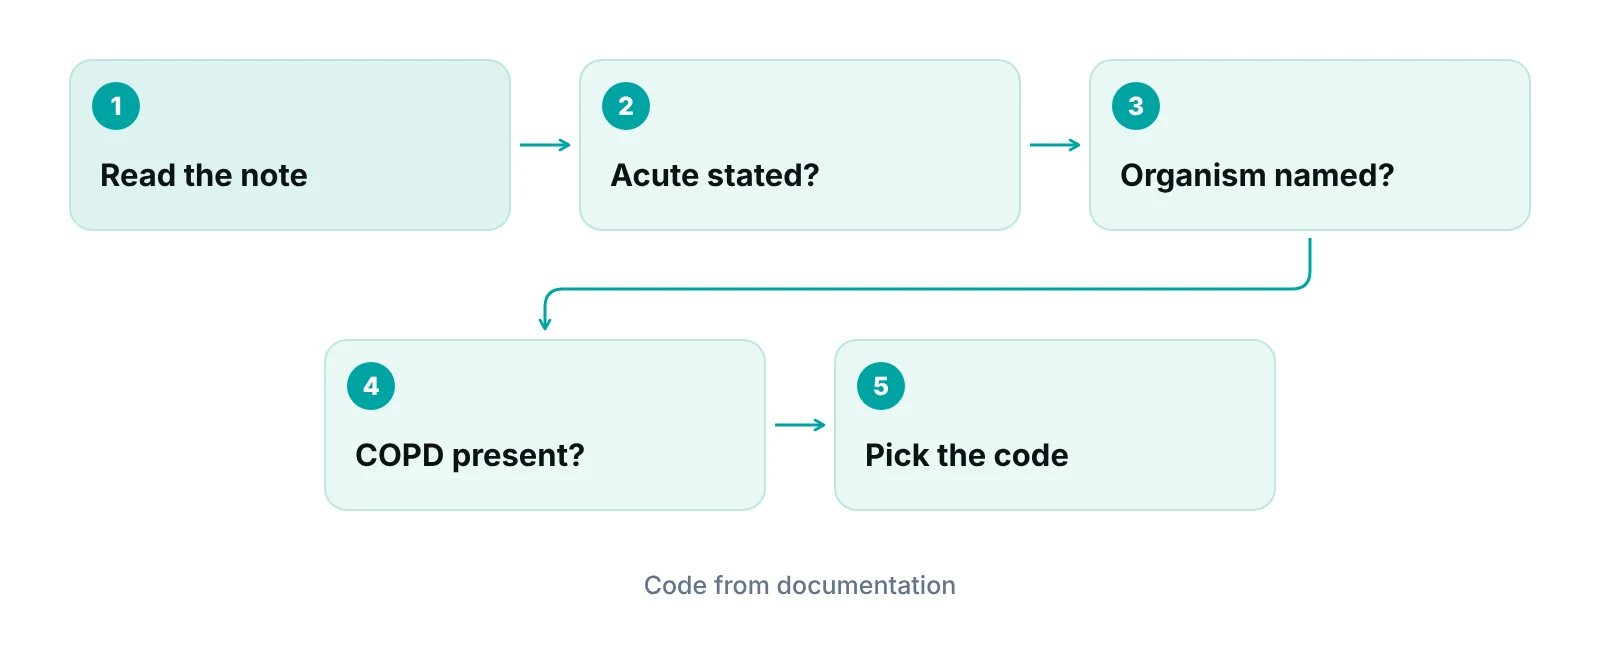
One more point on J20 versus its parent. The category J20 on its own is not reportable, so a claim that lists “J20” without the last digit is incomplete, and a claim scrubber that checks code validity should catch it; our clean claim checklist covers the other checks that belong in the same place.
J20.9 vs J40: acute bronchitis or just "bronchitis"?
If the provider writes “bronchitis” and nothing more, the code is J40, not J20.9. J40 is titled “Bronchitis, not specified as acute or chronic” and lists “bronchitis NOS”, “catarrhal bronchitis” and “tracheobronchitis NOS” as inclusion terms.
The two codes cannot be used together. J20 carries an Excludes1 note for bronchitis NOS and tracheobronchitis NOS (J40), and J40 carries an Excludes1 note for acute bronchitis (J20.-). Under the FY2027 guidelines an Excludes1 note means “not coded here” and the excluded code should never be used at the same time as the code above the note.
This is a documentation problem more than a coding one. Many templates default the assessment to “bronchitis”. The coder then has two bad options: guess “acute” from the visit reason, or report J40. J40 is the accurate code for what was written. If the visit was clearly an acute illness, the fix is a provider query and, over time, a template that asks for acute or chronic.
J40 also has its own “use additional code” list for tobacco: tobacco dependence (F17.-), tobacco use (Z72.0), history of tobacco dependence (Z87.891), and exposure to tobacco smoke codes (Z77.22, Z57.31, P96.81). J20 shows no such list in the copies we checked. Add the tobacco code when the provider documents it. It tells the payer more about the patient and costs nothing to report.
| What the provider wrote | Code family | Why |
|---|---|---|
| Acute bronchitis | J20.9 | Acute stated, no organism |
| Acute bronchitis due to RSV | J20.5 | Organism named and linked |
| Bronchitis | J40 | Acute or chronic not stated |
| Acute bronchitis, patient has COPD | J44.0 plus the infection | COPD with acute lower respiratory infection |
| Allergic bronchitis | J45.909 | Allergic bronchitis NOS is excluded from J20 and J40 |
Source: ICD-10-CM tabular notes for J20, J40 and J44.0 as shown by AAPC and RapidClaims (checked October 14, 2026); code set FY2027.
What if the patient has COPD? Understanding J44.0
Acute bronchitis in a patient with COPD is not coded with J20.9 alone. J20 lists “acute bronchitis with chronic obstructive pulmonary disease (J44.0)” and “acute bronchitis with chronic obstructive asthma (J44.0)” in its Excludes2 notes, which sends those cases to J44.0.
J44.0 is titled “Chronic obstructive pulmonary disease with (acute) lower respiratory infection”. It carries a “code also” note: code also to identify the infection. Under J44 as a whole there is a second “code also” note for the type of asthma, if applicable (J45.-).
Now the Excludes2 point, because it changes what you can report. An Excludes2 note means “not included here”: the excluded condition is not part of the condition in the code, and a patient may have both. So the J20 note does not say “never report J20 with J44.0”. It says J20 does not cover the COPD case, and J44.0 plus its “code also” instruction does. How to report the infection code on a given claim, and in what order, is for the Chapter 10 guidelines and the Index. We could not read that chapter of the FY2027 guidelines, so check it before you build a rule around it.
For deeper COPD detail, including exacerbation and the J44 subcodes, see our COPD ICD-10 coding guide. Keep J44.0 in mind for older patients, long-term smokers and anyone whose problem list shows emphysema or chronic bronchitis. If COPD is on the problem list but the note never mentions it, query before you assume it is part of this visit.
Bronchitis that is not a J20 code
Several bronchitis types sit outside J20 on purpose. J20 lists them in its Excludes2 note so the coder is sent elsewhere. This is the list worth knowing for respiratory claims.
| Documentation says | Go to | Note |
|---|---|---|
| Allergic bronchitis NOS | J45.909 | Also excluded from J40 (Excludes1) |
| Bronchitis from chemicals, fumes or vapors | J68.0 | Also excluded from J40 |
| Chronic bronchitis NOS | J42 | Chronic, not acute |
| Chronic simple bronchitis | J41.0 | Chronic, simple |
| Chronic mucopurulent bronchitis | J41.1 | Chronic, mucopurulent |
| Chronic obstructive bronchitis or tracheobronchitis | J44.- | COPD family |
| Acute bronchitis with bronchiectasis | J47.0 | Bronchiectasis involved |
Source: Excludes2 note under J20 in the FY2027 ICD-10-CM tabular list, as shown by AAPC and RapidClaims (checked October 14, 2026).
J40 also has Excludes1 notes for allergic bronchitis NOS (J45.909), asthmatic bronchitis NOS (J45.9-) and bronchitis due to chemicals, gases, fumes and vapors (J68.0). These are Excludes1, so if one of those is the diagnosis, J40 is the wrong code. Asthmatic bronchitis is a common source of trouble because it sounds like a bronchitis code and is not one.
What about COVID-19 and acute bronchitis?
Acute bronchitis confirmed as due to COVID-19 uses two codes. The FY2027 official guidelines, in the COVID-19 section, say to assign U07.1 and J20.8 for a patient with acute bronchitis confirmed as due to COVID-19.
Note the word “confirmed”. The guideline covers a provider’s confirmed link between the bronchitis and COVID-19. A positive COVID-19 test in a patient who also has a cough is not the same thing, so the documentation still has to connect the two. If it does not, the query rule from earlier applies.
The reason J20.8 appears here is simple: COVID-19 virus is not one of the seven named organisms, so it falls under “other specified organisms”. The same logic applies to any other organism the provider names that has no code of its own at J20.0-J20.7.
Where bronchitis coding goes wrong on the claim
Bronchitis errors often start in the chart, not with the coder. Four patterns are worth checking for.
- Template default. The assessment auto-fills “bronchitis” and the claim goes out as J40 for an acute visit.
- Organism left on the chart. The provider names the cause in the note, but the claim carries J20.9 because the coder reads only the diagnosis field.
- COPD missed. The note says acute bronchitis, the problem list says COPD, and the claim carries J20.9.
- Wrong bronchitis type. Allergic or asthmatic bronchitis goes out as J20.9 or J40 even though both are excluded.
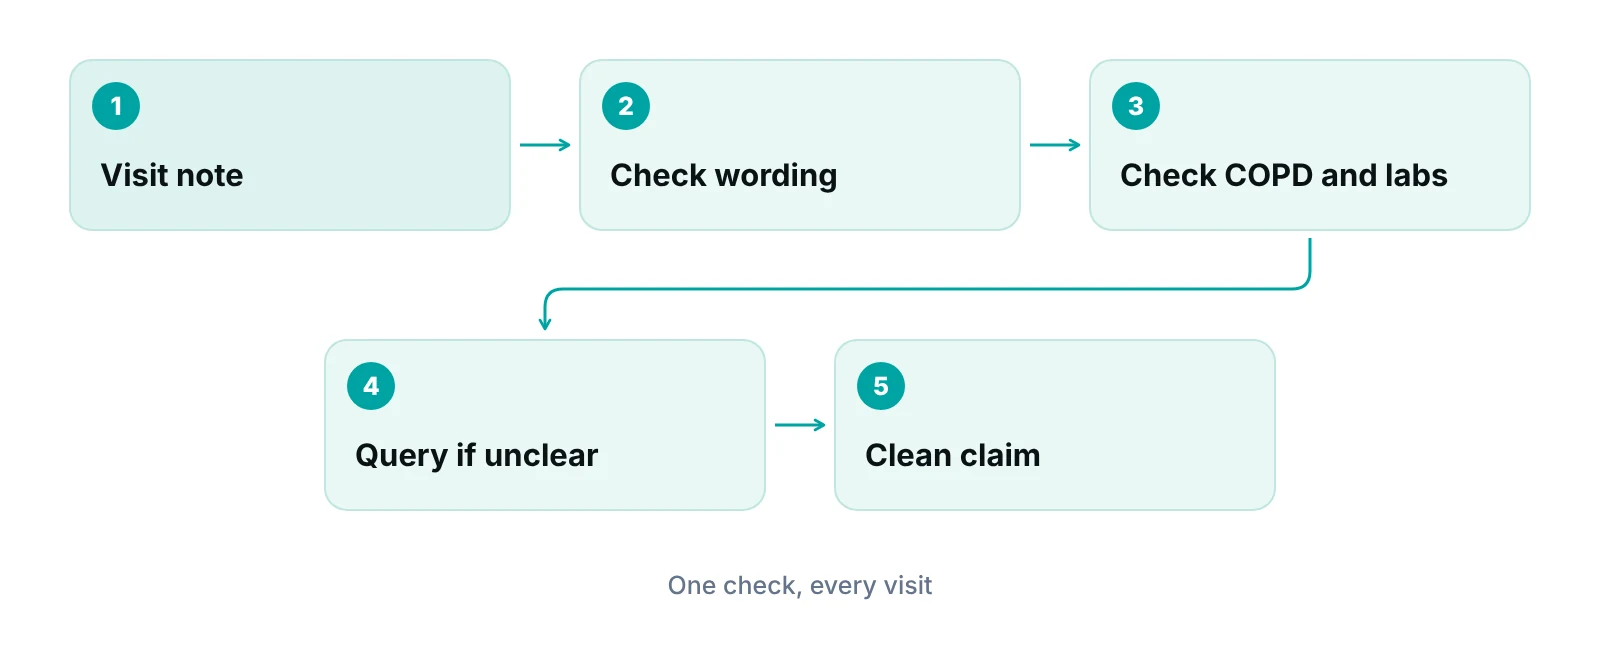
None of these needs advanced coding skill to fix. They need a clear process: the coder checks the assessment wording, the problem list and the lab section on every respiratory visit, and queries when they disagree.
Primary care and urgent visits see most of this volume, so family practice billing and coding support is where the habit pays off fastest. The same checks hold in any specialty that treats respiratory visits. If your team wants a second pair of eyes on diagnosis capture and claim edits, our medical billing and coding support works inside your existing EHR (for example PrognoCIS, eClinicalWorks or athenahealth). If you have a specific coding question, you can contact our team.
Want a second look at your respiratory claims?
A free practice audit reviews how diagnosis codes move from the chart to the claim, and where they get stuck.
A diagnosis code that does not match the documentation, or that is excluded by a tabular note, can also be the start of a payer question. How a denial is worked, and how to tell a coding error from a payer policy issue, is covered in our guide to medical billing denial management. For the broader picture of how ICD-10 sits beside CPT and HCPCS, read how ICD-10, CPT and HCPCS codes work together, and for further worked examples see our medical coding examples.
“I would rather a coder send one polite query than guess the nearest code. A guessed code still has to be defended later.”
— Awais Afzal, Healthcare Operations & Data Analyst
Our recommendations
- Build a three-line bronchitis check into coding review. For every respiratory visit, the coder reads the assessment wording, the problem list and the lab section before choosing J20.x, J40 or J44.0. It takes under a minute and catches most of the patterns above.
- Ask providers to write "acute" or "chronic". If your template defaults the assessment to plain “bronchitis”, change it. That one edit removes most J40 claims for acute visits.
- Write one standard query for organisms. Use a short yes, no or unable-to-determine question and keep the answer with the chart. Consistent queries are easy for providers to answer and easy to defend later.
- Add a COPD flag to your respiratory claim review. If COPD is on the problem list, stop and check the note before J20.9 goes out. Use J44.0 guidance where the documentation supports it.
- Re-check the code set each October. Codes, titles and notes can change at the start of each federal fiscal year, on October 1. Confirm the J20, J40 and J44 entries again when the new tabular list is released, and update your cheat sheets the same week.
Bottom line
Acute bronchitis ICD-10 coding comes down to wording. “Acute bronchitis” with no organism is J20.9, a named organism points to J20.0-J20.8, plain “bronchitis” is J40, and acute bronchitis with COPD brings in J44.0 and its “code also” instruction. When the chart and the code disagree, query the provider rather than guess. If denials tied to diagnosis codes are costing your team time, our denial management services can help find where they start. You can also use the revenue calculator to size what unpaid claims cost your practice.
Frequently asked questions
What is the ICD-10 code for acute bronchitis?
Acute bronchitis is in category J20. J20.9 (acute bronchitis, unspecified) is the code when the provider documents acute bronchitis and does not name an organism. If an organism is documented as the cause, use J20.0 through J20.8. The category J20 on its own is not reportable.
When should I use J20.9 instead of J40?
Use J20.9 when the provider documents “acute bronchitis”. Use J40 when the provider writes only “bronchitis”, with no acute or chronic wording. The two have Excludes1 notes against each other, so they should not be reported together. If the note is unclear, query the provider.
Can I code J20.9 with J44.0 for a COPD patient?
J20 lists acute bronchitis with COPD under its Excludes2 note and points to J44.0, which has a “code also” instruction to identify the infection. Excludes2 allows both conditions to be reported when both are present. Check the Chapter 10 guidelines and the Index for the exact reporting rule before you set a billing rule.
Which code is used for acute bronchitis due to COVID-19?
The FY2027 official guidelines say to assign U07.1 and J20.8 for acute bronchitis confirmed as due to COVID-19. The provider must link the bronchitis to COVID-19 in the documentation. A positive test alone is not that link, so query the provider if the connection is not stated.
Is allergic bronchitis coded as J20.9?
No. Allergic bronchitis NOS is listed as J45.909 in the Excludes notes at J20 and J40, so neither code fits. Asthmatic bronchitis NOS (J45.9-) is also excluded from J40. Code these from the provider’s exact words and check the J45 entries in the tabular list.
Which ICD-10-CM code set year applies to bronchitis coding now?
The FY2027 code set, effective October 1, 2026 through September 30, 2027, applies to encounters in that window. CDC and CMS both list it. Encounters before October 1, 2026 use the FY2026 code set. Confirm entries each October, since titles and notes can change.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- ICD-10-CM files and code set years (FY2027, FY2026) — CDC / NCHS (2026)
- ICD-10 Codes page, 2027 ICD-10-CM files — CMS (2026)
- FY 2027 ICD-10-CM Official Guidelines for Coding and Reporting — CMS (2026)
- ICD-10-CM J20 Acute bronchitis (tabular mirror) — AAPC (2026)
- ICD-10-CM J40 Bronchitis, not specified as acute or chronic (tabular mirror) — AAPC (2026)
- ICD-10-CM J44.0 COPD with (acute) lower respiratory infection (tabular mirror) — AAPC (2026)
- J20 Acute bronchitis codebook page — RapidClaims (2026)
- J44.0 codebook page — RapidClaims (2026)
- Chest Cold (Acute Bronchitis) Basics — CDC (2026)
Disclaimer: This post is general educational information about revenue cycle operations. It is not legal, coding, billing-compliance or clinical advice. ICD-10-CM codes, titles and notes change each fiscal year and payer rules vary. Code from the provider's documentation and confirm entries against the official tabular list and guidelines for the date of service.
