
Medicare mental health reimbursement for therapy in 2026 follows the physician fee schedule: relative value units for the code, adjusted for your locality, multiplied by a conversion factor of $33.40, or $33.57 for qualifying APM participants. There is no single national rate for a session, so price your own locality.
The old version of this article predicted a 14 percent drop for 2025 and printed a state table. Neither held up when checked against CMS, so both are gone. This update is built from CMS and Medicare contractor pages and shows you how to work out your own number. It is written for therapists, psychiatrists and practice managers who bill Medicare Part B and want to budget with figures they can defend. If you are newer to the codes, start with our mental health CPT codes guide.
Key takeaways
- The 2026 Medicare conversion factor is $33.40 for most clinicians and $33.57 for qualifying APM participants, up from about $32.35 in 2025.
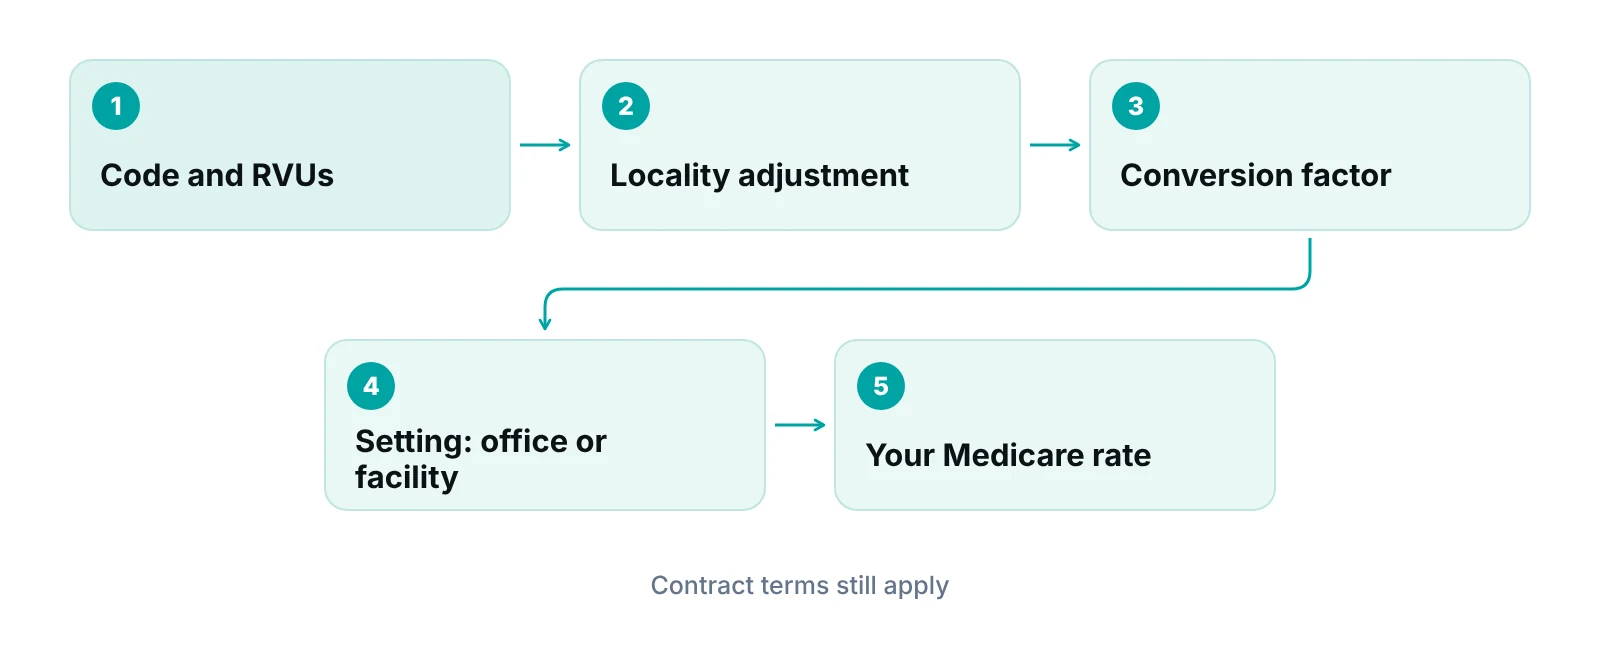
- A session’s payment is relative value units times your locality adjustment times the conversion factor, so two practices can be paid different amounts for the same code.
- Psychotherapy codes are chosen by documented time: 90832 for 16 to 37 minutes, 90834 for 38 to 52 and 90837 for 53 or more.
- Medicare telehealth for mental health is in place through December 31, 2027, with an in-person visit rule starting after that date.
- Check any article that prints one dollar figure per code. Look up your own locality in the CMS fee schedule files.
What Medicare pays for therapy in 2026
Medicare pays for psychotherapy under the Medicare Physician Fee Schedule. CMS sets one conversion factor for the year, and that number turns every code’s relative value units into dollars. For 2026, the CMS final rule fact sheet gives $33.40 as the conversion factor for clinicians who are not qualifying alternative payment model (APM) participants and $33.57 for those who are. CMS describes both against a current conversion factor of $32.35.
| Measure | Amount | Change from $32.35 |
|---|---|---|
| 2025 conversion factor (CMS ‘current’) | $32.35 | Baseline |
| 2026, not a qualifying APM participant | $33.40 | +$1.05 (+3.26%) |
| 2026, qualifying APM participant | $33.57 | +$1.22 (+3.77%) |
Source: CMS, CY 2026 Medicare Physician Fee Schedule final rule fact sheet (2025).
That is an increase, not the cut described in the old article. The fact sheet says the 2026 figure includes a one-year increase of 2.50 percent set by statute. CMS also finalized an efficiency adjustment of minus 2.5 percent for 2026. It applies to services that are not time-based. The fact sheet lists time-based codes as exempt, naming evaluation and management services, care management, behavioral health and services on the telehealth list. Most psychotherapy codes are defined by time, but check the exempt-code list for each code you bill rather than assuming.
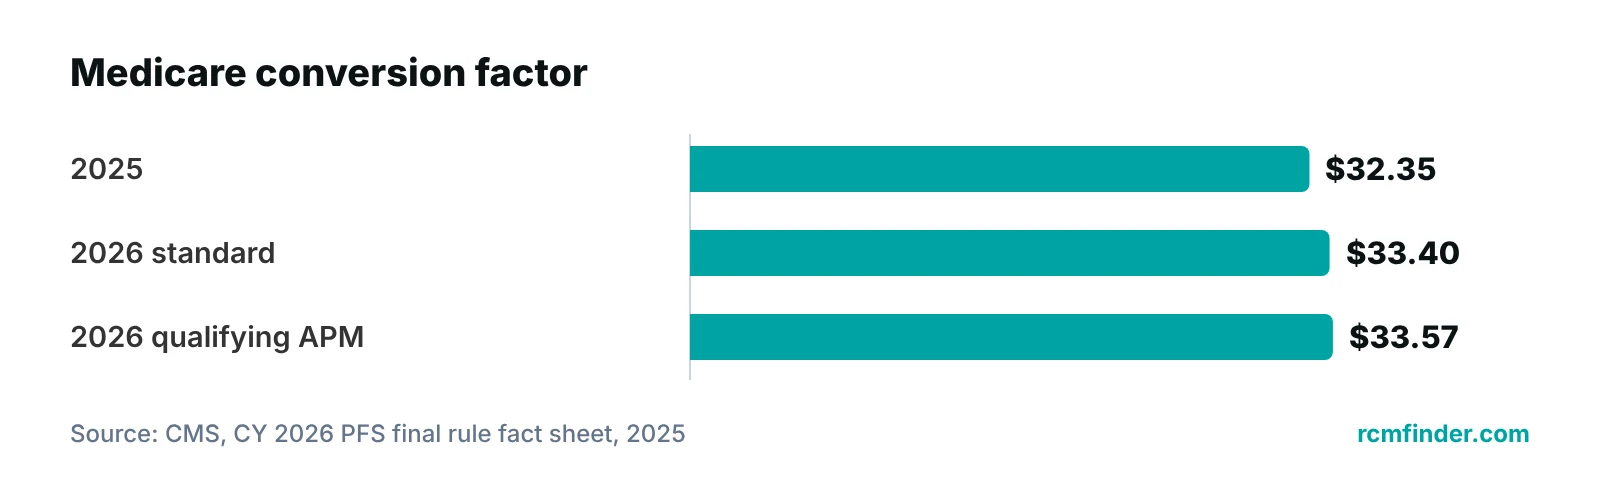
A higher conversion factor does not mean every code rises by the same amount. The relative value units behind each code also change, and the fact sheet mentions an estimated adjustment for work RVU changes. Treat the conversion factor as one input, then look up the codes you bill.
How the payment for one session is built
Each code has relative value units for physician work, practice expense and malpractice. CMS adjusts each part for the geographic practice cost index of your locality, adds them up, and multiplies by the conversion factor. That is why a published national average does not predict your check.
Three reasons your rate differs from a national figure
- Locality. Payment varies by Medicare locality, so the same code pays differently in different areas.
- Setting. Non-facility and facility payment amounts are separate. CMS pays home-based telehealth claims at the non-facility rate, as its telehealth FAQ explains for place of service 10.
- Clinician status. Since January 1, 2026, CMS publishes separate payment files for qualifying APM participants and everyone else, per its 2026 national payment amount file page.
To get your number, use the CMS Physician Fee Schedule look-up tool or download the national payment amount file, choose the non-qualifying file unless you are a qualifying APM participant, and read the amount for your locality and setting. Run this for each psychotherapy code you bill and keep the date you checked.
Be careful with single dollar figures
A figure labeled as the Medicare rate for a code is only useful if it names the year, the locality, the setting and the file it came from. Without those four details, do not budget with it. This article does not print per-code dollar amounts for that reason.
Which psychotherapy code you bill, and how time decides it
The three standard psychotherapy codes are picked by the documented minutes of face-to-face psychotherapy. Medicare contractor Noridian lists the ranges below, and states that psychotherapy should not be billed for sessions under 16 minutes. For a deeper look at two of them, see our guide to CPT codes 90834 and 90837.
| Code | Service (our wording) | Time or rule | Billing note |
|---|---|---|---|
| 90791 | Psychiatric diagnostic evaluation | Once per day | Not on the same day as an E/M by the same individual for the same patient |
| 90832 | Psychotherapy, about 30 minutes | 16 to 37 minutes | Document exact minutes |
| 90834 | Psychotherapy, about 45 minutes | 38 to 52 minutes | Document exact minutes |
| 90837 | Psychotherapy, about 60 minutes | 53 minutes or more | Document exact minutes |
| 90833, 90836, 90838 | Add-on psychotherapy with an E/M visit | Time of the psychotherapy portion | E/M and psychotherapy must both be significant and separately identifiable |
| 90839 | Crisis psychotherapy, first hour | First 60 minutes | Billed once per day and not alongside other psychotherapy codes |
Source: Noridian Healthcare Solutions, Mental Health (JF Part B); CGS Medicare, Psychotherapy checklist.
A few rules cause most avoidable denials. Document the actual time spent on psychotherapy separately from any E/M time. CGS tells providers to pick the code closest to the time in the code descriptor and to record exact times in the chart. Interactive complexity (90785) can be added to psychotherapy codes 90832 through 90838 when communication factors complicate the session, and the note should show those factors.
A usable therapy note also carries the patient name, date of service, session length, mental status, interval history, interventions used, progress or regression, and the treatment plan or diagnosis, with a legible signature and credentials. Noridian lists the same elements and names “cannot bill less than 16 minutes” as a common error found in CERT reviews.
Who can bill Medicare for therapy
Noridian’s page lists psychiatrists and other physicians, clinical psychologists, nurse practitioners, physician assistants, clinical nurse specialists and licensed clinical social workers among those who can bill. It says staff such as registered nurses, counselors and some other clinicians cannot enroll or bill Medicare directly, and that qualified non-physician practitioners can work incident to or bill independently. Enrollment rules for other provider types change, so confirm yours with your Medicare Administrative Contractor.
Incident-to billing has its own supervision and documentation rules. Read our Medicare incident-to billing guide before you rely on it for a therapist who is not enrolled. If you are building a practice around these services, our behavioral and mental health billing and operations page shows how the front end, coding and follow-up fit together.
Enrollment also decides which payers you can see at all. If you are adding clinicians, our therapist insurance credentialing guide covers the payer side.
Telehealth for therapy: the dates to plan around
Medicare telehealth for behavioral health is available now and has a dated change coming. The CMS telehealth FAQ says beneficiaries can receive Medicare telehealth services anywhere through December 31, 2027. Starting January 1, 2028, most services will be limited to medical facilities in rural areas, with behavioral health services excepted. CMS also says behavioral health telehealth in the home is allowed, and Noridian lists place of service 02 and 10 as covered for the psychotherapy codes.
| Date | What CMS says | What to do |
|---|---|---|
| Through Dec 31, 2027 | Medicare telehealth services can be received anywhere; audio-only home services continue | Keep documenting modality and place of service on every visit |
| After Dec 31, 2027 | An in-person visit within 6 months before the first mental health telehealth service | Plan how you will schedule that visit for new telehealth patients |
| After Dec 31, 2027 | Patients who began mental health telehealth at home on or before that date need an in-person visit every 12 months, per CMS | Build a yearly in-person reminder into your workflow |
| Jan 1, 2028 | Physical therapists, occupational therapists, speech-language pathologists and audiologists can no longer furnish Medicare telehealth | Matters if your group includes those clinicians |
Source: CMS, Medicare Telehealth FAQ (updated 2026).
Dates in this area have moved before, so check the CMS FAQ again before you set a policy. For modifiers and place-of-service coding, see our telehealth billing guide.
Not sure what your Medicare mix is worth?
Enter your visit volume and payer mix to see where revenue may be leaking before you plan for 2026 rates.
How to budget with the 2026 rate
Budgeting from the fee schedule is a short checklist. It takes an hour or two the first time, and a few minutes each January after that.
- Pull the non-qualifying (or qualifying) payment file for your locality and read the amounts for 90791, 90832, 90834 and 90837 in the setting you bill.
- Multiply by the number of each code you billed last year to get a Medicare-only revenue estimate.
- Compare that estimate with what the remittance advice actually paid. A gap is a payment-posting or coding question, not a fee schedule question.
- Separate Original Medicare from Medicare Advantage in your reports. Advantage plans pay under their own contracts, so the fee schedule is not your rate for those patients.
- Record the file name and date you used so the next review starts from the same point.
“A rate you cannot trace to a file, a locality and a date is an assumption, not a budget.”
Once you know the expected amount, the work is catching claims that pay less. A practice management system that tracks claims by stage can flag a payment that comes in under the expected amount. See our practice management system that tracks claims by stage for how that works. If the volume is more than your front desk can follow, medical billing services cover charge entry, claims and follow-up.
Also look at the new 2026 behavioral health items in the CMS fact sheet. It lists three new add-on G-codes that can be billed with the advanced primary care management base code in the same month, covering behavioral health integration and the psychiatric Collaborative Care Model, and it extends digital mental health treatment device payment to devices that treat ADHD. These apply to specific setups, so confirm eligibility before you plan around them. Our behavioral health billing and RCM guide covers the wider billing picture.
Want a second reader on your Medicare therapy claims?
Our free practice audit looks at how your Medicare behavioral health claims are coded, paid and followed up.
Our recommendations
- Price from the CMS file, not from articles. Download the national payment amount file for your locality and setting, and save it with the date. Re-check it each January and whenever CMS posts a revised file.
- Document minutes for every session. Add a field for psychotherapy start and stop time to your note template. Time decides the code, and missing minutes invite a downcode or a denial.
- Keep E/M and psychotherapy time apart. When a visit has both, record the time of each service separately so both are supported.
- Compare expected and paid amounts monthly. Sample remittances for your four most-billed codes. A repeated shortfall points to a coding, modifier or enrollment issue worth fixing.
- Write a telehealth policy with the 2027 date in it. Record which patients started telehealth at home, the date they started, and when each last had an in-person visit.
- Verify the provider type before billing under a clinician. Confirm each clinician’s Medicare enrollment status before you submit claims in their name.
Track each Medicare therapy claim by stage, with an owner.
Our practice management system tracks claims by stage and flags underpayments against the expected amounts you set, so a mismatch with your fee schedule lookup is visible early. It also runs completeness checks before submission.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Medicare mental health reimbursement in 2026 comes down to a formula you can check yourself: the code’s relative value units, your locality, and a conversion factor of $33.40 or $33.57. Use the CMS files for your number, document time on every session, and watch the telehealth dates. If you want a second reader on your Medicare therapy claims, see our denial management services and our end-to-end revenue cycle management, or ask for a free practice audit.
Frequently asked questions
How much does Medicare pay for a therapy session in 2026?
There is no single national amount. Medicare multiplies the code’s relative value units, adjusted for your locality, by the 2026 conversion factor of $33.40, or $33.57 for qualifying APM participants. Look up your locality and setting in the CMS fee schedule files for the exact dollar figure and keep the date you checked.
Did Medicare cut mental health reimbursement for 2026?
CMS describes the 2026 conversion factor as an increase over the current $32.35, which includes a one-year 2.50 percent statutory increase. It also finalized a minus 2.5 percent efficiency adjustment for services that are not time-based, and lists time-based and behavioral health codes as exempt. Check your specific codes against CMS’s list.
Which Medicare codes cover a 30, 45 and 60 minute therapy session?
Medicare contractors list 90832 for 16 to 37 minutes, 90834 for 38 to 52 minutes and 90837 for 53 minutes or more. Do not bill psychotherapy for a session under 16 minutes. Document the exact minutes in the chart so the code is supported if the claim is reviewed.
Can a practice bill Medicare for telehealth therapy in 2026?
Yes. CMS says beneficiaries can receive Medicare telehealth services anywhere through December 31, 2027, and behavioral health telehealth in the home is allowed. After that date an in-person visit requirement applies to mental health telehealth. Dates have changed before, so confirm them in the CMS telehealth FAQ.
Is the Medicare Advantage rate the same as the fee schedule?
Not necessarily. Medicare Advantage plans pay providers under their own contracts, so the fee schedule may not be what you are paid. Check your contract and remittances for those patients, and report Original Medicare and Medicare Advantage separately when you review revenue.
Who can bill Medicare for psychotherapy?
Noridian lists psychiatrists and other physicians, clinical psychologists, nurse practitioners, physician assistants, clinical nurse specialists and licensed clinical social workers among billers. Clinicians who cannot enroll with Medicare cannot bill directly. Confirm your provider type and enrollment with your Medicare Administrative Contractor before you submit claims.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Calendar Year (CY) 2026 Medicare Physician Fee Schedule Final Rule (CMS-1832-F) fact sheet — CMS (2025)
- Medicare Telehealth FAQ (updated 2026) — CMS (2026)
- Mental Health – JF Part B — Noridian Healthcare Solutions (2026)
- Psychotherapy checklist — CGS Administrators (2026)
- PFS National Payment Amount File PFREV26A — CMS (2026)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. CPT is a trademark of the American Medical Association, and the code descriptions here are our own summaries. Medicare payment figures, telehealth dates and payer rules change, and your Medicare Administrative Contractor and contract terms control what you are paid. Check current CMS and contractor sources before you bill or budget.
