
Mental health CPT codes are chosen by service, E/M pairing and documented minutes. Evaluation uses 90791 or 90792, stand-alone therapy uses 90832, 90834 or 90837, and therapy with a medical visit uses add-ons 90833, 90836 or 90838. The note must show the time.
Many code lists online mix up add-ons, group timing, health behavior codes and telehealth. This guide is written for practice managers and billers who need to decide how to code, and when to ask for help.
Key takeaways
- Pick the code from the service delivered, whether an E/M visit was billed, and the documented minutes.
- Psychotherapy bands are 16 to 37, 38 to 52 and 53 or more minutes; under 16 minutes is not reported.
- Add-ons 90833, 90836 and 90838 need an E/M visit and separately recorded therapy time.
- Telehealth uses the same codes; place of service and payer modifiers carry the difference.
- Health behavior codes 96150 to 96155 were replaced in 2020 and are not substance use codes.
What are mental health CPT codes?
They are the five-digit procedure codes that a practice puts on a claim to say what a behavioral health clinician did: an evaluation, a therapy session, a crisis visit, a family or group session, or a round of testing. The American Medical Association (AMA) owns and updates the code set, so this guide describes each code in plain words and does not reproduce the official wording.
Most mental health claims come from a short list. Think of it as seven families: diagnostic evaluation, individual psychotherapy, psychotherapy add-ons that ride on a medical visit, interactive complexity, crisis psychotherapy, family and group psychotherapy, and psychological testing. A few older health and behavior codes are also worth knowing about because they still show up in outdated code lists.
This guide builds the list from Medicare contractor pages, psychiatric and psychological association guidance and CMS and HHS telehealth pages. Where a point could not be confirmed from a primary page, it says so.
Which clinician are you?
The right code family depends on who delivers the service. A therapist or psychologist who does not report medical visits uses the stand-alone psychotherapy codes. A psychiatrist, physician, nurse practitioner or physician assistant who also reports a medical visit may use the add-on psychotherapy codes. The next section shows the split.
How do you choose the right mental health CPT code?
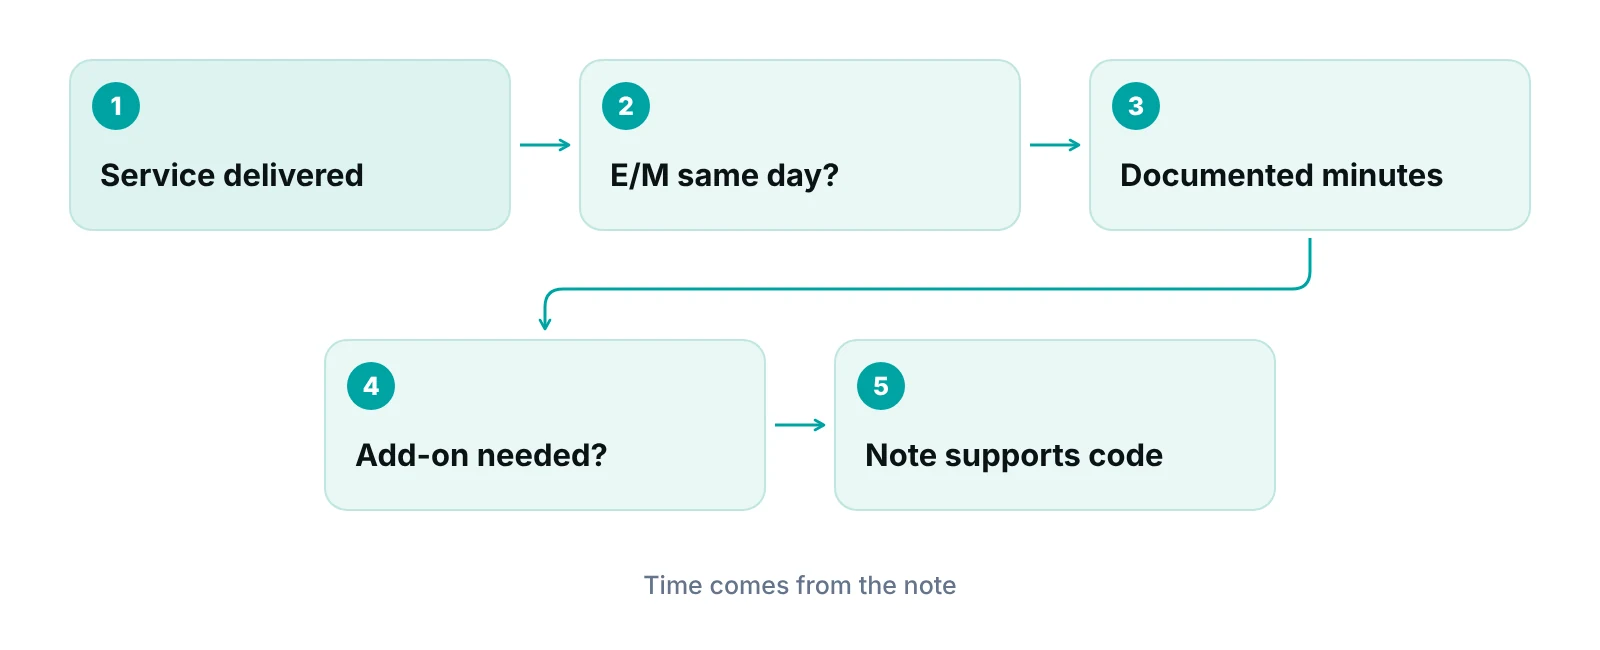
Answer three questions in order: what service was delivered, whether a medical evaluation and management (E/M) visit was part of the same encounter, and how many minutes of the service were documented. The code follows from those answers, not from what the practice usually bills.
- What was the service? Diagnostic evaluation, psychotherapy, crisis, family, group or testing.
- Was a medical E/M visit billed the same day by the same clinician? If yes, the psychotherapy is reported with an add-on code. If no, it is reported with a stand-alone code.
- How many minutes of psychotherapy are documented? Pick the code whose time band the note supports.
Time is where most coding errors start. CGS Administrators (2021 fact sheet) says psychotherapy is not reported for fewer than 16 minutes, that the code closest to the documented time should be chosen, and that exact times must be recorded in the medical record. First Coast Service Options gives the same bands for the Medicare psychotherapy codes (page reviewed in 2026).
| Code | Used for | Time basis | Main rule |
|---|---|---|---|
| 90791 | Psychiatric diagnostic evaluation, no medical services | Not time-based | Report once per day; not the same day as an E/M by the same clinician |
| 90792 | Psychiatric diagnostic evaluation with medical services | Not time-based | Same once-per-day limit; adds a medical assessment |
| 90832 | Individual psychotherapy, stand-alone | 16 to 37 minutes | No more than one unit in most settings |
| 90834 | Individual psychotherapy, stand-alone | 38 to 52 minutes | No more than one unit in most settings |
| 90837 | Individual psychotherapy, stand-alone | 53 minutes or more | No more than one unit in most settings |
| 90846 | Family psychotherapy without the patient present | Contractor lists 50 minutes, midpoint of 26 | Primary purpose must be treating the patient’s condition |
| 90847 | Family psychotherapy with the patient present | Contractor lists 50 minutes | Can be reported with 90832 to 90838 only as a separate, distinct service in a separate time interval |
| 90853 | Group psychotherapy | Contractor describes typically 45 to 60 minutes | One contractor caps groups at 10 participants |
Source: First Coast Service Options (2026), Noridian Healthcare Solutions (2026), CGS Administrators (2021), American Psychiatric Association (2013). Medicare contractor rules; other payers differ.
Which code covers the first visit: 90791 or 90792?
Use 90791 for a diagnostic evaluation with no medical services and 90792 when the evaluation includes a medical assessment. Noridian Healthcare Solutions describes 90792 as adding the medical assessment or physical exam piece to the evaluation.
Both are untimed. CGS Administrators lists the required elements as a complete medical and psychiatric history, a mental status exam, an initial diagnosis, an evaluation of the patient’s ability to respond to treatment and an initial treatment plan. The same fact sheet says to report the evaluation once per day and not on the same day as an E/M service by the same clinician for the same patient.
Some patients need a new evaluation later in the year. Noridian says 90791 or 90792 may be reported more than once per year when there is a separate evaluation. Document why the new evaluation was needed, because a repeat code with no explanation is an easy payer edit.
If the evaluation also needs a second person to help the patient communicate, such as a parent or an interpreter, that may call for interactive complexity. It is covered in the add-on section below. For how the wider behavioral health billing process fits around the first visit, see our guide to behavioral health eligibility verification.
How do the psychotherapy time bands work for 90832, 90834 and 90837?
Each stand-alone psychotherapy code has a time band, not a fixed length. First Coast Service Options lists 90832 as 16 to 37 minutes, 90834 as 38 to 52 minutes and 90837 as 53 minutes or longer. A 45-minute session therefore sits in the middle band, and a 36-minute session stays in the 30-minute code.
Psychotherapy time can include family members who are present as informants. The American Psychiatric Association’s 2013 CPT overview says psychotherapy time counts time with the patient and/or a family member, not only time face to face with the patient alone. The Medicare checklist adds that the patient must be present for all or part of the session.
Medicare contractors also limit units. First Coast says 90832 to 90834 and 90836 to 90838 should not be reported with more than one unit, except in place of service 52 (partial hospitalization), and that claims with more than one unit have been denied outside that setting since July 1, 2022. A long session is reported by choosing the higher band, not by adding units.
“The code is a summary of the note. If the note cannot show the minutes, the code is not safe to submit.”
Dedicated explainers exist for the codes practices ask about most. See the 90832 guide for the 30-minute band, and the guide to CPT 90834 and 90837 for the longer sessions.
What are add-on codes like 90833, 90836, 90838 and 90785?
Add-on codes cannot be billed alone. The three psychotherapy add-ons mirror the stand-alone time bands but are reported with an E/M visit. First Coast Service Options lists 90833 as 16 to 37 minutes, 90836 as 38 to 52 minutes and 90838 as 53 minutes or longer, and lists the eligible E/M families as 99202 to 99255, 99304 to 99337 and 99341 to 99350.
Some lists describe 90833 and 90838 only as 30- and 60-minute add-ons. That is incomplete. They are tied to the E/M visit, they need their own documented minutes, and CGS Administrators says they must be submitted with an E/M service by a physician or nonphysician practitioner. The E/M and the psychotherapy have to be significant and separately identifiable, as First Coast puts it.
Time is kept apart. Noridian says psychotherapy time must be documented separately from E/M time, not as one combined total. See the 90836 guide for a worked pairing.
Interactive complexity (+90785) is a different kind of add-on. It does not depend on minutes. The CGS fact sheet says it can be billed with any psychotherapy code from 90832 to 90838, does not factor into E/M selection, and needs documentation of the communication factor, such as a language barrier, high reactivity, use of play equipment or a sentinel event. Noridian adds that it may be reported with 90791, 90792, 90832, 90834, 90837, 90838 and 90853, and it does not list 90839.
| Add-on | Attaches to | Time basis | Documentation point |
|---|---|---|---|
| +90833 | An E/M visit by an MD/DO or nonphysician practitioner | 16 to 37 minutes | Psychotherapy minutes recorded apart from E/M time |
| +90836 | An E/M visit by an MD/DO or nonphysician practitioner | 38 to 52 minutes | Psychotherapy minutes recorded apart from E/M time |
| +90838 | An E/M visit by an MD/DO or nonphysician practitioner | 53 minutes or more | Psychotherapy minutes recorded apart from E/M time |
| +90785 | 90791, 90792, psychotherapy codes and 90853, per Noridian | Not time-based | State the specific communication complexity |
| +90840 | Crisis psychotherapy 90839 | Each additional 30 minutes | Crisis must be life-threatening and need immediate attention |
Source: First Coast Service Options (2026), Noridian Healthcare Solutions (2026), CGS Administrators (2021). Always confirm with the individual payer.
How are crisis, family and group sessions coded?
Crisis psychotherapy uses 90839 for the first block and 90840 for each additional 30 minutes. Noridian describes 90839 as the first 60 minutes, says the problem must be life-threatening and need immediate attention for a patient in high distress, and says it cannot be billed with other psychotherapy codes and is billed once per day. Some lists quote a 30 to 74 minute range for 90839. That could not be confirmed on a primary page, so check the exact minute thresholds in the current AMA CPT book.
Family sessions split by whether the patient is in the room. 90846 is family psychotherapy without the patient; 90847 is conjoint with the patient. Noridian says both are covered only when the primary purpose is treating the patient’s condition. First Coast adds that 90846 and 90847 may be reported with 90832 to 90838 on the same date when performed as a separate and distinct service in a separate time interval. For detail, see the 90846 family therapy billing guide.
Group psychotherapy is 90853. Some lists give it a 45 to 60 minute range as if the code were timed. Noridian describes the session as typically 45 to 60 minutes and caps participants at 10, and the APA 2013 overview does not give 90853 a timed band. Treat the length as a description and ask each payer whether it applies a minimum.
What about psychological testing and health behavior codes?
Psychological testing has its own code family, separate from therapy. The APA Monitor reported that new testing codes took effect on January 1, 2019. 96130 covers the first hour of testing evaluation services (test selection, data integration, interpretation, treatment planning and feedback), and 96131 is each additional hour. Administration and scoring are reported separately with 96136 and 96137 for a psychologist and 96138 and 96139 for a technician, in 30-minute units.
Health and behavior assessment codes need extra care. Some lists show 96150 and 96152 as substance abuse treatment codes. They are not. A California DHCS notice said 96150 to 96153 would be eliminated effective January 1, 2020 and replaced, and the APA Monitor says the replacement set is 96156 (assessment), 96158 and 96159 (individual intervention), 96164 and 96165 (group) and 96167 and 96168 (family with the patient). These codes require a physical health diagnosis as the primary diagnosis, not a mental health diagnosis, and they cannot be billed on the same date as psychotherapy.
| Code or range | What it is | Common mistake |
|---|---|---|
| 96130, +96131 | Psychological testing evaluation, first hour and each additional hour | Billing it for an ordinary therapy intake |
| 96136 to 96139 | Test administration and scoring in 30-minute units, by a psychologist or a technician | Using the psychologist code for technician time |
| 96146 | One automated test on an electronic platform | Using it when two or more electronic tests are given |
| 96156 to 96171 | Health behavior assessment and intervention, which replaced 96150 to 96155 in 2020 | Treating them as substance use or psychotherapy codes |
| 90839, +90840 | Crisis psychotherapy | Billing them with other psychotherapy codes on the same day |
Source: APA Monitor (2019, 2020), California DHCS (2019), Noridian Healthcare Solutions (2026).
Tobacco and substance use screening and counseling codes exist but sit outside the therapy list. HHS lists several of them (for example 99406, 99407, G0396 and G2086 to G2088) in a separate group on its telebehavioral billing page. Use the payer’s own substance use policy before choosing among them.
Do telehealth sessions use different mental health CPT codes?
No. The same psychotherapy and evaluation codes are used, and the place of service and any payer modifier tell the payer it was a telehealth visit. Some lists show “brief psychotherapy via video” as if it were a separate telehealth code. It is not.
HHS’s telehealth resource page (updated July 29, 2025) lists 90785, 90791, 90792, 90832 to 90840, 90846, 90847 and 90853 as having permanent Medicare telehealth coverage. Noridian lists place of service 02 for telehealth outside the patient’s home and 10 for telehealth in the home. The CMS telehealth FAQ says POS 02 applies outside the home and POS 10 at home, and that at-home telehealth claims have been paid at the non-facility rate since January 1, 2024.
Dates matter more than codes here. In the CMS FAQ version reviewed (updated October 9, 2026), Medicare telehealth flexibilities run through December 31, 2027, and the in-person visit requirement for mental health telehealth at home applies from January 1, 2028. After the first at-home mental health telehealth service, an in-person service is needed within 12 months of each mental health telehealth service. These dates have changed more than once, so re-read the FAQ before relying on them.
Modifiers are payer-specific. The CMS FAQ page reviewed does not discuss modifier 95 or the audio-only modifier, so this guide does not state a Medicare rule for them. Ask each commercial payer for its telehealth modifier and place-of-service policy in writing. The telehealth billing guide walks through that checklist.
What should the note show, and what do denials usually trace back to?
The note should let a reviewer rebuild the code without calling the clinician. Noridian Healthcare Solutions lists these elements for psychotherapy notes: patient name, date of service, session length, reason for the encounter, mental status, interventions, the patient’s progress or setback, the treatment plan and any change in diagnosis or medication, expected outcomes and high-risk factors, modality and frequency, and a legible signature with credentials. CGS Administrators says services must be signed and late signatures should not simply be added to the record.
- Time not shown. A start and stop time, or a clear total, for the psychotherapy portion.
- E/M and therapy blended. Add-on claims fail when one combined time is written for both.
- Wrong band. A 36-minute session billed as 90834, or a 50-minute session billed as 90837 because it is the practice’s usual code.
- More than one unit. Medicare contractors deny extra units outside partial hospitalization.
- Wrong rendering clinician. Noridian lists who may bill Medicare directly and says counselors in some roles cannot enroll or bill direct.
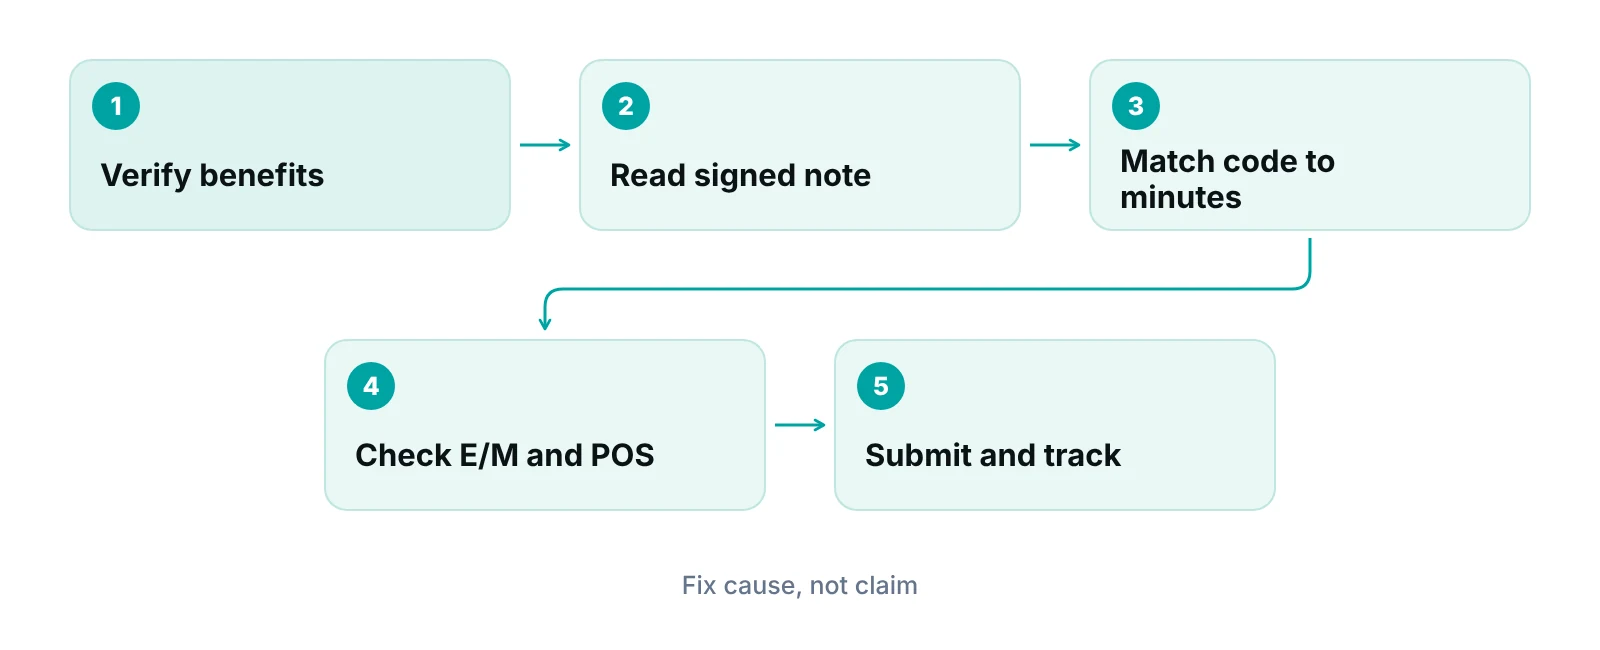
If a claim comes back denied for coding, read the denial reason first. Then compare the claim to the note and to the payer’s policy before resubmitting, and fix the cause so it does not repeat.
Want a second pair of eyes on your behavioral health claims?
A free practice audit reviews your code selection, note support and denial patterns, then tells you where claims are leaking. No pricing is quoted until you have seen it.
Should a practice keep mental health coding in-house?
Keep it in-house when one person owns code selection, the clinicians write time into every note, and denials are reviewed monthly. Consider help when time bands or add-on rules keep causing rework, when clinicians change often, or when telehealth and payer rules move faster than staff can follow.
Whichever route you take, ask for the same things: a written scope, who corrects a code when the note does not support it, how clinician questions are handled, and how often you see denial reports. Ask any vendor to sign a Business Associate Agreement before patient data is shared.
RCM Finder offers medical billing services with coding support for behavioral health, and the behavioral and mental health RCM operations page explains how that work is organized.
Our recommendations
- Make time part of the note template. Add start time, stop time and psychotherapy minutes as required fields. If the note does not show the minutes, the code is a guess.
- Code from the note, not from the schedule. The booked length of an appointment is not the documented length. Let billing staff correct the code to match the note and tell the clinician why.
- Keep E/M time and therapy time apart. For add-on claims, write the medical work and the psychotherapy minutes as two entries so the add-on has support.
- Build a one-page payer sheet. List telehealth place of service, modifier rules, unit limits and group-session rules per payer, with the date you last checked each one.
- Check the current code book once a year. Medicare contractor pages are a good guide, but the AMA CPT book is the final word on descriptors. Review it each January and update templates.
Bottom line
Mental health CPT codes follow the note, so the fix for most denials is better time documentation and a clear E/M pairing. If code selection or denials keep consuming staff time, a review of your claims by denial management services or a free practice audit is a practical next step.
Frequently asked questions
What are the most common mental health CPT codes?
The usual short list is 90791 and 90792 for diagnostic evaluation, 90832, 90834 and 90837 for individual psychotherapy, 90833, 90836 and 90838 as add-ons with an E/M visit, 90846, 90847 and 90853 for family and group sessions, and 90839 with 90840 for crisis. Psychological testing uses 96130 onward. Which you use depends on who delivered the service and the documented minutes.
Which mental health CPT code do I use for a 45-minute session?
A documented session of 38 to 52 minutes falls in the 90834 band when billed alone, or in the 90836 band when it is an add-on to an E/M visit, according to Medicare contractor pages. Use the time in the note, not the scheduled length. Sessions under 16 minutes are not reported as psychotherapy.
Can the same CPT code be used for in-person and telehealth sessions?
Yes. Telehealth uses the same psychotherapy and evaluation codes, and the place of service tells the payer how it was delivered. Medicare uses POS 02 outside the home and POS 10 at home. Modifier requirements vary by payer, so get the commercial rules in writing.
When do I use an add-on code such as 90833 or 90785?
90833, 90836 and 90838 are used only with an E/M visit by a physician or nonphysician practitioner, with the therapy minutes documented separately. 90785 is for interactive complexity, such as a language barrier or a sentinel event, and is not time-based. Neither type of add-on can be billed alone.
Did mental health CPT codes change for 2025 or 2026?
This review did not confirm specific psychotherapy code changes for 2025 or 2026 from primary sources. The sources used show testing codes changed in 2019 and health behavior codes in 2020, and Medicare telehealth dates have kept moving. Check the AMA CPT book for your billing year.
My claim was denied for the wrong CPT code. What now?
Read the denial reason, compare the claim with the signed note and the payer policy, then correct and resubmit only if the note supports the new code. If the note cannot support any code, ask the clinician whether a compliant late entry is possible under payer rules. Track the cause so it does not repeat.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Psychotherapy services — First Coast Service Options (Medicare Administrative Contractor) (2026)
- Mental Health specialty page — Noridian Healthcare Solutions (Medicare Administrative Contractor) (2026)
- Psychotherapy checklist fact sheet — CGS Administrators (Medicare Administrative Contractor) (2021)
- Coding overview for psychotherapy services — American Psychiatric Association (2013)
- New testing codes — American Psychological Association (APA Monitor) (2019)
- Health behavior codes and reimbursement news — American Psychological Association (APA Monitor) (2020)
- PPL 19-033 CPT codes — California Department of Health Care Services (2019)
- Billing for telebehavioral health — HHS Telehealth.hhs.gov (2025)
- Medicare telehealth FAQ (updated 10-09-2026) — CMS (2026)
- Telehealth services — CMS (2026)
Disclaimer: This article is for education only. It is not legal, coding, compliance or medical advice. CPT is owned by the AMA, and payer rules, Medicare contractor policies and telehealth dates change. Confirm each code with the current CPT book and the payer before billing.
