
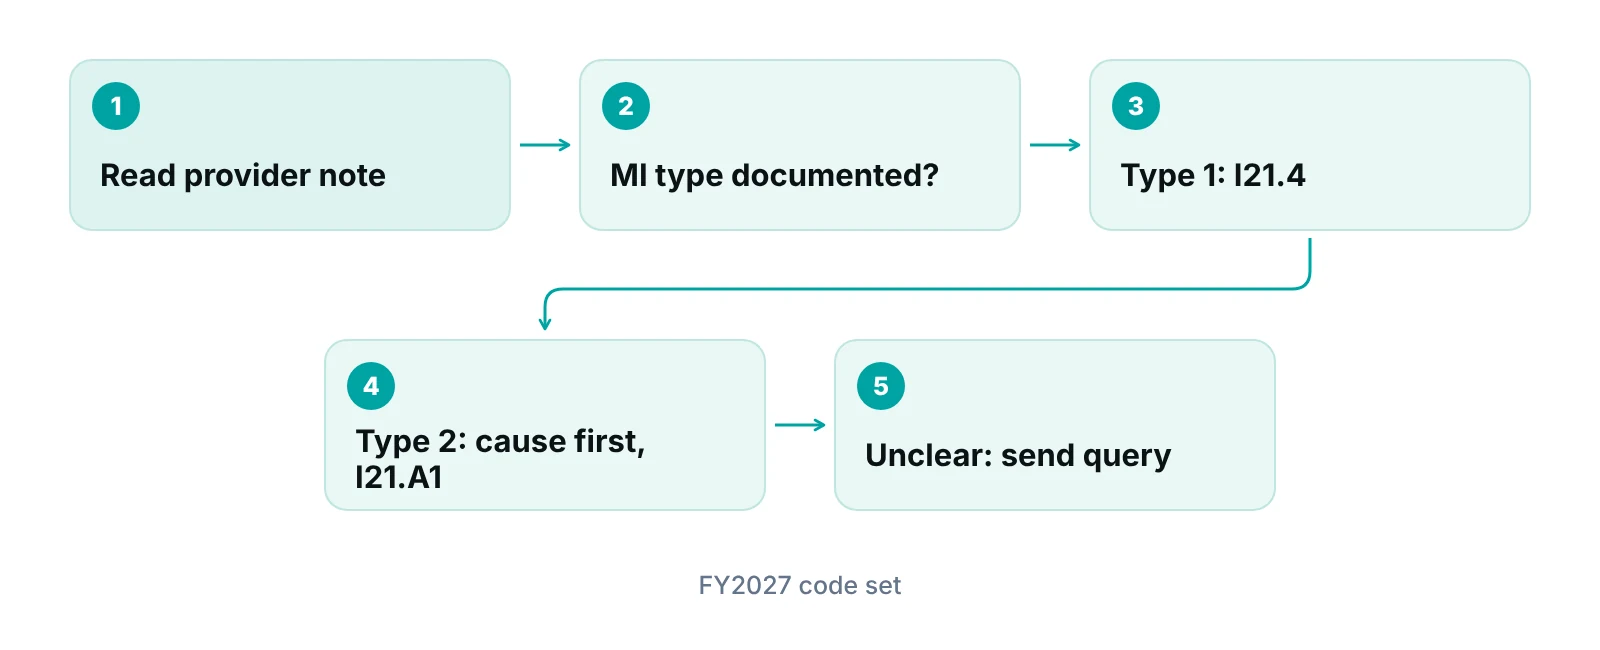
NSTEMI type 1 vs 2 comes down to cause, and the documented cause picks the code. In the FY2027 ICD-10-CM code set, a type 1 NSTEMI is I21.4. A type 2 MI is I21.A1, with the underlying cause coded first, even when the provider calls it an NSTEMI. The provider, not the coder, must document the type.
This guide is for coders, billers and practice managers. It covers the codes, the rule for type 2, and the claim errors to look for. It does not cover diagnosis or treatment. For the symptom stage, see our chest pain ICD-10 codes guide.
Key takeaways
- A type 1 NSTEMI is reported with I21.4. A type 2 MI is reported with I21.A1, with the underlying cause coded first.
- The Fourth Universal Definition lists five MI types, not six. Types 3, 4 and 5 map to I21.A9.
- The ECG label (NSTEMI) does not tell you the type. The provider’s documentation does.
- The old I24.8 code is no longer valid. The demand-ischemia code is I24.89.
- ICD-10-CM changes each October 1. This guide uses the FY2027 code set.
Which code fits? The FY2027 code map for NSTEMI type 1 vs 2
Start with what the provider documented, not with the ECG label. NSTEMI describes the ECG pattern. The type describes the cause. In the FY2027 ICD-10-CM code set, a type 1 NSTEMI is reported with I21.4, and a type 2 MI is reported with I21.A1, with the underlying cause coded first. CMS states that the FY2027 files apply to encounters from October 1, 2026 through September 30, 2027 (CMS).
That code-set year matters because ICD-10-CM changes every October. Every code in this guide was checked against a source that labels itself FY2027. If you are reading this after a later October 1, check the new year’s Tabular List before you rely on it. If the chart you are coding still says chest pain, our guide to chest pain ICD-10 codes covers the symptom codes.
| Code | Title (FY2027) | Use it when the note says | Watch for |
|---|---|---|---|
| I21.4 | Non-ST elevation (NSTEMI) myocardial infarction | NSTEMI, as a type 1 event | Only for type 1. A type 2 MI described as NSTEMI does not go here. |
| I21.A1 | Myocardial infarction type 2 | Type 2 MI, MI due to demand ischemia, or MI secondary to ischemic imbalance | A code-first note sends the coder to the underlying cause. Sequence it before I21.A1. |
| I21.A9 | Other myocardial infarction type | MI type 3, 4a, 4b, 4c or 5 | Has its own code-first and code-also notes (see below). |
| I21.9 | Acute myocardial infarction, unspecified | Acute MI with no type or site documented | A fallback. Ask the provider before you use it. |
Source: ICD-10-CM FY2027 code pages mirrored by icd-10codes.com (release dated October 1, 2026 to September 30, 2027), checked against ACDIS and AAPC coding articles. Confirm each entry in the CDC NCHS Tabular List.
Three cautions on the table. First, I21 is a category, not a billable code, so you always need a more specific code beneath it (icd-10codes.com, FY2027). Second, the I21 category includes MI that is specified as acute or has a stated duration of 4 weeks (28 days) or less. Third, the Excludes2 note at I21 lists old MI (I25.2), post-myocardial infarction syndrome (I24.1) and subsequent type 1 MI (I22.-), so a readmission needs a read of that note before you pick a code.
What the Fourth Universal Definition says about MI types
The Fourth Universal Definition of Myocardial Infarction (2018) lists five types of MI, not six. It was published in Journal of the American College of Cardiology 2018;72:2231-64, with simultaneous publication in Circulation and European Heart Journal (ACC summary). The old version of this post said six types, which was wrong.
Type 1 is an MI from acute coronary atherothrombotic injury, with plaque rupture or erosion and often thrombosis. Type 2 is acute ischemia from an oxygen supply-demand imbalance without acute atherothrombotic injury. Anemia, significant arrhythmias and coronary vasospasm, embolus or dissection are among the listed causes. Both can present as STEMI or NSTEMI, which is why the ECG label alone cannot choose the code.
| MI type | Short description | ICD-10-CM code family |
|---|---|---|
| Type 1 | Acute atherothrombotic coronary injury (plaque rupture or erosion, often with thrombosis) | I21.0- to I21.3 for STEMI, I21.4 for NSTEMI |
| Type 2 | Oxygen supply-demand imbalance without acute atherothrombotic injury | I21.A1, underlying cause coded first |
| Type 3 | Ischemic symptoms with no troponin measured because the patient died first | I21.A9 |
| Type 4 (4a, 4b, 4c) | PCI-related MI, stent thrombosis, restenosis | I21.A9 |
| Type 5 | CABG-related MI | I21.A9 |
Source: Fourth Universal Definition of MI (2018) as summarised by the American College of Cardiology; code families from FY2027 code pages (icd-10codes.com) and the I21.A9 entry, which lists MI types 3, 4a, 4b, 4c and 5.
Types 3, 4 and 5 are less common in day-to-day coding, but they matter for a cardiology group that bills around procedures. The I21.A9 entry carries a code-first note for postprocedural MI following cardiac surgery (I97.190) or during cardiac surgery (I97.790) and code-also notes for stent complications, so read it in full (icd-10codes.com, FY2027).
Type 2 MI: code the underlying cause first
For a type 2 MI, ICD-10-CM tells the coder to report the cause before I21.A1. The I21.A1 entry carries a code-first note that lists anemia (D50.0 to D64.9), chronic obstructive pulmonary disease (J44.-), paroxysmal tachycardia (I47.0 to I47.9) and shock (R57.0 to R57.9) as examples, and a code-also note for hypertension (I10 to I1A) (icd-10codes.com, FY2027). ACDIS describes the same sequencing instruction and points to guideline section I.C.9.e.5, “Other Types of Myocardial Infarction” (ACDIS).
What the guideline wording says about NSTEMI
Coding sources quote the Official Guidelines as saying that if a type 2 MI is described as NSTEMI or STEMI, only I21.A1 is assigned, and that I21.01 through I21.4 are for type 1 MI only (AAPC; ACDIS, quoting the 2020 guidelines). The FY2027 guidelines took effect October 1, 2026 (CMS). Read section I.C.9.e.5 in the current PDF before you write the rule into a policy.
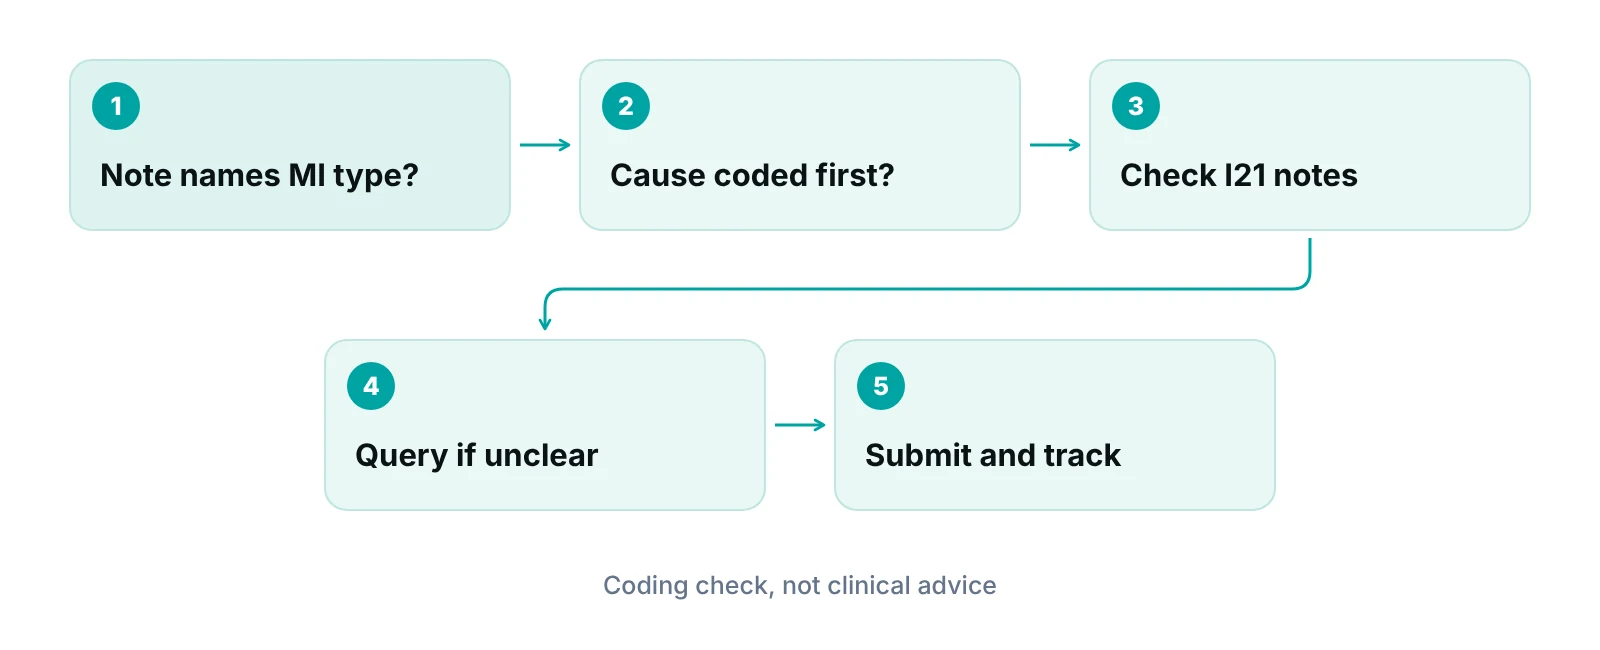
In practice, that means the words “NSTEMI due to tachycardia” are not enough to pick a code. If the provider documents a type 2 MI and the cause, the cause code comes first and I21.A1 follows. If the provider documents a type 1 NSTEMI, I21.4 is the code. If the note supports neither, the coder asks.
Demand ischemia is not the same statement as type 2 MI
The I21.A1 entry includes the terms “myocardial infarction due to demand ischemia” and “secondary to ischemic imbalance.” Those are descriptions of an MI. Demand ischemia with no MI documented is a different diagnosis. ACDIS notes that the guideline tells coders not to assign the “other forms of acute ischemic heart disease” code for demand ischemia when an MI is coded (ACDIS). That code was written as I24.8 in the 2020 guidelines. It has since been split, and the current demand-ischemia code is I24.89, which is why the old version of this post cited an invalid code (ICD-10-CM training deck citing the 2024 guidelines). A coder never converts one into the other. The provider does.
| What the note says | What the coder does | Why |
|---|---|---|
| “Type 2 MI due to anemia” (or another listed cause) | Report the cause code first, then I21.A1 | Code-first note at I21.A1 |
| “NSTEMI due to tachycardia,” no type stated | Send a non-leading query asking for the MI type | NSTEMI alone does not tell the coder type 1 from type 2 |
| “Type 2 NSTEMI” | Report I21.A1 with the cause first. Do not report I21.4 | Guideline wording on type 2 MI described as NSTEMI |
| “Demand ischemia,” no MI documented | Do not report an I21 code. Query only if the record points to an MI | Demand ischemia and type 2 MI are different statements |
| MI documented 3 weeks ago, patient readmitted | Read the I21 includes, Excludes2 and I22.- notes. Ask your coding lead | I21 covers MI of 4 weeks (28 days) or less; subsequent type 1 MI sits in I22.- |
Source: ICD-10-CM FY2027 code pages (icd-10codes.com), ACDIS (2019 article and Q&A) and AAPC coding articles. Coder actions are workflow suggestions, not payer rules.
Where NSTEMI type 1 vs 2 errors show up on a claim
A wrong MI type rarely announces itself. It can pass a scrubber and still misstate the chart. We removed the old post’s dollar ranges, denial percentages and audit claims, because no published source we could fetch supports them. What we can say is where the errors tend to sit.
- I21.4 reported when the note documents a type 2 MI.
- I21.A1 reported without the underlying cause coded first.
- I21.A1 and I21.4 both reported for the same event.
- Demand ischemia coded as an MI, or an MI coded as demand ischemia, without a provider statement.
- I21.9 reported because the type was never documented.
- A code chosen from last year’s code book after the October 1 update.
Inpatient claims are grouped by the diagnoses and procedures on them. CMS publishes the MS-DRG v44.0 Definitions Manual for the FY2027 logic, so a facility coding team can see how a principal diagnosis and secondary diagnoses change grouping for its own cases. We do not quote a payment difference here, because it depends on the procedures, the secondary diagnoses and the payer. Our guide to medical coding audits explains how to test a sample of these claims, and our medical billing services team runs diagnosis checks before claims leave the building.
A pre-claim check for MI codes
Clear provider notes make every step above easier. Our post on clear documentation in medical billing shows how note quality flows into claim quality.
What this means for a cardiology practice
For a cardiology group, the MI type decision sits in the provider’s note, and the billing team’s job is to make sure that note supports one code. Your cardiologists see patients before, during and after an MI, and the diagnosis you report on a follow-up visit has to match what the provider documents on that date. Our cardiology billing and RCM page describes how we support cardiology groups.
The I21 includes note covers MI with a stated duration of 4 weeks (28 days) or less, and the Excludes2 note points to I25.2 for old MI. The provider decides how the MI is described at each visit. The coder should not guess a stage from the date alone. For symptom-level coding before an MI is confirmed, see chest pain ICD-10 codes. For how diagnosis, procedure and supply codes fit together on one claim, see our explainer on CPT, ICD-10 and HCPCS codes.
Want a second pair of eyes on your cardiac diagnosis coding?
Send us your current claim workflow and we will look at how provider notes, MI codes and edits line up. The audit is free, and pricing is quoted after it.
Our recommendations
- Ask providers to write the type and the cause in one sentence. We would ask for wording such as “type 2 MI due to [cause]” in the diagnosis statement. It gives the coder one line to code from and removes the guesswork about type.
- Build a short MI query template. We would keep a non-leading query that lists the documented clinical facts and asks the provider to state the MI type. Check it against your facility’s query policy.
- Sequence the cause before I21.A1 in your encoder rules. We would add a check that flags I21.A1 when no code from the code-first list is on the claim. Treat the flag as a prompt to review, not as proof of an error.
- Stop I21.4 and I21.A1 appearing together. We would add an edit that holds a claim carrying both codes for the same event until a coder reviews it.
- Re-check I21 and I24 entries every October. We would put the October 1 code update on the calendar and re-read the I21 and I24 notes in the new Tabular List and guidelines.
- Audit a small sample each quarter. We would pull a sample of MI claims, compare the code with the provider note, and share the pattern with the providers. Keep the sample size and findings in your own compliance file.
Bottom line
NSTEMI type 1 vs 2 is a documentation question first and a coding question second. I21.4 is for type 1, I21.A1 is for type 2 with the cause coded first, and I21.A9 covers the other MI types. If your cardiac claims need a second review, our denial management services and end-to-end revenue cycle management teams can help, and our guide to clean claims shows what a clean submission looks like. You can also talk to our team.
Frequently asked questions
What is the ICD-10-CM code for NSTEMI type 1?
A type 1 NSTEMI is reported with I21.4, Non-ST elevation (NSTEMI) myocardial infarction. This answer uses the FY2027 code set, which applies to encounters from October 1, 2026 through September 30, 2027. The provider must document the event as a type 1 MI or as an NSTEMI with no other type stated.
What is the ICD-10-CM code for NSTEMI type 2?
A type 2 MI is reported with I21.A1, Myocardial infarction type 2, and the underlying cause is coded first. Coding sources quote the guidelines as saying that a type 2 MI described as NSTEMI gets I21.A1 only, not I21.4. Check section I.C.9.e.5 in the current guidelines.
How many types of MI are there?
The Fourth Universal Definition of Myocardial Infarction (2018) lists five types. Types 1 and 2 map to I21.4 and I21.A1 in ICD-10-CM, and types 3, 4a, 4b, 4c and 5 map to I21.A9, Other myocardial infarction type.
Can a type 2 MI be the first-listed diagnosis?
The I21.A1 code-first note tells the coder to report the underlying cause before I21.A1, so the cause code comes first on the claim. How the cause and the MI are sequenced on a given claim is a question for your coding lead and the Official Guidelines.
Is I24.8 still a valid code for demand ischemia?
No. I24.8 was split into more specific codes, and the demand-ischemia code is I24.89. Demand ischemia with no MI documented is not the same as a type 2 MI, so the coder does not swap one for the other without a provider statement.
Why did the old version of this post change?
We removed the claim of six MI types, the invalid I24.8 code, the DRG dollar ranges and the denial percentage, because none of them held up against primary or professional sources. The core point, that I21.4 is type 1 and I21.A1 is type 2, stays.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- 2027 ICD-10-CM files — Centers for Medicare & Medicaid Services (2026)
- FY 2027 ICD-10-CM Official Guidelines for Coding and Reporting — CMS / NCHS (2026)
- ICD-10-CM files page — CDC National Center for Health Statistics (2026)
- Fourth Universal Definition of MI: What's New? — American College of Cardiology (2018)
- I21 Acute myocardial infarction (FY2027) — icd-10codes.com (third-party mirror of CDC data) (2026)
- I21.A1 Myocardial infarction type 2 (FY2027) — icd-10codes.com (third-party mirror of CDC data) (2026)
- I21.A9 Other myocardial infarction type (FY2027) — icd-10codes.com (third-party mirror of CDC data) (2026)
- Q&A: Coding demand ischemia and MI — ACDIS
- When documenting Type 2 MI, start with the underlying cause — ACDIS (2019)
- Coding quiz: can you navigate myocardial infarction coding — AAPC
- ICD-10-CM/PCS training course, circulatory chapter — National Health Insurance Administration, Taiwan
Disclaimer: This article is educational and is not legal, coding, clinical or compliance advice. ICD-10-CM is maintained by the CDC National Center for Health Statistics and CMS, and the code set changes each fiscal year. Payer rules vary, and the provider's documentation controls code assignment. Confirm each code in the current Tabular List, the Official Guidelines and your payer's policy before you bill.
