
Out-of-network medical billing is how a practice bills a patient's health plan when the practice has no contract with that plan. The plan pays under the patient's out-of-network benefits, and the practice sets its own charge. Federal law limits balance billing in emergencies, at in-network facilities and for air ambulance.
If your practice is not credentialed with a plan, every visit from that plan’s members is an out-of-network visit. That changes who sets the price, how the claim is filed and what you may collect from the patient. This guide is written for practice owners and managers. It explains the basics, the documents you need, what the federal No Surprises Act does and does not cover, and how Medicare fits in. The page replaces our earlier out-of-network guides, so the common questions from both are answered here.
Key takeaways
- Out-of-network means no contract with that specific plan, so check network status plan by plan.
- The practice sets its fee, but the plan decides what it recognizes, so a written patient estimate prevents most disputes.
- The No Surprises Act bans balance billing for emergency care, air ambulance and ancillary providers at in-network facilities. It does not apply to Medicare or Medicaid.
- For NSA-covered claims, the plan has 30 calendar days to pay or deny, and negotiation and IDR deadlines are short.
- Medicare classifies providers by assignment status instead of network.
What is out-of-network medical billing?
Out-of-network (OON) billing applies when your practice has not signed a participation contract with the patient’s health plan. In-network practices accept the plan’s contracted rates. Out-of-network practices do not, so the plan treats the visit under the member’s out-of-network benefits, which are often less generous, and the member usually owes a larger share.
Network status is set per plan and often per product, so a practice can be in network for one plan from a carrier and out of network for another plan from the same carrier. Check the patient’s actual plan, not just the insurer’s name.
| Question | In-network | Out-of-network |
|---|---|---|
| Is there a contract with the plan? | Yes. The practice accepts the plan’s contracted rates. | No contract with this plan. |
| Who sets the price you bill? | You bill your charge, but the contract fixes what is allowed. | You set your fee. The plan decides what it recognizes as allowed under the member’s out-of-network benefits. |
| What does the patient owe? | Copay, deductible or coinsurance on the contracted amount. | Out-of-network deductible and coinsurance, plus any difference you are allowed to bill. |
| Who usually files? | The practice. | Either the practice or the patient, depending on your policy and the plan. |
| What limits can apply? | Contract terms. | Federal rules for emergency and some non-emergency services, state laws and plan terms. |
Our guide to in-network versus out-of-network care covers the same split from the patient’s side. If you are deciding whether to join a plan at all, read the section on staying out of network below.
How does an out-of-network claim get paid?
An out-of-network claim is paid when the plan applies the member’s out-of-network benefits to your billed charge. The plan keeps its own limit on what it recognizes, takes off the member’s deductible and coinsurance, and pays the rest. What is left between your charge and that recognized amount is the part that balance-billing rules govern.
| Line | Amount | How it is worked out |
|---|---|---|
| Practice charge | $300 | Your fee for the visit |
| Amount the plan recognizes | $180 | Set by the plan under the member’s OON benefits |
| Member coinsurance (40%) | $72 | 40% of $180, assuming the deductible is already met |
| Plan pays | $108 | $180 minus $72 |
| Difference between charge and recognized amount | $120 | $300 minus $180 |
| Most the patient could owe if balance billing is allowed | $192 | $72 coinsurance plus $120 difference |
Illustrative arithmetic only. Plan limits, deductibles and coinsurance vary by plan, and balance billing is restricted in many settings (see the federal rules below).
That last row is the reason estimates matter. If a patient is told the visit costs $300 and later learns the plan only reimbursed $108, the gap becomes a collection problem. A written estimate before the visit is the cheapest fix. See our insurance verification guide for how to confirm out-of-network deductibles and coinsurance before the patient arrives.
Superbill or claim: how does the practice get paid?
There are two common routes. The practice can file the claim itself, or it can hand the patient a superbill so the patient files with the plan. A superbill is an itemized statement of the visit that carries the data a plan needs to process a claim. The plan, not the practice, decides whether it will accept a patient-filed superbill, so confirm that before you promise it.
Whichever route you choose, the paperwork has to be complete. A claim or superbill that leaves out a field is a common reason for a denial or a delay, and the fix is cheap if you catch it before you send it.
What a complete superbill or out-of-network claim should carry
- Practice details: legal name, address, billing NPI and tax ID.
- Rendering provider: name and NPI of the clinician who saw the patient.
- Patient and policy details: name, date of birth, member ID and group number as they appear on the card.
- Visit details: date of service and place of service.
- Codes: the CPT or HCPCS code for each service and the ICD-10-CM diagnosis codes that support it.
- Charges and payments: your fee for each line, plus anything the patient has already paid.
- Signatures and authorizations: the patient’s signed consent to bill and, if the plan will pay you directly, an assignment of benefits.
Run the same data-completeness check you would run on an in-network claim, before the claim leaves the office.
What does the No Surprises Act change for out-of-network billing?
The No Surprises Act (NSA) limits when an out-of-network provider can bill a patient for more than in-network cost sharing. Its main rules took effect on January 1, 2022. They apply to patients with employer, Marketplace or individually purchased coverage and do not apply to people covered by Medicare, Medicaid, Indian Health Service, VA health care or TRICARE.
In short: emergency care is treated on an in-network basis, out-of-network charges for ancillary providers at in-network facilities are banned, and air ambulance out-of-network charges are banned. Patient cost sharing must be based on in-network rates. Other out-of-network balance billing is allowed only after a plain-language notice and the patient’s consent, and only where the patient had a real choice of provider.
| Situation | Balance billing allowed? | What the practice should do |
|---|---|---|
| Emergency services | No. Treated on an in-network basis, with no prior authorization required. | Bill the plan. Collect only the in-network cost sharing the plan assigns to the patient. |
| Post-stabilization services | Only with notice and consent, which the provider may request. | Use the notice and consent form only where the rules allow it. |
| Ancillary providers (for example anesthesiologists) at an in-network facility | No, in all circumstances. | Do not ask the patient to sign away protection. Bill the plan and use the payment dispute process if needed. |
| Scheduled non-emergency care by an OON provider at an in-network hospital or surgery center | Only with notice and consent, and not if the patient had no choice of provider or facility. | Give the notice and keep the signed consent. |
| Air ambulance | No. | Bill the plan and use the dispute process if the payment is too low. |
| Patient covered by Medicare, Medicaid, IHS, VA or TRICARE | The NSA does not apply. Program rules do. | Follow the program’s own rules (see the Medicare section). |
Source: CMS, No Surprises Act overview for assisters (accessed 2026); CMS, Provider requirements and resources (accessed 2026).
CMS names anesthesiologists as an example of ancillary providers. If anesthesia is your area, our anesthesia billing and RCM page explains how our team supports that billing.
State laws may add rules
The federal payment dispute process does not cover every item or service, and some states have their own laws. CMS publishes an applicability chart for checking. Look up your state insurance department’s rules before you rely on federal protections alone. Our guide to surprise medical bills and disputes covers the patient’s view.
What if the plan pays too little on a protected claim?
For services the NSA covers, the plan has 30 calendar days to make an initial payment or send a written denial. If you disagree with the amount, either side may start a 30-business-day open negotiation. If that fails, the federal independent dispute resolution (IDR) process decides the payment rate. Deadlines are short, so put the dates on a worklist.
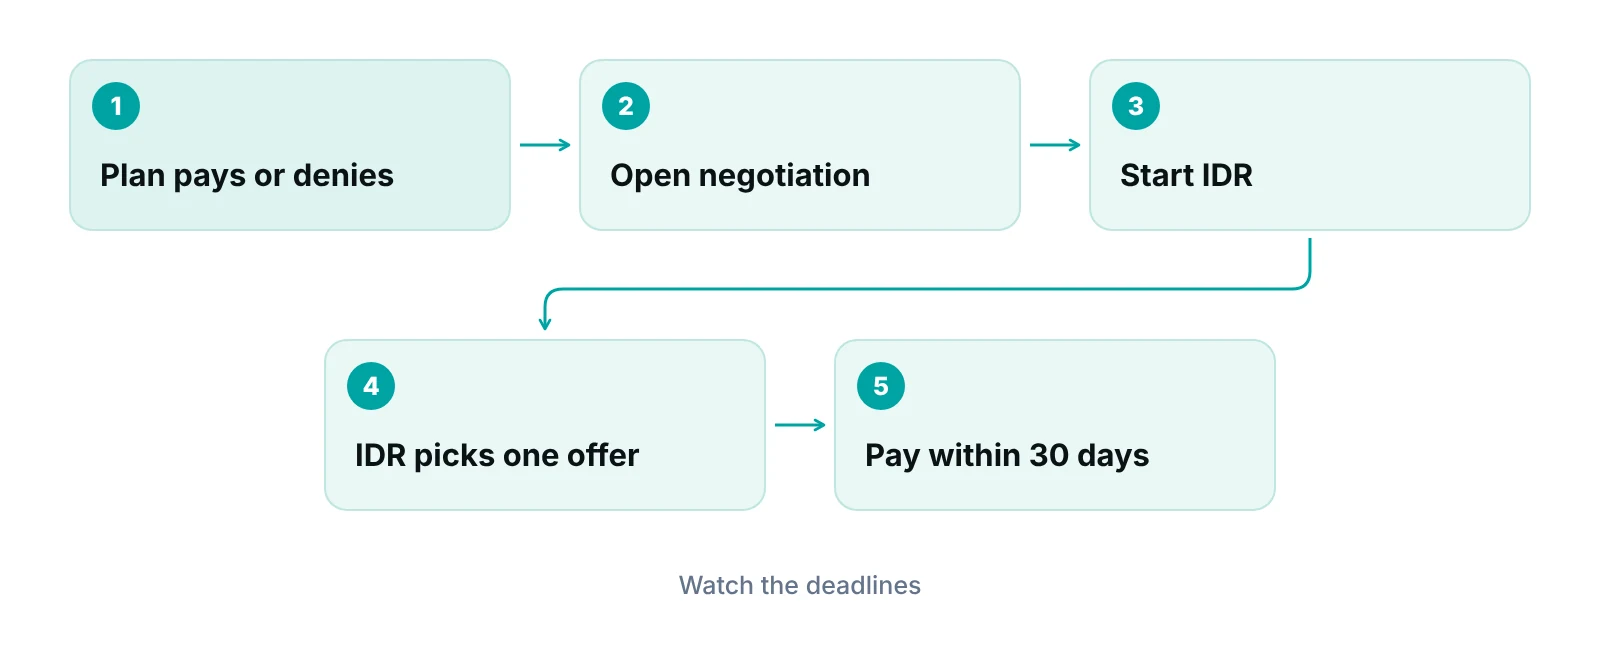
- Plan pays or denies within 30 calendar days. The clock starts when the plan has the information it needs to decide the claim. The plan must include the qualifying payment amount (QPA) and instructions for open negotiation with the payment or denial.
- Open negotiation. Either party may start it within 30 business days after you receive the initial payment or denial. It runs up to 30 business days. Send the standard notice, one per item or service unless they are bundled or batched.
- Start federal IDR. If no rate is agreed, either party may start IDR within 4 business days after open negotiation ends, by sending a Notice of IDR Initiation.
- The certified IDR entity picks one of the two offers. It does not set its own amount.
- Payment is due within 30 calendar days of the decision.
If a payer underpays or denies a claim that is outside the NSA, the normal appeal route applies. Plan appeal rules, filing limits and deadlines differ by payer and state, so record each payer’s deadline in your payer profile. Our denial management guide explains how to find the denial reason and write the appeal, and the CMS page on the federal IDR process lists the current steps.
How does Medicare treat out-of-network providers?
Medicare uses different terms. Medicare describes providers as accepting assignment, not accepting assignment (non-participating), or opted out. Providers who accept assignment take the Medicare-approved amount as payment in full for covered services and bill Medicare directly.
A provider who does not accept assignment may still treat Medicare patients and may charge more than the approved amount, but “in many cases, the charge can’t be more than 15% above the Medicare-approved amount.” Medicare calls this the limiting charge. Providers who opt out do not work with Medicare, and Medicare will not pay for their services except in emergencies. An opt-out lasts at least 2 years, and the patient may be asked to sign a private contract.
Because Medicare is outside the NSA, do not copy commercial out-of-network rules onto Medicare patients. If a patient is on a private Medicare plan, check that plan’s own network rules instead.
What must you give uninsured or self-pay patients?
Uninsured and self-pay patients are entitled to a good faith estimate before scheduled care. Under the NSA’s good faith estimate rules, the estimate is due within one business day of scheduling if care is scheduled at least 3 business days ahead, within three business days if it is scheduled at least 10 business days ahead, and within three business days of a request if care is not yet scheduled.
If the final bill is at least $400 more than the good faith estimate, the patient can start a patient-provider dispute resolution process, and has 120 calendar days from the bill to do so. Build the estimate into the scheduling workflow.
A practical out-of-network billing workflow
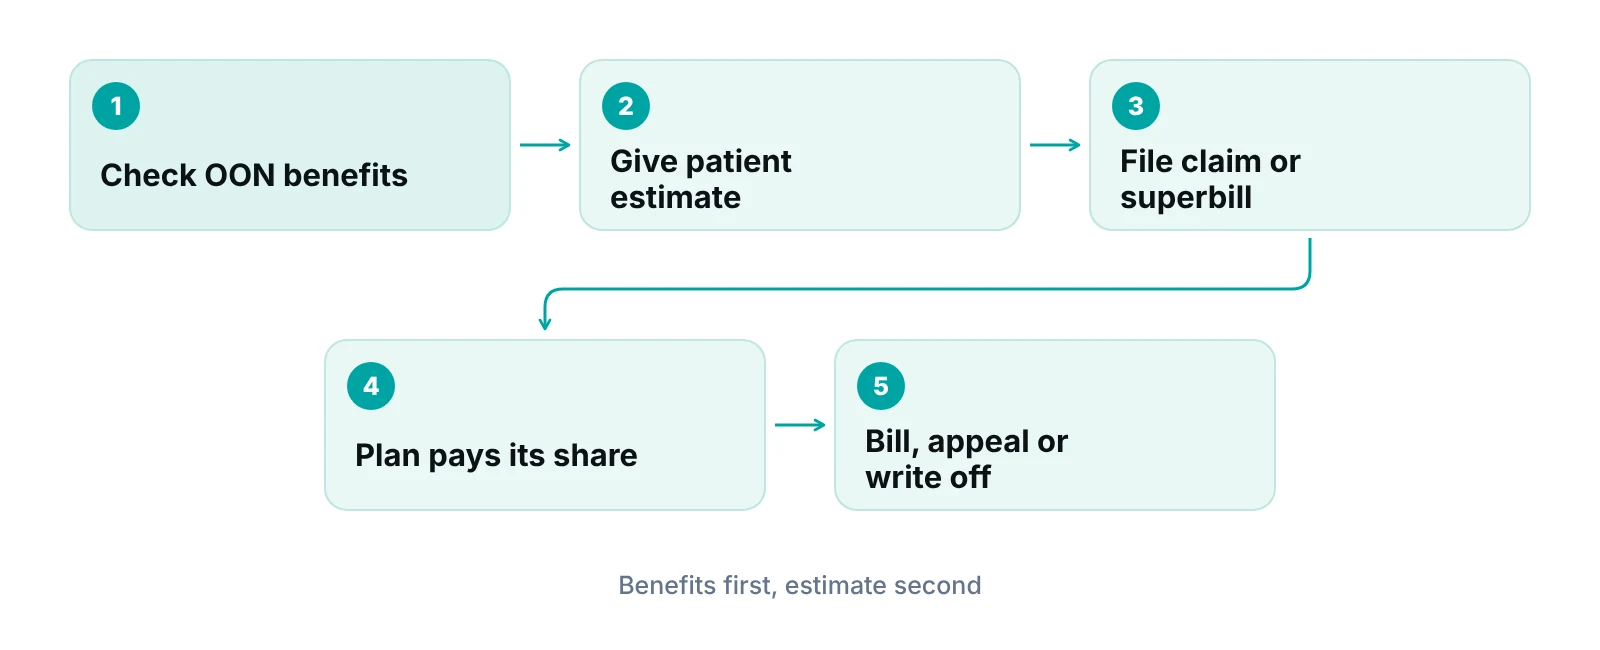
A reliable out-of-network process is mostly front-desk discipline: know the benefits, set expectations, send a clean claim and chase it. The steps below fit a small practice and can be handed to a billing team.
- Confirm network status per plan. Check the patient’s plan, not only the carrier, and record the date you checked.
- Verify out-of-network benefits. Ask for the out-of-network deductible, how much is met, coinsurance, and whether the plan pays the practice or the patient.
- Give a written estimate. Show your charge, the likely plan payment and the most the patient could owe, as in the example above.
- Check whether any federal or state protection applies. Emergency care and ancillary providers at in-network facilities fall under different rules from a scheduled office visit.
- File a complete claim or superbill. Use the field list above and keep a copy.
- Track every claim by stage. Note the date sent, the payer’s response date and the owner. A practice management system that tracks claims by stage can keep that list and flag payments that land below the expected amount.
- Post payments and work the difference. Decide, per your policy and the rules above, whether to bill the patient, appeal or adjust the balance.
- Review the oldest balances monthly. Out-of-network claims stay in A/R longer when nobody owns them.
“An out-of-network visit goes better when the patient hears the likely cost before the visit, not after the explanation of benefits arrives.”
If you would rather hand the claim work to a team, our medical billing services and denial management and appeals service cover claim submission and follow-up.
Not sure which visits are out of network?
A free practice audit looks at how your claims are being filed and followed up, including payer mix and open balances, and shows where the gaps are.
Should your practice stay out of network?
Staying out of network is a business decision, not a billing error. It gives you control over your fees, but it asks the patient to carry more cost and paperwork, and it makes your estimates and collections work more important. Joining a network shifts the trade the other way: contracted rates, easier patient access and a heavier credentialing and contract-management load.
- Fee control versus patient access. Ask how many of your patients ask whether you take their plan, and how many leave when you do not.
- Admin cost. Out-of-network work needs estimates, patient communication and more follow-up per claim. Count the staff hours.
- Timing. Enrollment can take time, so start early if you decide to join.
If you decide to enroll, our credentialing guide explains the steps, and our credentialing and payer enrollment service handles applications.
Our recommendations
- Record network status for every active plan. Keep a simple table of each plan you see, whether you are in or out of network, the date you checked and who checked it. Update it when contracts change.
- Verify out-of-network benefits before the visit. Ask for the out-of-network deductible, how much is met, coinsurance, any plan limit on what it recognizes, and whether payment goes to you or the patient.
- Give every out-of-network patient a written estimate. Show your charge, the likely plan payment and the most the patient could owe. Have the patient sign it, and keep it with the account.
- Check protections before you bill the difference. Before sending a patient bill above in-network cost sharing, check whether emergency, ancillary-at-in-network-facility, air ambulance or state rules apply. Ask a qualified advisor if unsure.
- Use one claim and superbill checklist. Make a single list of required fields, codes and signatures, and run it before every out-of-network submission.
- Put dispute deadlines on a worklist. For NSA-covered claims, track the 30-day payment date, the open negotiation window and the 4-business-day IDR start window so no deadline is missed.
A practice management system built around claims, not charts.
RCM Finder's portal tracks every claim by stage with an owner and flags payments that land below the expected amount, which helps with out-of-network claims. It is a claims system, not an EHR.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Out-of-network medical billing works when the practice knows each plan’s network status, shows the patient the likely cost first and sends a complete claim or superbill. The harder calls are legal ones, so check the federal and state rules before billing a patient above in-network cost sharing. If joining a plan makes more sense, see our credentialing and payer enrollment service, or talk to us about your out-of-network claims.
Frequently asked questions
What is out-of-network medical billing?
It is billing a plan for care when the practice has no participation contract with that plan. The practice sets its own fee, the plan pays under the member’s out-of-network benefits, and the patient usually owes a larger share than in network. Rules on billing the patient the remaining difference depend on the setting, the payer and the state.
What does a superbill need to include?
Practice name, address, billing NPI and tax ID, the rendering provider and NPI, the patient’s name, date of birth and member ID, the date and place of service, CPT or HCPCS codes with ICD-10-CM diagnosis codes, each charge, and any payment received. Confirm with the plan that it accepts patient-filed superbills before you promise this route.
Can an out-of-network provider balance bill a patient?
Sometimes. Under the federal No Surprises Act, balance billing is banned for emergency services, air ambulance, and out-of-network ancillary providers at in-network facilities, and patient cost sharing must follow in-network rates. Other scheduled care may be billed above that only after a notice and the patient’s consent. State laws and Medicare, Medicaid and TRICARE rules differ.
How does Medicare treat out-of-network providers?
Medicare classifies providers by assignment instead. Providers who accept assignment take the Medicare-approved amount as payment in full. Non-participating providers can charge more, and in many cases not more than 15% above the approved amount. Opted-out providers are not paid by Medicare except in emergencies. A private Medicare plan has its own network rules, so check that plan.
What can you do if an out-of-network claim is denied or underpaid?
Read the denial reason, correct any data errors, gather the records and appeal inside the payer’s deadline. For services the No Surprises Act covers, the process is open negotiation within 30 business days, then federal IDR within 4 business days after negotiation ends. The reviewer picks one of the two offers, and payment is due in 30 days.
Do out-of-network patients need a good faith estimate?
The federal rule covers uninsured and self-pay patients. The estimate is due within one business day of scheduling when care is at least 3 business days away, and within three business days when it is at least 10 business days away. If the bill is at least $400 over the estimate, the patient can start a dispute. Confirm with counsel how the rule applies to insured patients who choose not to bill their plan.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- No Surprises Act overview for assisters — CMS (2022)
- Provider requirements and resources — CMS (2026)
- About Independent Dispute Resolution — CMS (2026)
- Plan and issuer requirements checklist (NSA) — CMS (n/d)
- Open negotiation notice instructions — U.S. Department of Labor (EBSA) (n/d)
- Does your provider accept Medicare? — Medicare.gov (2026)
Disclaimer: This post is general educational information about revenue cycle operations. It is not legal, coding or compliance advice. Federal rules cover only some services and patients, state laws and payer contracts vary, and deadlines can change. Confirm requirements with each payer and a qualified advisor before acting.
