
The outpatient code editor (OCE) is CMS software that edits institutional outpatient claims inside Medicare's claims processing systems. It checks codes, modifiers, dates and units, assigns payment details, and decides whether a claim is paid, returned, rejected, denied or held. It applies to UB-04 outpatient billers such as hospital outpatient departments.
Most explanations of the OCE describe it as a tool a practice runs before it sends a claim. That is not how CMS describes it. The editor sits in Medicare’s own systems, so providers meet it as a set of results on a claim they have already submitted. This guide explains who it applies to, what the results mean, how it differs from the other edit sets billers hear about, and what to do when a claim comes back with an OCE reason code. It is written for practice managers and billers, and it is current as of the October 2026 release (version 27.3).
Key takeaways
- The OCE edits UB-04 institutional outpatient claims, including OPPS and non-OPPS hospital outpatient departments, critical access hospitals and community mental health centers.
- It runs inside Medicare’s claim processing systems after you submit, so you see its results as reason codes, not as software you run.
- A claim can be paid, returned to provider, rejected, denied or suspended, and individual lines can be rejected or denied on their own.
- CMS updates the editor every quarter. The October 2026 release is version 27.3 and took effect October 1, 2026.
- A typical physician-office claim is not the OCE’s audience, but the NCCI edits that overlap with it still matter to any biller.
What the outpatient code editor is
The Outpatient Code Editor, usually shortened to OCE and now called the Integrated Outpatient Code Editor (I/OCE), is one of two code editors CMS built to process UB-04 claims. The other is the Medicare Code Editor (MCE), which CMS describes as the inpatient code editor. The Medicare administrative contractor (MAC) guidance from Noridian says the I/OCE processes claims for all outpatient institutional providers.
The editor does more than catch errors. It applies a set of edits to a claim, identifies what is wrong and what action the claim needs, assigns an Ambulatory Payment Classification (APC) number and a status indicator to each line, computes payment, and decides whether services are packaged or discounted. In short, it is part error check and part pricing engine.
Two limits are worth knowing. It looks at one claim at a time, with no ability to compare across claims. And it handles up to 450 line items on a single claim. Because it works only from the data on the claim, it cannot read your chart. An edit can tell you a modifier does not fit a code. It cannot tell you whether your documentation supports that modifier.
Who uses the OCE, and does your practice?
Your practice is in scope if it bills Medicare for outpatient services on a UB-04 institutional claim. CMS’s October 2026 transmittal says the I/OCE routes all institutional outpatient claims through a single editor, covering OPPS and non-OPPS hospital outpatient departments, community mental health centers and all non-OPPS providers. It also covers limited services in home health agencies that are not under the home health PPS, and hospice patients treated for a nonterminal illness.
| Item | What CMS and its contractors say |
|---|---|
| Claim form | UB-04 institutional claims |
| Providers covered | Hospital outpatient departments (OPPS and non-OPPS, including critical access hospitals), community mental health centers, other non-OPPS providers, and certain home health and hospice claims |
| What it does | Applies edits, assigns APCs and status indicators, computes payment, applies packaging and discounts |
| Scope limits | One claim at a time; up to 450 line items per claim |
| Update cadence | Quarterly |
| Latest release | Version 27.3, effective October 1, 2026 (Transmittal 13979, Change Request 14594) |
Source: Noridian Healthcare Solutions (Medicare Part A MAC) I/OCE and MCE page (2026); CMS Transmittal 13979 (September 29, 2026).
A physician or group practice that bills on the professional claim form is not the audience. Its claims are checked against the practitioner side of the National Correct Coding Initiative (NCCI), which CMS publishes as a separate table. If your practice is owned by a hospital or runs as a provider-based clinic, ask your billing lead which claim form each service goes out on. That answer decides whether the OCE touches your claims. Our hospital versus professional billing guide explains the split, and our comparison of ASC and hospital outpatient billing covers one place where the two worlds meet.
Specialty does not decide this. A cardiology, pain management or radiology service can be billed on either form depending on where it is delivered and who employs the clinician. If you want to see how billing patterns differ by field, browse our specialty billing pages.
How a claim moves through the OCE
The OCE runs after you submit, not before. A CMS transmittal that installs the editor is addressed to the Medicare shared-system maintainers, who must install it and test it. That is why a provider never opens the OCE in the way a biller opens a scrubber.
What the provider does see is the outcome. Noridian explains that OCE edit numbers map to reason codes, and that providers can view those reason codes and line status indicators in Direct Data Entry (DDE) on the MAC’s portal. The reason code is the practical handle. It tells you which edit fired and which line it fired on.
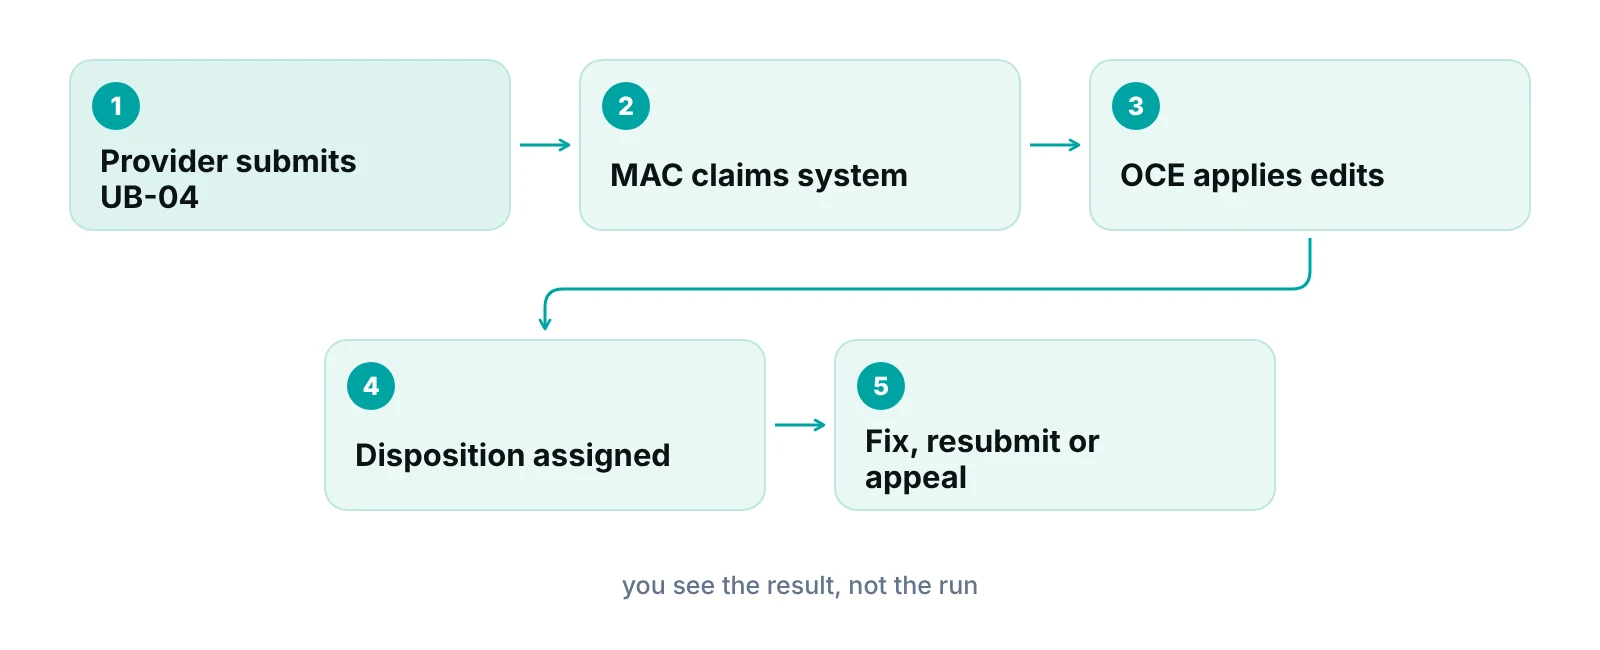
Putting this together, the sequence for one claim is simple. The provider organizes each service into a single claim record and passes it to Medicare. The OCE edits it. Each edit that fires carries a reason code, and the claim leaves the editor with a disposition. The next section explains what each disposition lets you do.
What the OCE can do to a claim
An OCE edit can send a claim down one of several paths, and the path decides what you may do next. The distinction that trips up billing teams most is between rejection and denial: a rejected claim can be corrected and resubmitted but not appealed, while a denied claim cannot be resubmitted but can be appealed.
| Disposition | Resubmit? | Appeal? | Applies to |
|---|---|---|---|
| Claim rejection | Yes, after correction | No | Whole claim |
| Claim denial | No | Yes | Whole claim |
| Return to provider (RTP) | Yes, once problems are corrected | Not stated by CMS in this context | Whole claim |
| Claim suspension | Not returned or paid until the MAC makes a determination | Not applicable | Whole claim |
| Line-item rejection | Yes | No | One line |
| Line-item denial | No for that line | Yes | One line; other lines can still be paid |
Source: Noridian Healthcare Solutions I/OCE and MCE page (2026); CMS Transmittal A-02-001 (OCE claim actions).
Line-item results matter because one bad line does not have to sink the claim. When an edit denies a single line, the claim can still be paid for its other lines. The line that was denied cannot be resubmitted. It can be appealed.
A worked example: the same-day inpatient procedure edit
Noridian’s guidance on reason code W7049 shows how this plays out. W7049 is a line-item denial for an outpatient service billed on the same day as an inpatient procedure. Under OPPS, a HCPCS code with status indicator C is an inpatient procedure, and other outpatient line items on that date are denied.
- What the biller sees: a line-item denial with the narrative about a service on the same day as an inpatient procedure.
- What to check first: the status indicator of every HCPCS code on the claim, using the OPPS addenda CMS publishes each year and quarter.
- If the code was a keying mistake: Noridian says to request a corrected claim through appeals.
- Where to look: Noridian points to the OCE flag status field in the claim’s line detail screen in DDE.
None of this requires reading the OCE specification. It requires a habit: when a reason code appears, find the line, check the code and its status indicator, and decide whether the claim was wrong or the service truly falls under the rule.
An example of the OCE changing: telehealth modifiers
The OCE is not static, and recent changes show the kind of rule it enforces. In the October 2026 release, edit 139 returns to provider a telehealth claim that carries modifier 93 or 95 when the HCPCS code is not on the CMS telehealth list. CMS gives two effective dates: October 1, 2026, and January 1, 2026 for OPPS hospitals and critical access hospitals.
For a billing team, the lesson is practical. The modifier alone does not make a service billable as telehealth. The code has to appear on the CMS list that applies to the date of service. If your organization bills telehealth on UB-04 claims, check that list each quarter, not each year. For the professional-claim side of telehealth, see our telehealth billing guide.
“An edit is only as useful as the habit behind it: read the reason code, find the line, and fix the cause rather than resubmitting the same claim.”
Quarterly updates: what changes and why it matters
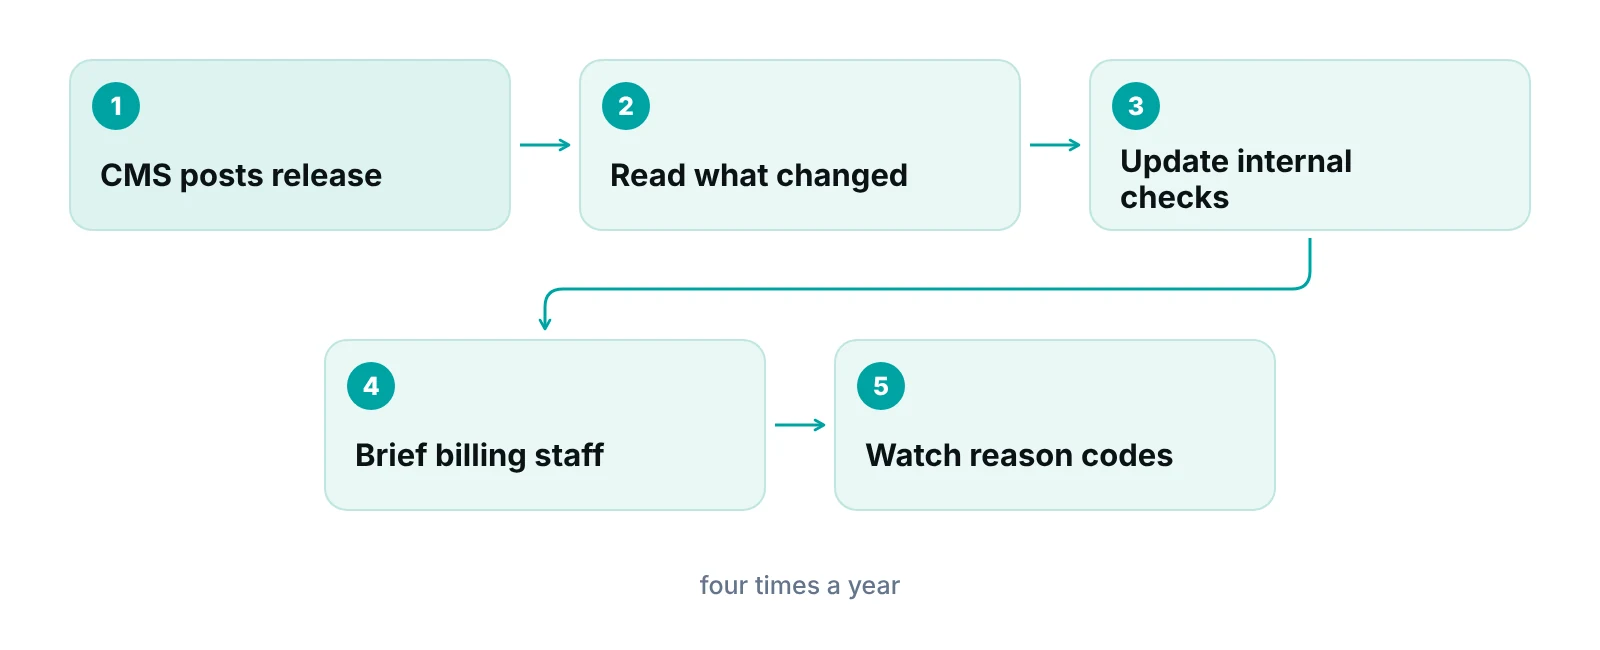
CMS updates the I/OCE every quarter, and each release has a version number and an effective date. The October 2026 update is version 27.3 (Transmittal 13979), issued September 29, 2026, effective October 1, 2026 and implemented on October 5, 2026. It replaces an earlier transmittal from August 20, 2026 to update attachments and add two business requirements.
A release carries two kinds of change. Logic changes alter how an edit behaves. Data changes refresh the tables the edits read. The October 2026 release shows both.
- Logic: new edits 192 and 193 for payer value code issues on suspended lines, and the telehealth change to edit 139 described above.
- Data: fiscal year 2027 ICD-10-CM diagnosis revisions, NCCI version 32.3, and added, deleted and modified HCPCS codes, APCs and status indicators.
- Reason codes: contractors must activate reason codes W7192 and W7193, re-activate reason code 32440, and update reason code narratives.
- History: the software retains 28 prior quarters of programs, with the earliest version included being v21.0, dated January 1, 2020.
Why this affects your denials
Effective dates matter. A claim is edited using the release in effect for its date of service, so a rule change in October can apply to some claims and not others. When a reason code looks new, check the release notes before assuming your staff made an error.
OCE, NCCI, MCE and claim scrubbers: how they differ
These four terms are often mixed up. The OCE and MCE are CMS editors that run in Medicare’s systems. NCCI is a set of coding edits CMS publishes. A claim scrubber is software on your side. CMS says the NCCI has one edit table for physician and practitioner services and one for outpatient hospital services, and that the outpatient hospital procedure-to-procedure edits are in the OPPS Outpatient Code Editor.
| Tool | Claim type | Who runs it | Updates |
|---|---|---|---|
| Outpatient Code Editor (I/OCE) | UB-04 institutional outpatient | Medicare’s claim processing systems | Quarterly |
| Medicare Code Editor (MCE) | UB-04 inpatient | Medicare’s claim processing systems | Quarterly |
| NCCI PTP edits and MUEs | Practitioner and outpatient hospital tables | CMS publishes; applied by Medicare systems and used by billing software | Quarterly files; policy manual yearly |
| Claim scrubber | Any claim your software supports | Your office or billing company, before submission | Depends on the vendor |
Source: CMS NCCI page (2026); Noridian I/OCE and MCE page (2026). The scrubber row describes common practice and is not a CMS statement.
For the code pairs and unit limits behind many edits, see CMS’s NCCI material. Procedure-to-procedure edits stop incorrect code combinations from being paid, and Medically Unlikely Edits (MUEs) stop incorrect units of service. Modifiers such as 59 can affect whether a pair is allowed, and our guide to understanding modifier 59 covers when that is appropriate.
A scrubber cannot run the Medicare OCE for you, because the official edit runs in Medicare’s systems after submission. What a scrubber can do is check the same kinds of problems earlier, so the claim has fewer reasons to return. We explain the process in our claim scrubbing guide and our guide to clean claims.
What to do when an OCE edit fires
Read the disposition first, then the reason code, then the line. The disposition tells you whether you fix and resubmit or appeal. The reason code tells you which edit fired. The line tells you what to correct.
- Identify the disposition. Rejection and return to provider are fixed and resubmitted. A denial is appealed.
- Pull the reason code. In DDE, edit numbers map to reason codes. Write down the code and the line number.
- Check the line’s status indicator and HCPCS code. The OPPS addenda explain what each status indicator means.
- Compare to the chart. Decide whether the claim was keyed wrongly or the service was truly not payable that way.
- Correct or appeal. Use the route the disposition allows, and keep a note of what changed.
- Track the pattern. If the same reason code appears three times in a month, fix the front-end cause, not each claim.
Repeated reason codes are usually a process issue, such as a charge master entry or an intake field. Our guide to medical billing denial management covers how to group denials by cause so the fix happens once.
Not sure which claims the OCE touches?
A free practice audit looks at which claim forms your services use and where your returns and denials start. Pricing, if you want help afterward, is quoted after the audit.
Our recommendations
- Map each service to its claim form. List every service line your organization bills and mark whether it goes out on a UB-04 or the professional claim form. That list tells you whether the OCE applies, and which edit set to study.
- Schedule a quarterly edit review. CMS updates the editor four times a year. Put the release on a calendar, read the transmittal summary, and brief the billing team on any logic change that touches your services.
- Log reason codes, not just denial counts. A count of denials does not show which edit fired. Record the reason code and line for every OCE result so patterns show up.
- Check status indicators before billing unusual combinations. Same-day inpatient and outpatient services, packaged services and procedures with status indicator C are common sources of line-item denials. A short check before submission is cheaper than an appeal.
- Keep telehealth lists current by date of service. If your claims carry modifier 93 or 95, check the CMS telehealth list for the date of service every quarter and pair it with your payer rules.
- Separate documentation questions from edit questions. The OCE reads claim data only. If the question is whether a note supports a code, that is a coding and compliance review, not an edit problem.
Bottom line
The outpatient code editor is a CMS program inside Medicare’s systems, not a tool a practice installs. It matters most to organizations that bill outpatient services on UB-04 claims, and it changes every quarter. If your claims are coming back with OCE reason codes, our medical billing services and denial management services can help you trace each one to its cause, and the revenue calculator gives a rough view of what unresolved denials cost you.
Frequently asked questions
What does OCE stand for in medical billing?
OCE stands for Outpatient Code Editor. CMS now calls the current program the Integrated Outpatient Code Editor, or I/OCE. It edits institutional outpatient claims in Medicare’s claim processing systems and assigns payment information such as APCs and status indicators.
Does a physician practice use the OCE?
Usually not directly. CMS describes the OCE as an editor for UB-04 institutional outpatient claims, such as those from hospital outpatient departments. Practices billing on the professional claim form are checked against the practitioner NCCI edits. A hospital-owned clinic may bill on either form, so confirm with your billing lead which form each service uses before assuming the OCE does or does not apply to you.
How often is the OCE updated?
Quarterly. The most recent release, version 27.3, is effective October 1, 2026. Each release can change edit logic and refresh the code tables the edits use, including ICD-10-CM, HCPCS, APCs and status indicators.
What is the difference between the OCE and the MCE?
Both are CMS code editors for UB-04 claims. The OCE handles institutional outpatient claims. The MCE is the inpatient code editor. Both receive quarterly updates, so a hospital may deal with each depending on the type of claim. CMS also publishes a comparison document listing each year’s quarterly changes to the MCE, which helps when you need to see what moved between releases.
Can I run the OCE before I submit a claim?
The official edit runs inside Medicare’s systems after submission. Your billing software may check similar problems earlier. A claim scrubber does this, but it is separate from the CMS editor and cannot replace the result Medicare assigns. Ask your software vendor what it checks and how often it updates its rules, since a scrubber is only as current as its last update.
What is the difference between a rejection and a denial?
A rejected claim can be corrected and resubmitted but cannot be appealed. A denied claim cannot be resubmitted but can be appealed. Single lines can also be rejected or denied while other lines on the same claim are paid.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Integrated Outpatient Code Editor (OCE) and Medicare Code Editor (MCE) — Noridian Healthcare Solutions (Medicare Part A MAC) (2026)
- October 2026 I/OCE Specifications Version 27.3, Transmittal 13979 (CR 14594) — CMS (2026)
- Transmittal A-02-001, OCE claim actions — CMS (2002)
- Reason Code W7049 — Noridian Healthcare Solutions (2026)
- National Correct Coding Initiative (NCCI) Edits — CMS (2026)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. CPT is a trademark of the American Medical Association. CMS updates the OCE every quarter, and payer and contractor rules vary. Check current CMS and MAC sources before you rely on any edit result.
