

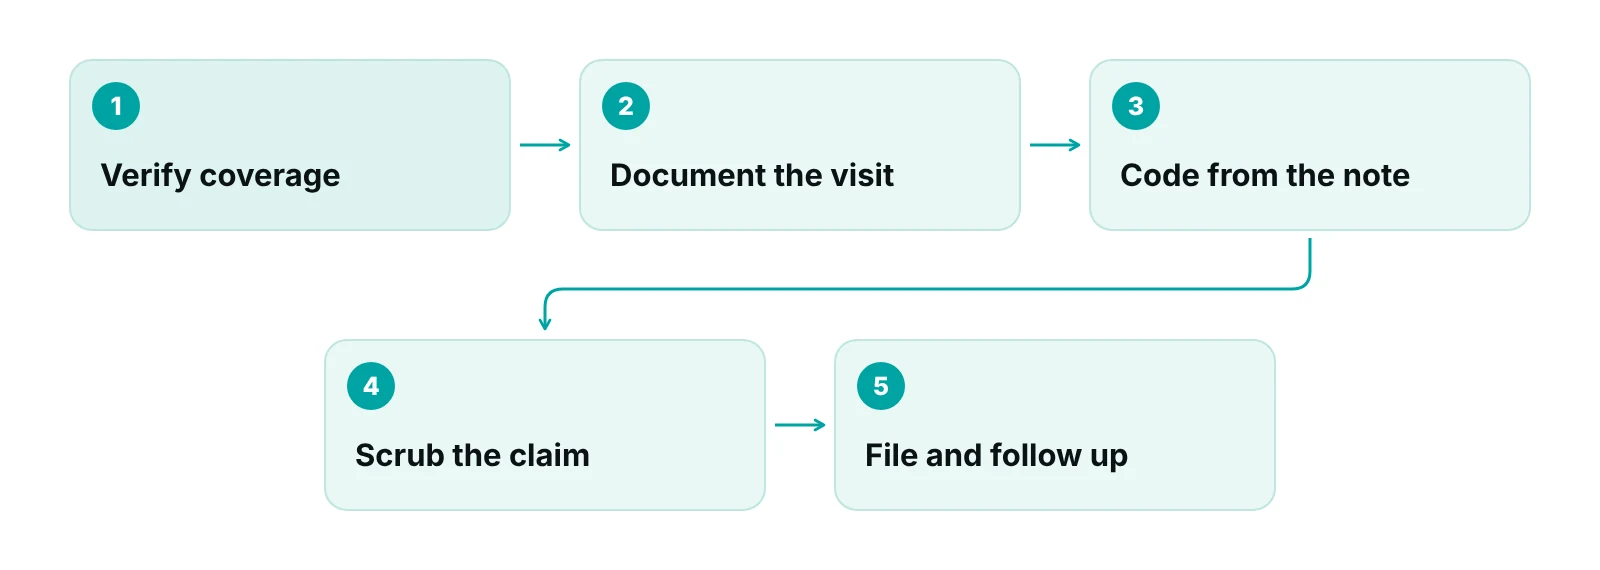
The common medical billing mistakes are wrong or missing patient data, unverified coverage, incomplete claims, thin documentation, coding errors, upcoding, late filing and unworked denials. Most start before the claim exists, so the fix is a checkpoint at each step: verify, document, code, scrub, file on time, then work every denial.
If claims keep coming back, the cause is rarely one big error. It is usually a handful of small, repeatable ones. This guide lists the eight we see most, shows where each begins, and separates what public data supports from the round numbers that circulate without sources.
Key takeaways
- Most billing errors start at registration, scheduling or documentation, not at claim submission.
- Public denial figures cover specific payers or programs. Measure your own first-pass denial rate by reason.
- Upcoding means billing above what the record supports. It is different from billing for services not provided.
- Medicare claims generally must be filed within one calendar year of the date of service. Other payers set their own limits.
What counts as a billing mistake, and what the data says
A billing mistake is any error between scheduling and payment that makes a claim late, wrong or unpayable. Some show up as payer denials. Others only show up later, as audit findings. Public data mixes these together, so be careful which number you quote and what it actually measures.
For Medicare fee-for-service, CMS estimated the fiscal year 2025 improper payment rate at 6.55%, or $28.83 billion, down from 7.66% and $31.70 billion in fiscal year 2024 (CMS). An improper payment is not the same as fraud. CMS says improper payment measurement is not a measure of fraud. Its claim-review program sorts errors into no documentation, insufficient documentation, medical necessity, incorrect coding and other (CMS CERT overview).
On the commercial side, KFF analyzed 2023 plan-year data for HealthCare.gov marketplace plans. About 20% of in-network claims were denied, roughly 86 million of 436 million, and the rate ranged from 1% to 54% across insurers (KFF). That is one market segment, not a national denial rate for every payer. It does show that the same claims can be paid or denied very differently depending on the payer.
| Measure | Figure | Year | What it tells you |
|---|---|---|---|
| Medicare fee-for-service improper payment rate | 6.55% ($28.83 billion) | FY 2025 | Compliance with Medicare rules, not a fraud rate. FY 2024 was 7.66% ($31.70 billion). |
| ACA marketplace in-network claims denied | About 20% (86 million of 436 million) | 2023 | Marketplace plans only. Insurer rates ranged from 1% to 54%. |
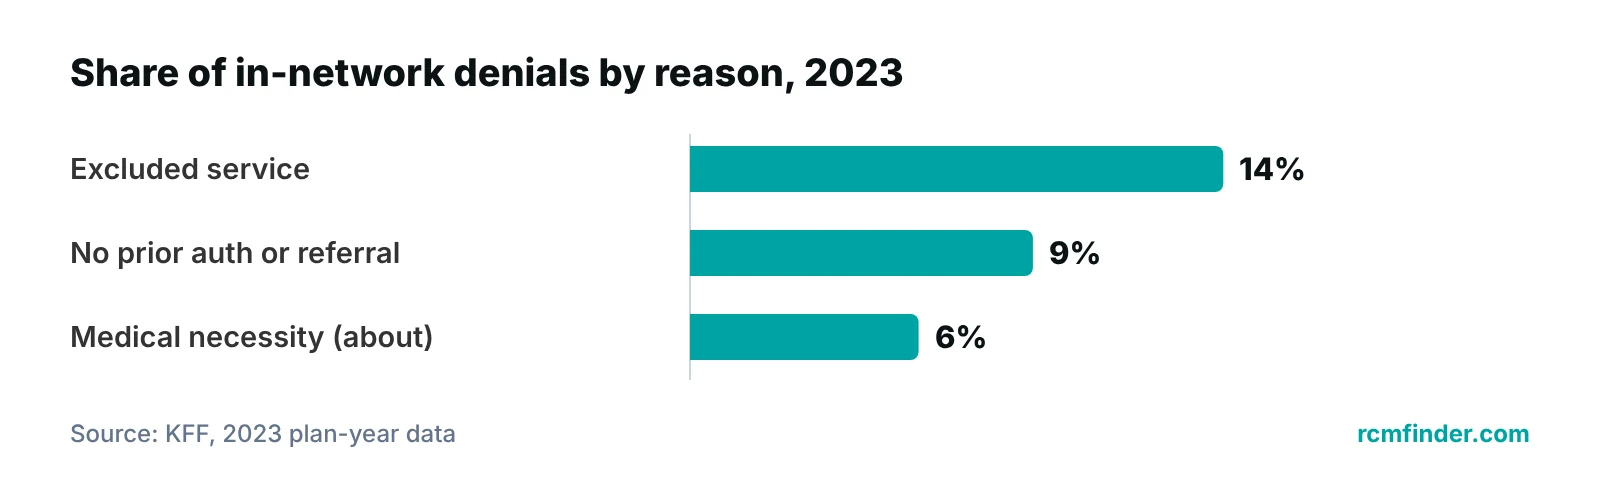
| Share of in-network denials: excluded service | 14% | 2023 | A coverage check before the visit can flag benefit exclusions. |
| Share of in-network denials: no prior authorization or referral | 9% | 2023 | A process gap that starts at scheduling. |
| Share of in-network denials: medical necessity | About 6% | 2023 | Often tied to diagnosis, documentation and payer policy. |
| Denied in-network claims that consumers appealed | 376,508 appeals; insurers upheld 56% | 2023 | Appeals were under 1% of denials. These are consumer-filed appeals, not provider appeals. |
Source: CMS (FY 2025 improper payments fact sheet); KFF (Claims Denials and Appeals in ACA Marketplace Plans in 2023, data updated September 2025)
Be careful with round-number statistics
You will see claims such as “X% of claims are denied” or “coding causes most denials” repeated across billing blogs without a traceable primary source. We left them out. If a number does not link to the agency, survey or dataset that produced it, do not build a budget on it. The most useful number is your own first-pass denial rate, broken down by reason.
Front-end mistakes: patient data and coverage
The first two common medical billing mistakes happen before the patient is seen. They are cheap to fix at the front desk and expensive to fix after the claim is denied.
1. Wrong or missing patient and insurance data
A misspelled name, a wrong date of birth, an old member ID or the wrong subscriber can stop a claim before anyone reviews the care. Payers check claim data against their own records, so a mismatch can mean a rejection or a denial. Prevention is routine: scan the card and photo ID at every visit, read the demographics back to the patient, and update the record when anything changes.
2. Coverage and authorization not checked
Checking eligibility and benefits before the visit tells you whether the plan is active, whether the service is covered and whether an authorization or referral is needed. In KFF’s 2023 marketplace data, 14% of in-network denials were for an excluded service and 9% were for no prior authorization or referral (KFF). Those are the kinds of gaps a pre-visit check is built to catch. Verify when the visit is booked and again close to the date, because coverage can change in between. Our insurance verification guide walks through what to confirm.
Coding and documentation mistakes
Four common medical billing mistakes sit between the visit and the claim: incomplete claim data, thin documentation, wrong codes and upcoding. They are separate problems, and they need separate checks.
3. Missing or incomplete claim information
A claim that leaves out a required field, such as a referring provider, an authorization number or a place of service, can be returned or denied for missing information. A claim scrubber checks required fields and common edit rules before submission, so the team fixes the claim while it is still in your hands. See our claim scrubbing guide for how that review works.
4. Documentation that does not support the claim
In Medicare’s review program, “insufficient documentation” means the records do not show whether the claim was payable, for example when a required element such as a test order is missing (CMS CERT overview). Payers review records the same way. If the note does not support the service, the claim is exposed to a denial or a recoupment. Give coders a simple way to query the provider before billing, and keep a template for the elements your highest-volume services need.
5. Incorrect coding
CMS describes incorrect coding as cases where the documentation supports a different code, provider or site of service than the one billed, or where a service was unbundled (CMS CERT overview). Modifier use is a common trouble spot. The AMA lists modifier 25 misuse among audit-risk missteps, such as adding it to an E/M service that was not significant or not separately identifiable (AMA). Our comparison of modifiers 25 and 59 explains when each one applies. Code from the note, not from habit or the superbill, and review a sample of each coder’s claims regularly.
6. Upcoding
Upcoding is billing a code that describes a more severe illness or a more expensive service than the record supports (AMA). It is not the same as billing for a service that was never provided. Both are serious, but they are different errors. A practice can upcode by habit, for example by defaulting to a higher visit level, with no intent to deceive, and still carry the risk.
A recent example: in October 2025, the University of Texas Health Science Center at Houston agreed to pay $390,853.86 to resolve civil monetary penalty allegations from a self-disclosure. OIG alleged that E/M visits were billed at level 4 or 5 when a lower level applied, and that E/M services were billed on some visits that involved only a procedure (HHS OIG). Separately, the DOJ’s 2025 False Claims Act penalty range is $14,308 to $28,619 under 31 U.S.C. 3729(a)(1), assessed after July 3, 2025, and that is only one component alongside damages (Federal Register). Our upcoding guide covers how audits look at pattern data.
Specialty rules change the details
E/M levels, bundling edits and modifier rules do not work the same way in every specialty. A cardiology group and a behavioral health group fail in different places. Our specialty billing pages show the billing patterns we plan around for each one.
Back-end mistakes: filing late and not working denials
The last two common medical billing mistakes cost money even when the claim was clean: filing too late and leaving denied or unpaid claims alone.
7. Late claim submission
For Medicare, a claim must generally be filed no later than the close of the period ending one calendar year after the date of service. Exceptions are narrow, such as an error by a federal agent or contractor, or retroactive Medicare entitlement (42 CFR 424.44, eCFR). Commercial payers and state Medicaid programs set their own limits, so read each contract. Do not plan around the deadline. Set a shorter internal target and watch the gap between date of service and claim sent.
8. No follow-up on denials and unpaid claims
A denial that nobody works is revenue you have already earned and then written off by default. KFF’s data shows how rarely denials are challenged: consumers appealed 376,508 of about 86 million denied in-network marketplace claims, under 1%, and insurers upheld 56% of those denials (KFF). Those are patient appeals, not provider appeals, so do not read them as your appeal odds. They do show that denial volume is large and challenge volume is small. Assign every denial an owner, a reason and a due date. The denial management guide and our accounts receivable guide cover the work queue in detail.
How to prevent them: one checkpoint at each step
Prevention works best as a short list of checkpoints, each with one owner, not as a yearly training session. Put a check at every point where a claim can go wrong, and measure what the check catches.
| Mistake | Where it starts | Checkpoint that catches it | What to track |
|---|---|---|---|
| Wrong patient or insurance data | Check-in and registration | Card and ID scan; read-back of demographics | Rejections for demographic mismatch |
| Coverage or authorization not checked | Scheduling | Eligibility and benefits check at booking and before the visit | Denials for eligibility, exclusions, no authorization |
| Missing claim information | Charge entry | Claim scrubber and required-field edits | Claims held or returned for missing data |
| Documentation gaps | Clinical note | Provider query before billing; note templates | Denials and records requests tied to documentation |
| Incorrect coding | Coding | Code from the note; sample audit by coder | Coding-related denials and coder error rate |
| Upcoding | Visit-level defaults | Periodic E/M level review against the note | Distribution of visit levels by provider |
| Late filing | Charge lag | Daily unbilled-charge report; internal filing target | Days from service to claim sent |
| No follow-up | Remittance and A/R | Denial work queue with owner and due date | Denials worked, overturned and left open |
Source: RCM Finder operating checklist, a practical framework. It is not a regulatory requirement.
Notice that every checkpoint produces a number you can review each week. If a step has no number, nobody can tell whether it is working.
Not sure which of these mistakes is costing you the most?
Our free practice audit reviews your denial reasons and claim flow and points to where the errors begin. Pricing is quoted after the audit.
Fix it in-house, with software, or with a billing partner
You can fix these mistakes with your own team, with software, with a billing partner or with a mix. The right choice depends on where your errors are, not on a general rule. Start by sorting your last quarter of denials by reason. If most trace to the front desk, that is a staffing and process problem. If most trace to coding or follow-up, that is where outside help pays off.
| Approach | Works best when | You keep | Watch for |
|---|---|---|---|
| In-house team | Errors are few and concentrated in one step | Full control and direct access to providers | Turnover, training time and no backup for sick days |
| Software only (scrubber, clearinghouse) | Errors are data-entry or formatting problems | Your current team and workflow | Alerts that nobody owns; software does not work denials |
| Hybrid (you bill, a partner works denials and A/R) | Claims go out clean but denials pile up | Charge entry and coding control | Clear handoff rules and shared reporting |
| Full outsourcing | Volume or staffing makes in-house billing hard to sustain | Provider documentation and oversight | Vendor transparency: ask for reports, access and a Business Associate Agreement |
If you decide to get help, our medical billing services cover charge entry, coding support, claim scrubbing and submission. Our team works inside your existing EHR, for example PrognoCIS, eClinicalWorks or athenahealth. You can also estimate what unworked claims may be costing you with the revenue calculator.
Put a number on unworked claims
Enter your own volume and denial figures in the revenue calculator to see what the gap could be worth to your practice.
Our recommendations
- Measure your own first-pass denial rate by reason. We start every review here. Pull 90 days of denials, tag each by reason, and rank them. Fix the top reason first, not the one that feels worst.
- Verify coverage twice. We recommend one check when the visit is booked and one a few days before. Record the result, including any authorization number, in the account.
- Give coders a way to query providers. A coder should never guess. A short query form, answered within the day, prevents most guesswork and protects both sides in an audit.
- Scrub every claim before it leaves. Run claims through a scrubber or a manual checklist, and review what it flags each week. A flag that is always ignored is a flag that needs fixing.
- Set an internal filing target. Pick a target well inside your shortest payer limit and report the gap between service date and claim date every week.
- Work every denial with an owner and a due date. Log the reason code, the root cause and the outcome. Review the log monthly and push the causes back to the front desk, coders or providers.
Many billing mistakes start as missing data at charge entry.
The portal runs data-completeness checks before a claim is submitted and applies specialty-aware billing logic to each claim.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Most common medical billing mistakes are process gaps you can trace, count and close, one checkpoint at a time. If denials and rework are taking your team’s time, our denial management services and medical billing services can take that queue off your desk. Start with a free practice audit, or talk to us.
Frequently asked questions
What are the most common medical billing mistakes?
The most common are wrong patient or insurance data, unverified coverage, missing claim information, documentation that does not support the service, incorrect coding, upcoding, late filing and no follow-up on denials. Most start before the claim exists, which is why checkpoints at registration, coding and scrubbing work better than fixing denials afterward.
What is the difference between upcoding and billing for services not provided?
Upcoding is billing a code for a higher level of service, or a more severe condition, than the record supports. Billing for services not provided is billing for care that never happened. Both create compliance risk, but they are different errors, and a practice can upcode through habit without intending to.
How long do I have to file a Medicare claim?
Generally, the claim must be filed by the close of the period ending one calendar year after the date of service, under 42 CFR 424.44. A few exceptions exist, such as agency error. Commercial payers and Medicaid set their own limits, so check each contract and state rule.
Does a Medicare improper payment mean fraud?
No. CMS states that improper payment measurement is not a measure of fraud. An improper payment can come from missing documentation, a medical necessity finding or a coding error. Fraud is a separate legal question, and a billing error alone does not prove it.
How do I find out which billing mistakes are costing my practice the most?
Pull a recent period of denied and returned claims and tag each one by reason: eligibility, authorization, missing information, documentation, coding or timing. Rank the reasons by count and by dollars. The top one or two usually point to the step that needs a checkpoint first. Repeat the exercise every month so you can see whether a new check is working.
When should a practice outsource billing instead of fixing it in-house?
Consider outside help when errors keep recurring after you have added checks, when you cannot staff billing reliably, or when denials pile up with nobody to work them. A hybrid model, where a partner handles denials and A/R, is a lower-risk first step than outsourcing everything. Whatever you choose, ask for weekly reporting and for a Business Associate Agreement before any patient data is shared.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Fiscal Year 2025 Improper Payments Fact Sheet — CMS (2026)
- Introduction to the Comprehensive Error Rate Testing (CERT) program — CMS (2025)
- Claims Denials and Appeals in ACA Marketplace Plans in 2023 — KFF (2025)
- 42 CFR 424.44 Time limits for filing claims — eCFR (2026)
- UT Health Science Center at Houston agreed to pay $390,853.86 (upcoded E/M claims) — HHS OIG (2025)
- Avoid these missteps to slash your medical coding audit risk — AMA
- Civil Monetary Penalty Inflation Adjustments (DOJ), 90 FR, July 3, 2025 — Federal Register (DOJ) (2025)
Disclaimer: This post is general educational information about revenue cycle operations. It is not legal, coding, billing-compliance or financial advice. Payer rules, filing limits and penalty amounts vary and change over time. Confirm requirements with the payer and qualified advisors before acting.
